IV Therapy For Pregnancy: What Actually Gets Done In The Clinic
Most people asking about IV therapy for pregnancy are dealing with morning sickness that won't quit, or they're just trying to keep up with hydration demands in the second trimester. I've run the protocols, adjusted them when standard mixes caused problems, and written out enough prescriptions to know what works without causing trouble. It's straightforward stuff when you skip the wellness-center marketing language and look at what the actual infusions contain. The typical setup for pregnancy-related IV therapy is a custom hydrating solution with added vitamins and anti-nausea medication. The base is usually half-normal saline or normal saline, depending on the patient's blood pressure and fluid status. From there you add B-complex vitamins, magnesium, calcium, and sometimes an antiemetic like ondansetron or metoclopramide. The Myers cocktail gets referenced a lot online, but I don't use it unchanged for pregnant patients because the vitamin K and some other components aren't ideal in standard doses during pregnancy. I adjust each bag individually based on lab work and symptoms.
When Iv Therapy For Pregnancy Makes Sense And When It Doesn't
I'll tell you where this actually helps and where it's overused. Hyperemesis gravidarum is the clearest indication. If a pregnant patient can't keep down fluids for more than 24 to 48 hours, is losing weight, and showing signs of dehydration like ketonuria or elevated BUN-to-creatinine ratio, IV hydration is not optional. Oral rehydration fails in these cases because the stomach won't tolerate it. You see rapid improvement within the first hour of infusion — urine output increases, nausea drops, and the patient can usually start taking oral fluids again afterward. That's the window where the IV does its job. Beyond that, the evidence gets thin. People chase the vitamin boost and the energy claims, but a balanced diet covers most of what goes into these bags. If someone is nutritionally adequate and just wants the perceived wellness benefit, you're spending money for a placebo effect and the inconvenience of an IV stick. I see patients come in already dehydrated from poor intake, and I treat that directly. The diagnosis matters more than the brand of vitamins being pushed. There are specific edge cases where IV therapy becomes necessary even outside hyperemesis. A patient with a history of kidney stones who gets dehydrated easily needs aggressive hydration that's hard to maintain orally. Someone with a thiamine deficiency from prolonged vomiting — this one I caught recently with a patient who was fatigued, had mild confusion, and was otherwise recovering from hyperemesis. We missed the thiamine part initially because we were focused on fluid replacement alone. She wasn't getting better despite adequate hydration and antiemetics. I ordered a thiamine level, it came back low, and we added B1 to the next infusion. Symptoms resolved within two days. That's the kind of thing you learn through repeated exposure, not from reading a pamphlet.
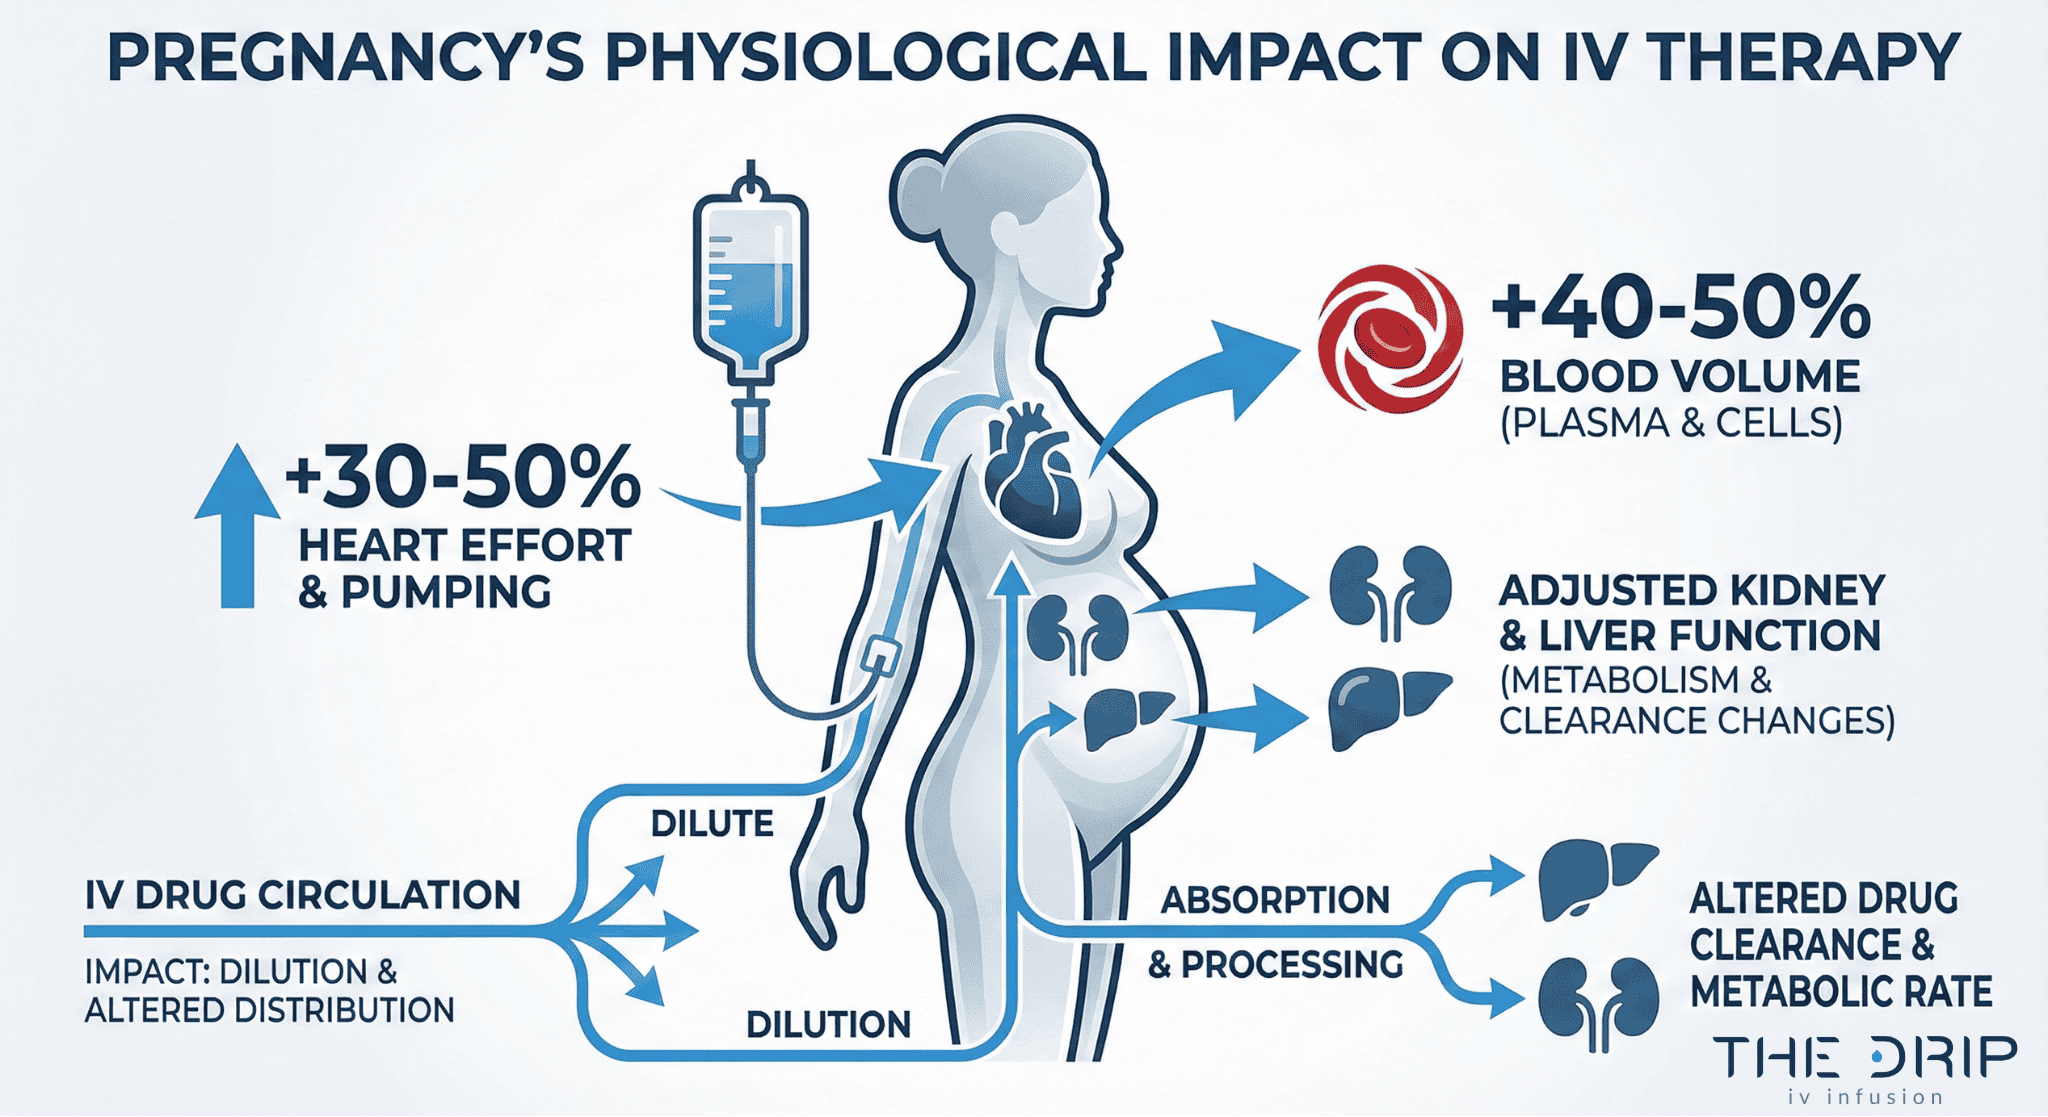
Fluid selection matters more than most clinics admit. Normal saline versus half-normal saline is not a trivial choice. A patient with borderline hypertension or preeclampsia risk gets half-normal saline to avoid unnecessary sodium load. The difference is about 154 milliequivalents of sodium per liter between the two solutions, and over multiple infusions that adds up. I track cumulative sodium intake across all IV sessions a patient receives during pregnancy because it affects fluid balance and blood pressure management. Additive dosing is another area where clinics cut corners. Magnesium sulfate for seizure prophylaxis in preeclampsia follows a completely different protocol than the magnesium chloride or magnesium gluceptate added for general repletion. The former is a high-dose acute intervention; the latter is a maintenance supplement. Mixing these up causes real problems. I've seen post-infusion labs show magnesium levels that were either too low to be therapeutic or too high to be safe, depending on which formulation was used and at what dose. Standard repletion doses run about 1 to 2 grams of elemental magnesium per infusion, split across sessions if needed. Acute seizure prophylaxis starts with a 4 to 6 gram loading dose followed by continuous infusion. These are not interchangeable.
Get the Full Details
What To Expect During An Actual Infusion Session
The process itself takes about 45 minutes to an hour for a standard hydration bag with additives. The IV site gets prepped, the catheter is placed, and the bag is hung. You monitor the patient for the first 15 minutes closely because that's when most acute reactions happen. If there's no reaction, you can relax a bit, but you stay within sight of the patient the whole time. Common complaints during the infusion are coldness at the injection site, a metallic taste if zinc or certain B vitamins are included, and mild dizziness from the fluid volume moving through the system. These are uncomfortable but not dangerous. I tell patients upfront about the metallic taste so they don't panic when it hits. Most stop noticing it after a few minutes anyway. There's one complication I run into more often than I'd like to admit. Some pregnant patients have veins that collapse easily under the flow rate of a standard IV setup. The veins in the antecubital fossa are the usual target, but pregnancy changes venous tone and vessel fragility. I switch to a smaller gauge catheter — 22 gauge instead of the usual 20 — and slow the initial flow rate for the first 10 minutes. This prevents the vein from rolling or collapsing mid-infusion. The trade-off is a slightly longer administration time, but it's better than restarting the IV halfway through.
Monitoring during and after the infusion includes checking blood pressure, heart rate, and oxygen saturation at baseline, at 30 minutes, and at completion. For patients with any history of cardiac issues or preeclampsia, I add a post-infusion weight check to assess fluid balance. The average bag delivers 500 to 1000 milliliters of fluid, and the body handles that differently depending on gestational age and existing fluid status. A patient in her first trimester with three days of vomiting handles a liter differently than someone in her third trimester with normal hydration. The same bag, different clinical picture.
Practical Limitations And Where This Approach Fails
IV therapy is not a solution for poor nutrition long-term. You can infuse vitamins and minerals all week, but if the patient's diet doesn't change, the deficiency returns. I've had patients come back for weekly infusions month after month without addressing the underlying dietary issue. It's a bandage, and everyone knows it, including the patient. I stop seeing them for this if they won't also work on oral intake and supplement compliance. Cost is another factor worth mentioning. A single IV therapy session for pregnancy ranges from $150 to $400 depending on location, additives, and whether insurance covers it. Most insurance plans do not cover elective IV hydration for pregnancy-related nausea unless it's documented hyperemesis gravidarum with supporting lab work. That documentation requires specific criteria: weight loss greater than 5 percent of pre-pregnancy weight, ketonuria, and electrolyte abnormalities. Without those, you're paying out of pocket. The frequency question comes up constantly. I don't recommend more than one infusion per week for routine cases, and even that is aggressive for most patients. Two to three sessions in the first trimester is a typical range for hyperemesis, then taper based on response. Going beyond that usually means the underlying issue isn't being addressed, or the patient is developing a psychological dependence on the infusion rather than building sustainable oral intake habits.

One thing nobody talks about is the risk of infection at the IV site. Pregnancy suppresses certain immune functions slightly, making patients more susceptible to local infections. I check every IV site at each visit for redness, warmth, or swelling before starting. If there's any sign of phlebitis, I move to a different site or delay the infusion until it resolves. Skipping this check has caused minor infections in my practice, and one case that required oral antibiotics. It was preventable with basic inspection. The timing within pregnancy also influences outcomes. First trimester infusions address acute symptoms and often provide the most relief because this is when nausea and vomiting peak. Second and third trimester infusions are less about nausea and more about maintaining hydration and nutrient levels as the growing fetus places higher demands on the mother's systems. The approach shifts accordingly, and so do the additive choices. More focus on iron and calcium in later trimesters, less on antiemetics unless symptoms persist.