IV Therapy For Sickle Cell Anemia: What Actually Happens in Practice
Sickle cell disease is a chronic hemolytic condition caused by a point mutation in the beta-globin gene, resulting in hemoglobin S. When oxygen tension drops, these abnormal red blood cells polymerize and take on a rigid sickle shape, which can block blood flow through small vessels. This is called a vaso-occlusive crisis, and it is the primary reason people with sickle cell end up in the hospital. IV therapy is one of the standard treatments used during these episodes. The most common scenario is hydration. Patients present with severe pain, often unable to drink enough to stay properly hydrated because of nausea, mouth sores, or just general misery. IV fluids are started to restore intravascular volume and help flush the system. Normal saline at 0.9% is the standard choice, running at a rate that maintains urine output without overloading the patient. The goal is roughly one and a half times the maintenance rate, adjusted based on age, weight, and cardiac function. You need to watch the patient closely if they have a history of heart issues or kidney problems because fluid overload is a real risk.
Iv Therapy For Sickle Cell Anemia
Pain management is usually the second component. Opioids are the standard, and the route matters. IV administration works faster than oral, which matters when someone is in acute distress. Hydromorphone, morphine, and fentanyl are commonly used. The key is dosing correctly from the start rather than chasing pain with incremental top-ups, which tends to leave patients in too much discomfort for too long. There is a specific edge case that catches people off guard. Some patients develop paradoxical worsening of their pain when given large volumes of hypotonic fluids like D5W or half-normal saline. This happens because water moves into the sickled cells, causing them to swell further and become even less deformable. I ran into this with a patient who was getting D5 1/2 NS at a decent rate and still complaining of worsening bone pain despite being on opioids. Switching to isotonic normal saline and slowing the rate while monitoring output brought relief within a few hours. It is a small detail that can make a big difference in outcomes. Beyond hydration and analgesia, there are other IV medications that may be used depending on the situation. Antibiotics are not routine unless there is evidence of infection, which is common because sickle cell patients are functionally asplenic and more vulnerable to certain organisms. Hydroxyurea is an important disease-modifying drug but it is oral, not IV. Blood transfusions are another consideration in severe cases, particularly for acute chest syndrome or stroke prevention, though this is more complex and requires careful matching to avoid iron overload and alloimmunization.
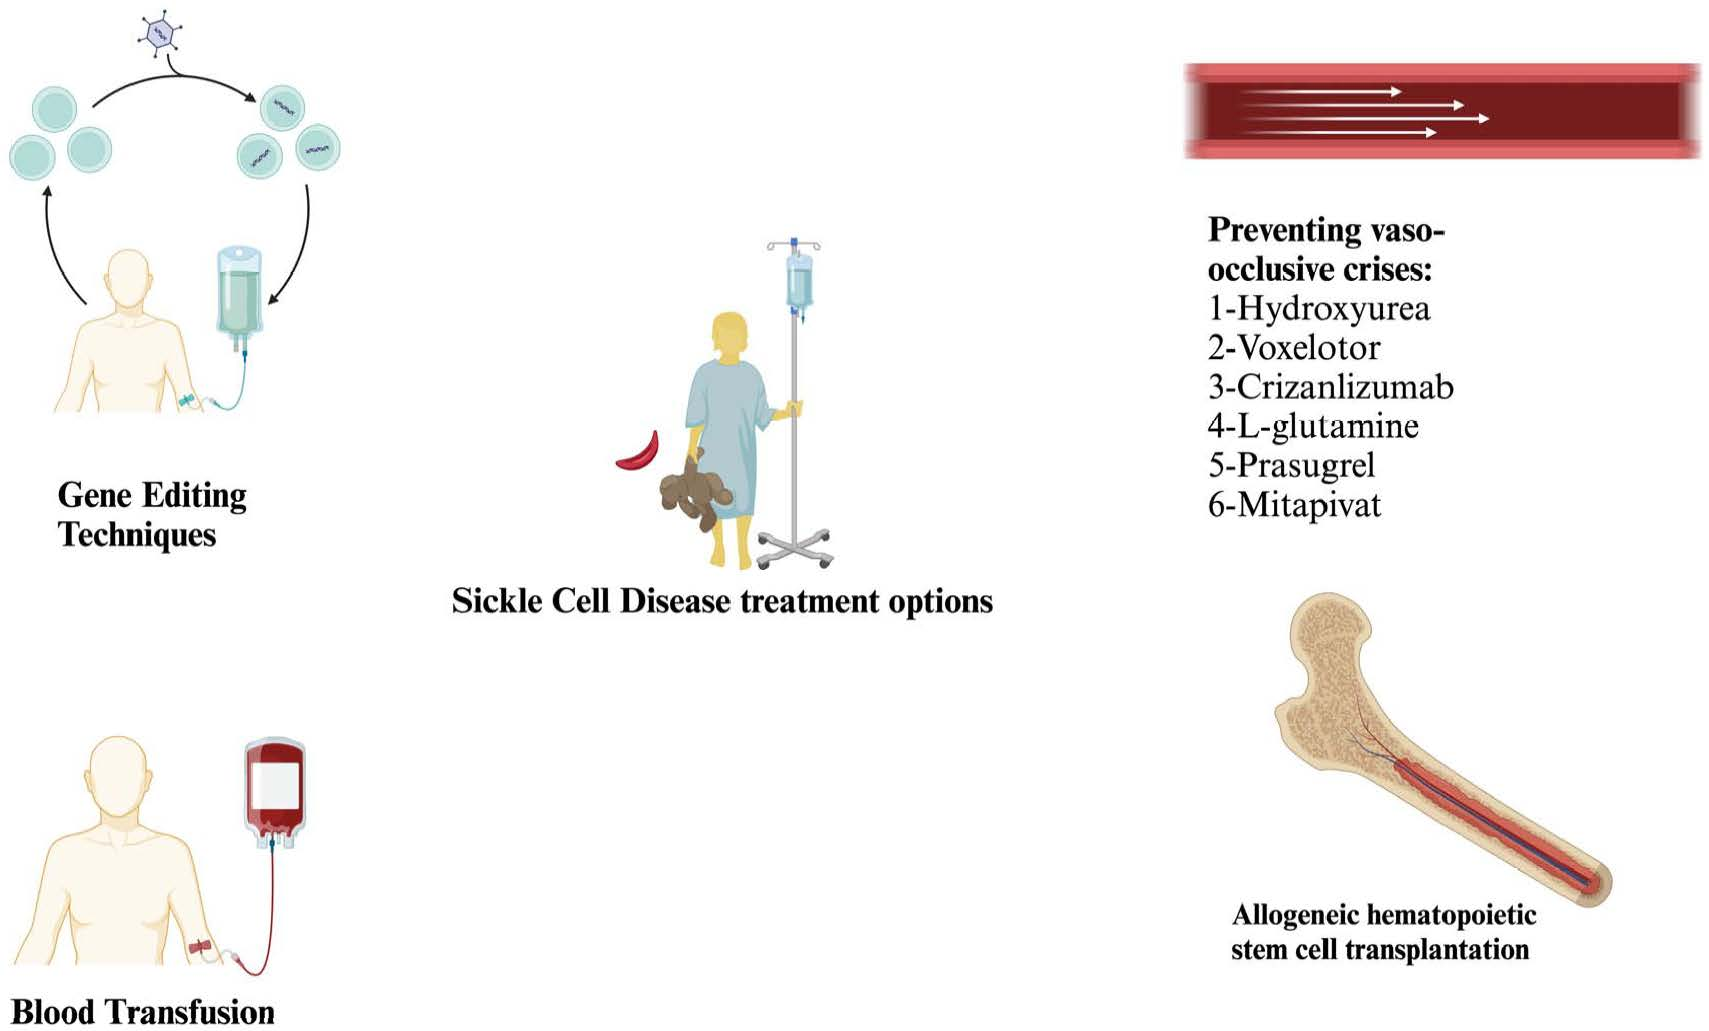
One counter-intuitive point that beginners miss is that IV therapy alone does not treat the underlying sickling process. It manages the symptoms and complications of a crisis. The real work of reducing how often crises happen lies in disease-modifying therapies like hydroxyurea, chronic transfusion programs, or newer agents like voxelotor and crizanlizumab. IV fluids in the emergency department or hospital are about stabilization, not cure. Another nuance involves electrolyte management. Sickle cell patients can lose potassium through the urine, especially during recovery phases when cells are being replaced. Hypokalemia can worsen pain perception and cause cardiac arrhythmias. Checking basic metabolic panels during treatment and replacing potassium as needed is standard practice that is sometimes overlooked in busy settings. The limitations of IV therapy are worth stating plainly. It does not work for everyone. Some patients have poor venous access due to repeated prior lines, which slows treatment down. Others do not respond well to standard opioid protocols and may need alternative approaches or specialist consultation. In some cases, the crisis is driven by factors that IV fluids and pain meds cannot address, such as a pulmonary embolism or sepsis, and delaying proper diagnosis in those situations is dangerous. If IV therapy is not helping after an adequate trial, further investigation is necessary rather than simply increasing the dose of pain medication.
Get the Full Details
In practice, the best approach combines prompt IV access, appropriate fluid resuscitation with isotonic solutions, timely and adequate analgesia, and continuous monitoring for complications. It is straightforward in theory but requires attention to detail because sickle cell disease presents differently in every patient.