Getting Your IV Vitamin Formulas Right the First Time
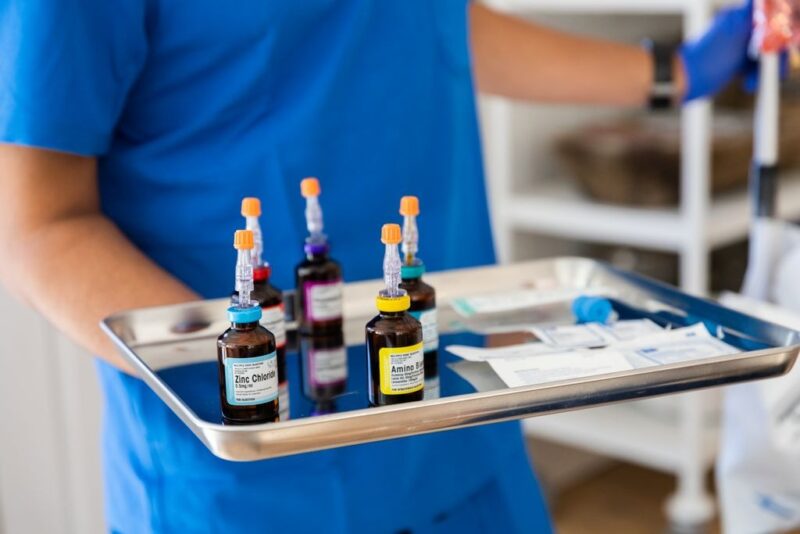
Most people coming into compounding pharmacy with IV vitamin therapy don't realize how different this is from oral compounded suspensions. The margin for error is thinner, the sterility requirements are non-negotiable, and the regulatory scrutiny has gotten much heavier over the last five years. I've watched pharmacies pivot into this space and burn through batches because they treated it like regular compounding with extra steps. The basic workflow starts with choosing your base solution, typically 0.9% sodium chloride or 5% dextrose in water depending on the vitamins involved. You then pull active pharmaceutical ingredients from sterile sources — not the bulk powder from a regular compounding supplier. The difference matters because the endotoxin testing requirements change entirely when you're working with injectable-grade material. I spent three weeks last year tracking down a supplier for pharmaceutical-grade ascorbic acid that actually had a COA with particulate matter data under 25 microns. Without that documentation, your USP <797> audit will flag you immediately.Iv Vitamin Therapy Compounding Pharmacy Workflow
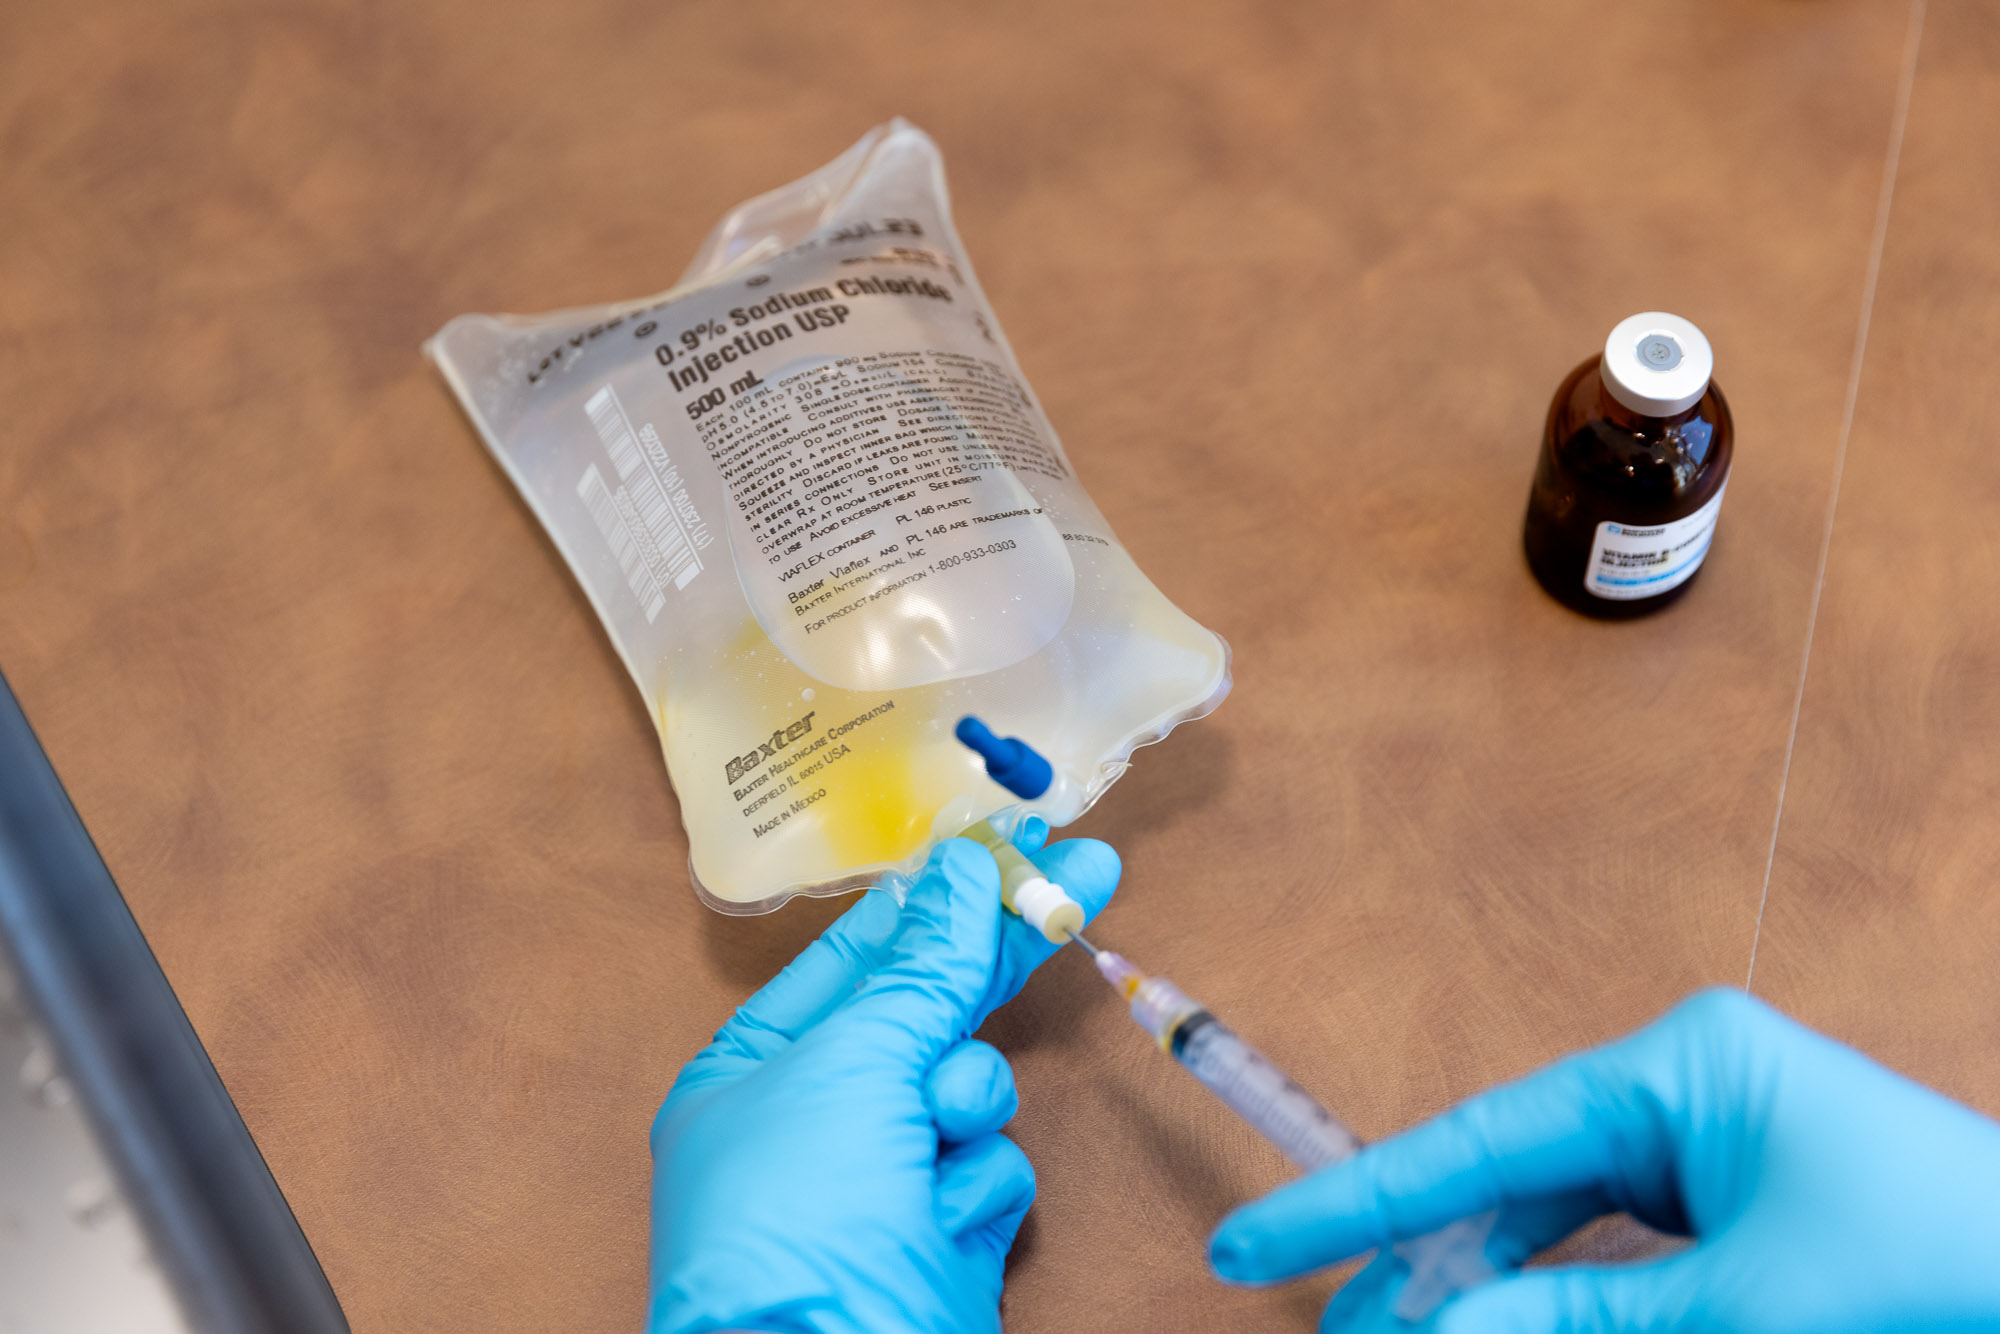
The actual compounding process follows a strict sequence that most tutorials skip over because it's tedious. First, you calculate the osmolarity of your final solution. IV vitamin formulations often end up hyperosmolar when you load them with B-complex vitamins and high-dose C. If your final product exceeds 600 mOsm/L, you're pushing into territory where peripheral administration becomes risky. The standard workaround is either diluting with additional carrier fluid or routing through a central line, which changes your prescribing protocol entirely. After osmolarity is settled, you move to pH compatibility checking. Most B vitamins degrade rapidly below pH 4.5 or above pH 7.5. Ascorbic acid drops the pH of your solution significantly, and if you're also adding glutathione or certain amino acids, you can get precipitation within hours. I once compounded a batch with 1500mg of vitamin C, 600mg of glutathione, and B-complex in a 100ml bag. Six hours into the hold time, the solution turned slightly opaque. We discarded the entire lot. The fix was running a small-scale compatibility study first — not skipping it because it costs time. It costs less than a recall. Transfer technique determines your actual sterility outcome. Working in an ISO Class 5 hood with proper alcohol prep and aseptic transfer sets, you're using sterile transfer needles or luer-lock connections designed for parenteral use. The needle gauge matters more than most compounding pharmacists account for. A 21-gauge needle creates larger puncture sites on vial septa, which increases the risk of particulate silicone shedding from syringe plungers. I switched to 22 or 23 gauge for all my transfers and started inspecting each bag against a light box before release. It adds about forty-five seconds per unit but catches cloudy particulates that would otherwise go out the door.
Testing and Release Criteria
Beyond the visual inspection, you need to be running sterility testing and endotoxin testing on your batches. The USP <797> requirements for beyond-use dating depend on your sterility assurance level. For low-risk level compounding with proper ISO Class 5 conditions, the typical BUD is 48 hours at room temperature or 14 days under refrigeration. High-risk compounding drops that to 3 days refrigerated. Most IV vitamin protocols fall into the medium-risk category, which gives you roughly 10 days refrigerated if your environmental monitoring is clean. Endotoxin testing using the LAL method is straightforward if you've done it before. The kits run about eighty dollars per test and take roughly twenty minutes of hands-on time. I batch my tests weekly rather than per-compound because the cost per unit drops significantly. The real bottleneck is the incubation period — you need to hold samples for fourteen hours minimum before reading results. Plan your scheduling around that constraint or you'll be waiting on releases and missing clinic windows.
Common Pitfalls That Cost Pharmacies Money
The biggest waste I see in this space is over-ordering individual vitamin ingredients. Most compounding pharmacies don't need full vial sizes. Manufacturers like Hameln or Lucane offer smaller unit doses that cut your per-dose cost by roughly sixty percent. The tradeoff is longer storage times for each ingredient since you're opening smaller containers more frequently. I keep a running inventory log and reorder when stock hits forty percent, which has kept my shrinkage under three percent annually. Another issue is preservative selection. Some clinics want preservative-free formulations, which means single-use vials or bags. That doubles your packaging cost and cuts your BUD down to administration time. Others accept benzyl alcohol or metacresol as preservatives, which extends shelf life but introduces a conversation you need to have with the prescribing provider upfront. Documented patient consent for the preservative is worth the five minutes it takes. I've seen two pharmacies get cited for not having that documentation on record. Documentation is where most new operations fail their first audit. Batch records need to capture the lot numbers of every active ingredient, the lot number of the base solution, the preparation date and time, the prepared-by and verified-by signatures, the BUD, and the environmental monitoring readings for that day. I use a simple spreadsheet template that cross-references lot numbers with supplier COAs. It takes about eight minutes per batch to fill out correctly. Skipping it to save time is how you lose your license.
Get the Full Details

What This Approach Doesn't Fix
IV vitamin therapy compounding is not a high-volume operation. Even with streamlined workflows, a single pharmacist can realistically prepare and verify maybe thirty to forty bags per day without rushing sterility checks. If your demand exceeds that, you need either a second compounding station or a contract with a 503A outsourcing facility. The economics shift dramatically at scale because the overhead of ISO Class 5 hood maintenance, environmental monitoring, and QC testing is largely fixed regardless of batch size. There's also the question of whether the clinical outcomes justify the operational complexity. The peer-reviewed evidence for most IV vitamin protocols remains limited. You're building a pharmacy service around treatments that many practitioners prescribe based on observational data and anecdotal reports. That doesn't make the work invalid, but it does mean you'll occasionally field calls from clinics wanting customized protocols that aren't backed by any established safety data. Having a clear stance on what you will and won't compound is a business decision, not just a clinical one.