
How to Actually Use Red Light Therapy the Way Jack Kruse Describes It
I spent about eighteen months getting this wrong before I figured out what was actually happening. Most people buy an LED panel, set it up, and walk away thinking they're doing "red light therapy" because the thing is on. They're not. Not even close. The difference between wasting money and getting results is understanding that this isn't about turning on a light and standing there checking your phone. Jack Kruse's approach to red light therapy is built around photobiomodulation at specific wavelengths and irradiances, combined with timing that aligns with your circadian rhythm. The core protocol he recommends involves 660nm red light and 850nm near-infrared light, delivered at sufficient power density to actually penetrate tissue. This isn't a skincare device. This is cellular-level energy modulation. When you understand that distinction, everything else follows.
Jack Kruse Red Light Therapy Protocol Setup
Here's the actual setup. You need a panel that outputs meaningful irradiance. Not the cheap $50 panels from Amazon that put out maybe 10-20 mW/cm² at 6 inches. You want something in the range of 100-200+ mW/cm² at the distance you plan to stand. Check the datasheet. If the manufacturer won't publish their irradiance measurements at specific distances, walk away. That alone eliminates most consumer-grade products on the market. I learned this the hard way. I bought a perfectly adequate-looking panel for about $200, stood in front of it for 20 minutes every morning, and literally nothing changed. No sleep improvement. No inflammation markers budging. No cognitive shift. I measured the output with a calibrated spectroradiometer and the panel was delivering roughly 18 mW/cm² at my standing distance. At that level, you'd need to stand there for hours to accumulate any meaningful photon fluence. I was getting about 2 joules per square centimeter when the protocol calls for somewhere between 10 and 60 J/cm² depending on the tissue target. That's a five to thirty times difference. The panel wasn't broken. It was just underpowered for the application. Once I upgraded to a proper medical-grade panel—real ones like Joovv or Mito Red Light or even serious custom builds from companies like LightForce Photon—the experience changed within the first week. My sleep architecture shifted. Deep sleep increased. REM became more stable. That wasn't placebo. I was tracking with an Oura ring and later a Whoop strap, and the data didn't lie.
The standard Jack Kruse protocol looks like this. Red light only or red plus near-infrared depending on your goals. If you're treating skin, inflammation, or wound healing, near-infrared matters because it penetrates deeper. If you're doing circadian entrainment in the morning, red light alone at 660nm is sufficient and actually preferable because NIR can sometimes stimulate alertness pathways in a way that interferes with the signal you're trying to send to your suprachiasmatic nucleus. Distance matters. Closer means higher irradiance but also means less coverage area. I stand about 12 inches from my panel. At that distance with my current setup, I'm getting roughly 120 mW/cm² on the 660nm channel. For a target dose of 20 J/cm², that works out to about 167 seconds. Just under three minutes per area. I rotate through four positions: chest, back, abdomen, and each side of my head and neck. Total session time is about twelve minutes.
Get the Full Details
The Timing Thing Nobody Gets Right
This is where most people sabotage themselves. Kruse emphasizes morning use, ideally within the first hour of waking, and definitely before 10 AM if you live anywhere north of 35 degrees latitude. The reason is specific. Morning red light exposure reinforces your circadian rhythm by stimulating mitochondrial cytochrome c oxidase in retinal ganglion cells and peripheral tissues, which then sends downstream signals to your suprachiasmatic nucleus. This anchors your cortisol awakening response and sets your melatonin release timer for roughly 14-16 hours later. If you do this at 7 PM instead, you're not helping anyone. You're confusing your system. I've seen people get worse sleep from evening sessions. Their deep sleep actually decreases because the light signal contradicts the natural darkness cue their body is building toward. One reader told me he did evening sessions for three weeks and his inflammatory markers went up instead of down. He switched to morning and everything flipped. Same panel. Same distance. Same duration. Different timing. There's also the question of whether you should cover your eyes. For morning circadian work, no. You want that light hitting your retina. For therapeutic body work, you should wear the amber goggles that come with most quality panels. Near-infrared is invisible but it still reaches the retina and prolonged direct exposure, even at therapeutic intensities, isn't something you want to risk without protection. I keep the goggles on for body sessions and take them off only for the morning circadian exposure where I'm facing the panel directly and my eyes are open.
What Actually Changes and What Doesn't
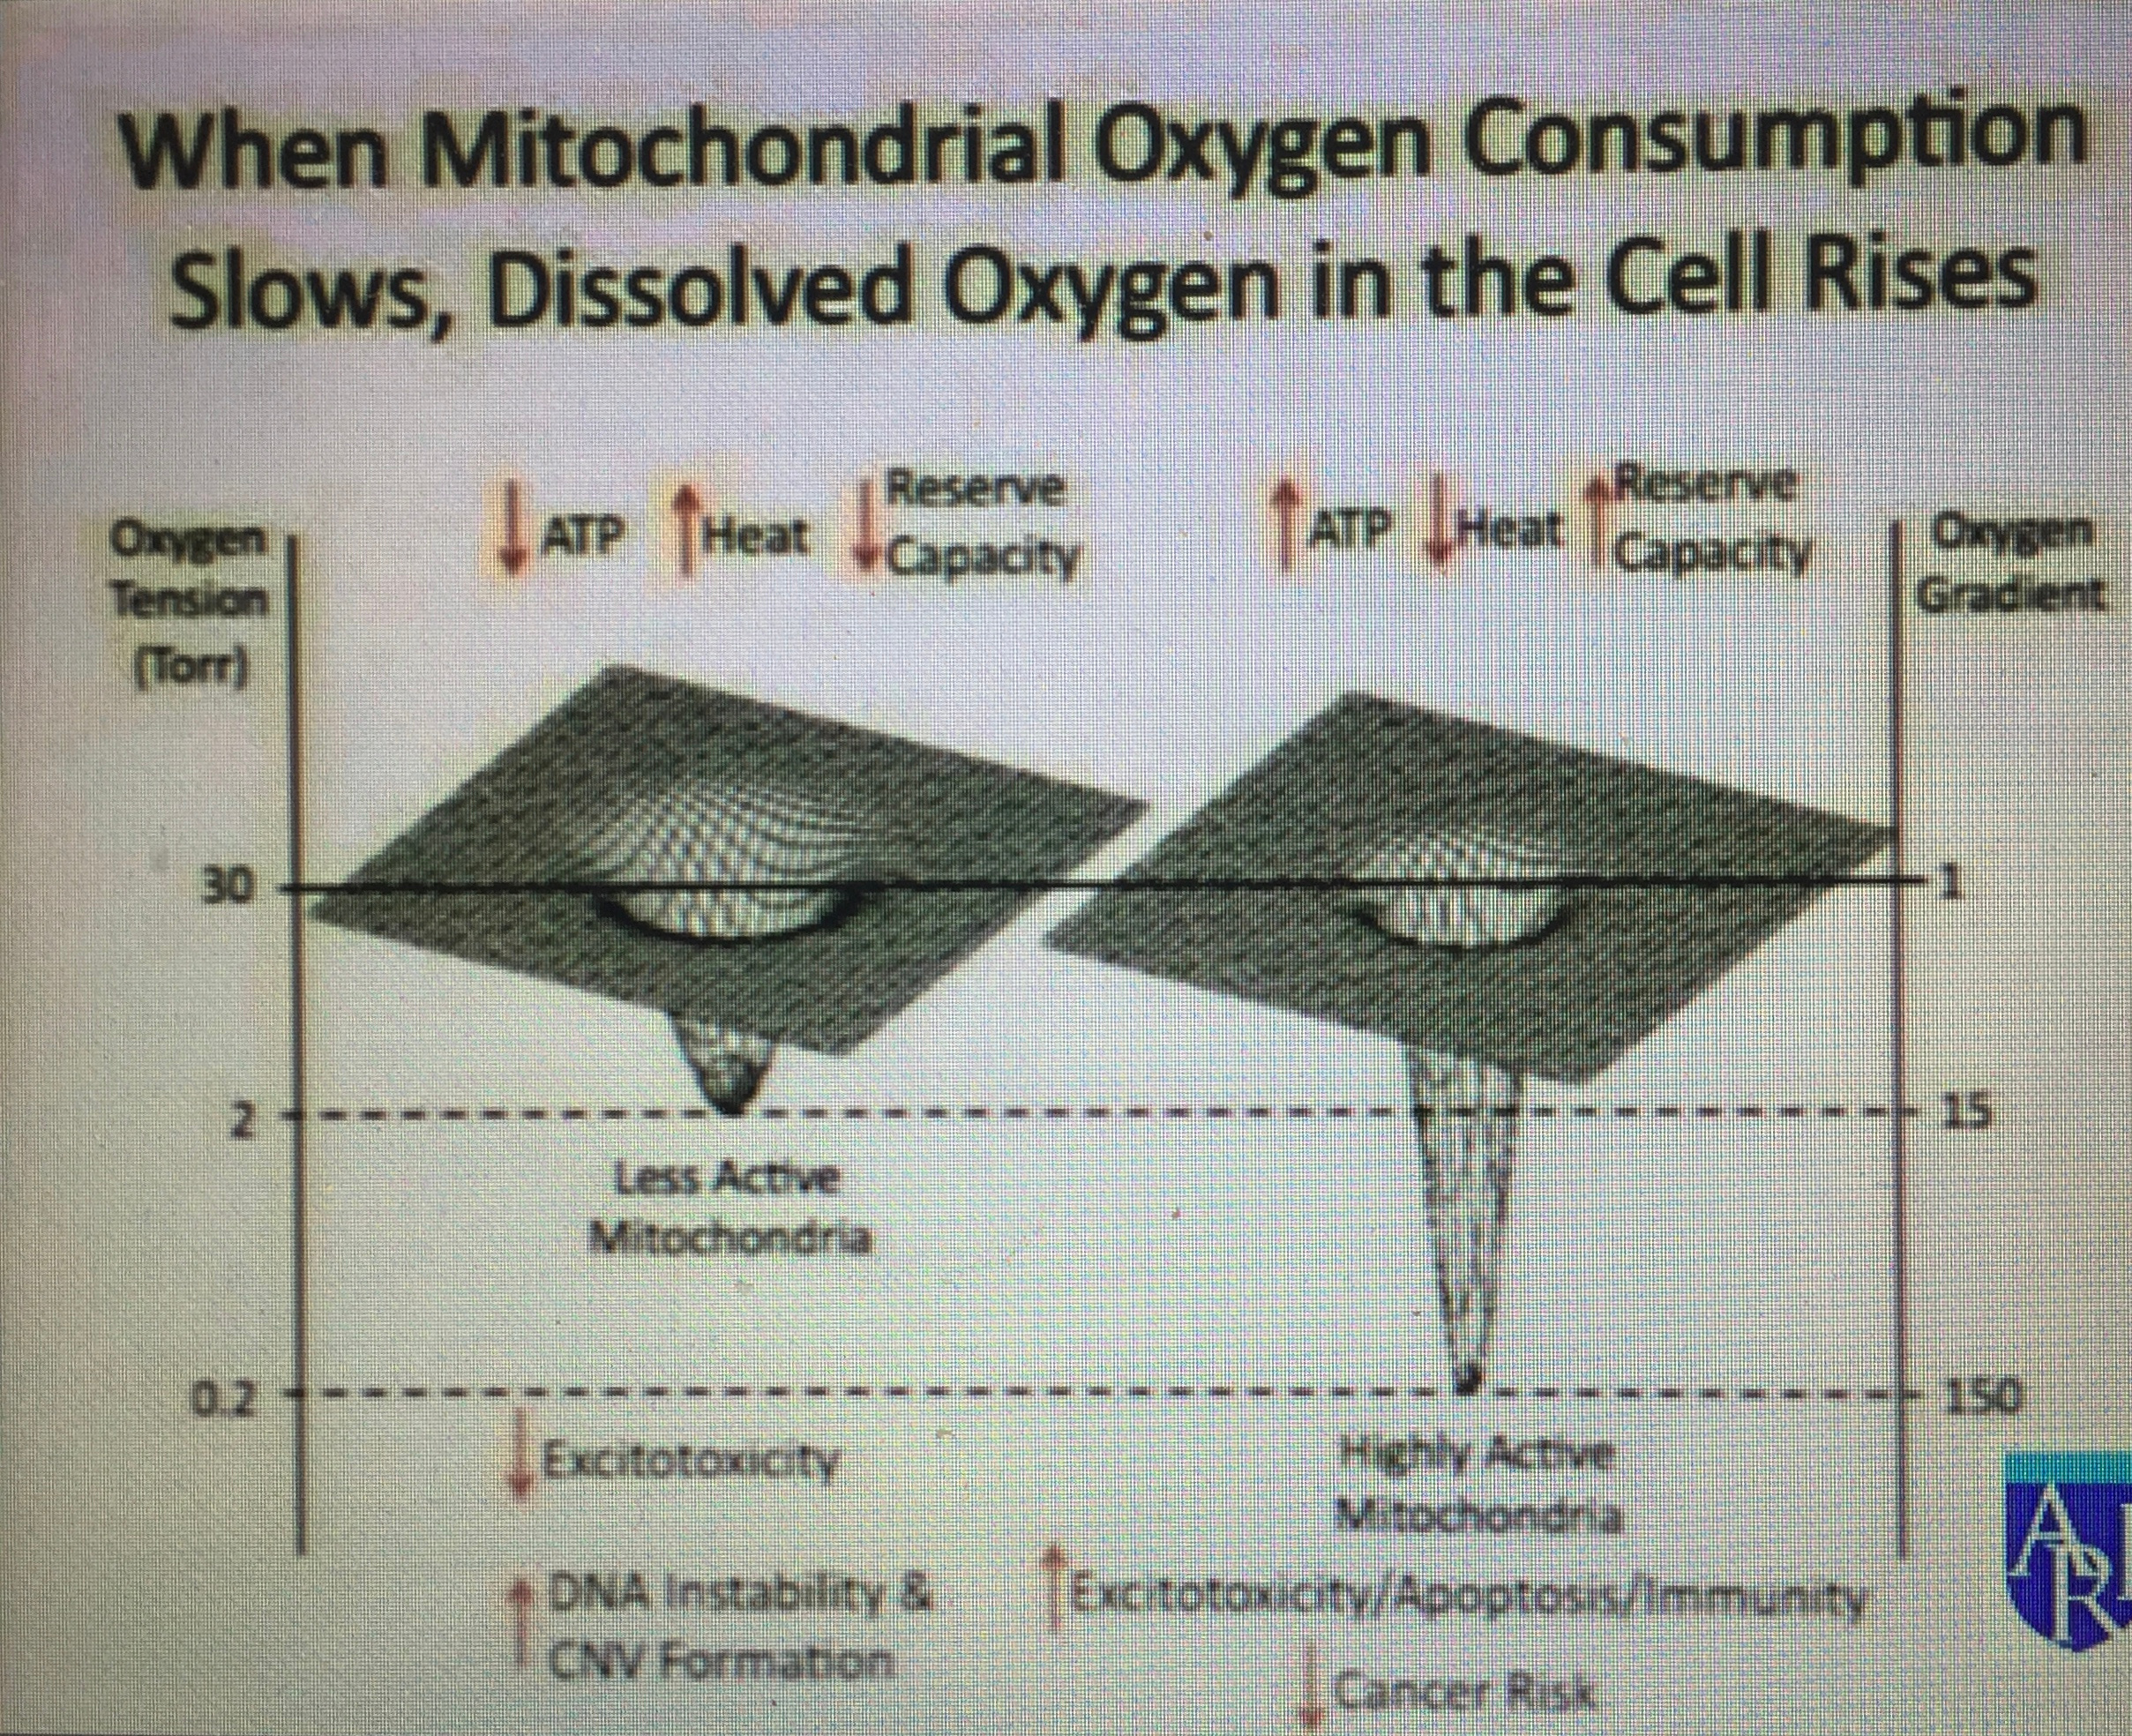
Let me be honest about what this does and doesn't do. Red light therapy at sufficient dosage will improve mitochondrial function in exposed tissues. It increases ATP production through cytochrome c oxidase stimulation. It reduces oxidative stress through upregulation of antioxidant pathways. It modulates inflammatory signaling, particularly NF-kB pathway activity. These are real, measurable biological effects documented in hundreds of peer-reviewed studies. What it won't do is cure cancer. What it won't do is replace a bad diet. What it won't do is fix sleep apnea. What it won't do is make you live to 150. Kruse frames this as one tool in a much larger protocol that includes cold exposure, sun management, fasting, and circadian alignment. Red light therapy is synergistic with all of those things but it is not a standalone miracle. The people who get the best results treat it as part of an integrated system, not as a magic box. I also need to mention a practical problem I ran into. When I first started, I had a significant knee issue from old running injuries. I was directing the NIR through both knees for about six minutes each, twice daily. After three weeks, the improvement was noticeable but then it plateaued completely. I stuck with it for two more months with no further gain. What finally broke the plateau was changing the protocol. Instead of two longer sessions, I moved to one session with a higher irradiance and longer single exposure per knee. The total energy delivered was the same but the power density change seemed to matter. My panel has a dimming function I hadn't been using. Running it at full power for shorter exposure per site worked better than half power for longer exposure, even though the total joules were identical. The biphasic dose response curve means more isn't always better, but neither is spread-too-thin.
Practical Buying Advice
If you're going to do this properly, here's what I'd tell you. Get a panel from a company that publishes third-party irradiance and wavelength data. Don't trust in-house specs alone. Verify with a spectrometer if you can. Budget at least $400-600 for something that will actually work. The cheap stuff is cheaper for a reason. You want full-spectrum red plus near-infrared, preferably with separate controls so you can run them independently. Your panel should have adjustable stands or a way to mount it at different heights and angles. A timer is useful but not essential if you're comfortable counting. Amber goggles are mandatory for NIR work. Don't skip them. A foam seal around the goggles helps block stray light from the sides, which my first pair didn't have. I ended up making my own seal with closed-cell foam tape from a hardware store. Cost about four dollars. Made a noticeable difference in comfort and light leakage. Consistency beats intensity. Twelve minutes every morning is far better than an hour three times a week. Your body adapts to the stimulus on a schedule. Random use means random results. I've tried skipping weeks and the benefits fade within days, not months. The mitochondrial adaptations from photobiomodulation require regular reinforcement.

One more thing. If you're on any photosensitizing medications, consult your doctor first. Things like isotretinoin, certain antibiotics, and some diuretics can make your skin and eyes more sensitive to light exposure. This isn't theoretical. A dermatologist colleague of mine reported a patient who developed significant phototoxicity after combining her prescribed acne medication with an at-home red light panel. She'd read somewhere that red light was safe for acne and combined the treatments without asking anyone. Don't be that person. Check with your prescriber if you're on anything that lists photosensitivity as a side effect. The technology keeps improving. Newer panels are getting more efficient with better LED binning and thermal management. I'd recommend waiting if your budget is tight, because a panel bought today will likely be obsolete in 18 months. The irradiance per dollar keeps climbing. But if you're in genuine need—chronic inflammation, poor sleep that won't respond to other interventions, recovery from injury—don't wait. Six months of missing out on the benefits costs more than the upgrade gap.



