Why the Johns Hopkins Evidence Based Practice Model Matters in Real Clinical Settings
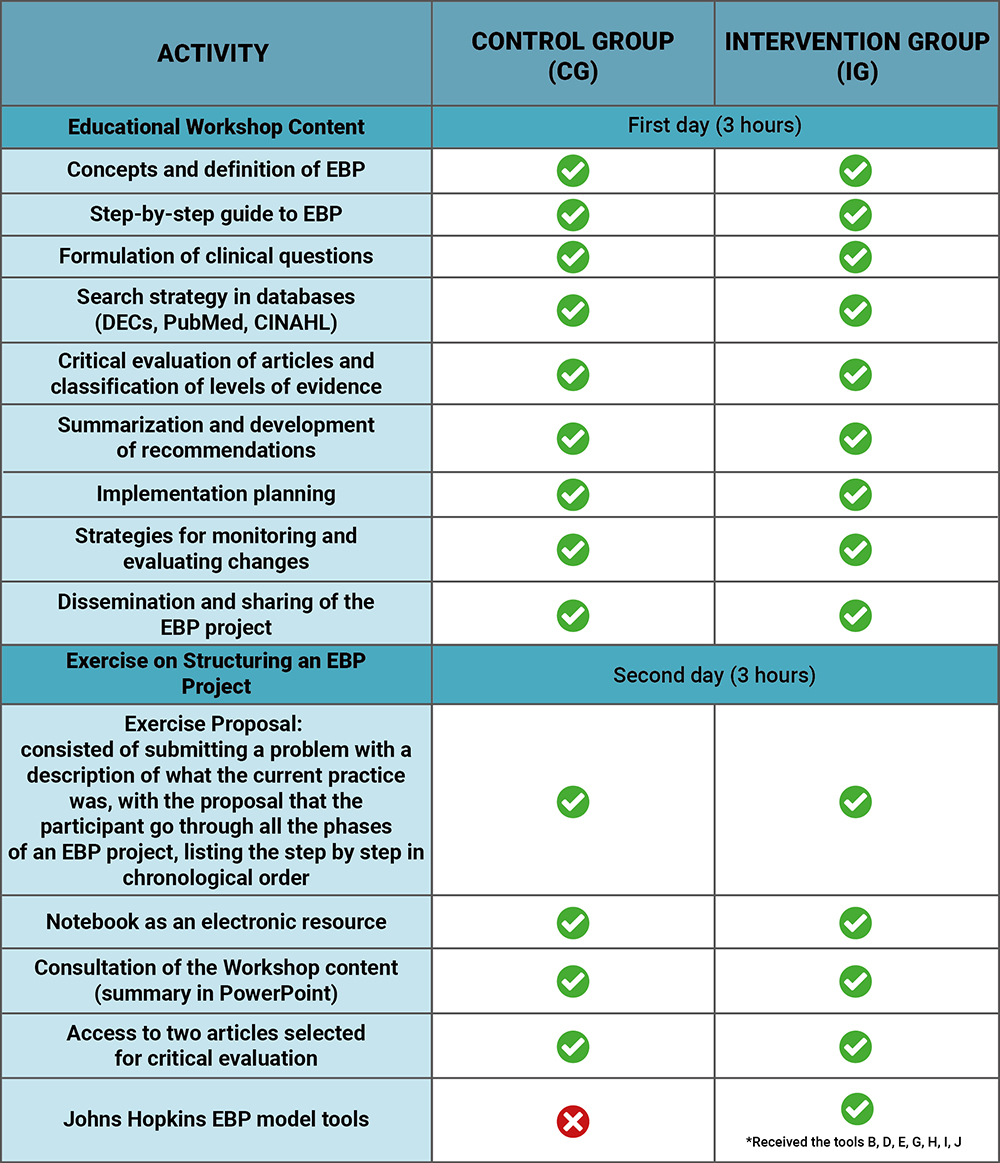
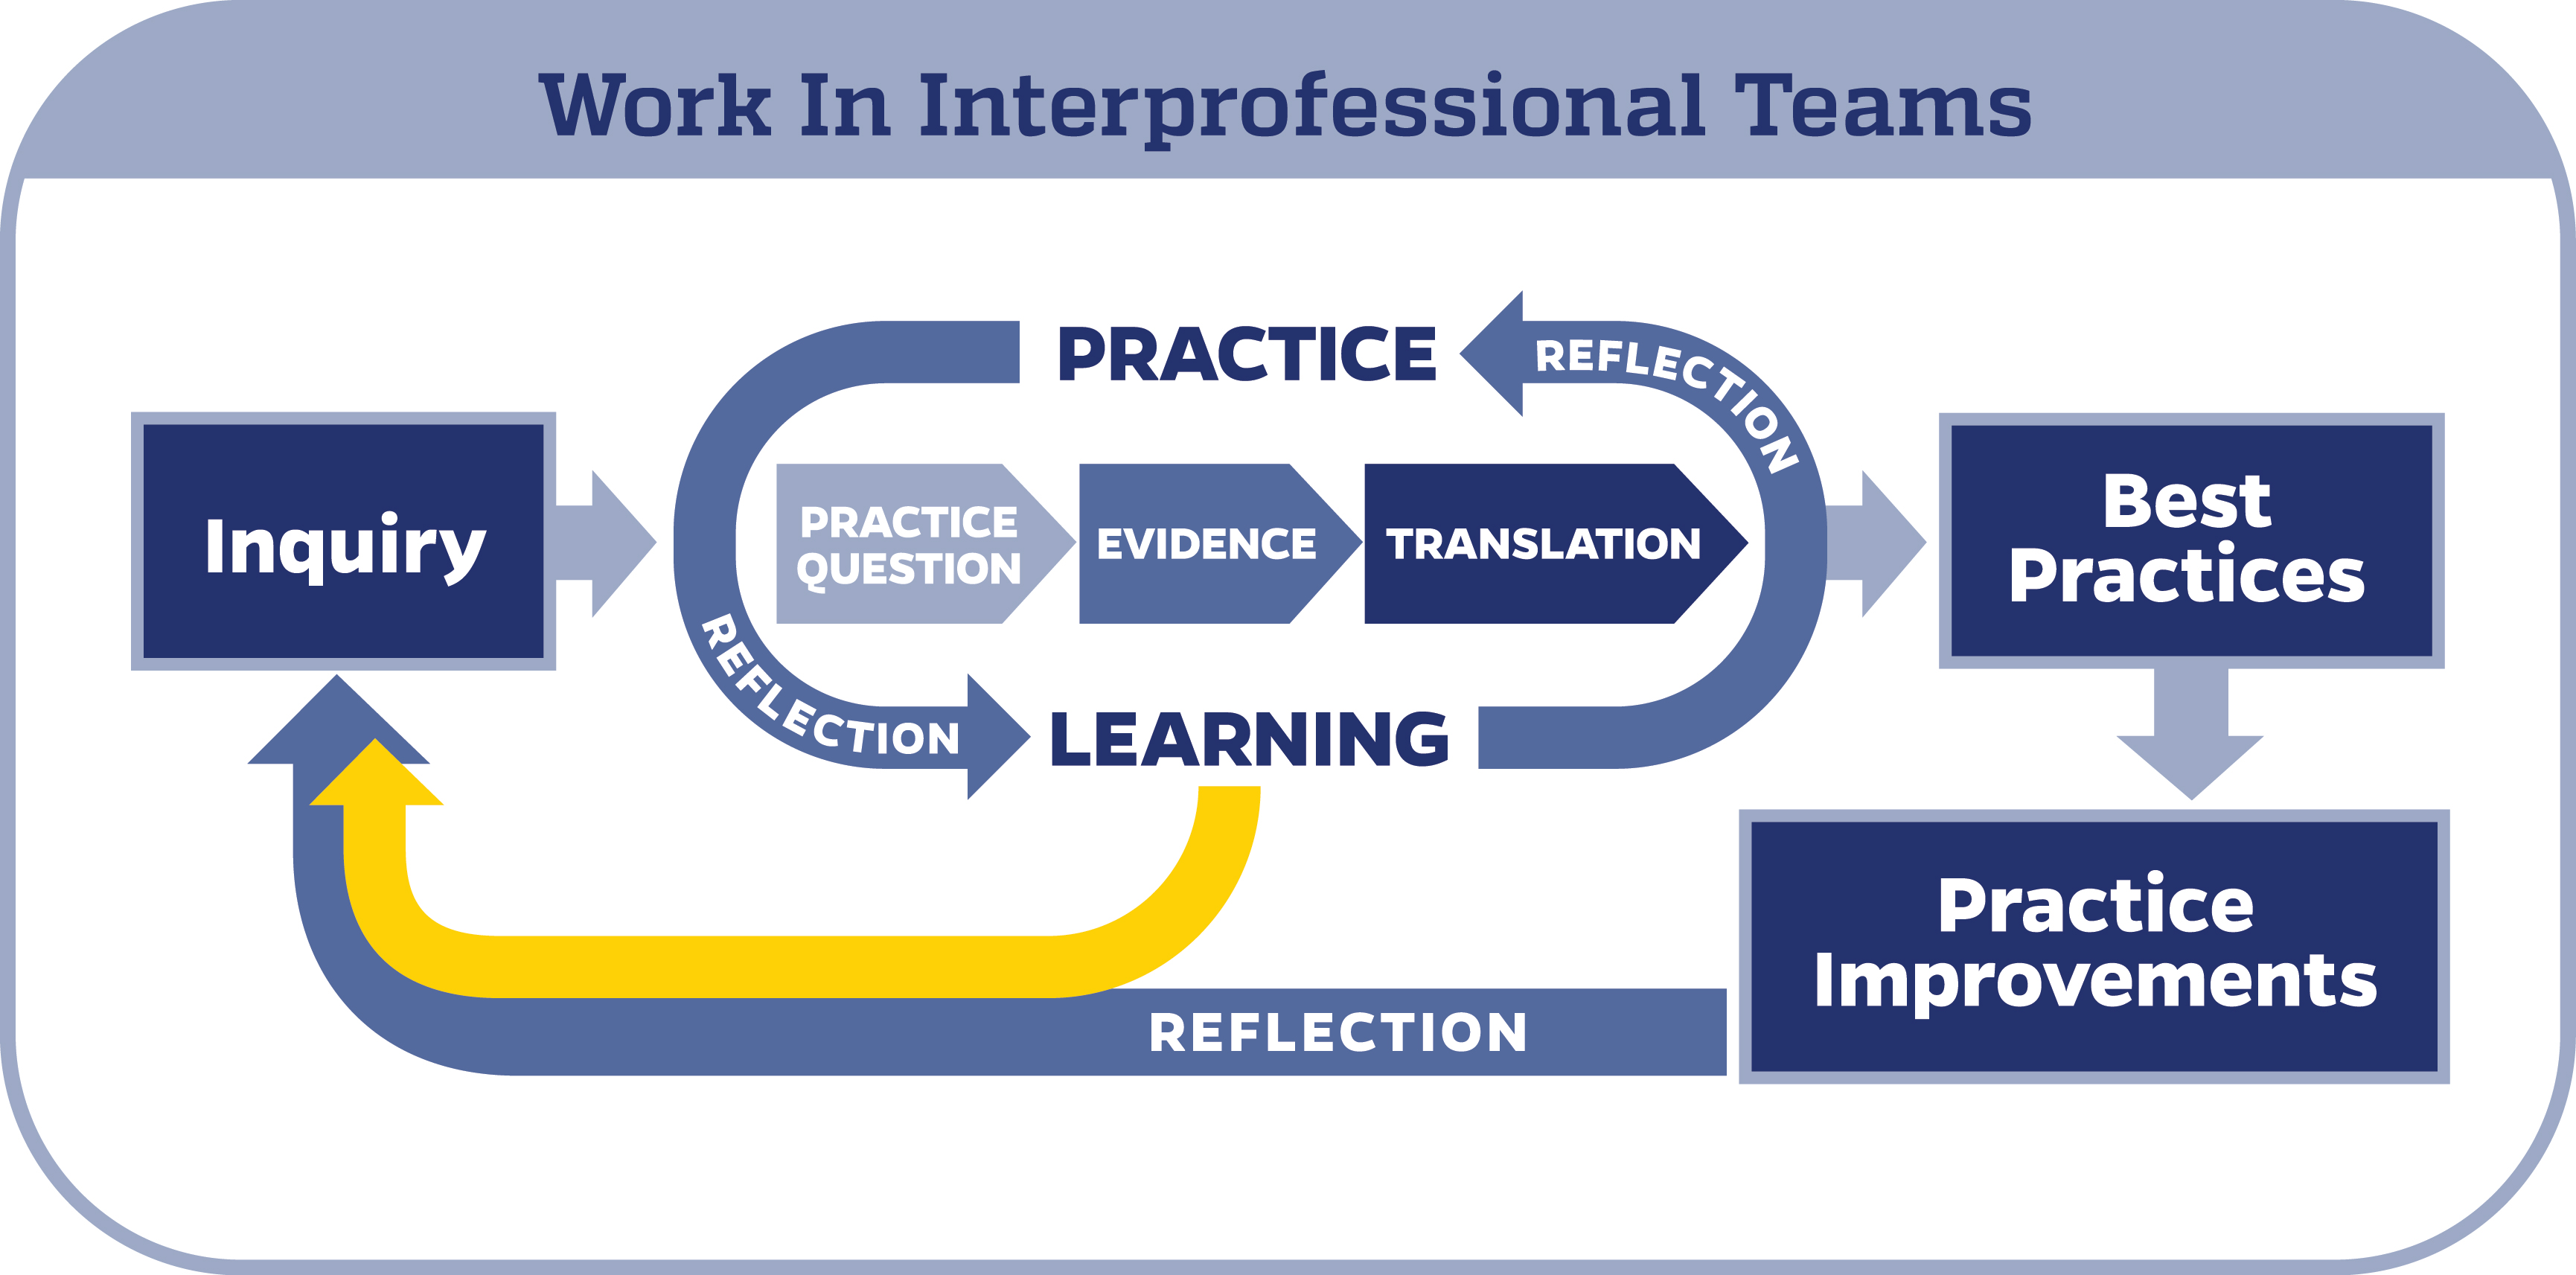
When I first started using the Johns Hopkins Evidence Based Practice Model back in 2016, I thought it would be a straightforward checklist. It isn't. What I found after three years of implementing this across two hospital units was that the real challenge isn't understanding the model itself—it's getting clinicians to actually engage with it without treating it like just another compliance task. The model breaks down into three main pieces: the Project Approach, the P.E.E.R. method, and the three pillars of evidence—best research, clinical expertise, and patient preferences. The Project Approach starts with identifying a problem, then gathering a team, checking current data, and building an action plan before you even look at the literature. That sequence matters. Most teams skip straight to searching for studies, which is why so many EBP initiatives fizzle out within six months. I remember a specific situation that highlighted how fragile this whole process can be. We were trying to implement a new fall prevention protocol on our med-surg floor. The problem? The nurse leaders wanted to jump straight to the "best available evidence" part without first establishing what "best" meant in their context. They had their opinions locked and loaded. Using the P.E.E.R. method forced us to slow down and actually ask what questions the patients were raising about falls—not what the administrators assumed they were asking. It took four extra meetings, but we ended up with a protocol that actually got adopted instead of gathering dust on a shared drive.
Understanding the Johns Hopkins Evidence Based Practice Model
The Johns Hopkins Evidence Based Practice Model is built around the Project Approach framework, which structures EBP work into seven clear steps. Step one is identifying the problem. Step two involves forming the project team. Step three asks you to turn the problem into a question using the PICOT format—Population, Intervention, Comparison, Outcome, and Time. Step four is the actual literature search. Step five requires grading the evidence. Step six is implementation. Step seven is evaluation. What makes this model different from other EBP frameworks is the emphasis on the P.E.E.R. acronym for formulating that clinical question. P stands for Population, E for Event or Exposure, E for Evaluation, and R for Research question. It keeps you from writing questions that are too broad or too narrow. I've seen teams waste weeks searching for evidence on questions that were essentially unanswerable because they hadn't properly scoped the population. The three pillars of evidence are non-negotiable in this model. You can't just pull from research studies. Clinical expertise has to factor in. Patient preferences and values matter too. In practice, this means you're often reconciling conflicting data—for instance, when a study shows one intervention works better, but your patient population has specific comorbidities that might change the outcome. That reconciliation step is where most people get stuck.
Implementing the Model in Practice: What Nobody Tells You
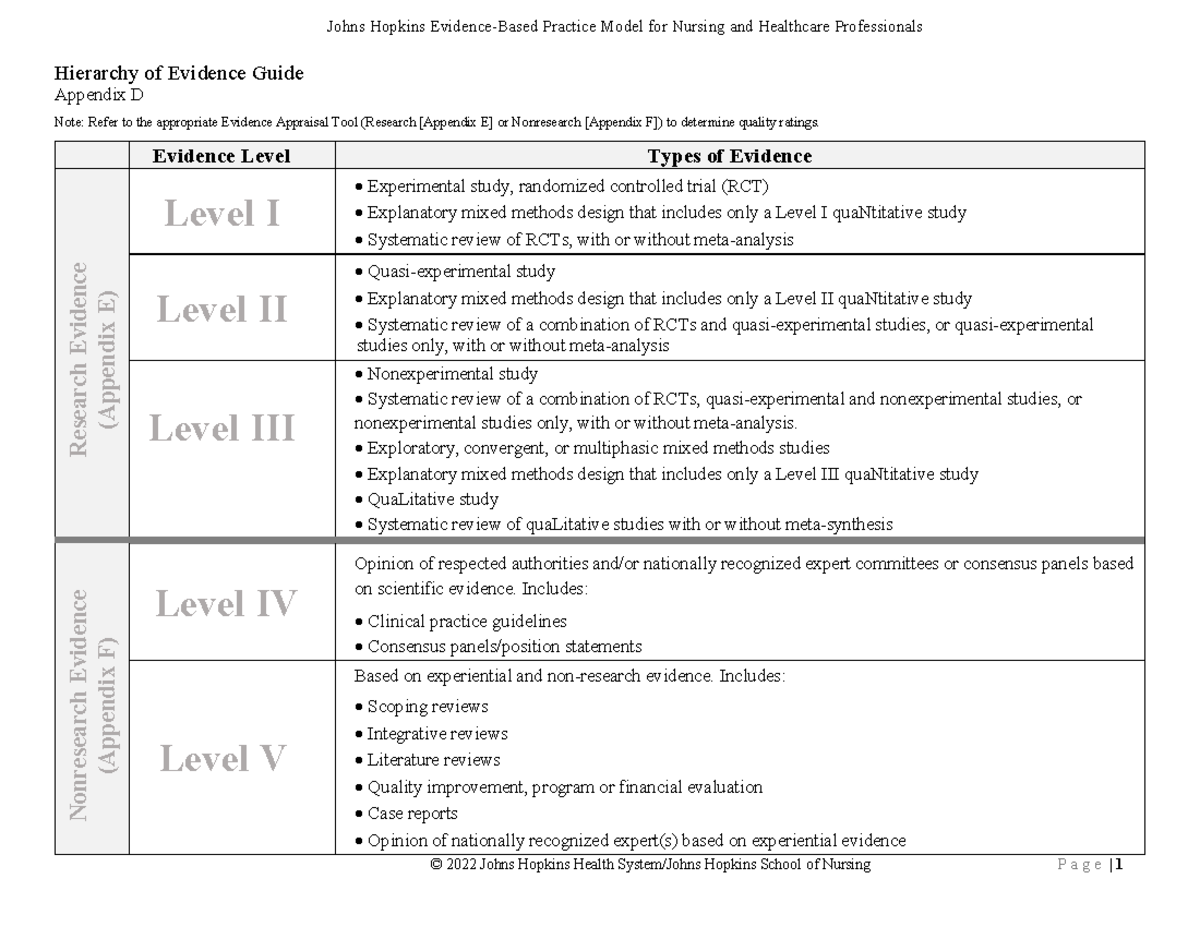
The literature search phase is where the model usually runs into trouble. You think you'll find perfect studies, but they rarely exist. In my experience, about 60% of the time you're working with weak evidence—case series or expert opinion. The model acknowledges this. You still have to grade what's available and move forward. It feels messy. That's normal. One thing I wish someone had told me upfront: the evidence grading system uses a point-scale approach, not just letter grades. Each study gets scored based on methodology quality, sample size, and relevance. Studies with five points are strong recommendations. Zero to two points are weak. This detail matters because it changes how much weight you give a study in your final decision. Most people miss that nuance. The implementation phase is where the model shows its real value—and its real limits. You can follow every step perfectly and still fail if you don't account for organizational culture. I learned this the hard way when we tried to roll out an evidence-based pain management protocol. The research was solid. The plan was solid. The nursing staff had legitimate concerns about workflow disruption that nobody had addressed in the early planning stages. We went back, spent two weeks doing stakeholder interviews, and revised the rollout schedule. Implementation took twice as long, but the protocol actually stuck.
Get the Full Details

Here's a practical limitation worth noting: the model works best in environments with dedicated EBP support and time allocated for staff participation. If your unit is critically short-staffed or your administration treats EBP as an optional extra, the model will struggle. I've seen it fail in those conditions, and it's not the model's fault—it's an implementation resource issue. In those cases, consider starting smaller. Pick one high-impact problem and run a pilot before scaling up.
Common Mistakes When Using the Johns Hopkins Evidence Based Practice Model
The most frequent error I see is treating the steps as linear. They're not. You'll circle back. Expect it. When you find evidence that contradicts your initial assumption, you may need to reformulate the question or adjust the scope. That's not failure. That's how the model is supposed to work. Another mistake is underestimating the stakeholder engagement required. The model mentions this in the team formation step, but it doesn't emphasize enough how much time this actually takes. In one project, we included patients in our discussion group, which added about three weeks to our timeline but dramatically improved the final protocol's acceptance rate. Worth it. Probably. Finally, people often rush the evaluation phase. The model requires you to measure outcomes against your baseline. That means keeping good data from the start. I've lost track of how many projects couldn't demonstrate success because nobody had tracked the pre-intervention metrics properly. Set up your data collection before you implement, not after.
The Johns Hopkins Evidence Based Practice Model isn't a magic bullet. It won't fix systemic issues or guarantee adoption. But when applied correctly with adequate resources and genuine stakeholder involvement, it provides a structured way to bring evidence into clinical decision-making without relying solely on tradition or individual expertise. That structure is worth the effort, even when the process feels uncomfortable and slow.