The Johns Hopkins Evidence Level and Quality Guide Is a Practical Tool, Not a Perfect System
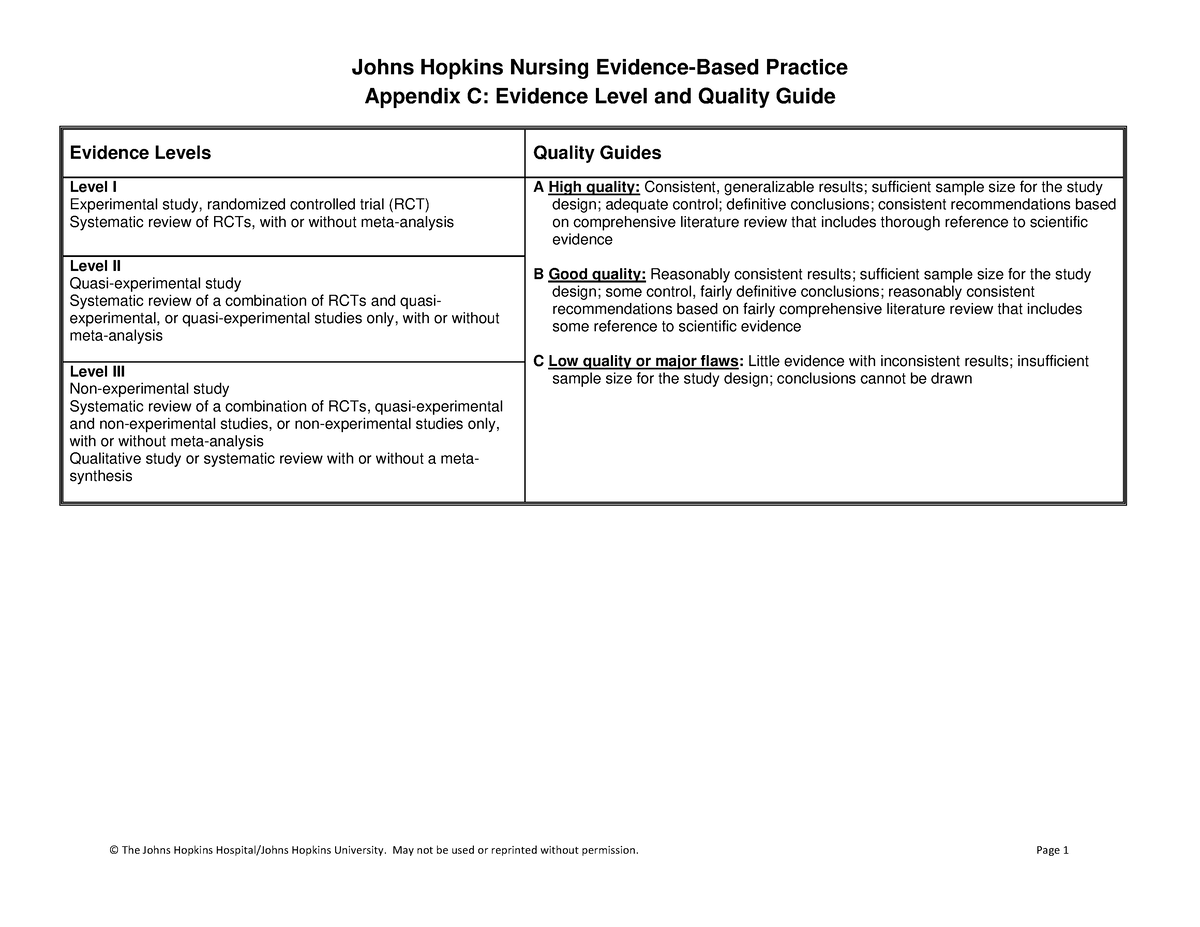
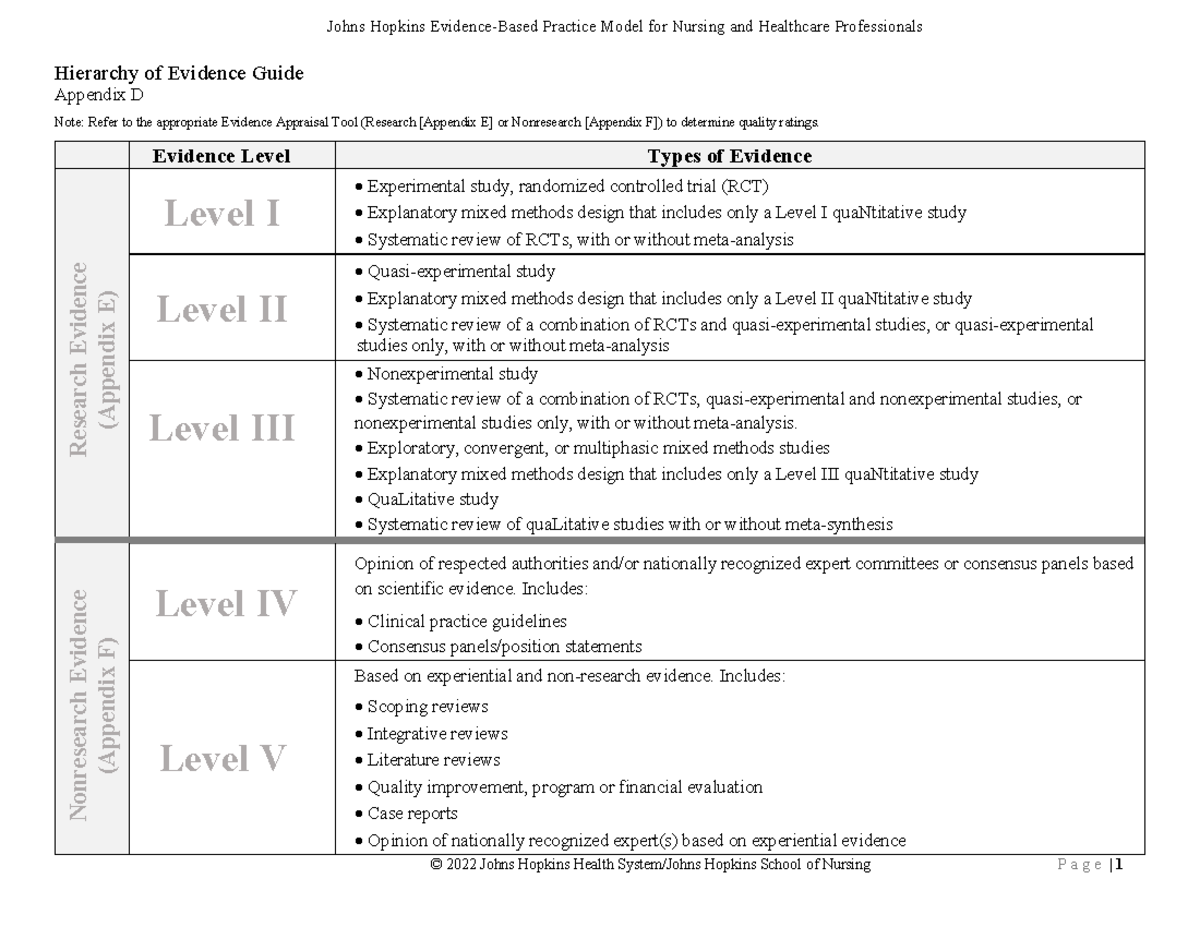
If you're working in nursing or healthcare research, you've probably run into the Johns Hopkins Nursing Evidence-Based Practice model at some point. It's one of the most widely used frameworks for appraising clinical evidence, and for good reason. The system assigns levels from I to V based on study design and then grades quality as A, B, or C depending on how rigorous the evidence is. It sounds simple on paper. In practice, it gets messy very quickly. The level assignment part is where most people trip up. Level I requires at least one systematic review or meta-analysis of randomized controlled trials. Level II is a single RCT. Level III covers quasi-experimental work. Level IV is descriptive nonexperimental research. Level V is expert opinion, case reports, or clinical consensus. That's the textbook version. The real problem shows up when you encounter a study that doesn't fit neatly into one box. I spent weeks last year trying to categorize a longitudinal cohort study that had elements of both Level II and Level III design. The protocol didn't have randomization, but it did use a control group with prospective data collection. The answer turned out to be context-dependent. I checked the original Johns Hopkins manual directly and confirmed that the presence of a comparison group pushes it toward Level III, even if the data collection is prospective. If you skip reading the actual rubric and just go by study type alone, you'll misclassify half your references.
How to Use the Johns Hopkins Evidence Level And Quality Guide Correctly
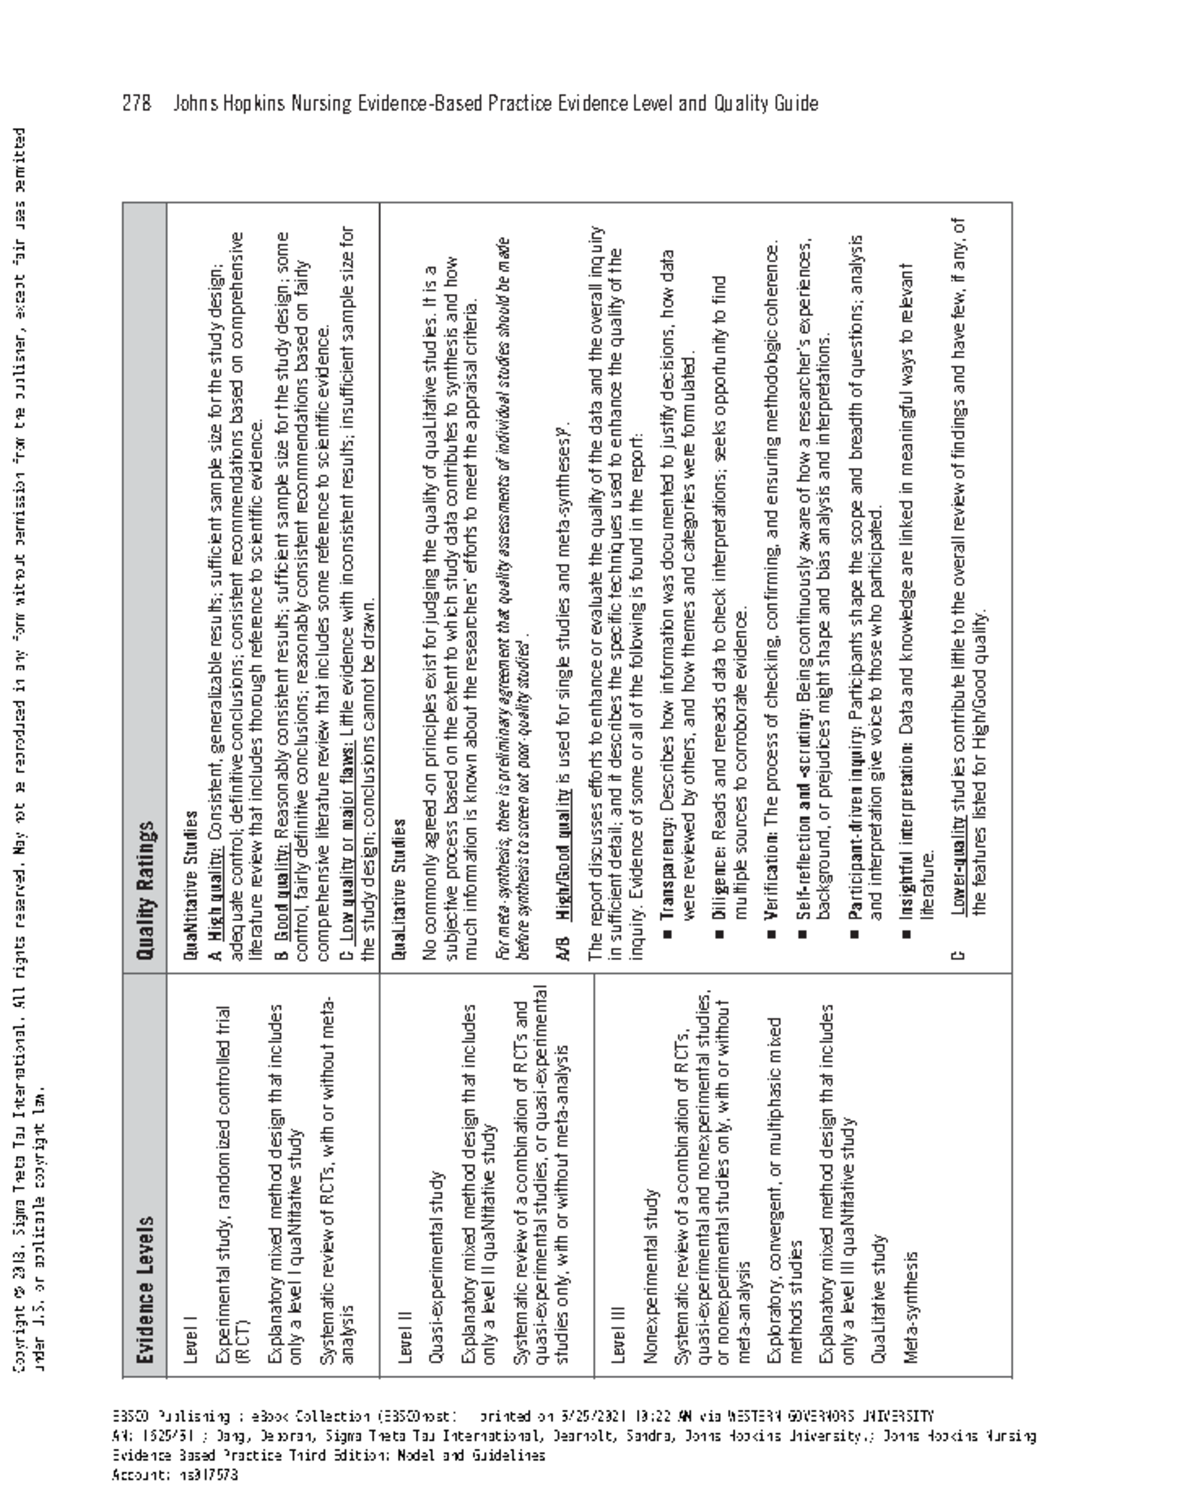
Start by pulling the full guideline from the Johns Hopkins website or your institution's library portal. The PDF version has detailed flowcharts for each evidence type. Download it and keep it open while you work. Don't rely on memory. I learned that the hard way after spending two days arguing with a colleague over a Level II versus Level IV designation before we both realized we were using different editions of the framework. The 2016 revision changed how qualitative studies are handled compared to the earlier version. Once you have the current guide, you need to separate the evidence level question from the quality grade question. They're independent ratings. A Level I study can receive a Grade C quality rating if it has serious methodological flaws. I see this all the time in nursing journals where a meta-analysis gets published with clear publication bias and heterogeneity issues but still carries the Level I label because of its design. The quality grade catches that. You assign the grade by looking at internal validity, consistency of results, and directness to your clinical question. The grade breakdown is A for high-quality evidence, B for moderate, and C for low-quality or conflicting findings. Here's the thing most people don't mention: the qualitative evidence track works differently. The Johns Hopkins model includes a separate appraisal process for qualitative research. You're not just looking at sample size or randomization. You're evaluating credibility, transferability, dependability, and confirmability. If you try to force a qualitative study into the quantitative level scale, you'll get the wrong rating. I ran into this with a phenomenological study on patient experience with chronic wound care. Someone on my team initially marked it as Level IV because it was descriptive. It should have been rated under the qualitative appraisal pathway, which operates on its own criteria entirely. Check the qualitative section of the guide before you do anything else if your study isn't a traditional trial.
Where This Framework Breaks Down
For all its utility, the Johns Hopkins system has limitations that matter in real clinical settings. It was designed primarily for nursing practice, which means it sometimes struggles with interdisciplinary research. A study that combines epidemiological modeling with clinical outcomes data doesn't map cleanly onto the five-level structure. I worked on a project last year involving predictive algorithms for sepsis onset. The evidence base included machine learning models, simulation studies, and retrospective chart reviews. None of those fit Level I through V without some creative interpretation. We ended up using a hybrid approach where we assigned the closest quantitative level and then documented the structural mismatch in our methodology section. It's not ideal, but it's honest. If you're working outside of traditional clinical nursing research, consider supplementing the Johns Hopkins framework with the GRADE system. GRADE handles cross-disciplinary evidence better and gives you more granular ratings for certainty of evidence. Another bottleneck is time. Appraising every reference through the full Johns Hopkins process takes longer than people expect. A single Level I systematic review with fifty-plus included studies can take forty-five to sixty minutes to properly evaluate against the quality criteria. When you're building a guideline with two hundred references, that adds up fast. I've seen teams cut corners by only grading the top three references and assuming the rest fell into similar categories. That's risky. Two studies can share the same design but differ significantly in execution quality. I caught this once with two Level II RCTs on pressure ulcer prevention. One had proper blinding and allocation concealment. The other didn't. Same level. Different quality grades. Using them interchangeably in a protocol would have been a mistake.
Get the Full Details

Practical Steps for Getting Started
Grab the current Johns Hopkins Nursing Evidence-Based Practice Model and Quality Appraisal Tools document. It's freely available online through the Johns Hopkins School of Nursing website. Look for the most recent version, ideally post-2016. Older versions have outdated qualitative appraisal criteria. Next, create a spreadsheet with columns for citation, study design, evidence level, quality grade, and a notes field for edge cases. Put your edge case notes in the notes field. Don't skip that. The times I've gone back to resolve a classification dispute, I was always grateful I'd written down why I made the call. A Level III quasi-experimental study with a historical control group needs a justification for why it wasn't rated Level II, for example. Future you will thank present you. When you're done appraising, don't just stack the grades. Synthesize them. A collection of Grade B qualitative studies on a topic like palliative care communication might actually be more actionable for your clinical question than a single Grade B quantitative study that measures something tangential. The level system doesn't tell you which evidence matters most for a specific decision. That part still requires human judgment. I've found that pairing the Johns Hopkins appraisal with a quick relevance scoring of 1 to 5 helps prioritize which findings to actually build recommendations around. It keeps the whole process from becoming a box-checking exercise.