Needle Placement Is Half The Battle
Most people think joint and soft tissue injection is about finding the right spot and pushing fluid in. It is not. It is about knowing what you are injecting into, understanding the anatomy, and having a clear plan before you even touch the skin. I learned that after wasting an hour on a knee case because I did not account for an anomalous fat pad that shifted the landmark by nearly two centimeters. That happened to me once. I do not forget.
Joint And Soft Tissue Injection: What Actually Happens
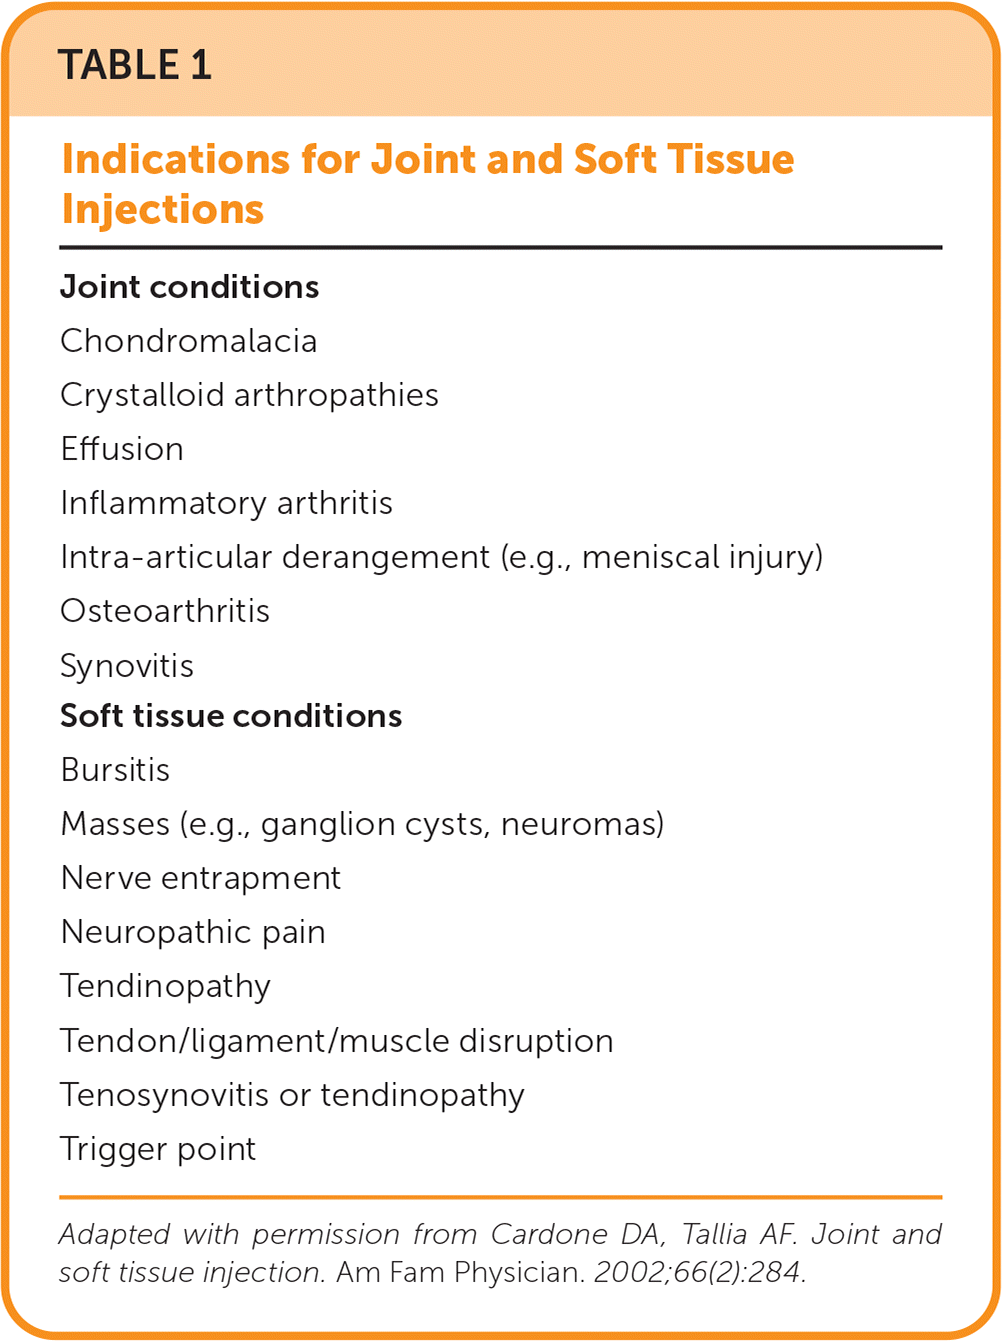
The procedure involves delivering medication directly into a joint space or soft tissue structure using a needle. Common targets include the knee, shoulder, wrist, hip, and various tendon sheaths. The medication is usually a corticosteroid, sometimes combined with a local anesthetic, though some clinicians use platelet-rich plasma or hyaluronic acid depending on the pathology. The goal is to reduce inflammation, manage pain, and improve function in a localized area without systemic side effects.The difference between a joint injection and a soft tissue injection matters more than people admit. A joint injection enters the intra-articular space, which is a closed compartment. A soft tissue injection targets structures outside the joint capsule — tendons, bursae, ligaments, or trigger points. Mistaking one for the other leads to suboptimal outcomes and unnecessary complications.
How To Approach This Properly
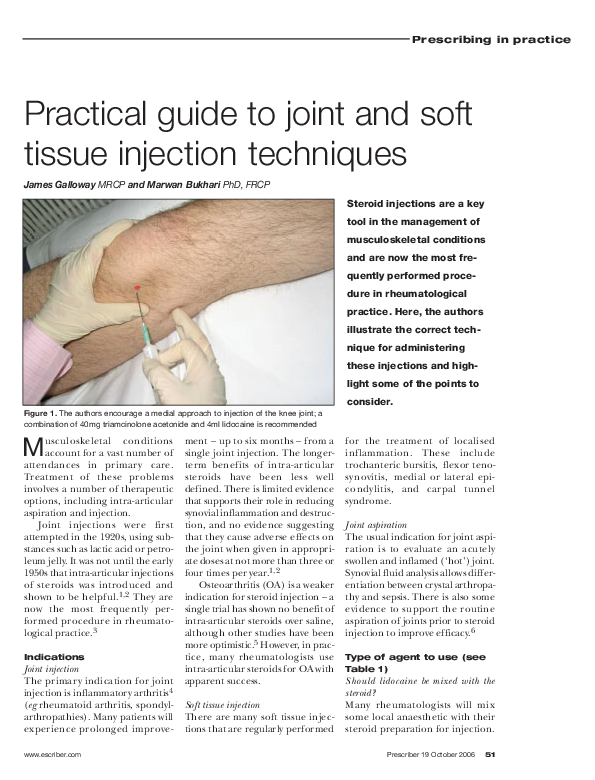
Start with anatomy. Not the kind you read once and forget, but the kind where you can visualize the relationship between the needle path and nearby neurovascular structures. Palpate the landmarks on a live patient before attempting anything. Mark the entry point with a pen while the patient is standing or in the position they will be during the procedure, because soft tissue shifts with gravity and muscle tension.For a knee injection, the lateral approach is generally safer than the medial approach if you are not using ultrasound guidance. The patellar tendon is a reliable landmark. Insert the needle just medial or lateral to the tendon, angling slightly toward the center of the joint. Advance slowly. If you meet resistance at about one centimeter, back off. You may be in the infrapatellar fat pad, not the joint space. Aspirate to confirm you are not in a vessel. Inject a small amount of anesthetic first to confirm spread within the joint. The fluid should move freely. If it does not, you are likely in the wrong plane. Shoulder injections require a different mindset entirely. The rotator interval approach and the posterior approach are both valid, but the posterior approach is more forgiving for less experienced operators. Have the patient sit upright with their arm resting across their abdomen. Identify the coracoid process anteriorly and the spine of the scapula posteriorly. Insert the needle between these two landmarks, aiming medially and slightly inferiorly. You should feel a distinct pop as you penetrate the joint capsule. Inject only what the joint can accommodate. Pushing more than five to seven milliliters usually means you have gone extra-articular or into a bursal space, which changes the therapeutic effect entirely. Wrist injections are tricky because the space is small and multiple flexor and extensor compartments exist. The dorsal approach to the radiocarpal joint is standard. Pass between the Lister's tubercle and the extensor pollicis brevis. Direction is critical here. Aim slightly ulnar and distal to avoid the radial artery. A 25-gauge needle is sufficient. Do not use a larger gauge thinking you need rigidity — it only increases tissue trauma and patient discomfort.
Get the Full Details

Ultrasound guidance has changed the landscape significantly. It is not mandatory, but it reduces complication rates and improves accuracy, especially in deeper joints like the hip and shoulder. I switched to routine ultrasound for hip injections after a case where blind technique deposited the medication into the iliopsoas bursa instead of the hip joint. The patient reported no improvement for three weeks. Retracing with ultrasound showed the entire volume sitting in the wrong compartment. It took me eight seconds to see it on imaging. Eight seconds that could have prevented weeks of a patient's frustration.
Complications And What To Avoid
Post-injection flare occurs in approximately ten to fifteen percent of corticosteroid injections. The patient experiences increased pain for twenty-four to forty-eight hours after the procedure. It is self-limiting but often mistaken for infection. Differentiating between the two is straightforward if you know what to look for. Infection presents with progressive pain, erythema, warmth, and systemic symptoms like fever. A flare is maximal at six to twelve hours and begins resolving by forty-eight hours. Ice and oral analgesics manage a flare adequately.Tendon rupture is a rare but serious risk when injecting near weight-bearing tendons. The Achilles and patellar tendons have limited evidence supporting corticosteroid injection due to this risk. If you must inject these areas, use the lowest effective dose, avoid intratendinous placement entirely, and counsel the patient appropriately about activity restriction afterward. Many practitioners overlook the counseling part. Intra-articular cartilage damage from repeated steroid injections is a long-term concern. Three to four injections per year per joint is the general upper limit. More than that and the cumulative effect on chondrocyte metabolism becomes difficult to ignore. The data is not definitive, but the clinical consensus is cautious. Allergic reactions to the components of the injection are uncommon but documented. Preservatives like benzyl alcohol and methylparaben are the usual culprits, not the steroid itself. Have a protocol ready for anaphylaxis regardless of how unlikely it seems. I keep epinephrine auto-injectors accessible in my clinic. It is not about expecting the worst. It is about being prepared when something unexpected happens.
Practical Constraints That Nobody Talks About
Patient body habitus is a major factor. Obese patients make landmark-based injections significantly more challenging. Subcutaneous fat displaces bony landmarks and requires longer needles. A two-inch needle may not reach the joint space in a larger patient. I stopped guessing and started measuring with ultrasound when I encountered a patient whose suprapatellar pouch was over four centimeters deep from the skin surface. A standard one-and-a-half-inch needle simply could not get there. The injection ended up in subcutaneous tissue with zero therapeutic benefit. Coagulopathy and anticoagulant use are relative contraindications rather than absolute ones, but they require careful assessment. Continue or hold anticoagulants based on the specific agent, the joint being targeted, and the bleeding risk. Small joints like the wrist carry less bleeding risk than larger vascular joints. Compression post-procedure is standard practice.
Adequate time matters more than people realize. Rushing through a joint injection leads to mistakes. A thorough joint aspiration and injection typically takes five to fifteen minutes for an experienced operator. Less time than that and you are cutting corners. More time than twenty minutes on a straightforward case and something is probably wrong.
When To Choose Something Else
Joint and soft tissue injection is not appropriate for every condition. Septic arthritis requires aspiration for diagnostic analysis and immediate antibiotic treatment, not a steroid injection. Gout and pseudogout benefit from injection only after crystal analysis confirms the diagnosis and infection is ruled out. Neoplastic processes involving the joint are an absolute contraindication for diagnostic uncertainty. When the diagnosis is unclear, imaging and laboratory work come first. Injection without a working diagnosis is gambling with the patient's health.Physical therapy and load management should always be part of the treatment plan. An injection reduces symptoms temporarily. It does not correct biomechanical dysfunction or strengthen supporting structures. Patients who receive injections without addressing the underlying mechanical issue tend to return for repeat procedures within months. That is not a failure of the injection. It is a failure of the overall treatment approach. The evidence base for hyaluronic acid injections in knee osteoarthritis remains mixed across studies. Some guidelines recommend it, others do not. The cost is significantly higher than corticosteroid injections with no clear superiority in most head-to-head trials. I use it selectively for patients who cannot tolerate steroids or who have failed multiple steroid courses, but I do not present it as a first-line option. The best injections are the ones where the indication is clear, the technique is sound, and the patient understands what to expect. Everything else is just expense and risk without proportionate benefit.