Joint Commission Emergency Management Plan 4 Key Principles
Verma
2025-01-13
What the Joint Commission Actually Looks For in Your Emergency Plan
Most people treat the Joint Commission Emergency Management Plan 4 Key Principles as a checklist exercise. They fill out the templates, run the annual exercise, and hope nobody asks hard questions during the survey. That approach works until something actually happens and your plan falls apart because it was written to satisfy an evaluator rather than to function in reality.
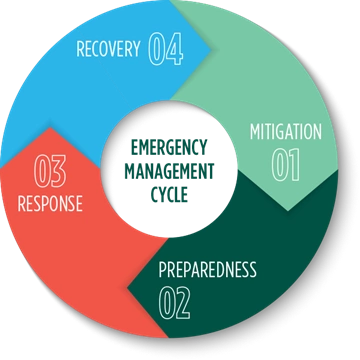
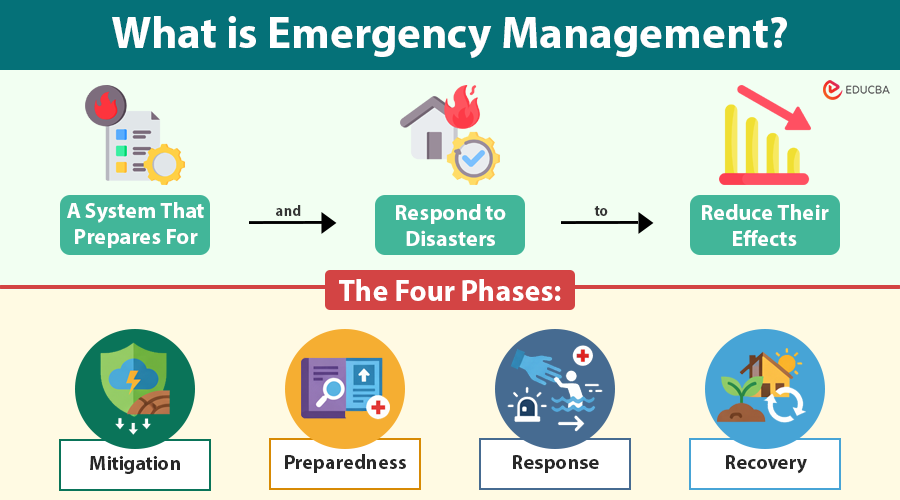
The four key principles are Mitigation, Preparedness, Response, and Recovery. That sequence matters because it reflects how real emergency management works from a practical standpoint, not just how textbooks organize it.
Joint Commission Emergency Management Plan 4 Key Principles Explained
Mitigation comes first and it is the most commonly misunderstood principle. People think mitigation means installing fire extinguishers and checking exit signs. It does, but that is the bare minimum. Real mitigation requires you to identify what could disrupt your facility and then make structural or procedural changes to reduce either the likelihood or the severity of that disruption. I worked at a hospital where we had a legitimate flood risk from a nearby river that flooded roughly every eight years. Our previous mitigation plan was a stack of sandbags in a closet and a hope-based timeline. The actual fix involved elevating critical electrical panels, installing backflow preventers on basement plumbing, and relocating our emergency supply cache to the second floor. That took about fourteen months and roughly $220,000. The Joint Commission was satisfied because we could show the risk assessment, the capital request, the work order, and the final inspection. They do not care about your sandbags. They care about evidence that you identified the risk and acted on it.
Preparedness is where most facilities accumulate the most paperwork without gaining real capability. Your emergency management plan needs to address communications, resource allocation, personnel training, and public coordination. The tricky part is that your EOP has to be living documentation, not a binders-worth-of-text-that-nobody-reads. I reviewed a plan for a 150-bed facility where the contact list was three years old, the mutual aid agreement with the neighboring county had expired, and the disaster supply inventory listed items we no longer stocked. The surveyor flagged twelve separate deficiencies in the preparedness section alone. The root cause was that nobody had assigned anyone the responsibility of reviewing and updating those documents on a schedule. After that survey, we implemented a quarterly review cycle with named owners for each section. It added roughly forty minutes of work per week across three people, but it eliminated the recurring deficiency pattern.
Response is the phase where your planning either holds up or it does not. Your response procedures need to address activation criteria, incident command structure, communication protocols, patient care continuity, and staff accountability. The Joint Commission specifically looks for evidence that your staff knows how to activate the plan and understand their roles during activation. The common failure mode here is that your EIP gets triggered only for catastrophic events. In practice, you need tiered activation levels that match the severity of the situation. A water main break on a Friday afternoon should trigger at least a partial activation, not sit in someone's desk until Monday morning when the plant finally responds.
Recovery is the phase nobody wants to think about until it is too late. Your recovery plan should address restoring operations, returning patients to normal care settings, documenting losses for insurance and regulatory purposes, and conducting after-action reviews. The Joint Commission expects to see a formal after-action process following any activation. This is where the practical gap shows up most often. I handled an activation after a chemical spill at a nearby industrial facility that required us to shelter in place for approximately eleven hours. Our after-action report took six weeks to complete because we had no designated writer and no deadline built into the plan. The next year we assigned the quality improvement director to own the AAR process with a mandatory 30-day turnaround. The revised report came back in eighteen days and identified four specific corrective actions that were implemented before the next annual exercise.
How to Build Something That Actually Works
Start with a hazard vulnerability analysis that covers natural disasters, technological hazards, and human-caused incidents specific to your region and facility type. A rural critical access hospital in Oklahoma has a very different risk profile than a urban trauma center in Florida. Your HVA should reflect that reality and your plan should reference it explicitly.
Build an emergency operations plan with clear activation thresholds. Define what event triggers full activation versus partial activation versus monitoring status. Include your incident command structure with named alternates for each role, not just titles. When you lose your charge nurse to exposure, you need to know immediately who steps in. Having "supervising nurse" listed as a role sounds fine on paper until you realize three people with that title are off-site at a conference.
Establish communication protocols that work when infrastructure fails. Your primary communication method will probably fail during a significant event. Your secondary should be something entirely different. If your primary is phone and your secondary is also phone through the same carrier, you have not built redundancy. We moved to a hybrid system where our primary was our internal mass notification platform, our secondary was satellite phones for key personnel, and our tertiary was a designated meeting point with a check-in board. This took about three weeks to implement and cost roughly $8,000 for equipment and testing.
Conduct training and exercises on a regular schedule. The Joint Commission requires annual drills that test different functions of your plan. Full-scale exercises every three years. The requirement is straightforward, but the execution is where facilities stumble. Running an exercise just to check the box produces worthless results. Design your exercises around the vulnerabilities you identified in your HVA. If your HVA shows that power loss is your highest probability risk, your annual exercise should stress that scenario specifically.
Maintain mutual aid agreements with nearby facilities and local emergency management agencies. These agreements need to be current, signed, and tested. An unsigned agreement or one that references an agency that no longer exists will not impress a surveyor. Verify the contact person listed in each agreement exists and has authority to commit resources.
Document everything. The Joint Commission evaluates based on what you can demonstrate, not what you intend to do. Risk assessments, training records, exercise evaluations, after-action reports, corrective action plans, plan revisions with dates and version numbers. Your documentation trail should tell a coherent story of continuous improvement.
The main limitation of the Joint Commission emergency management framework is that it sets a floor, not a ceiling. Meeting the requirements does not guarantee you are prepared for a catastrophic event that overwhelms your region's capacity. The framework works well for routine emergencies and moderate-scale incidents. For events like a pandemic or a major earthquake that takes out regional infrastructure, you will need to supplement it with state and federal coordination protocols that operate on a completely different timescale. Some facilities have found value in adding CDC Hospital Preparation Index or HAN alerts integration into their monitoring systems to catch threats before they reach the activation threshold defined in their EOP.
Gallery Joint Commission Emergency Management Plan 4 Key Principles
The Joint Commission: Emergency Management Plans and … / the-joint-commission-emergency ...
The Joint Commission Emergency Management Toolkit | Joint Commission
The 4 Elements Of The Emergency Management Plan - HSEWatch
Phases of emergency management with linkage to the Joint Commission... | Download Scientific Diagram
Emergency Management | Phases, Roles & Key Principles