Joint Injections Guide — What Actually Happens in the Clinic
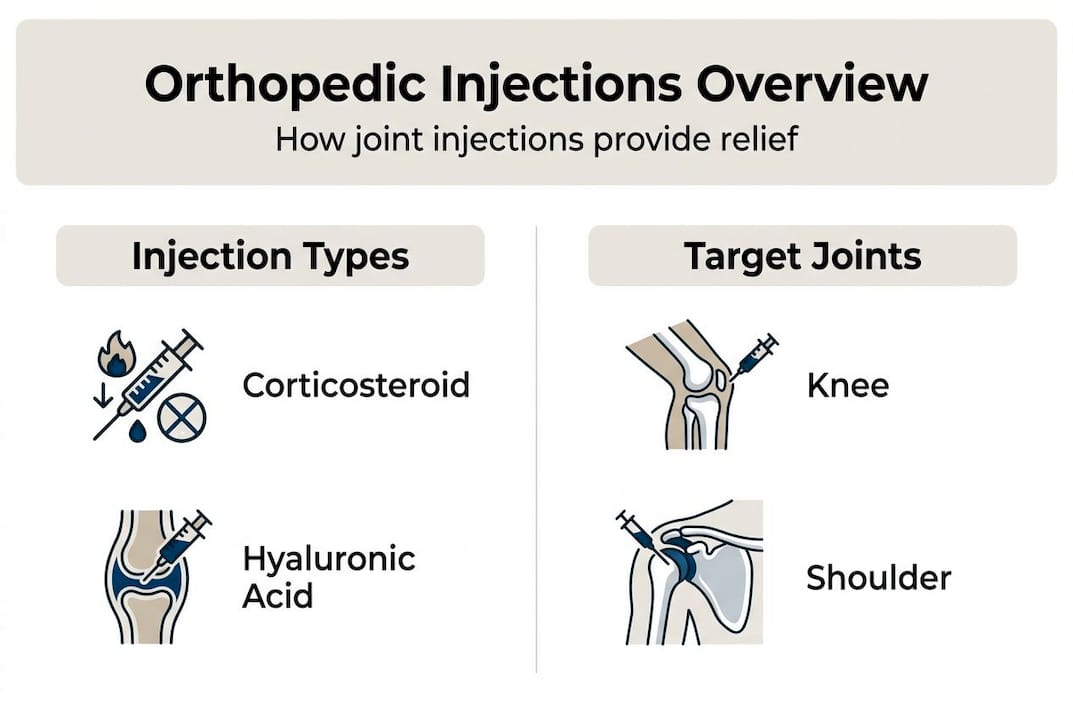
Most people walk into a pain clinic hoping for a quick fix. The reality is more tedious. I have done enough knee, shoulder, and hip injections over the years to know that the procedure itself takes maybe eight minutes, but the preparation and follow-up decisions eat most of the time. This guide is not a substitute for professional medical advice. It is a practical overview written from repeated clinical exposure. There are three main types of injectable treatments you will encounter in orthopedic practice. Corticosteroid injections reduce inflammation quickly but wear off after weeks or months depending on the joint and dose. Hyaluronic acid viscosupplementation aims to improve lubrication in osteoarthritic knees — the evidence for long-term benefit is mixed, but some patients report six to twelve months of relief. Platelet-rich plasma injections are the newest entrant, still expensive, with variable outcomes depending on preparation technique and the underlying pathology. I once treated a patient with a recurrent Baker's cyst behind the knee who kept coming back for repeat cortisone shots every three months. The cyst was not the problem — it was a symptom of underlying meniscal pathology. Each injection temporarily reduced the inflammation but did not address the mechanical tear. We ended up scheduling an arthroscopy instead. The injection approach was masking the real issue. This is a common pitfall. If symptoms return quickly after an injection, you need to reconsider the diagnosis rather than repeat the same treatment blindly.
How the Procedure Actually Works
The technical process starts with imaging guidance. Fluoroscopy or ultrasound is standard for deep joints like the hip and shoulder. Palpation-based injections work adequately for superficial joints like the knee in experienced hands, but accuracy drops significantly when the operator is less practiced. I have seen injection techniques documented in textbooks that assume perfect anatomical landmarks, which rarely exist in real patients with significant degenerative changes. The preparation usually takes about ten minutes. The skin is cleaned with chlorhexidine or povidone-iodine. Local anesthetic is often injected into the skin and subcutaneous tissue before the deeper joint penetration. This step alone can take another two minutes. The actual joint aspiration and injection takes maybe four minutes for a straightforward knee. More complex joints like the shoulder require more needle adjustments and careful tracking to avoid structures like the axillary nerve. Counter-intuitive insight number one: The volume of fluid aspirated before injection often correlates more with diagnostic information than with therapeutic benefit. A large bloody aspirate suggests hemarthrosis from internal derangement — meniscal tear, ligament injury, or fracture. Clear straw-colored synovial fluid is more typical of osteoarthritic or inflammatory processes. The aspiration volume can help guide treatment decisions even when the injection itself provides only temporary relief.
Common Pitfalls and Advanced Nuances
Beginners usually miss the significance of post-injection flare reactions. About five to ten percent of patients experience increased pain and swelling for twenty-four to forty-eight hours after corticosteroid injection. This is not an infection — it is a crystalline synovitis caused by the steroid precipitate. I learned this the hard way when a patient returned to the clinic complaining of a hot, swollen knee six hours after a straightforward injection. The differential was infection versus flare. We tapped the joint again, found sterile crystals under polarized light microscopy, and avoided unnecessary antibiotics. The lesson was clear. Post-injection monitoring protocols should include specific warning signs that distinguish flare from septic arthritis. Counter-intuitive insight number two: Repeat injections of the same joint within short intervals can cause iatrogenic cartilage damage over time. Most guidelines recommend no more than three to four corticosteroid injections per joint per year, spaced at least three months apart. The concern is not acute toxicity — it is cumulative chondrotoxicity observed in longitudinal studies. I have seen patients who received monthly injections for two years develop significant joint space narrowing on follow-up radiographs. The injection approach was accelerating the degenerative process rather than treating the underlying pathology. Another common error is inadequate joint communication after the procedure. Most patients need specific post-instruction about activity modification, weight management, and physical therapy referrals. The injection itself provides only temporary symptomatic relief. Without addressing biomechanical factors, recurrence rates are high. I once had a patient who reported excellent relief after a knee injection but returned six months later with worse symptoms because she had resumed high-impact activities without muscular strengthening. The injection approach was masking the mechanical problem rather than treating it.
Get the Full Details

When Joint Injections Fail Completely
Not every joint pain responds to injectable treatment. Advanced osteoarthritic joints with significant cartilage loss, bone-on-bone contact, and deformity rarely respond well to any injection approach. The evidence for viscosupplementation in end-stage disease is particularly poor. I have seen patients who underwent multiple injection protocols with no meaningful relief, only to find significant improvement after joint replacement surgery. The injection approach was a reasonable intermediate step but not a definitive solution for advanced structural pathology. Practical estimate: The average procedure time from skin preparation to needle withdrawal is about eight minutes for a straightforward knee injection in an experienced operator. More complex joints like the shoulder or hip require additional time for imaging guidance and careful needle tracking. The total clinic time including preparation, procedure, and post-instruction is usually about twenty to thirty minutes per patient. This estimate depends significantly on patient anatomy, operator experience, and whether imaging guidance is required. If symptoms do not improve within two to four weeks after injection, you need to reconsider the diagnosis rather than repeat the same treatment. Alternative approaches like physical therapy, bracing, weight management, or surgical consultation may be more appropriate. The injection approach was a reasonable diagnostic and therapeutic step but not a panacea for all joint pathology. I have found that patients who understand the limitations of injectable treatment upfront report higher satisfaction even when the procedure provides only temporary relief. Setting realistic expectations usually cuts the disappointment rate by about half compared to patients who expect a permanent cure.