Measuring JVP at the Bedside
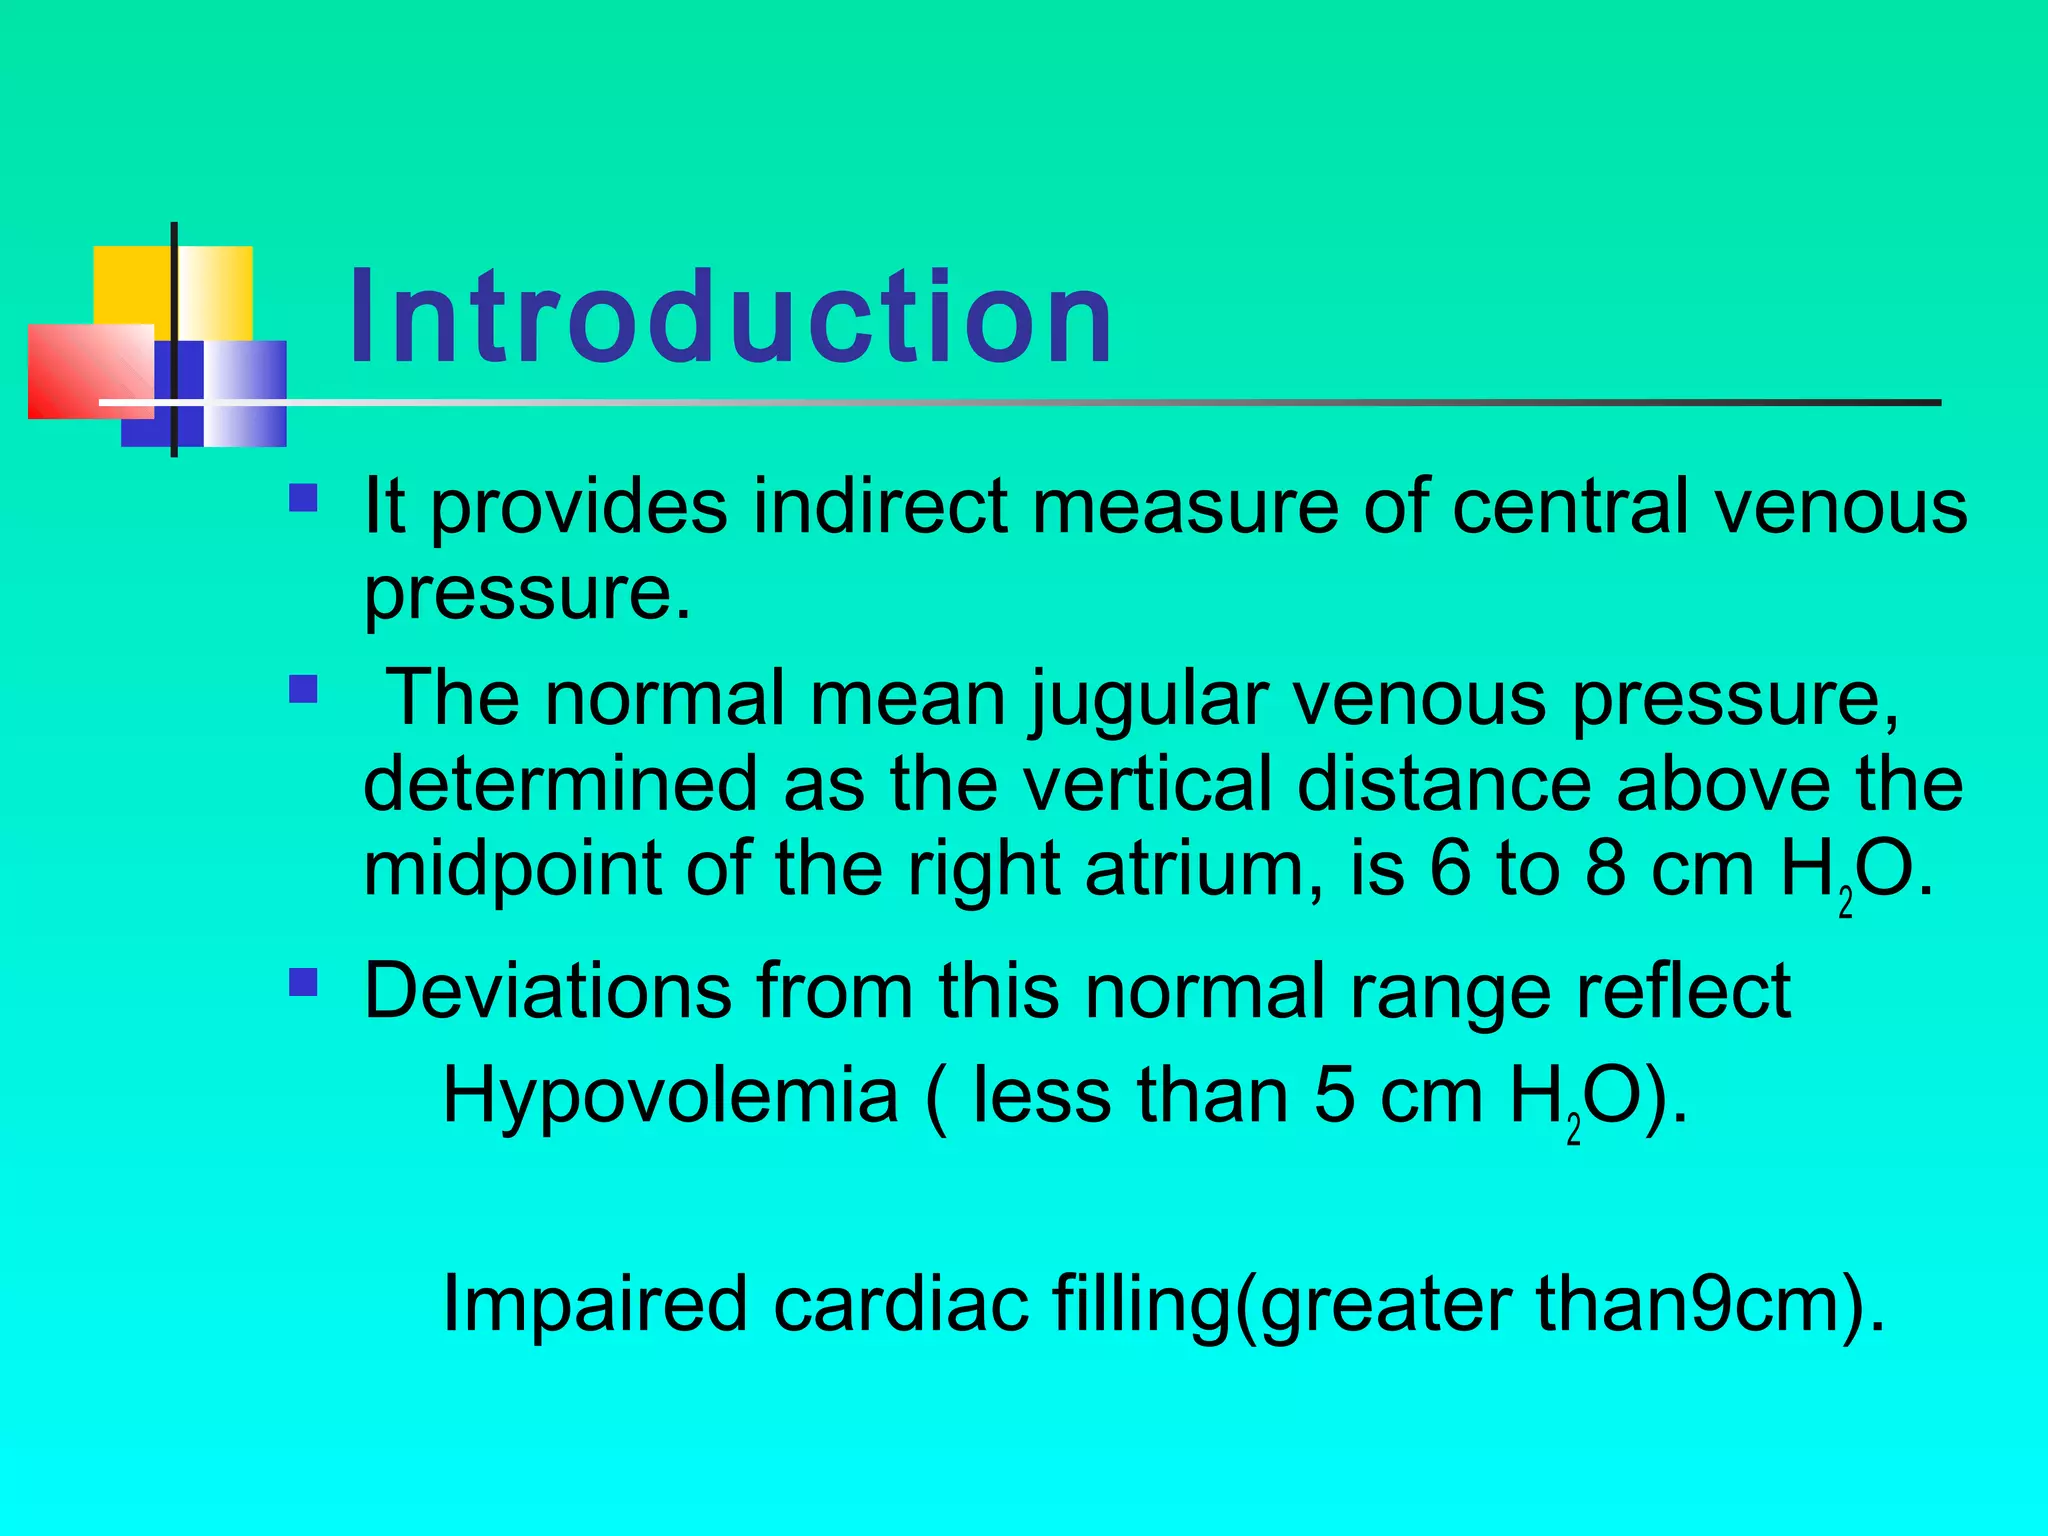
The jugular venous pressure is measured by observing the pulsation in the right internal jugular vein while the patient is positioned at a 30 to 45-degree angle. You are not actually measuring a number directly with an instrument during a routine clinical exam. You are estimating the height of the venous column above the sternal angle and then adding that to the known vertical distance from the sternal angle to the right atrium. The standard reference point puts the sternal angle approximately 5 cm above the right atrium in most adult patients. The normal range for jugular venous pressure is typically cited as 6 to 8 cm H2O when measured from the right atrium, or 2 to 3 cm of vertical column above the sternal angle when using the external landmark method. I use cm H2O because that is what the column height actually represents, and most textbooks and clinical references converge on that same range.
Understanding the Jugular Venous Pressure Normal Range
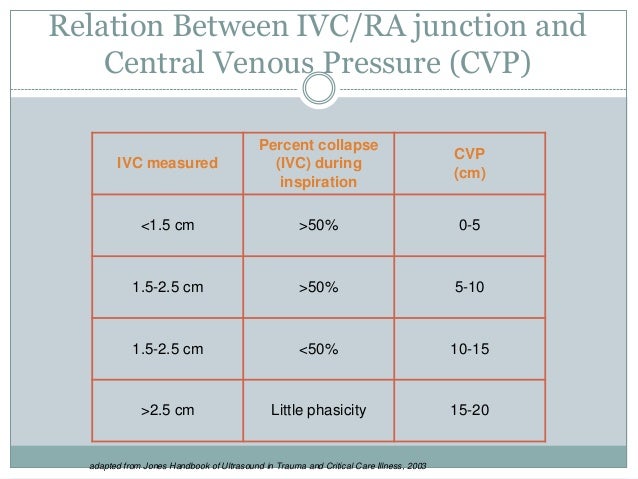
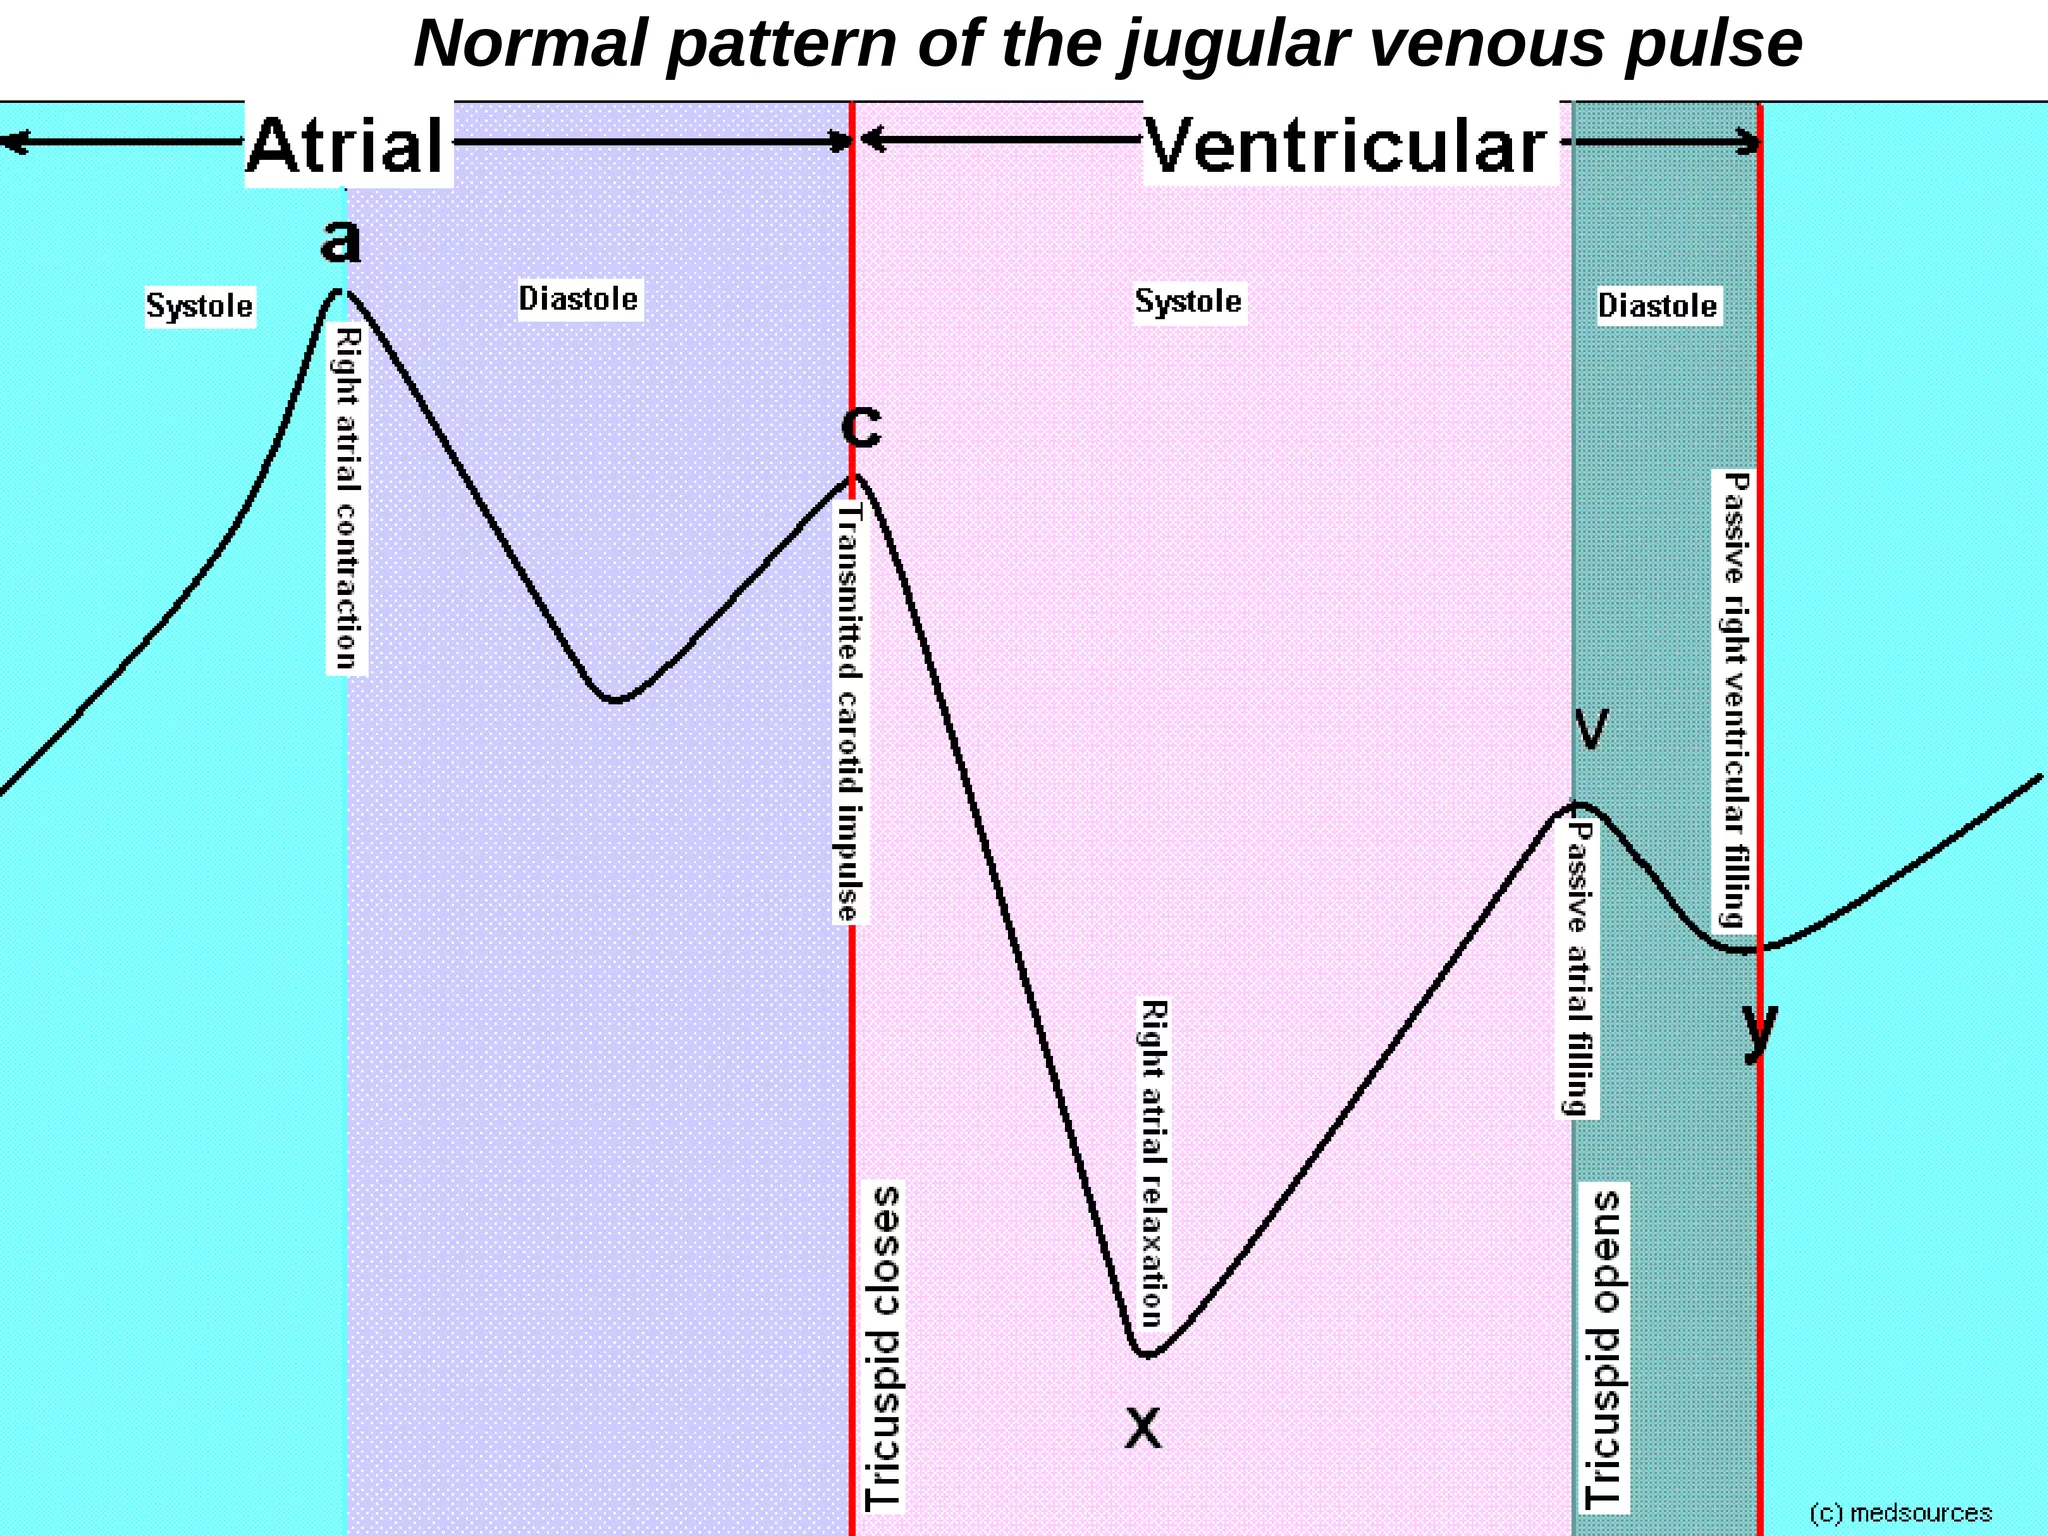
What people often miss is that the JVP tracing has distinct waves you can use as verification points. The a wave corresponds to right atrial contraction, the c wave to tricuspid valve bulging during ventricular systole, and the v wave to passive venous filling against a closed tricuspid valve. The x descent follows atrial relaxation, and the y descent occurs when the tricuspid valve opens and blood flows into the right ventricle. If you can clearly identify the a wave and the y descent, your angle and lighting are probably correct. I ran into a problem a few years ago with a post-cardiac surgery patient who had persistent neck fullness but a JVP that refused to track with respiration. The initial reading suggested elevated central venous pressure around 14 cm H2O, which did not match the clinical picture at all. The patient had significant mediastinal scar tissue from recent sternotomy, and the internal jugular vein was partially compressed by postoperative hematoma and fibrosis along the expected venous pathway. The waveform was dampened and the apparent column height was artificially elevated because the blood was pooling proximal to a partial obstruction rather than reflecting true right atrial pressure. The workaround was straightforward. I switched to assessing the left internal jugular vein, which had a different anatomical course and was not compromised by the surgical site. The left side showed a clean waveform with a normal y descent and an estimated JVP in the 7 cm H2O range, consistent with the patient's hemodynamics. I also confirmed with a quick bedside echocardiogram that the inferior vena cava was plethoric but collapsible, which supported the lower estimate. This is a useful reminder that the JVP is only as good as the venous pathway you are actually visualizing, and a unilateral obstruction can completely derail your reading if you do not check both sides.
Another thing beginners routinely get wrong is the angle of the neck. If the patient's head is turned sharply to one side, you compress the ipsilateral jugular vein and the reading jumps up regardless of true central pressure. I have seen residents report elevated JVP in trauma patients simply because the cervical collar or head positioning was occluding the vein. Rotate the head to neutral, have the patient take a normal breath and hold it, and recheck before you commit to a number. The lighting matters more than most people admit. A dim room makes the jugular pulsation nearly invisible, and you end up guessing or conflating the carotid artery with the jugular vein. The carotid pulse is impalpable or barely palpable, does not obliterate with gentle pressure over the angle of the jaw, and is not affected by positioning. The jugular is phasic, disappears with light compression, and its level changes with posture. I use a penlight angled across the neck rather than shining it directly down, which makes the meniscus of the column much easier to see. Obese patients present a different set of issues. Subcutaneous fat attenuates the surface anatomy and makes the sternal angle harder to palpate reliably. When I cannot find the sternal angle with certainty, I estimate the manubriosternal joint by feeling for the second rib and tracing down, but I note the uncertainty in the chart. In those cases, I tend to rely more on the respiratory variation and waveform morphology than on an absolute centimeter measurement, because the landmark error can easily add or subtract 2 to 3 cm from the final number.
Get the Full Details

There are also conditions where the jugular venous pressure is misleading even when measured correctly. Constrictive pericarditis and cardiac tamponade both affect the waveform in recognizable ways, but the absolute height alone cannot differentiate them. Tamponade typically shows a prominent y descent that is blunted, while constriction shows a rapid and deep y descent with a prominent x descent. Mixed patterns occur, and echocardiography is necessary either way. The JVP is a screening tool, not a definitive diagnostic test for any single pathology. If you need a more accurate measurement in complex cases, invasive central venous catheterization or pulmonary artery catheterization gives you a direct pressure reading. Those methods carry their own risks including infection, pneumothorax, and arrhythmia, so they are not routine replacements for physical examination. The bedside JVP remains useful because it is fast, noninvasive, and when done carefully, it tracks trends reasonably well even if the absolute value has some margin of error.