What Just Culture Actually Looks Like When You Stop Reading the Brochure
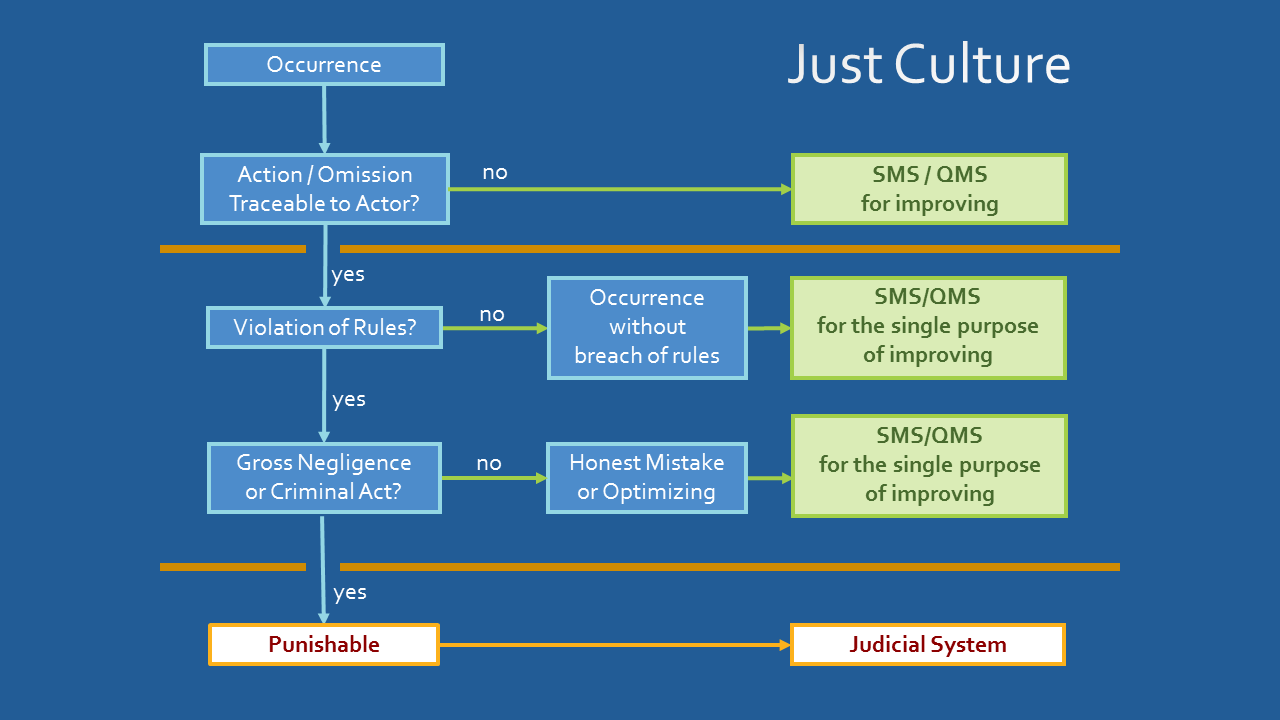
Most organizations implement just culture incorrectly because they conflate accountability with blame. That distinction matters more than anything else in this process. A Just Culture Guide exists to help leadership separate intentional misconduct from system-induced errors, but getting there requires abandoning the instinct to punish first and investigate later. Just culture originated in healthcare safety research, specifically from the work of David Marx and others who studied how organizations respond to medical errors. The framework classifies human behavior into three categories: human error, at-risk behavior, and reckless behavior. Each category demands a different managerial response. Human error is when someone makes a mistake despite having good intentions and adequate training. A nurse double-checks a dosage calculation and still misreads the decimal point. The appropriate response here is not discipline. It is fixing the system that allowed the error to occur. You streamline the medication dispensing process. You add barcode scanning. You redesign the label to reduce visual confusion.
At-risk behavior involves choices that increase danger without obvious benefit to anyone. A technician skips a routine safety check because they have done the task ten thousand times and nothing has ever gone wrong. The response to at-risk behavior is coaching, not punishment. The person needs to understand the gap between perceived safety and actual safety, and they need practical alternatives that are easier than the risky shortcut. Reckless behavior is when someone consciously disregards a substantial and unjustifiable risk. This is the category that warrants disciplinary action. A manager falsifies inspection records knowing they have not been completed. That crosses a line that coaching cannot fix. I spent roughly fourteen months building a just culture program for a regional hospital system. The hardest part was not designing the framework. It was convincing senior leadership that promoting reporting required actually stopping the automatic referral of incident reports to HR for disciplinary review. We had an internal policy that flagged every near-miss involving patient interaction for investigation. That policy destroyed psychological safety overnight. Staff stopped reporting incidents within three weeks. We removed that requirement and replaced it with a threshold-based review process. Reporting volume increased by 340% in six months.
Common Mistakes That Derail Just Culture Implementation
The most damaging mistake I see is using just culture as a public relations exercise while maintaining zero-tolerance policies underneath. You can post the framework on your intranet and hold the annual training session, but if the VP of Nursing still refers every chart error to HR, the program is theater. People notice the contradiction quickly and they learn to hide their mistakes instead. Another pitfall is failing to train frontline supervisors. The framework only works if the person receiving the incident report knows how to classify the behavior correctly. A unit manager who interprets at-risk behavior as reckless behavior because they are frustrated with recurring compliance issues will systematically punish staff through the back door. I have seen this happen repeatedly. The workaround is mandatory calibration sessions where supervisors review de-identified case examples together and reach consensus on classification before they ever handle a real report. You should also expect resistance from certain employee groups. Nurses and physicians often view just culture as soft on accountability. Technicians and administrative staff often view it as insufficient protection from managerial overreach. Both perspectives have merit. The framework addresses both, but you have to articulate that clearly to each audience rather than using the same message for everyone.
Get the Full Details

What to Expect When Things Break
Just culture does not eliminate errors. It changes how you respond to them. In my experience, error rates typically increase during the first six to twelve months after implementation because people finally feel safe enough to report what was already happening. Leadership sometimes interprets this spike as proof the program failed. It is the opposite. The data was always there. It was just invisible. The framework also struggles with ambiguous cases that fall between categories. I encountered a situation where a pharmacist compounded a medication incorrectly due to a formula sheet that had been recently updated but not redistributed. Was this human error? At-risk behavior, since the pharmacist could have verified the current version? Or a system failure because the distribution process was flawed? The classification depended entirely on whether you examined individual responsibility or organizational process first. I resolved it by classifying it as system failure and using the incident to audit every medication reference document across three facilities. That took eight weeks. The alternative would have been disciplining the pharmacist, which would have solved nothing.
Practical Steps to Build Your Framework
Start by auditing your current incident response policies. Look for any language that mandates automatic discipline or treats all errors identically. Replace categorical language with decision trees that force classification before any action. A simple flowchart asking whether the behavior was intentional, whether the risk was obvious, and whether the person had the knowledge and resources to avoid it will catch most ambiguities. Train your incident investigation team on behavioral science basics. They do not need a degree, but they need to understand cognitive load, normalization of deviance, and the difference between active failures and latent conditions. Without that foundation, they will default to blaming individuals because it is faster and feels more satisfying to management. Measure the right things. Track reporting volume, classification distribution, time from report to response, and employee sentiment on psychological safety. Do not track discipline rates as a success metric. If discipline rates drop to near zero after implementation, that is either a perfectly behaved organization or a broken reporting system. Verify which one it is.
A properly implemented just culture framework reduces litigation exposure over time because early reporting gives you visibility into systemic problems before they cause harm. It also improves staff retention in high-stress environments. People stay where they believe they will be treated fairly when something goes wrong. That is not idealism. It is operational reality.