Understanding the Thoracic Cage Without Losing Your Mind
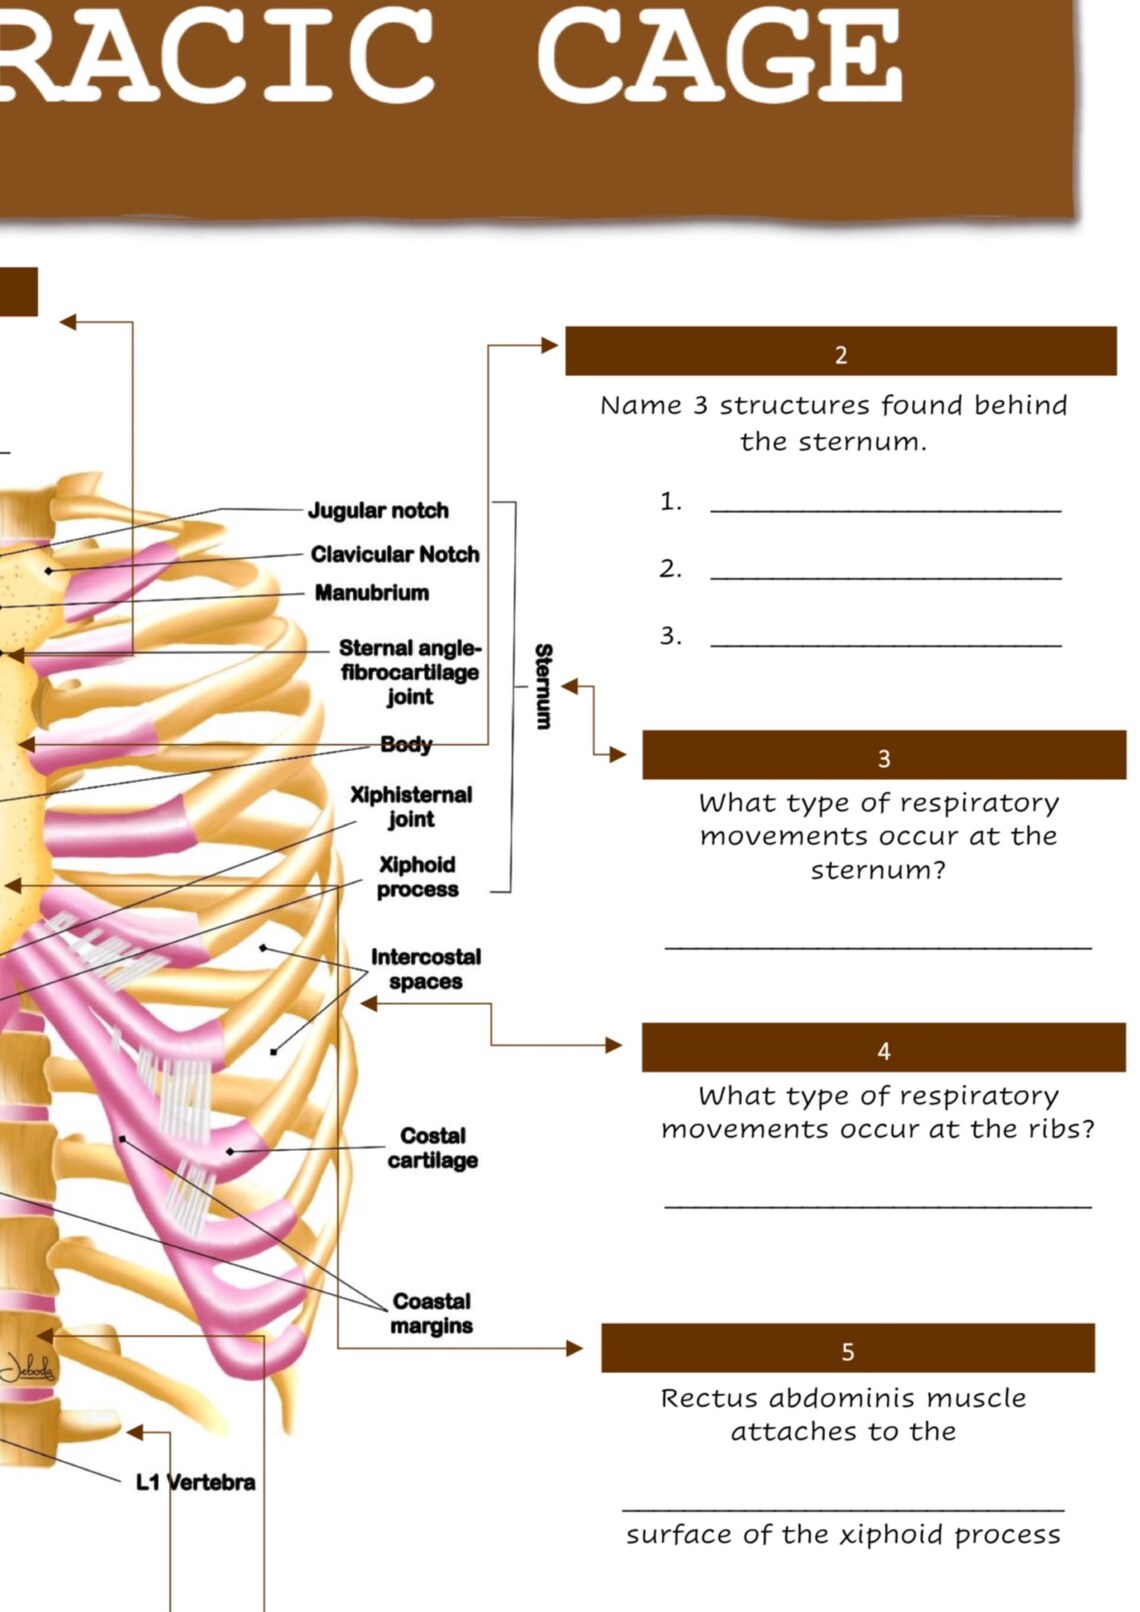
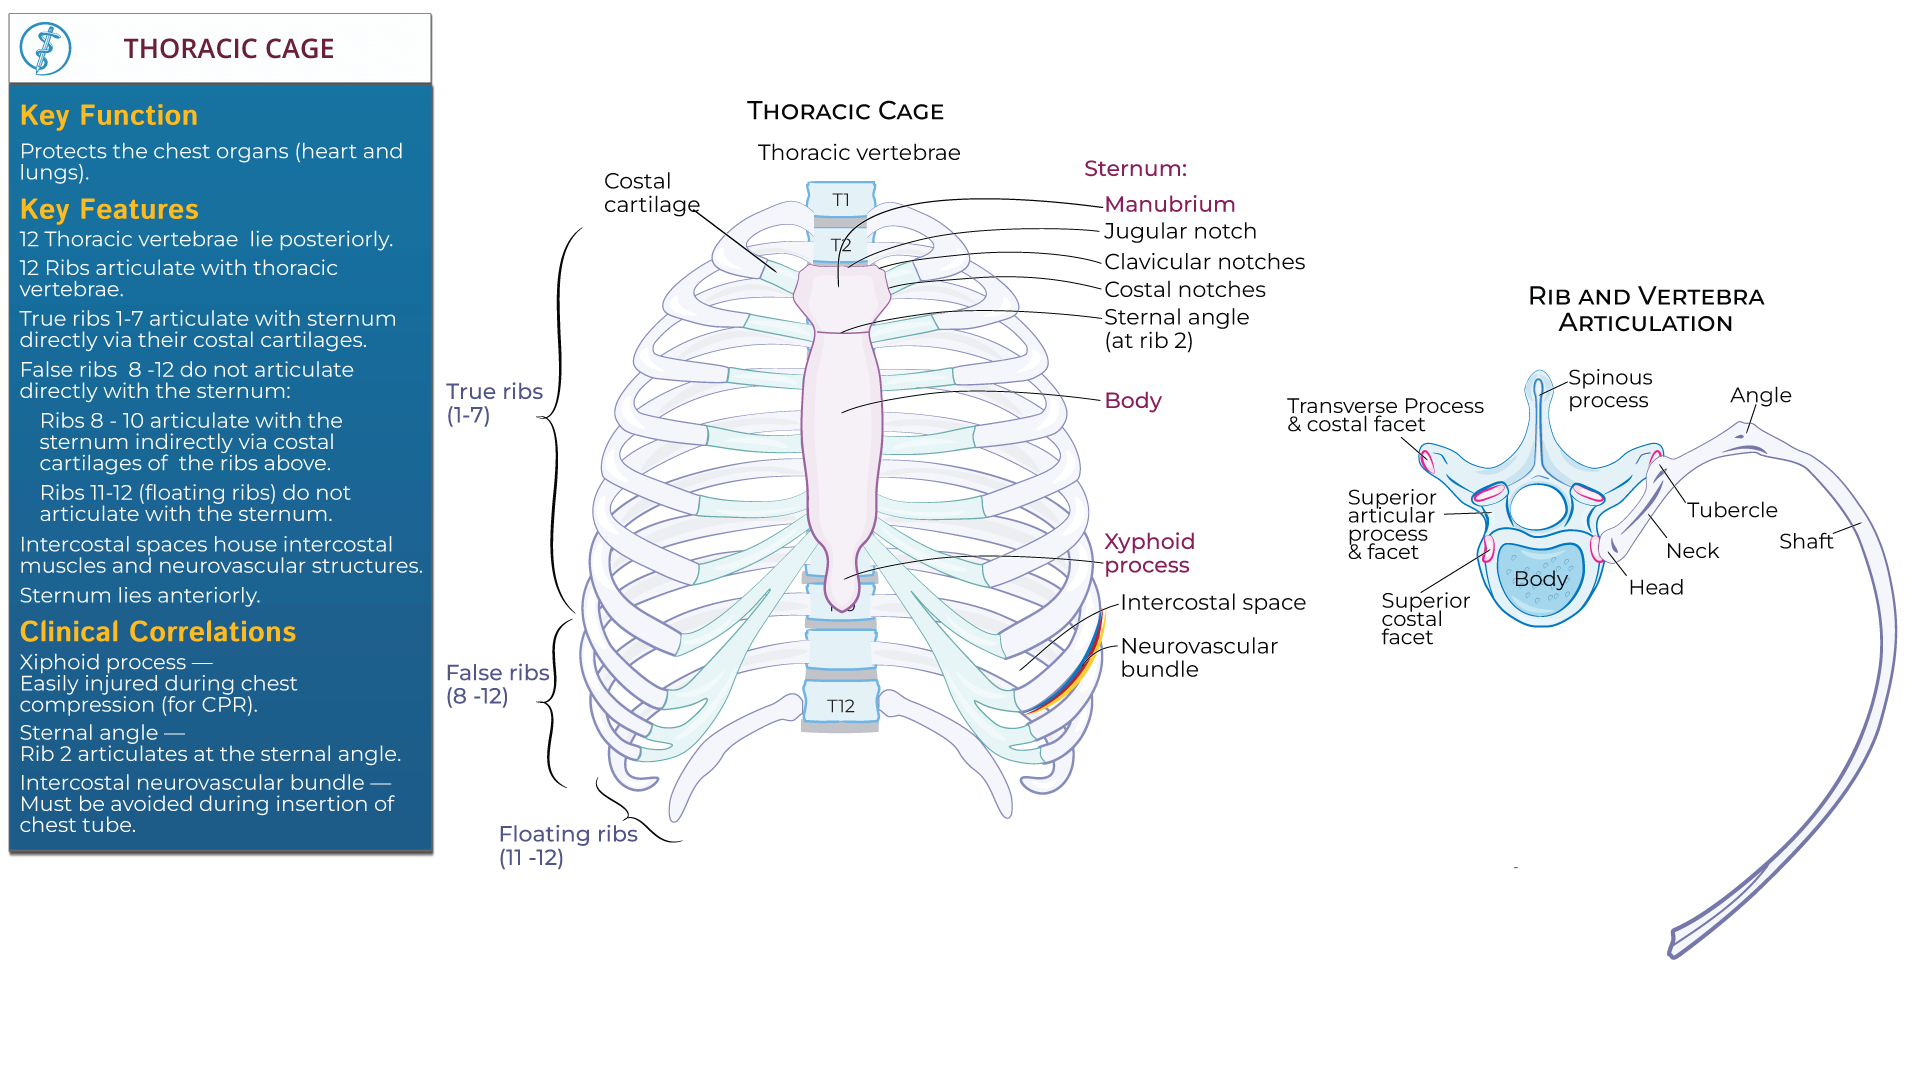
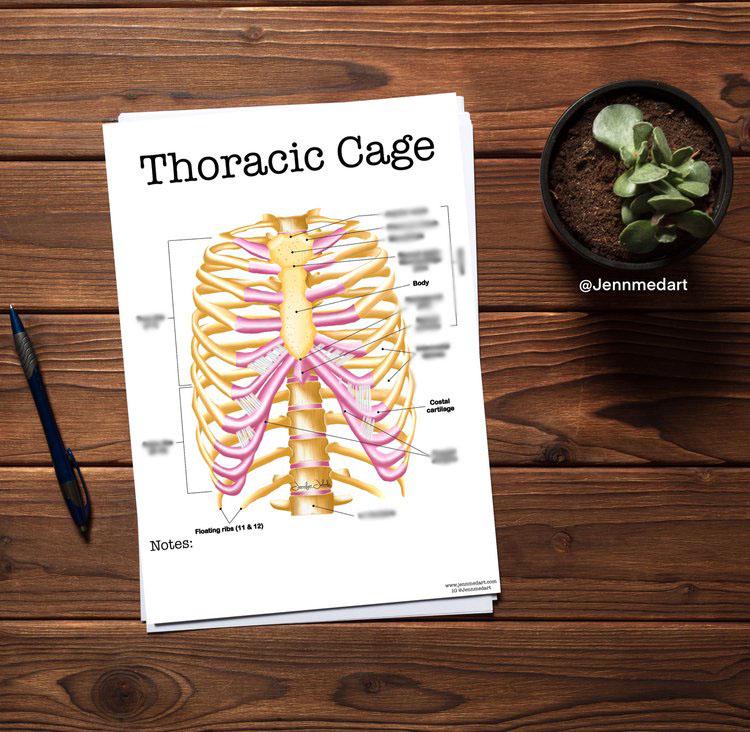
The thoracic cage is one of those anatomy topics that looks simple on paper and falls apart when you actually need to identify every landmark under exam pressure. I put together a detailed Key To Thoracic Cage Study Guide after watching too many students fail practical osseous identification because they only memorized names without context for location and function. This resource breaks the thoracic cage into three structural components: the true ribs (pairs 1 through 7), the false ribs (pairs 8 through 10), and the floating ribs (pairs 11 and 12). That basic categorization shows up on every midterm. The guide goes further though, mapping costal cartilage attachments, sternal angle landmarks, and the clinical significance of rib fractures at common break points. Most textbook chapters skip the detail about why the angle of Louis matters beyond being a surface landmark. The sternoclavicular joint versus the costochondral junction distinction trips people up constantly. The study guide includes labeled diagrams showing the difference between the manubrium, body, and xiphoid process with their corresponding costal notch counts.
I spent three semesters grading practical exams before I realized the pattern. Students could name the ribs but couldn't differentiate a first rib from a second on sight. First ribs are flat, broad, and have a subclavian groove. Second ribs have the tuberosity for the serratus anterior. These features don't show up in most simplified charts. My guide flags them explicitly with high-resolution bone photographs rather than illustrations, because drawings tend to smooth over the details that actually matter.
How to Use This Guide Effectively
Don't read it passively. The material works when you hold a bone, point to a landmark, and say the name out loud before moving to the next. Passive highlighting creates the illusion of knowing something. It isn't. The guide is organized top-down, starting with the sternum and working outward through the rib pairs. This mirrors how you'd actually palpate the anatomy on a living person, which matters for physical diagnosis questions that frequently appear on board exams and clinical skills assessments. Each section includes a quick-reference table matching rib number to its key identifying features. I ran into a specific problem that most guides completely miss. When students study rib articulations, they memorize the head, neck, tubercle, and shaft labels but then can't explain why ribs 1 through 10 articulate with the sternum differently. Ribs 1 through 7 have direct costal cartilage connections. Ribs 8 through 10 share cartilage with the rib above them. Ribs 11 and 12 terminate freely. This distinction determines whether a trauma scenario involves a flail chest or a more localized injury. I included a dedicated section on this after a student lost points on a clinical vignette because she couldn't reason through the fracture pattern.
Get the Full Details
Common Pitfalls That Will Cost You Points
The first pitfall is confusing the superior and inferior borders of a rib. The costal groove runs along the inferior inner border and contains the neurovascular bundle. If a question asks where intercostal needle decompression should avoid, the answer depends on knowing that exact anatomy. The guide marks this region in red on every rib diagram because getting it wrong is the difference between a passing score and a remedial lab. Another issue involves the thoracic inlet boundaries. People forget that the first thoracic vertebra, the first pair of ribs, and the superior border of the sternum form a complete ring. A question about structures passing through this inlet requires knowing all three boundaries simultaneously. The guide includes a quick sketch diagram that shows the spatial relationship without forcing you to open three different chapters to piece it together. Here is a blunt limitation I need to be honest about. The study guide does not replace cadaver dissection or hands-on palpation practice. It compensates for the fact that many programs simply do not allocate enough time for physical examination of skeletal specimens. If your course provides access to bones, go use them. This guide fills gaps; it does not eliminate the need for tactile familiarity. No amount of reading will substitute for holding a first rib and noticing how dramatically different it feels compared to a seventh.
What the Guide Includes
The current version contains forty-eight illustrated plates covering every major landmark, a forty-page summary document organized by rib number, and a self-test section with fifty identification questions pulled from actual clinical anatomy practicals. There is also a comparison table for common fractures including posterior versus anterior rib breaks and their associated organ injury risks. Prioritizing the self-test section early in your study schedule tends to reveal weak spots faster than rereading notes. I consistently see students score below seventy percent on the first attempt and then improve to ninety-plus after targeted review. The test answers include explanations that reference specific pages in the guide so you can immediately close the knowledge gap. Access the full Key To Thoracic Cage Study Guide through the usual academic resource channels or reach out if your program does not yet have a copy. The material updates periodically as new edition textbooks shift their emphasis, and the latest revision addresses the most common questions from the 2024 and 2025 testing cycles.