Striking the Patellar Tendon: What Actually Happens and Where People Mess It Up
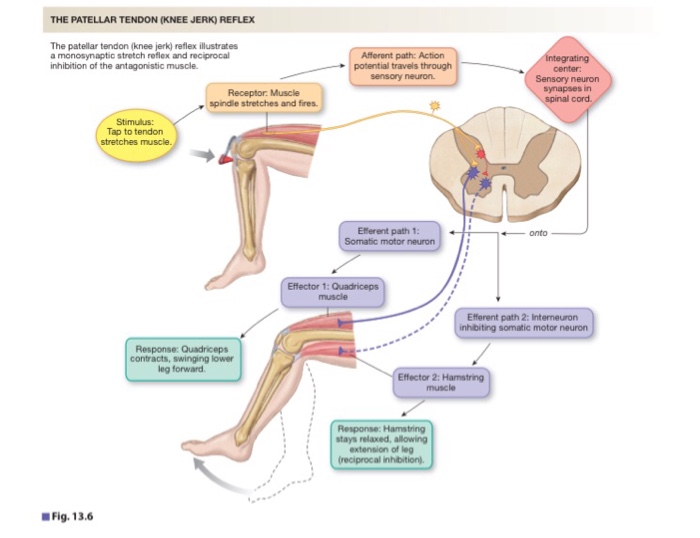
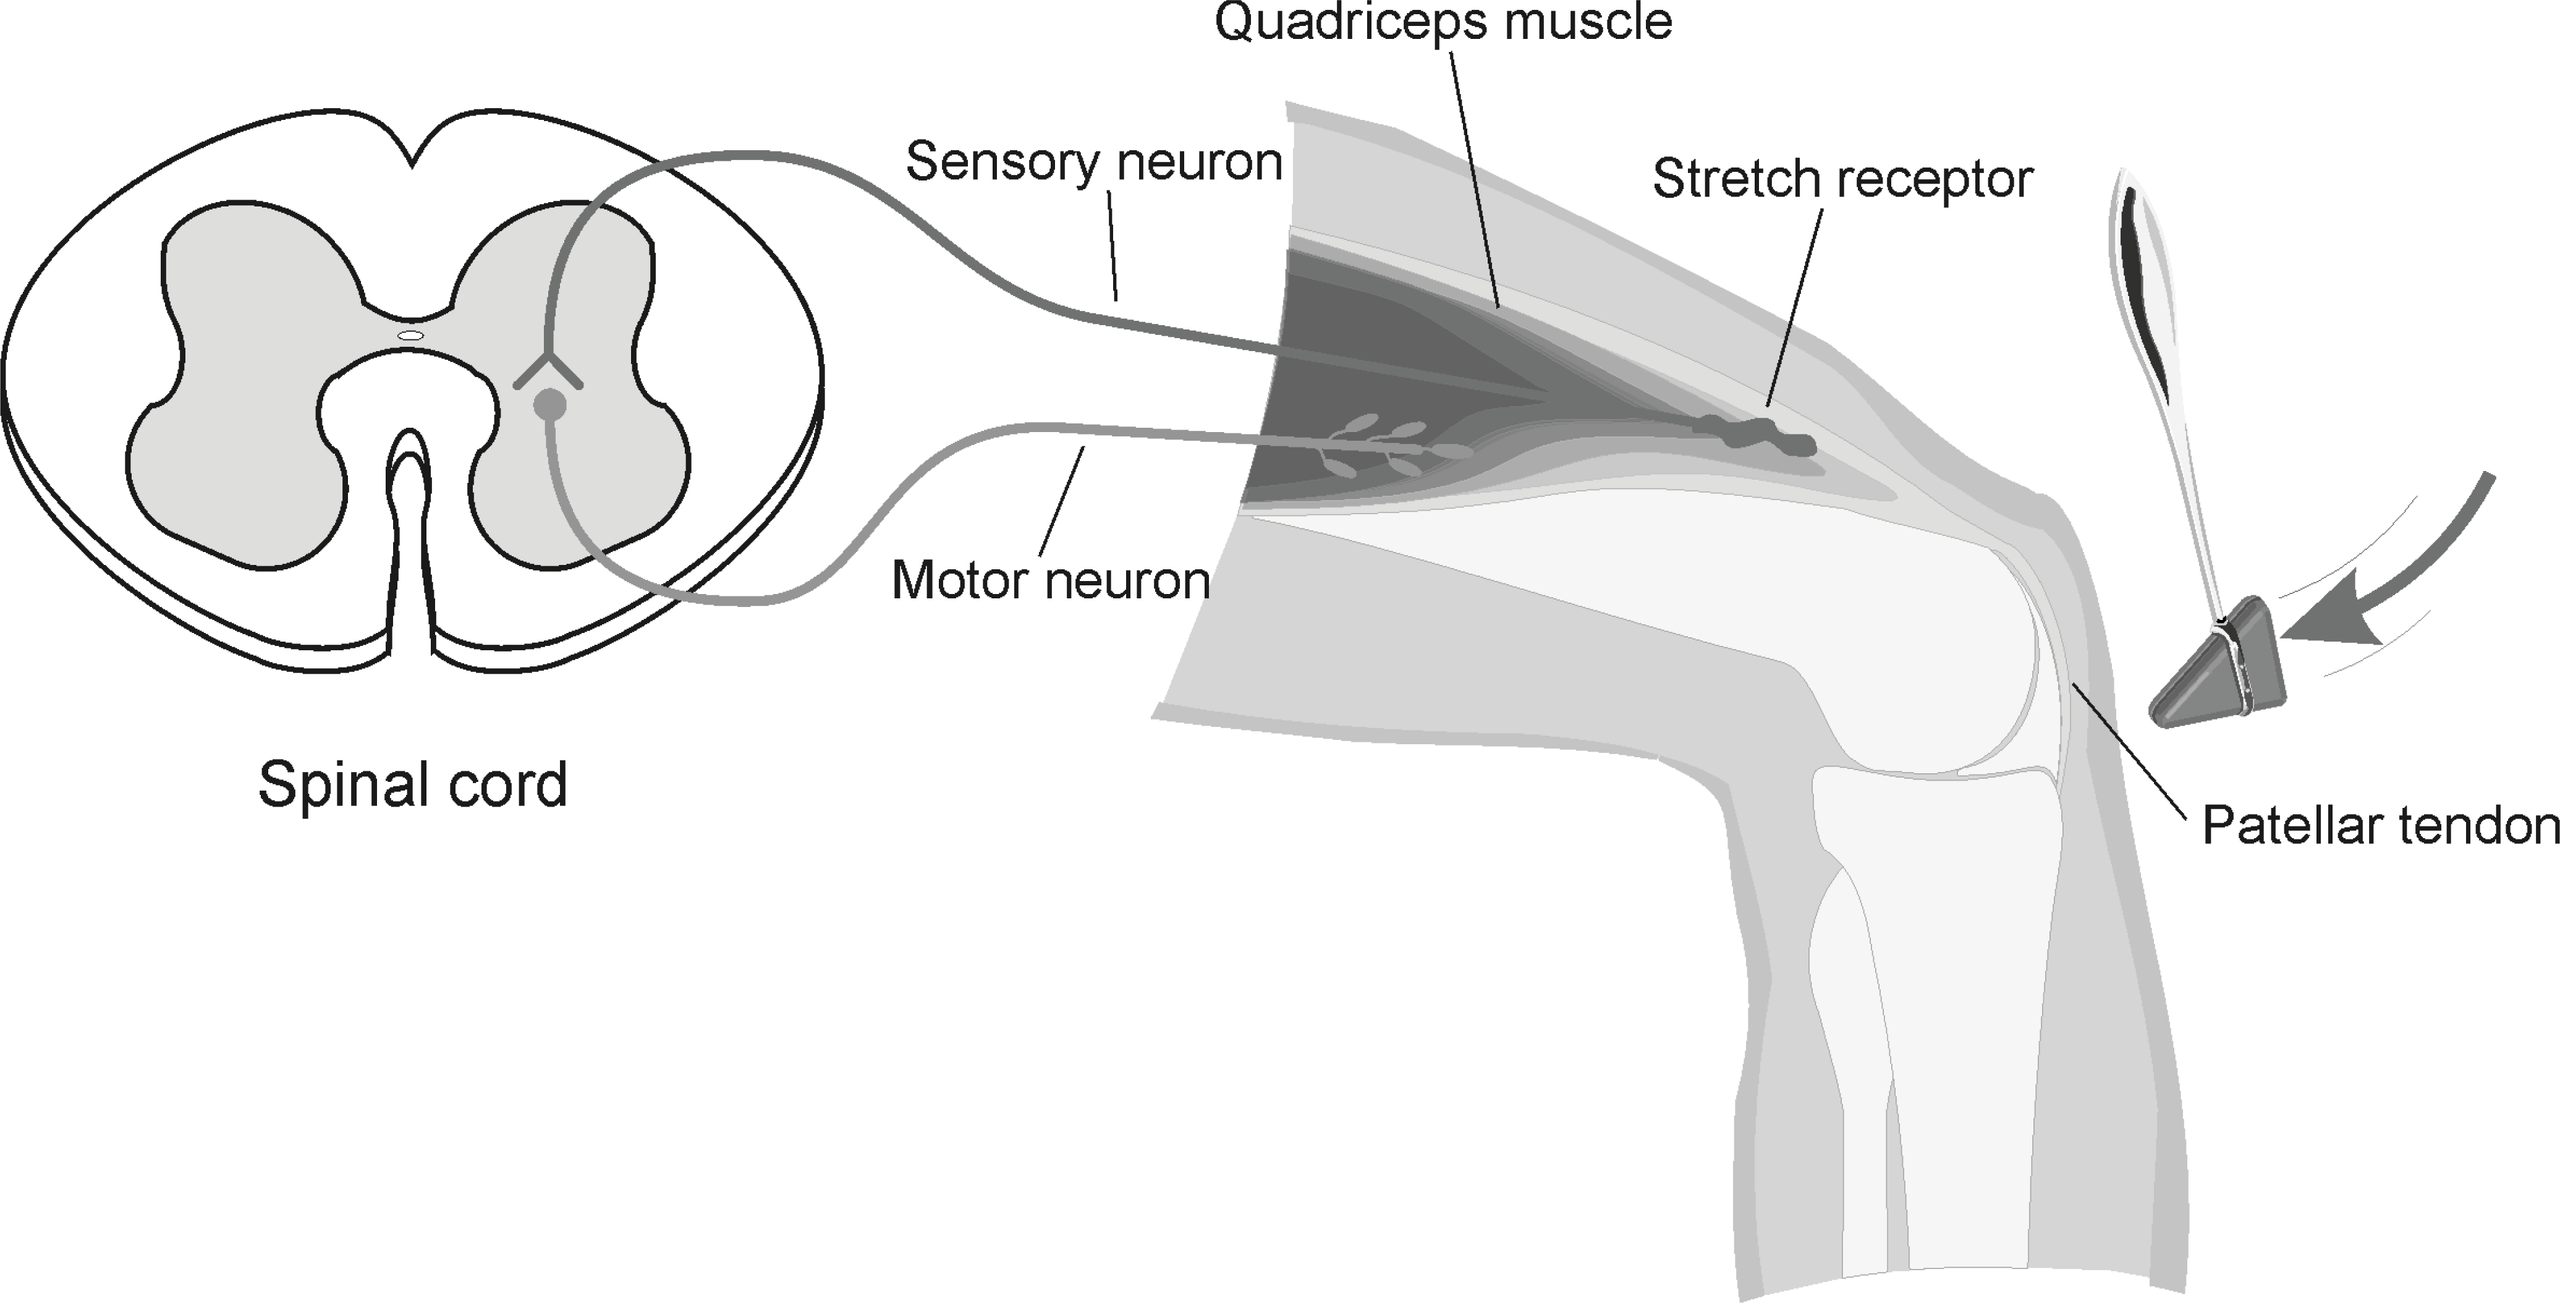
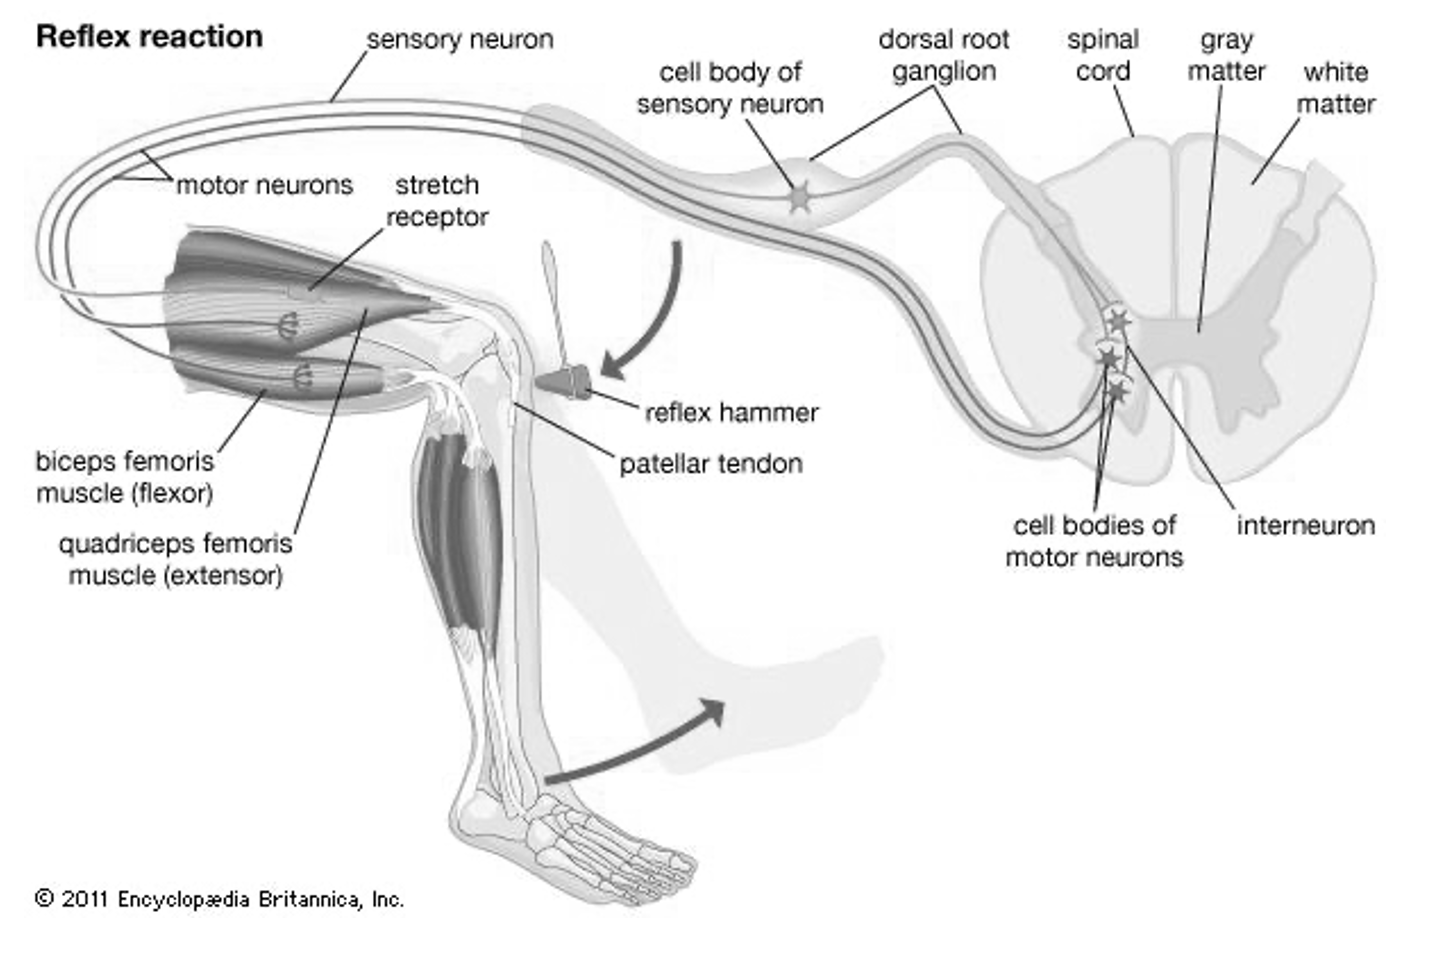
The knee jerk reflex tendon is the patellar tendon, a thick cord of connective tissue running from the bottom of the kneecap to the tibial tuberosity on the shin. When a clinician taps it with a reflex hammer, the sudden stretch sends a signal through the femoral nerve into the spinal cord at L2 through L4, and the quadriceps contracts almost immediately. This is a monosynaptic reflex arc, one of the simplest neurological pathways in the body. The whole thing takes roughly 30 to 50 milliseconds from strike to kick. I used to do neurology exams during my residency and I hit this reflex dozens of times a day. The trick most people miss is positioning. If the patient's leg is dangling freely without support, the tendon is already under some baseline tension from gravity and the quadriceps is partially engaged just holding the leg up. You'll get a response, but it won't be accurate. The patient needs to be seated with the knee bent at roughly 90 degrees and the leg completely relaxed. Sometimes they have to cross the other leg over and let it hang without touching the bed. A lot of students skip this step and then complain the reflex is "absent" when it's just hyperactive from tension.
The Knee Jerk Reflex Tendon and Why It Matters Clinically
A normal response is a quick extension of the lower leg. Absent or diminished reflexes point to peripheral nerve damage, radiculopathy at those spinal levels, or certain metabolic issues like hypothyroidism. Hyperactive reflexes suggest upper motor neuron lesions, things like multiple sclerosis, stroke, or spinal cord compression. The reflex itself is just a diagnostic tool, not a treatment target. Here's the part textbooks gloss over: the patellar tendon is also a common site for tendonitis, especially in runners and cyclists. The repeated loading causes microtrauma at the inferior pole of the patella, what we call jumper's knee. The pain sits right below the kneecap and gets worse with jumping, squatting, or going downstairs. I had a patient who thought his reflex was abnormal because every time I tapped that spot he flinched from pain rather than from the stretch reflex. We ended up diagnosing patellar tendinopathy, not a neurological issue. The workaround was simple - I switched to gently percussing the skin just below the patella rather than striking the tendon directly, and referred him for ultrasound imaging. Another practical detail people don't expect: the reflex can be modified by psychological state. Anxiety increases it. Fatigue decreases it. Certain medications like benzodiazepines and barbiturates suppress it, while stimulants amplify it. If you're testing a reflex and the result seems off, consider whether the patient took their anxiety medication that morning before you show up.
The biomechanics are worth understanding if you're studying this seriously. The patellar tendon acts as a force transmitter, increasing the lever arm of the quadriceps by about 5 millimeters compared to a direct attachment. That small anatomical detail gives you roughly 15 percent more mechanical advantage when extending the knee. It's why the patella exists - without it, the tendon would still work but the knee extension would be noticeably weaker, especially at shallow angles. If you're looking for diagrams or reference images, the most reliable sources are anatomy texts like Netter's or Gray's Anatomy, or databases like Radiopaedia for imaging correlations. There's no single download link worth following since everything is scattered across academic publishers and medical image repositories, and most quality resources require institutional access anyway. The reflex itself is reproducible under the right conditions about 85 to 90 percent of the time in healthy adults. That means roughly one in ten taps won't elicit a response even when the nervous system is completely intact. Don't panic over a single miss. Tap three times in slightly different locations and angles before you document anything as absent.
Get the Full Details