Getting to KRAS G12D Targeted Therapy: What It Actually Takes
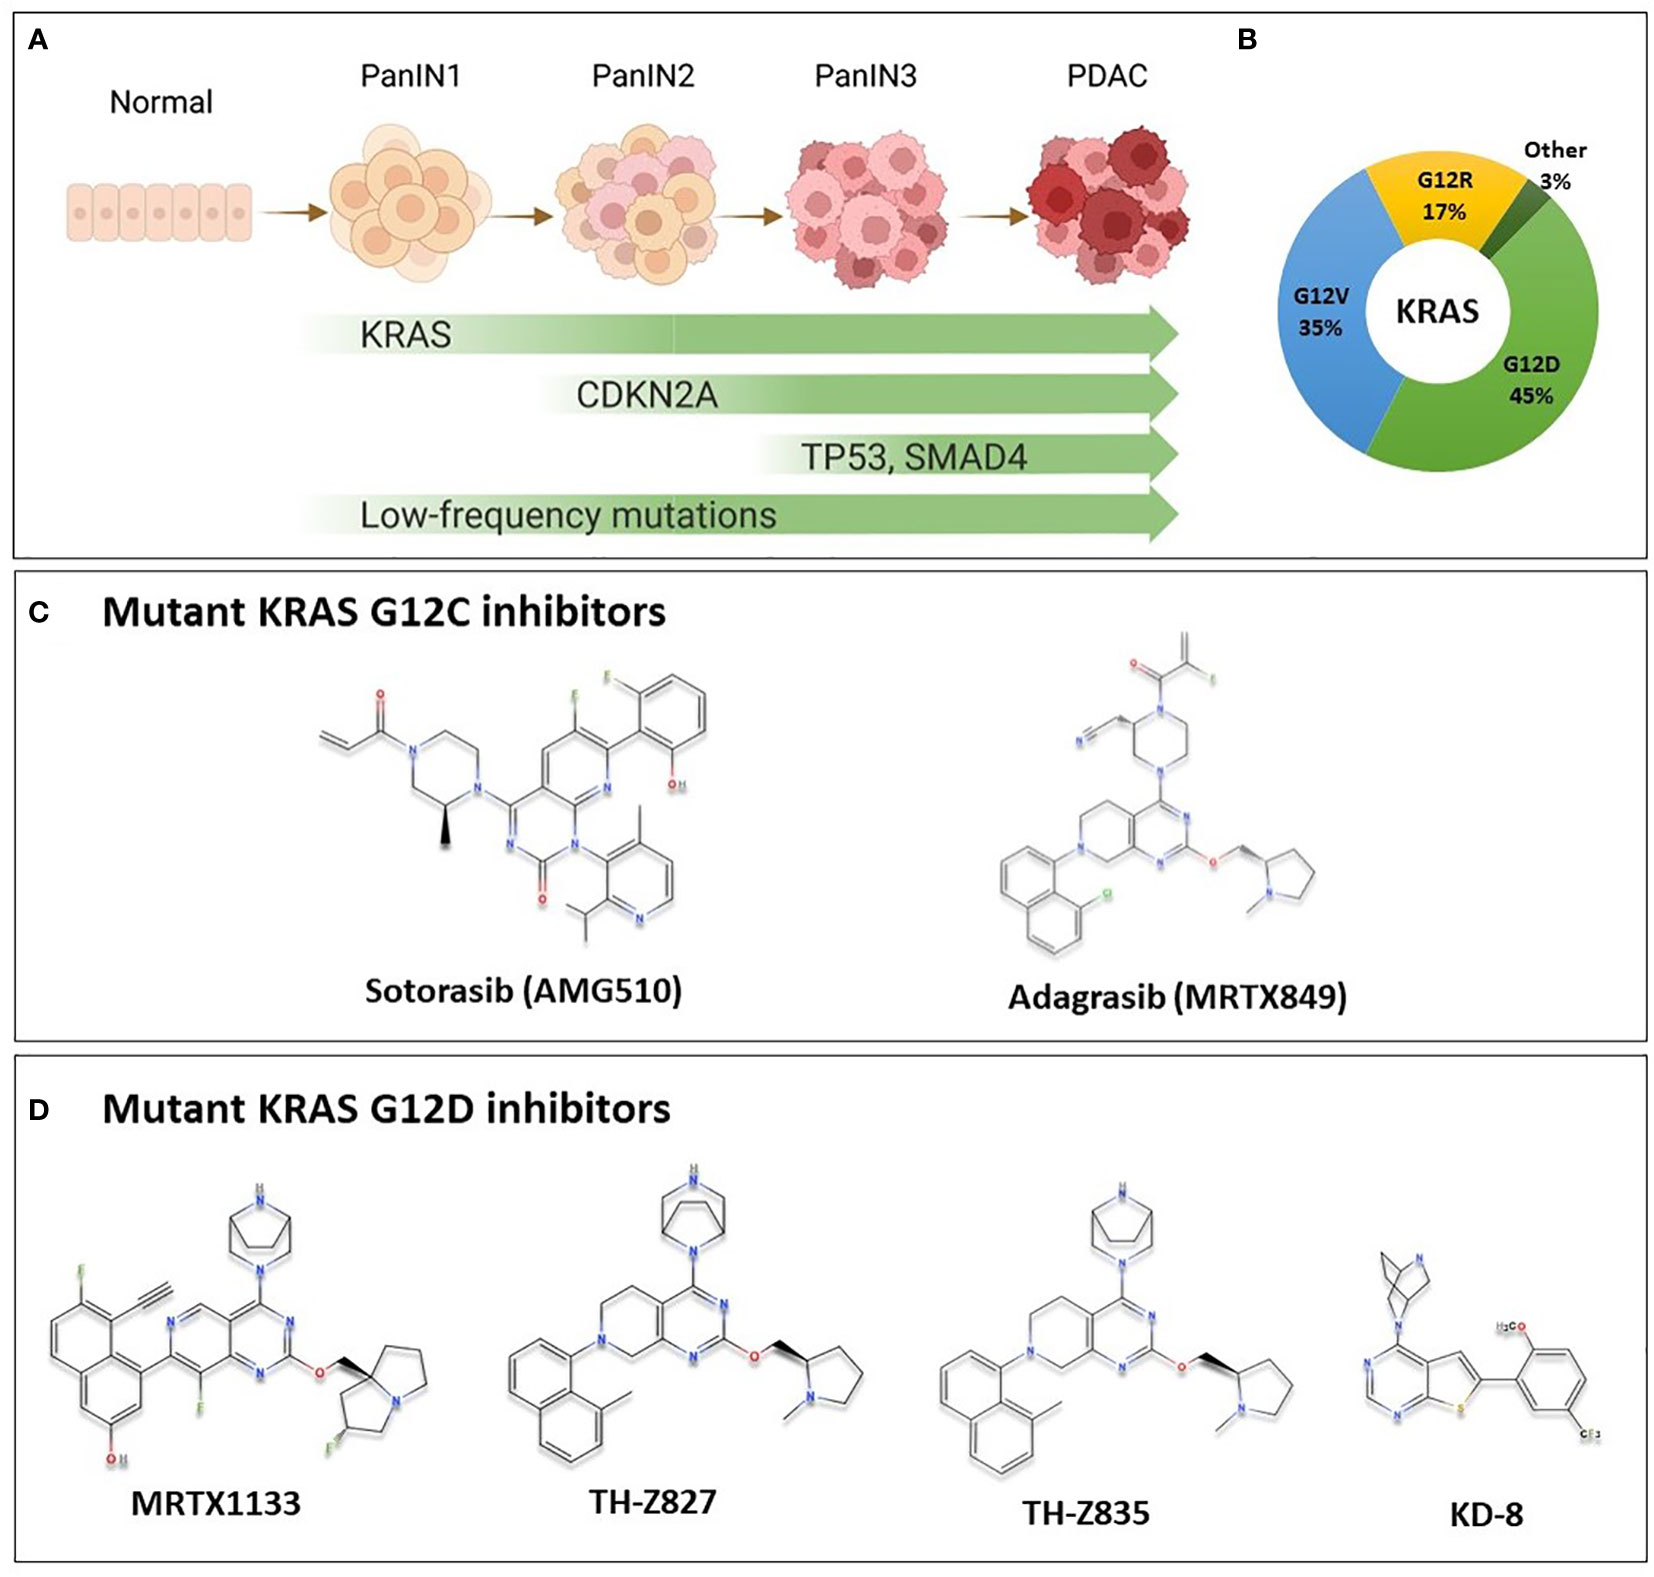
KRAS G12D is one of the nastiest oncogenic mutations to hit on, and for years it was basically untreatable with a targeted agent. The G12C variants got all the early spotlight because the cysteine at position 12 gives a covalent inhibitor something to latch onto. Aspartate doesn't work the same way. I watched Sotorasib and Adagrasib get approved for G12C and then immediately hit a wall when researchers tried to apply the same chemistry to G12D. It just didn't bind. So everyone had to start over from scratch. The fundamental problem is structural. KRAS G12D creates a charged pocket near the switch II region, and that's where the current generation of non-covalent inhibitors are finding their footing. They don't form a covalent bond. They sit in the switch II pocket and trap KRAS in its GDP-bound inactive state. It's a different mechanism, which means different pharmacokinetics, different resistance pathways, and a different clinical timeline than what we saw with the G12C drugs.
Kras G12d Targeted Therapy Clinical Pipeline and Trial Access
Several programs are in active development. MRTX1133 from Mirati is probably the most followed covalent-inactive-state approach, currently in phase 1/2 studies. RMC-6236 from Revolution Medicines takes a completely different angle by hitting both KRAS and downstream RAF, which matters because single-agent KRAS inhibition tends to cause feedback reactivation through the MAPK pathway. There's also JAB-21822 from Jazz, and various RNA-based approaches from smaller biotechs that haven't gotten as much visibility but are showing preliminary data. For someone looking to access these therapies, the first step isn't calling a pharmaceutical company. It's making sure your tumor has been sequenced properly. I've seen too many cases where a patient was told they were ineligible for a G12D trial because their initial liquid biopsy came back negative, but a subsequent tissue-based NGS panel picked up the G12D mutation that the blood test missed. Circulating tumor DNA sheds unevenly. Pancreatic and colorectal cancers in particular can have low ctDNA fractional abundance even when the tumor is clearly carrying the mutation. The practical workaround I recommend is requesting tissue NGS through a CLIA-certified lab if your liquid biopsy is negative or indeterminate. Guardant360 and FoundationOne CDx are the most common panels, and they both detect G12D, but the sensitivity differs between them depending on tumor purity and sample quality. A biopsy with less than 20 percent tumor cellularity will underperform on ctDNA assays. This is the kind of detail that gets lost in a fifteen-minute conversation with an oncologist who's juggling sixty patients a week.
Once you have confirmed G12D status, the next step is matching to a trial. ClinicalTrials.gov is the baseline resource, but the enrollment criteria for KRAS G12D trials tend to be specific about prior therapy lines. MRTX1133 for example has included patients who've progressed on standard chemotherapy, but some cohorts require no prior KRAS-targeted therapy. RMC-6236 trials often allow prior immunotherapy but exclude certain combination regimens. Reading the inclusion and exclusion criteria carefully before calling a trial coordinator saves weeks of paperwork later.
Get the Full Details

Why G12D Is Fundamentally Harder Than G12C
Here's something the press releases rarely emphasize. The switch II pocket that non-covalent G12D inhibitors target is more conformationally dynamic than the covalent cysteine pocket. That means these drugs often require higher plasma concentrations and more frequent dosing to maintain target engagement. In early phase data, MRTX1133 showed dose-dependent KRAS-G12D inhibition, but the exposure-response relationship wasn't as clean as what we saw with Sotorasib in G12C patients. Another counterintuitive point: having a G12D mutation doesn't guarantee response to a KRAS-G12D inhibitor. Downstream pathway dependencies vary. Some tumors with G12D also carry secondary mutations in PIK3CA or PTEN loss, which decouples the tumor's growth signal from KRAS alone. In those cases, KRAS inhibition alone produces minimal clinical benefit. The dual RAF-KRAS inhibitor strategy with RMC-6236 attempts to address this by blocking the pathway further downstream, and early data suggests broader response rates in mixed-mutation backgrounds, though that comes with its own toxicity profile. The toxicity picture is different too. G12C inhibitors like Sotorasib had a relatively clean safety signal. G12D inhibitors are still working through their dose-escalation phases, so adverse event profiles aren't fully characterized. Diarrhea, fatigue, and elevated liver enzymes are common class effects for KRAS pathway inhibitors, but the non-covalent approach may introduce distinct issues since these molecules often have different off-target binding characteristics. I flagged this with a colleague managing a pancreatic cancer patient on an early MRTX1133 cohort who developed unexpected grade 2 transaminitis that required dose interruption. Standard LFT monitoring protocols caught it within the first cycle, but it delayed treatment by ten days and made dose optimization considerably more complicated.
Combination Strategies Are Where the Real Work Is
Single-agent KRAS G12D inhibition is showing modest response rates in solid tumors, somewhere in the ten to twenty percent range depending on the cancer type and line of therapy. That's not zero, but it's not a turnaround either. The combinatorial approaches are where meaningful signals are emerging. The most common combination being tested pairs KRAS G12D inhibitors with MEK inhibitors. The logic is sound. When you inhibit KRAS, the feedback loop through SOS1 and RAF activity tends to rebound within days. Adding a MEK inhibitor like trametinib or cobimetinib blocks that escape route. Early-phase data from several combinations shows improved progression-free survival compared to KRAS inhibitor monotherapy, though the toxicity compounds. Diarrhea and rash become dose-limiting much sooner in combination arms. There's also emerging data on combining KRAS G12D inhibitors with immune checkpoint blockade. The rationale here is that KRAS-mutant tumors tend to have higher tumor mutational burden in certain contexts, particularly lung cancers, which should make them more immunogenic. But the pharmacodynamic interaction between KRAS inhibition and the tumor microenvironment is still being mapped. Some preclinical data suggests KRAS inhibitors can increase CD8+ T cell infiltration, while other data shows the opposite effect depending on the tumor type and prior treatment history. The clinical trial data is mixed.
For pancreatic ductal adenocarcinoma specifically, which is where G12D is most prevalent, the combination landscape is critical. PDAC has such a dense desmoplastic stroma and immunosuppressive microenvironment that even effective KRAS inhibition struggles to penetrate. The standard of care remains FOLFIRINOX or gemcitabine plus nab-paclitaxel, and any KRAS G12D targeted therapy would almost certainly be added on top of that backbone rather than replacing it. The trials reflecting this are the ones to watch most closely right now.

Practical Steps for Patients and Caregivers
If you're navigating this path, start by confirming the mutation with tissue NGS if you haven't already. Request a copy of the full pathology report and the NGS report. Don't rely on verbal confirmation. The reports will list variant allele frequency, which tells you how much of the tumor actually carries the G12D mutation. A VAF below five percent might still be clinically relevant, but it affects trial eligibility and prognostic interpretation. Then identify trials actively enrolling. The major cancer centers usually have the most KRAS G12D studies, but community oncology practices sometimes have trial access too, especially through cooperative group networks like ECOG-ACRIN. Travel and logistics matter more than people expect. Some of these trials require weekly infusions or frequent PET scans at specific sites. If you live more than two hours from a trial site, ask about satellite visit locations before enrolling. Insurance and clinical trial coverage is another area where people get blindsided. Covered drugs under a trial protocol are typically paid by the sponsor, but ancillary tests, travel, and supportive care medications may not be. Get a financial counseling appointment before you sign consent forms. Most trial coordinators will help with this, but they're managing twenty patients at once and won't catch every coverage gap.
There's also the question of what happens if the trial doesn't work or you progress. Having a backup plan matters. Some patients qualify for next-line trials, but waitlists exist. Others may be candidates for off-label combinations that some oncologists are exploring based on emerging data, though that's a decision that requires careful discussion about evidence level and risk.
Realistic Expectations
KRAS G12D targeted therapy is advancing, but it's not ready to replace standard chemotherapy in most indications. The response rates are meaningful but not dramatic. Progression-free survival extensions are in the months range for responding patients, and a subset of those responses appears durable. The toxicity of combination regimens is real and can be severe. Trial access is geographically constrained. And the biomarker story isn't fully resolved yet, which means some patients who look like good candidates on paper don't respond, and we don't always know why. What's clear is that the biology is being understood better with each trial readout. The switch II pocket inhibitors are improving. The combination strategies are getting smarter. And the patient selection criteria are sharpening. It's incremental progress, not a breakthrough, but it's progress in a space that was completely empty five years ago.