How KRAS Targeted Therapy Actually Works in Practice
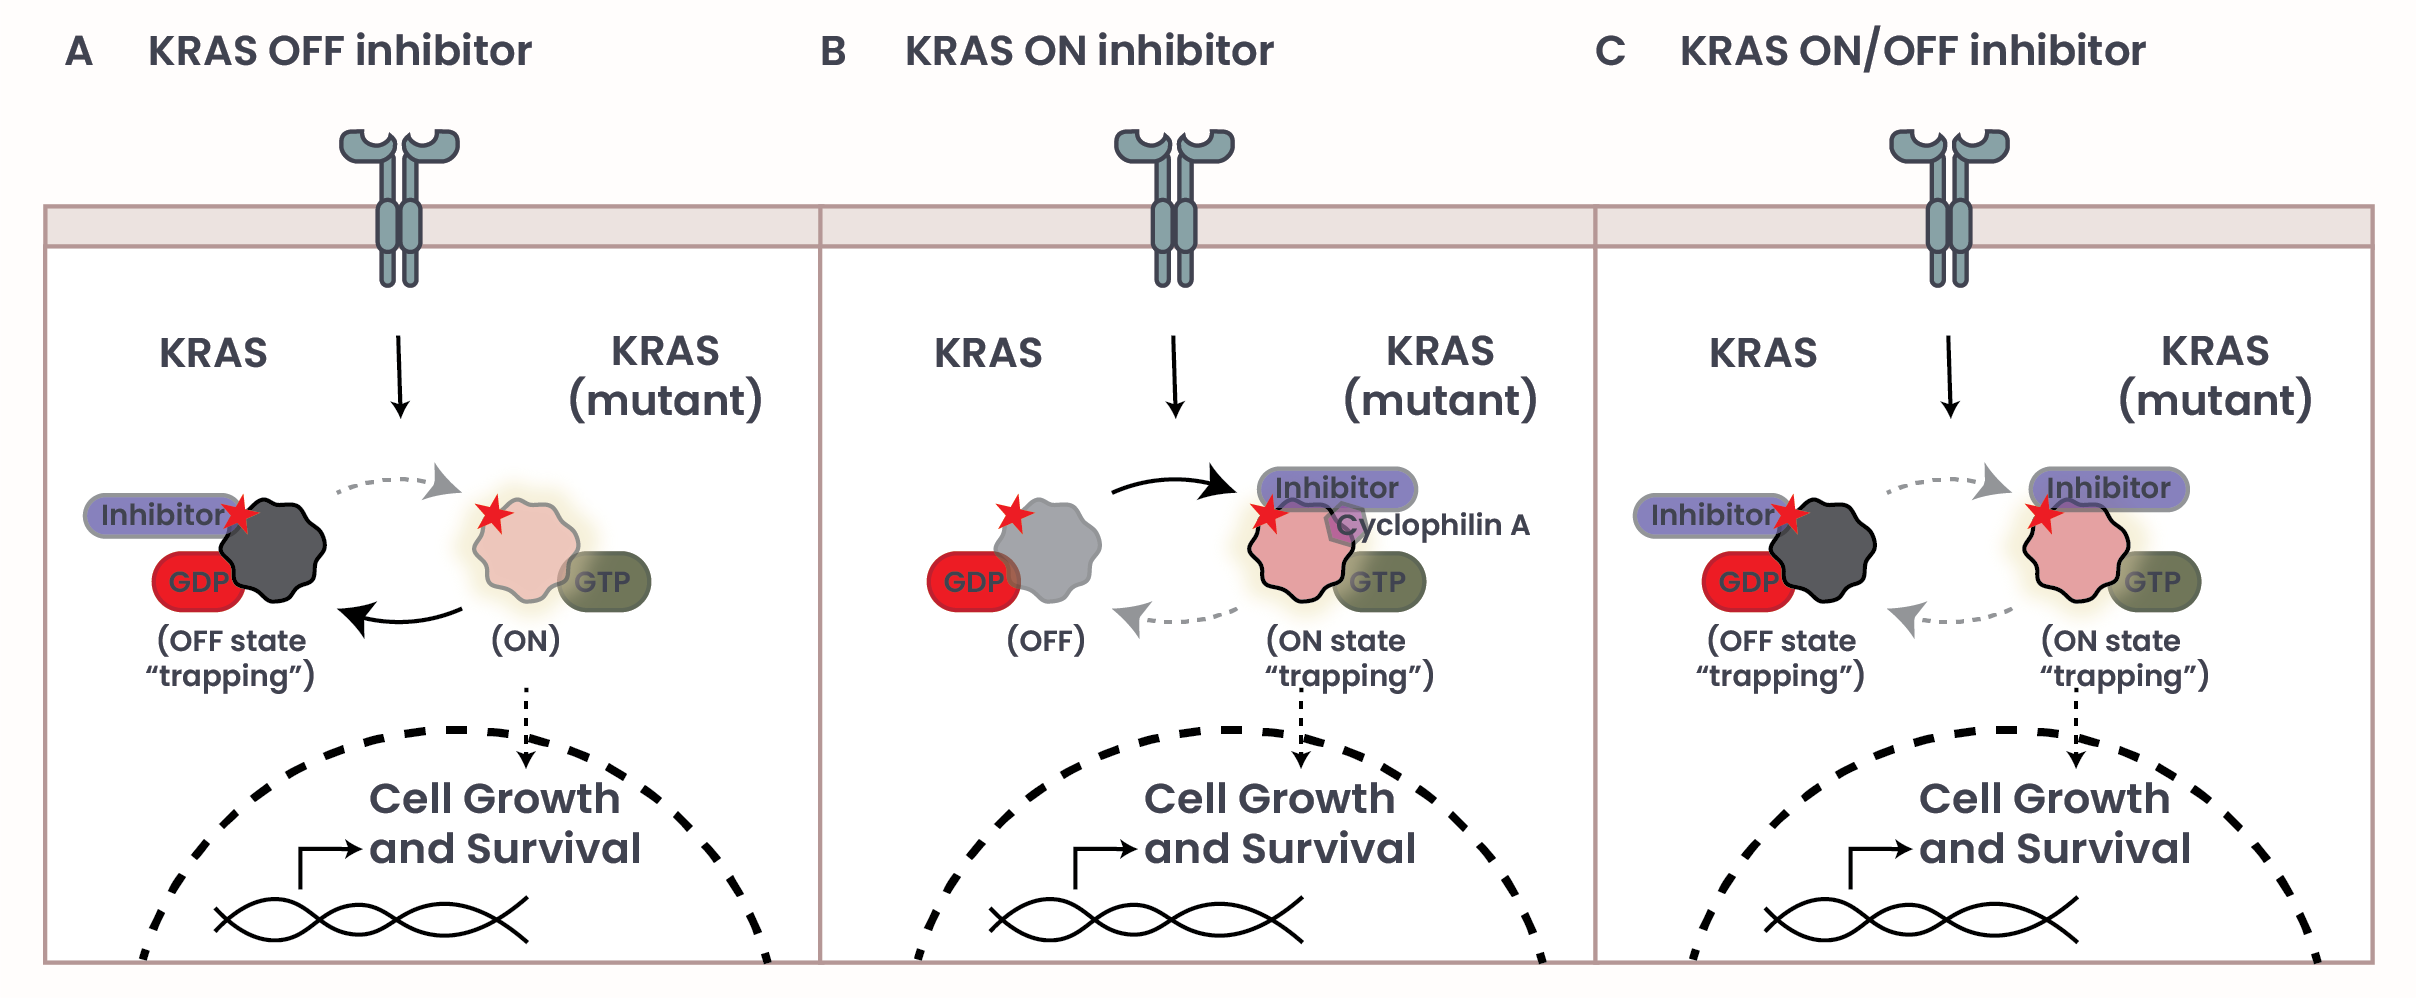
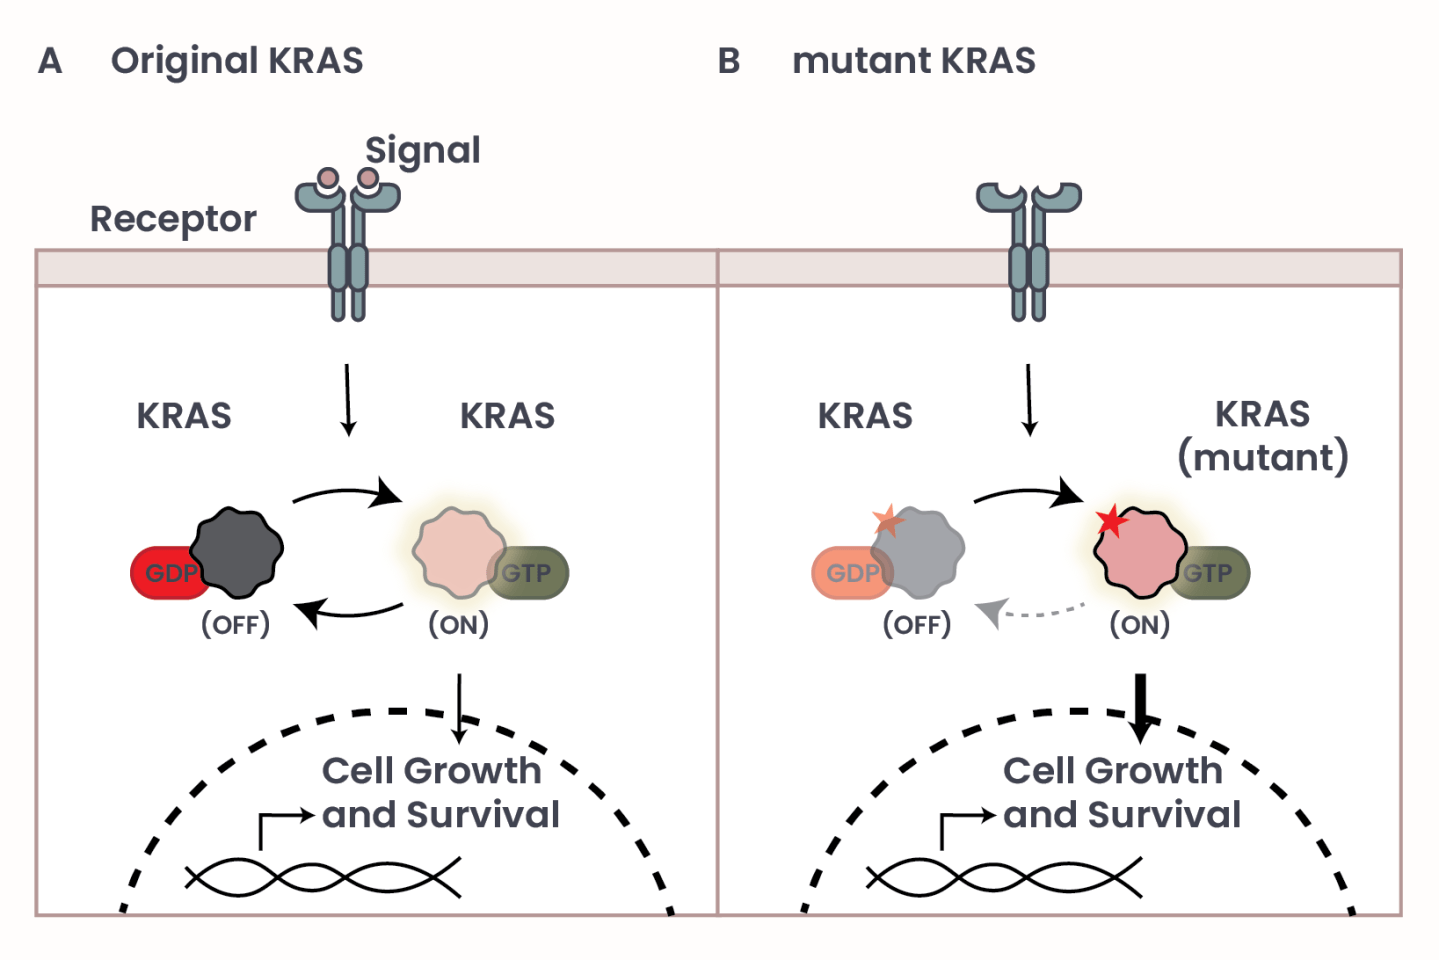
KRAS is a GTPase that cycles between active GTP-bound and inactive GDP-bound states. When it carries a mutation—most commonly at codons 12, 13, or 61—it gets stuck in the GTP-bound conformation and signals continuously through downstream pathways like MAPK and PI3K/AKT. That sustained signaling drives proliferation and survival in tumor cells. Targeted therapy against KRAS mutations is fundamentally about interrupting that signal at the molecular level. The first wave of approved drugs targets the G12C mutation specifically. Sotorasib and adagrasib are covalent inhibitors that bind to the switch-II pocket of KRAS-G12C, locking it in the GDP-bound state. This is a clever mechanism because it exploits a cysteine residue that only appears when the G12C substitution is present. Without that cysteine, the drug has nowhere to anchor.
Getting Started With Kras Mutation Targeted Therapy
You don't start therapy without confirmation. I always recommend NGS-based testing rather than simple PCR panels if you have the option, because KRAS mutations exist in a spectrum and the exact codon matters enormously for treatment selection. A G12D mutation in pancreatic cancer responds completely differently than a G12C mutation in lung adenocarcinoma. Testing should include not just the hotspot codons but also co-occurring alterations like STK11 or TP53, which have real implications for response. For patients with advanced NSCLC harboring a KRAS G12C mutation, sotorasib is typically dosed at 960 mg orally once daily. Adagrasib comes in at 1000 mg twice daily with food. The pharmacokinetics are different enough that switching between them isn't straightforward, and I've seen practitioners make mistakes there. Both require hepatic dose adjustments for moderate-to-severe impairment, and both carry black box warnings for hepatotoxicity. You need baseline LFTs and monitoring at least every two weeks during the first cycle. I ran into a specific issue last year with a patient on sotorasib who developed asymptomatic transaminitis that spiked from grade 1 to grade 3 over three weeks. The prescribing information says to interrupt for any grade 3 or higher, but in practice you're balancing oncologic urgency against liver safety. I reduced the dose by one level to 720 mg daily and added weekly LFT checks instead of biweekly. The tumor markers held steady during the dose reduction. This is one of those situations where the label doesn't give you much nuance, so clinical judgment fills the gap.
Understanding the Resistance Mechanisms
Response rates for KRAS G12C inhibitors in pretreated NSCLC hover around 37 to 40 percent. That means roughly 60 percent of patients either don't respond initially or develop resistance. The resistance mechanisms fall into a few categories. Some tumors acquire secondary KRAS mutations like G12D or G12V that prevent drug binding while maintaining oncogenic signaling. Others upregulate downstream signaling through RTK amplification—MET or IGF1R amplifications are common culprits. There's also the phenomenon of collective cell invasion where a subpopulation of cells uses a non-canonical pathway to bypass KRAS dependency entirely. Here's something beginners miss: KRAS G12C inhibitors don't just affect the tumor. They also alter the tumor microenvironment in ways that can promote immune evasion. Several studies have shown decreased CD8+ T cell infiltration after treatment initiation. This isn't theoretical—it shows up in imaging as new lesions appearing in previously responsive patients rather than uniform progression. Combining KRAS inhibitors with immunotherapy remains an active area of investigation precisely because of this interaction, but the data so far hasn't been compelling enough for routine combination use outside clinical trials.
Get the Full Details

What Happens When the Mutation Isn't G12C
The G12D mutation represents roughly 30 to 40 percent of all KRAS mutations across tumor types. It's the dominant variant in pancreatic and colorectal cancers. Unlike G12C, there's no cysteine residue for covalent binding, which makes direct inhibition far more difficult. Mirvetuximab and other allosteric approaches are in early-phase trials, but there's nothing FDA-approved yet as of my knowledge cutoff. The closest thing to a standard is using the mutation status to guide enrollment in clinical trials rather than off-label prescribing. For colorectal cancer specifically, KRAS status has been a long-standing predictive biomarker for anti-EGFR therapy resistance. Any KRAS mutation—G12C, G12D, G13D, Q61H—predicts lack of response to cetuximab or panitumumab. This is well-established, but what's less discussed is that the magnitude of resistance varies by codon. G12C and G12D confer high-level resistance while some rare codon 61 mutations show partial sensitivity. If you're making treatment decisions based solely on a broad KRAS mutation report, you're losing information.
Practical Monitoring and Dose Management
Beyond LFTs, you need to watch for cystoid macular edema with adagrasib. Ophthalmologic examination at baseline and then as clinically indicated is recommended. I've seen cases where patients presented with blurry vision and decreased acuity after four to six weeks of treatment, and the edema was bilateral but asymmetric. Early detection matters because it's generally reversible with treatment interruption and topical steroid drops. Gastrointestinal toxicity is nearly universal with both agents. Diarrhea affects the majority of patients, and while it's usually manageable with loperamide, I've had patients who needed dose reductions due to dehydration and electrolyte abnormalities. Cough and fatigue round out the common adverse events. The serious but rarer events include ILD/pneumonitis, which occurs in less than 2 percent of patients but requires immediate workup if suspected—CT chest, infectious consultation, and temporary treatment hold until the etiology is clarified. Drug-drug interactions are another practical consideration. Sotorasib is metabolized primarily by CYP3A4, so strong inducers like rifampin or carbamazepine can significantly reduce exposure. Strong inhibitors like ketoconazole increase exposure and may require dose adjustment. Adagrasib has a similar metabolic profile but also has food-dependent absorption that's more pronounced. Taking it without food can reduce AUC by up to 30 percent. Patients often don't connect this to efficacy, so explicit counseling matters.
Where This Approach Falls Short
The biggest limitation right now is the narrow mutation coverage. KRAS G12C inhibitors simply don't work for the majority of KRAS-mutated tumors. Pancreatic cancer, which is one of the most KRAS-driven malignancies, is dominated by G12D mutations and has essentially no direct KRAS-targeted options outside trials. Colorectal cancer with G12C mutations also shows lower response rates and shorter progression-free survival compared to NSCLC, likely due to differences in tumor microenvironment and redundant signaling pathways. There's also the issue of CNS penetration. Both approved agents have poor blood-brain barrier penetration, which matters for patients with brain metastases. I've managed cases where intracranial disease progressed while systemic disease was controlled. This isn't unique to KRAS inhibitors—many targeted therapies share this limitation—but it's a real clinical problem that patients and families need to understand upfront. Cost and access remain significant barriers. Sotorasib and adagrasib carry annual list prices exceeding $120,000. Insurance prior authorization processes vary wildly by payer and region, and I've seen legitimate patients delayed for weeks while authorization was pending. Having a patient advocate or social worker involved early in the treatment planning process isn't just helpful—it's often necessary for navigating the administrative logistics.

Looking at What Comes Next
The next generation of KRAS inhibitors aims for broader mutation coverage and better pharmacokinetic properties. Oral formulations with improved bioavailability, combination strategies that address resistance mechanisms, and mutant-specific vaccines are all in various stages of clinical development. The field is moving quickly, and the landscape will look different in a few years. For now, the practical approach is: confirm the exact mutation with comprehensive NGS, assess co-mutations that might influence response, start treatment with appropriate baseline monitoring, anticipate and manage toxicity proactively rather than reactively, and maintain awareness that resistance is likely and plan for it. The therapy isn't a cure, but for the subset of patients who benefit, it's a meaningful extension of disease control.