The reality of treating postural kyphosis
Kyphosis isn't just "bad posture." It's a structural adaptation where the thoracic spine curves excessively forward, usually from years of forward head and rounded shoulder positioning. The muscles in front get short and tight, the ones in the back get lengthened and weak, and the joints settle into that position because nothing's actively pulling them back. Most people who come in with this have been sitting at desks or hunched over phones long enough that their thoracic spine genuinely has lost some extension range. That matters because it changes which exercises will actually work and which are just wasted effort. I dealt with a case recently where a client had what looked like standard postural kyphosis, so I loaded up on thoracic extension work and scapular retraction drills. After three weeks, they were more uncomfortable, not less. Turns out they also had significant lumbar hypolordosis compensating for the upper curve, and all that extension work was driving more compression into their already-flattened lower back. The workaround was dropping the prone extension series entirely and focusing on rib cage decompression first — specifically rib raises and diaphragmatic breathing with lateral costal expansion — before adding any aggressive spinal extension. Once the lower ribs had more mobility, the thoracic work finally started producing results instead of pain.
Essential Kyphosis Physical Therapy Exercises
Prone Y raises are about as fundamental as it gets. Lie face down on the floor with your forehead resting on a towel or thin mat. Arms extended overhead in a Y shape, thumbs pointing up. From there, lift both arms off the ground by squeezing your lower traps and rhomboids, not by shrugging your shoulders. The common mistake is initiating the movement with the upper trapezius, which just reinforces the same compensatory patterns causing the kyphosis in the first place. Keep your neck long, your shoulder blades down and back, and only raise your arms to the point where you can maintain that position without your neck cramping. Two sets of eight to ten reps, three days a week. The burn you feel between the shoulder blades is the target muscles actually engaging. Wall slides with external rotation address both thoracic extension and scapular control simultaneously. Stand with your back against a wall, heels about six inches out. Press your lower back, upper back, and the back of your head against the surface. Raise your arms to a goalpost position, elbows at ninety degrees, and press your forearms and wrists against the wall. Slide your arms up overhead while maintaining full contact along the entire arm, then return. If your lower back arches or your ribs flare as you reach up, you're pushing through your lumbar spine instead of your thoracic spine — back off the range until you can keep everything pinned. This directly fights the forward shoulder rotation that accompanies kyphosis by forcing the humerus into external rotation under load. Dead bugs seem unrelated to kyphosis at first glance, but they're essential because thoracic extension work fails when the core can't stabilize the lumbar spine. Lie on your back, arms reaching toward the ceiling, legs in tabletop position. Lower your right arm overhead and extend your left leg straight out while keeping your lower back pressed into the floor. Return to start and switch sides. The critical detail is maintaining that lumbar contact throughout the entire movement. If your back arches even slightly, the exercise stops working for you and starts potentially worsening your curve by encouraging lumbar hyperextension as compensation. Start with just arm movements before adding legs if you can't maintain contact with both.
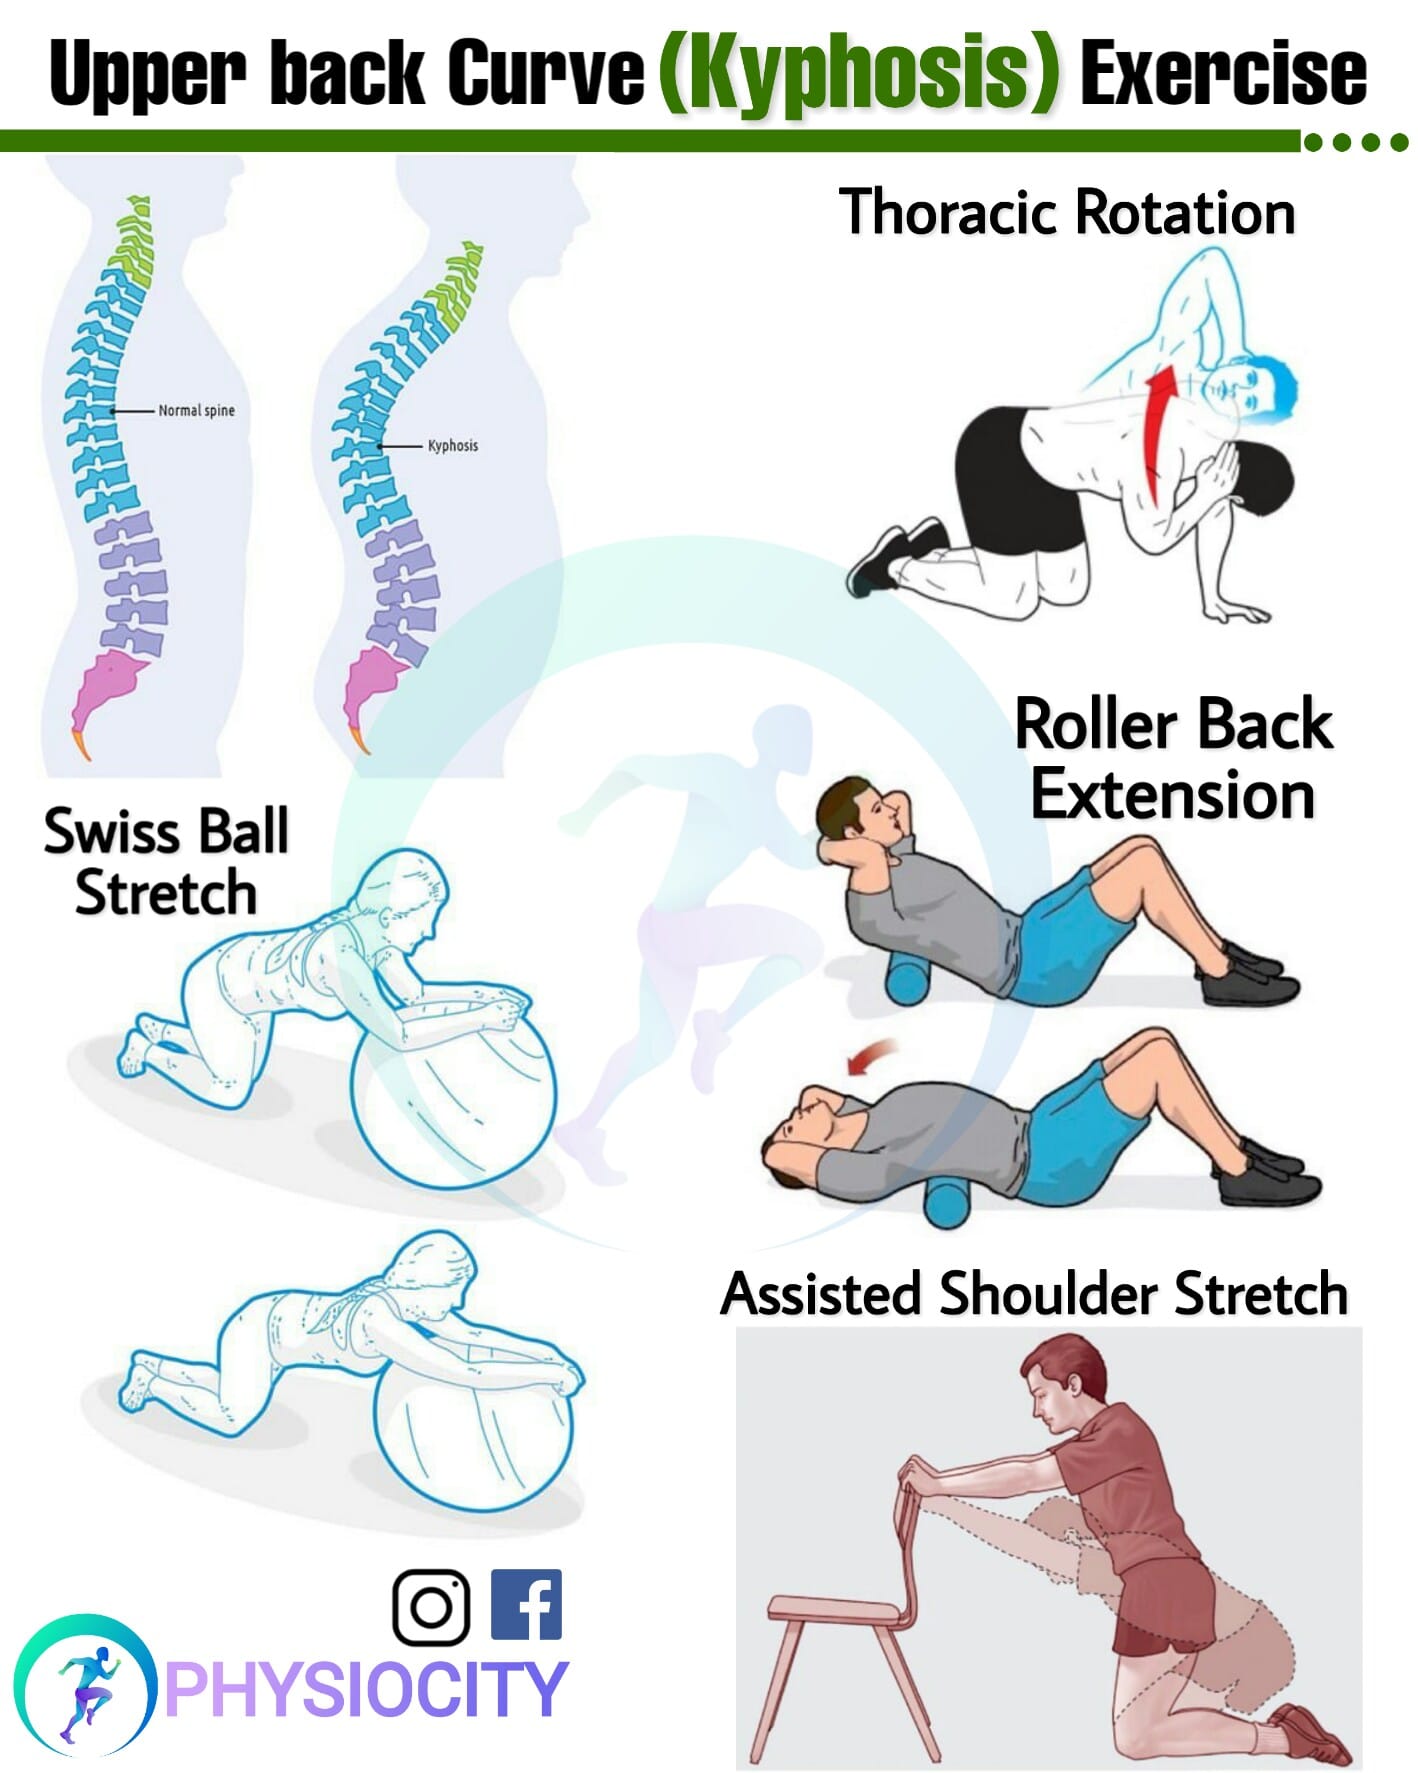
Doorway pec stretches tackle the anterior tightness that's actively pulling the shoulders forward. Stand in a doorway with your forearms on the doorframe at roughly shoulder height, elbows bent at ninety degrees. Step one foot through and gently lean forward until you feel a stretch across the front of your shoulders and chest. Hold for thirty to forty-five seconds. Repeat three times on each side. Don't push into sharp pain — this should be a moderate stretch, not a forced tear. Tight pectorals are one of the primary mechanical drivers of thoracic kyphosis, and no amount of strengthening the back will overcome that pull if the front remains shortened. Thoracic extension over a foam roller is the mobility piece that supports everything else. Place the foam roller horizontally across your mid-back, just below the shoulder blades. Support your head with your hands and gently arch back over the roller, letting your thoracic spine extend against it. Move the roller up and down by one inch at a time, working through the entire thoracic region. Each segment needs about two to three breaths of extension at the end range. The goal here isn't to force the spine into extension arbitrarily — it's to restore segmental mobility so that when you do the strengthening exercises later, your thoracic spine can actually move rather than your neck or lower back taking over the work. People with significant kyphosis often find that the upper thoracic region (around T1-T4) is the stiffest and most resistant, and that's exactly where you need to spend the most time.
Get the Full Details

What most people get wrong
The biggest issue I see is people chasing thoracic extension without addressing the scapular upward rotators first. Your shoulder blades need to rotate upward smoothly for your thoracic spine to extend fully. If your serratus anterior and lower trapezius are weak or inhibited, forcing extension just causes the shoulder blades to wing or the neck to take over. The workaround is adding serratus punches before the extension work — lie on your back with arms overhead and press your shoulder blades off the floor by reaching further toward the ceiling, keeping elbows straight. This pre-activates the muscles that will stabilize the scapula during the more demanding exercises. Another counter-intuitive point: more stretching isn't better. I've seen clients spending twenty minutes daily on pec and anterior shoulder stretching with minimal improvement in their kyphosis. The issue is that chronic postural adaptation isn't primarily a soft tissue length problem — it's a neuromuscular control problem. Your nervous system has simply accepted the rounded position as "normal." The strengthening exercises that retrain scapular positioning and thoracic extension under load produce more durable change than stretching alone, which is why the exercise emphasis should be roughly 70 percent strengthening and 30 percent mobility for most non-structural kyphosis cases.
When these exercises won't help
It's important to be clear about the limits here. Kyphosis Physical Therapy Exercises are effective for postural and adaptive kyphosis, which is the vast majority of cases seen in clinical practice. They do not reverse structural kyphosis caused by vertebral body deformities such as Scheuermann's disease, congenital anomalies, or advanced degenerative changes with disc space loss and osteophyte formation. If your kyphosis is structural, the exercises can still help with pain management and slowing progression, but they won't straighten the spine. A lateral bending x-ray is the standard way to determine whether your curve is flexible or rigid, and anyone with known structural spinal pathology should be working with a physical therapist or spine specialist rather than self-prescribing. The timeline is also something people underestimate. For postural kyphosis, noticeable improvement in standing posture typically takes eight to twelve weeks of consistent work, and meaningful change in resting thoracic curvature takes longer — often four to six months. The exercises need to be done three to four times per week minimum. Doing them once a week produces virtually no adaptation. The soreness between the shoulder blades in the first two weeks is normal and indicates the targeted muscles are being engaged. If you're feeling pain in your neck or lower back instead, the form is likely compensating and needs to be dialed back.