What Actually Works After an L2 Compression Fracture
Most people coming off a lumbar compression fracture don't need fancy rehab protocols. They need to know what not to do first, because that's where things go sideways. The L2 vertebra sits right in the middle of your thoracolumbar junction, which means it takes a solid amount of load when you bend forward or stand for long periods. Getting it to heal properly is mostly about patience and avoiding the positions that re-injure it.I spent three years working with spinal injury patients before I stopped keeping detailed notes, and one thing kept coming up: the standard "flexion avoidance" advice gets applied too rigidly. Yes, you avoid forward bending in the early weeks. But complete immobilization leads to deconditioning that makes recovery longer than it needs to be. The sweet spot is controlled, pain-free movement within safe ranges, progressing as the fracture consolidates on imaging. After the initial inflammatory phase settles, you introduce gentle core engagement work. Think abdominal bracing without spinal movement. Lie on your back, knees bent, draw your belly button in just enough to feel the deep abs activate, hold for five seconds, release. That's it. Ten reps. You're waking up the muscles that will eventually support that healing vertebra, not loading it. Once clearance comes through on follow-up imaging - usually around the six-week mark for a mild to moderate compression - you can start adding extensions. Prone on elbows, the kind of position you'd see in a McKenzie protocol. Stay in it for thirty seconds, come down, repeat three times. The goal here isn't to stretch anything. It's to encourage the anterior vertebral body to remodeled under load in the right direction and to re-establish extension tolerance, which gets shut down quickly after a fracture.
Where People Mess This Up
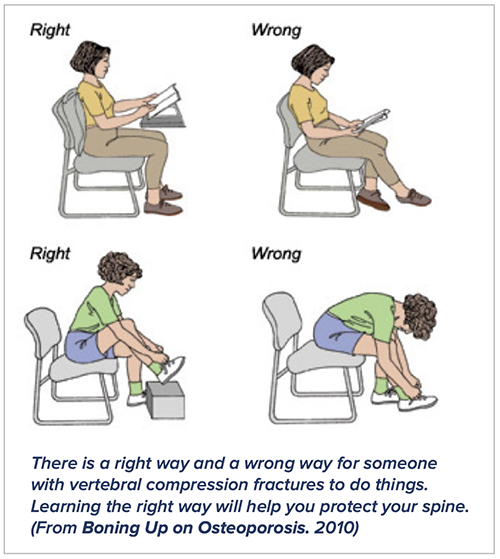
The biggest mistake I see is jumping into flexion-based exercises like toe touches or sit-ups because a website told them to "strengthen their core." That's exactly how you turn a healing compression fracture into a worse one. The L2 body is compressed anteriorly - the front of the vertebra is squished. Any forward flexion under load drives more compression into that same spot. Don't do it. Period.Another issue is the hip flexor tightness that develops from sitting so much during recovery. Tight hip flexors pull on the lumbar spine and change your posture in ways that increase compressive load on L2 even when you're just standing. I had a patient who was healing well but kept having flare-ups. Turns out he'd been sitting for hours daily during lockdown and his psoas was so tight it was literally tugging on his lumbar vertebrae. We added gentle psoas stretches - half-kneeling, posterior pelvic tilt, hold for forty-five seconds - and the flare-ups stopped. Weeks four to six: if imaging shows early consolidation, add prone propping and maybe supine leg slides. Still no flexion under load. Bridge poses are borderline - some clinicians clear them at four weeks, others wait until six. Follow your provider's call on this. Weeks six to twelve: gradual progression into bird dogs, modified planks on knees, continued extension work. You're building endurance now, not max strength. The fracture is healing but not fully remodeled. Heavy loading, impact, contact sports are still off the table.
After twelve weeks: most simple compression fractures are clinically healed. You're into strengthening territory now. But even then, you've lost some height in that vertebral body and your biomechanics are slightly different. You'll want to maintain core work and avoid repetitive heavy axial loading for several months after that.
Get the Full Details

When This Approach Doesn't Work
Severe compression fractures with retropulsion - where bone fragments push backward toward the spinal canal - need a different conversation entirely. Exercise is not the primary intervention there. You're looking at possible vertebroplasty, kyphoplasty, or surgical fixation depending on neurology and stability. Same thing if you have osteoporosis-related fractures that aren't responding to conservative management. In those cases, you treat the underlying bone density issue and assess whether procedural intervention is needed. Exercises come much later in the sequence, if at all in the acute phase.Pain that doesn't improve at all after two to three weeks of conservative management should be re-evaluated. It might not be the fracture anymore. Could be a nerve irritation, a different level involved, or something else entirely that's being masked by the original injury. Don't just keep doing the same routine and hope it changes. Bowel function matters more than people admit. Opioids for fracture pain cause constipation. Straining on the toilet increases intra-abdominal pressure against a healing vertebral body. Use a stool softener if you're on anything stronger than acetaminophen. It's a small thing that prevents a real problem. Sleeping position is another one that gets overlooked. On your back with a pillow under your knees takes the lumbar spine out of extension. On your side with a pillow between your knees keeps everything aligned. Stomach sleeping is generally uncomfortable and puts the spine in extension that some patients find painful at this stage. Find what works and stick with it.
The whole process from injury to full activity typically runs four to twelve weeks depending on severity, bone quality, and adherence. There's no shortcut that doesn't carry risk. The exercises I've outlined above are starting points, not a substitute for professional guidance. Get imaged, get a diagnosis that specifies your fracture grade, and work with someone who can adjust the plan as you progress. The last thing you want is to be the person who healed fine and then messed it up because someone on the internet told you to try something that wasn't appropriate for your specific case.