
Starting L5 S1 Degenerative Disc Disease Exercises
Most people with L5 S1 degenerative disc issues jump straight into what they find on Google first, which is usually a list of stretches they copy from someone else's recovery timeline. That rarely works because the L5-S1 segment sits at the very bottom of the lumbar spine, bearing the most compressive load, and every person's presentation at that level is different. The disc can be bulging, herniated, annularly torn, or just showing age-related desiccation. The exercise prescription changes depending on which of those you're dealing with. The fundamental mechanism at L5-S1 involves flexion intolerance for a lot of people. The posterior annulus gets compressed during forward bending, which can push disc material further into the spinal canal or against the S1 nerve root. That's why so many standard routines that work fine for upper lumbar issues make things worse at the lowest segment. The S1 nerve root specifically controls sensation down the back of the leg to the outer foot and powers plantar flexion, so any irritation there has a fairly distinctive symptom pattern.
L5 S1 Degenerative Disc Disease Exercises That Actually Move the Needle
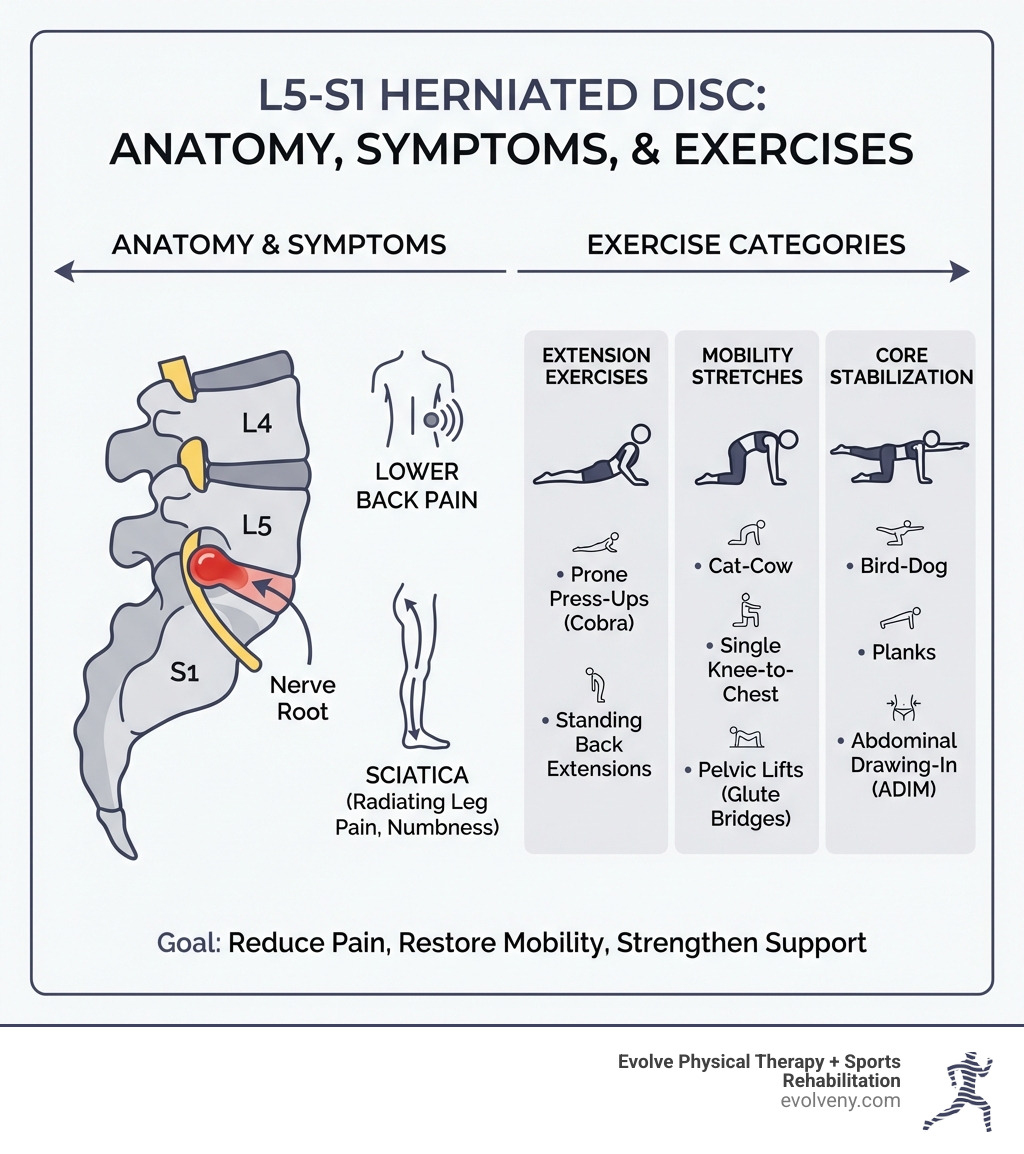
I always start patients on extension-biased movements if they have centralization symptoms, meaning their leg pain retreats toward the spine when they press up into extension. The classic prone press-up, which you find in theMcKenzie method, is the default here. Lie on your stomach, place your hands under your shoulders, and gently press your upper body up while keeping your pelvis grounded. Hold for a few seconds at the top, lower back down. Start with ten repetitions, two or three times per day. The goal is to see if the leg symptoms move closer to the trunk, which signals the disc material is shifting away from the nerve. When extension centralizes the pain, that is the green light to layer in more work. If extension makes the pain travel further down the leg, you need to stop immediately and pivot. Some people with L5-S1 issues are actually flexion-intolerant in a different way, and they need neutral-spine approaches instead. That usually means something like the McGill big three: curl-up, side plank, and bird dog, all done with a braced core and absolutely no spinal flexion or extension. The bird dog is particularly useful at this level because it trains anti-extension stability without loading the disc through flexion. You get on all fours, brace your core as if someone is about to poke you in the stomach, extend one arm forward and the opposite leg back, hold for five to eight seconds, and lower with control. Three sets of eight to ten reps per side, every other day. The key is not letting the lower back sag or arch as you extend the leg. That sagging re-introduces the exact compressive force you are trying to avoid at L5-S1.
Dead bugs are another solid option for the same reason. Lie on your back, arms extended toward the ceiling, legs in a tabletop position, and press your lower back flat into the floor. Slowly lower one arm overhead and the opposite leg forward while maintaining that contact point between your spine and the ground. If your back arches off the floor, you have gone too far. Shorten the range of motion until you can maintain neutral. This trains the deep core without putting shear force on the disc.
Get the Full Details
The Nerve Gliding Component
Many people skip nerve glides entirely, but if you have any radicular component from the S1 root, stiff neural tissue will resist your other exercises and make progress feel slower than it should be. The seated or supine sciatic nerve glide is the standard approach. Sit on the edge of a chair, straighten one knee while simultaneously pointing your toes toward you, then bend the knee and point your toes away. The movement should be smooth and pain-free, staying below the threshold where symptoms flare. Ten to fifteen repetitions per side, once or twice daily. You are not stretching the nerve. You are passingively moving it through its channel so it does not get stuck and sensitized. I had a patient a few years back who fit the textbook profile for extension-biased work at L5-S1. His leg pain centralized nicely with press-ups, he was progressing well for about six weeks, and then one morning he woke up and could not point his toes on the affected side without sharp pain. His S1 myotome was compromised. We had been doing bird dogs with full leg extension, and I realized he was probably pushing his hip extension beyond what his irritated root could tolerate. The workaround was straightforward: I dropped the leg extension entirely and moved him to a modified bird dog where he only lifted the arm, keeping the opposite knee bent and grounded the whole time. Once the acute root irritation settled over about three weeks, we reintroduced the leg lift in a much smaller range of motion. Full extension didn't come back until week nine. Had we pushed through the earlier phase, I likely would have made things worse. The biggest mistake I see is treating this like a generic back problem. Single-leg deadlifts, toe touches, sit-ups, and especially any twisting motion under load are high-risk at L5-S1 because that segment experiences the highest combination of compression and shear in the entire spine. The lumbar spine above L5-S1 can handle more variety because the lever arm is shorter. At L5-S1, the fulcrum effect is maxed out.
Another common error is progression timing. People add range of motion or load too quickly once their pain decreases. Pain decreasing does not mean the annular fibers have healed. Disc tissue remodeling takes months, not weeks. Keep the range of motion conservative for at least eight to twelve weeks even if you feel great by week four. I usually tell patients to use a simple rule: if an exercise produces any increase in peripheral symptoms the next day, you did too much the day before. Scale back by about thirty percent and rebuild more slowly.
Limitations and When This Approach Stops Working
This framework works well for most mechanical and mild-to-moderate radicular presentations at L5-S1. It does not work when there is significant spinal stenosis causing neurogenic claudication, because extension-based exercises will typically worsen symptoms in that scenario. If your leg pain and heaviness increases when you stand upright and walking and improves when you sit or lean forward, you are dealing with a different mechanical problem. In that case, flexion-biased work like stationary cycling and seated pelvic tilts is more appropriate, and extension exercises should be avoided. Severe calcified herniations with fixed neurological deficits, including progressive weakness in foot drop or bowel and bladder dysfunction, require surgical consultation regardless of what exercises you do. No amount of core stabilization will reabsorb a calcified extrusion that is mechanically compressing a nerve root. Same with cauda equina syndrome, which is a medical emergency. Spondylolisthesis at L5-S1, which is fairly common given that is where the transition to the sacrum occurs, also changes the exercise picture significantly. Forward slippage of L5 over S1 creates a different set of constraints, and aggressive extension can worsen the slip. If you have a known spondylolisthesis, you need imaging review and a modified protocol before starting any of this.

Building a Practical Weekly Structure
A reasonable starting structure looks like this. Daily nerve glides, ten to fifteen reps per side. Daily extension exercises if they centralize symptoms, ten reps, two to three sets. Bird dogs and dead bugs on alternating days, three sets of eight to ten per side. Walking is your cardio, starting at ten to fifteen minutes and adding two minutes per session as tolerated, stopping well before symptoms flare. Avoid anything that loads the spine through flexion or rotation for the first eight to twelve weeks. Once you have been pain-free at rest for several weeks and your daily movements are consistently symptom-free, you can begin adding stability work under load. Pallof presses, farmer carries, and glute bridges with progression are all viable. The glute bridge in particular is important because weak glutes shift more load to the lumbar spine with every step. Strong glutes take that load off. Start with double-leg bridges, progress to single-leg when the double feels easy, and only then consider adding resistance. Most people rush this part and reinjure themselves three months into recovery because they were not actually ready. The whole process from first exercise to return to normal activity typically runs four to sixteen weeks depending on severity, compliance, and the specific pathology. There is no shortcut that works reliably across all cases, and anyone selling one is probably selling something else. Consistency with the right movements beats intensity every time at this level of the spine.


