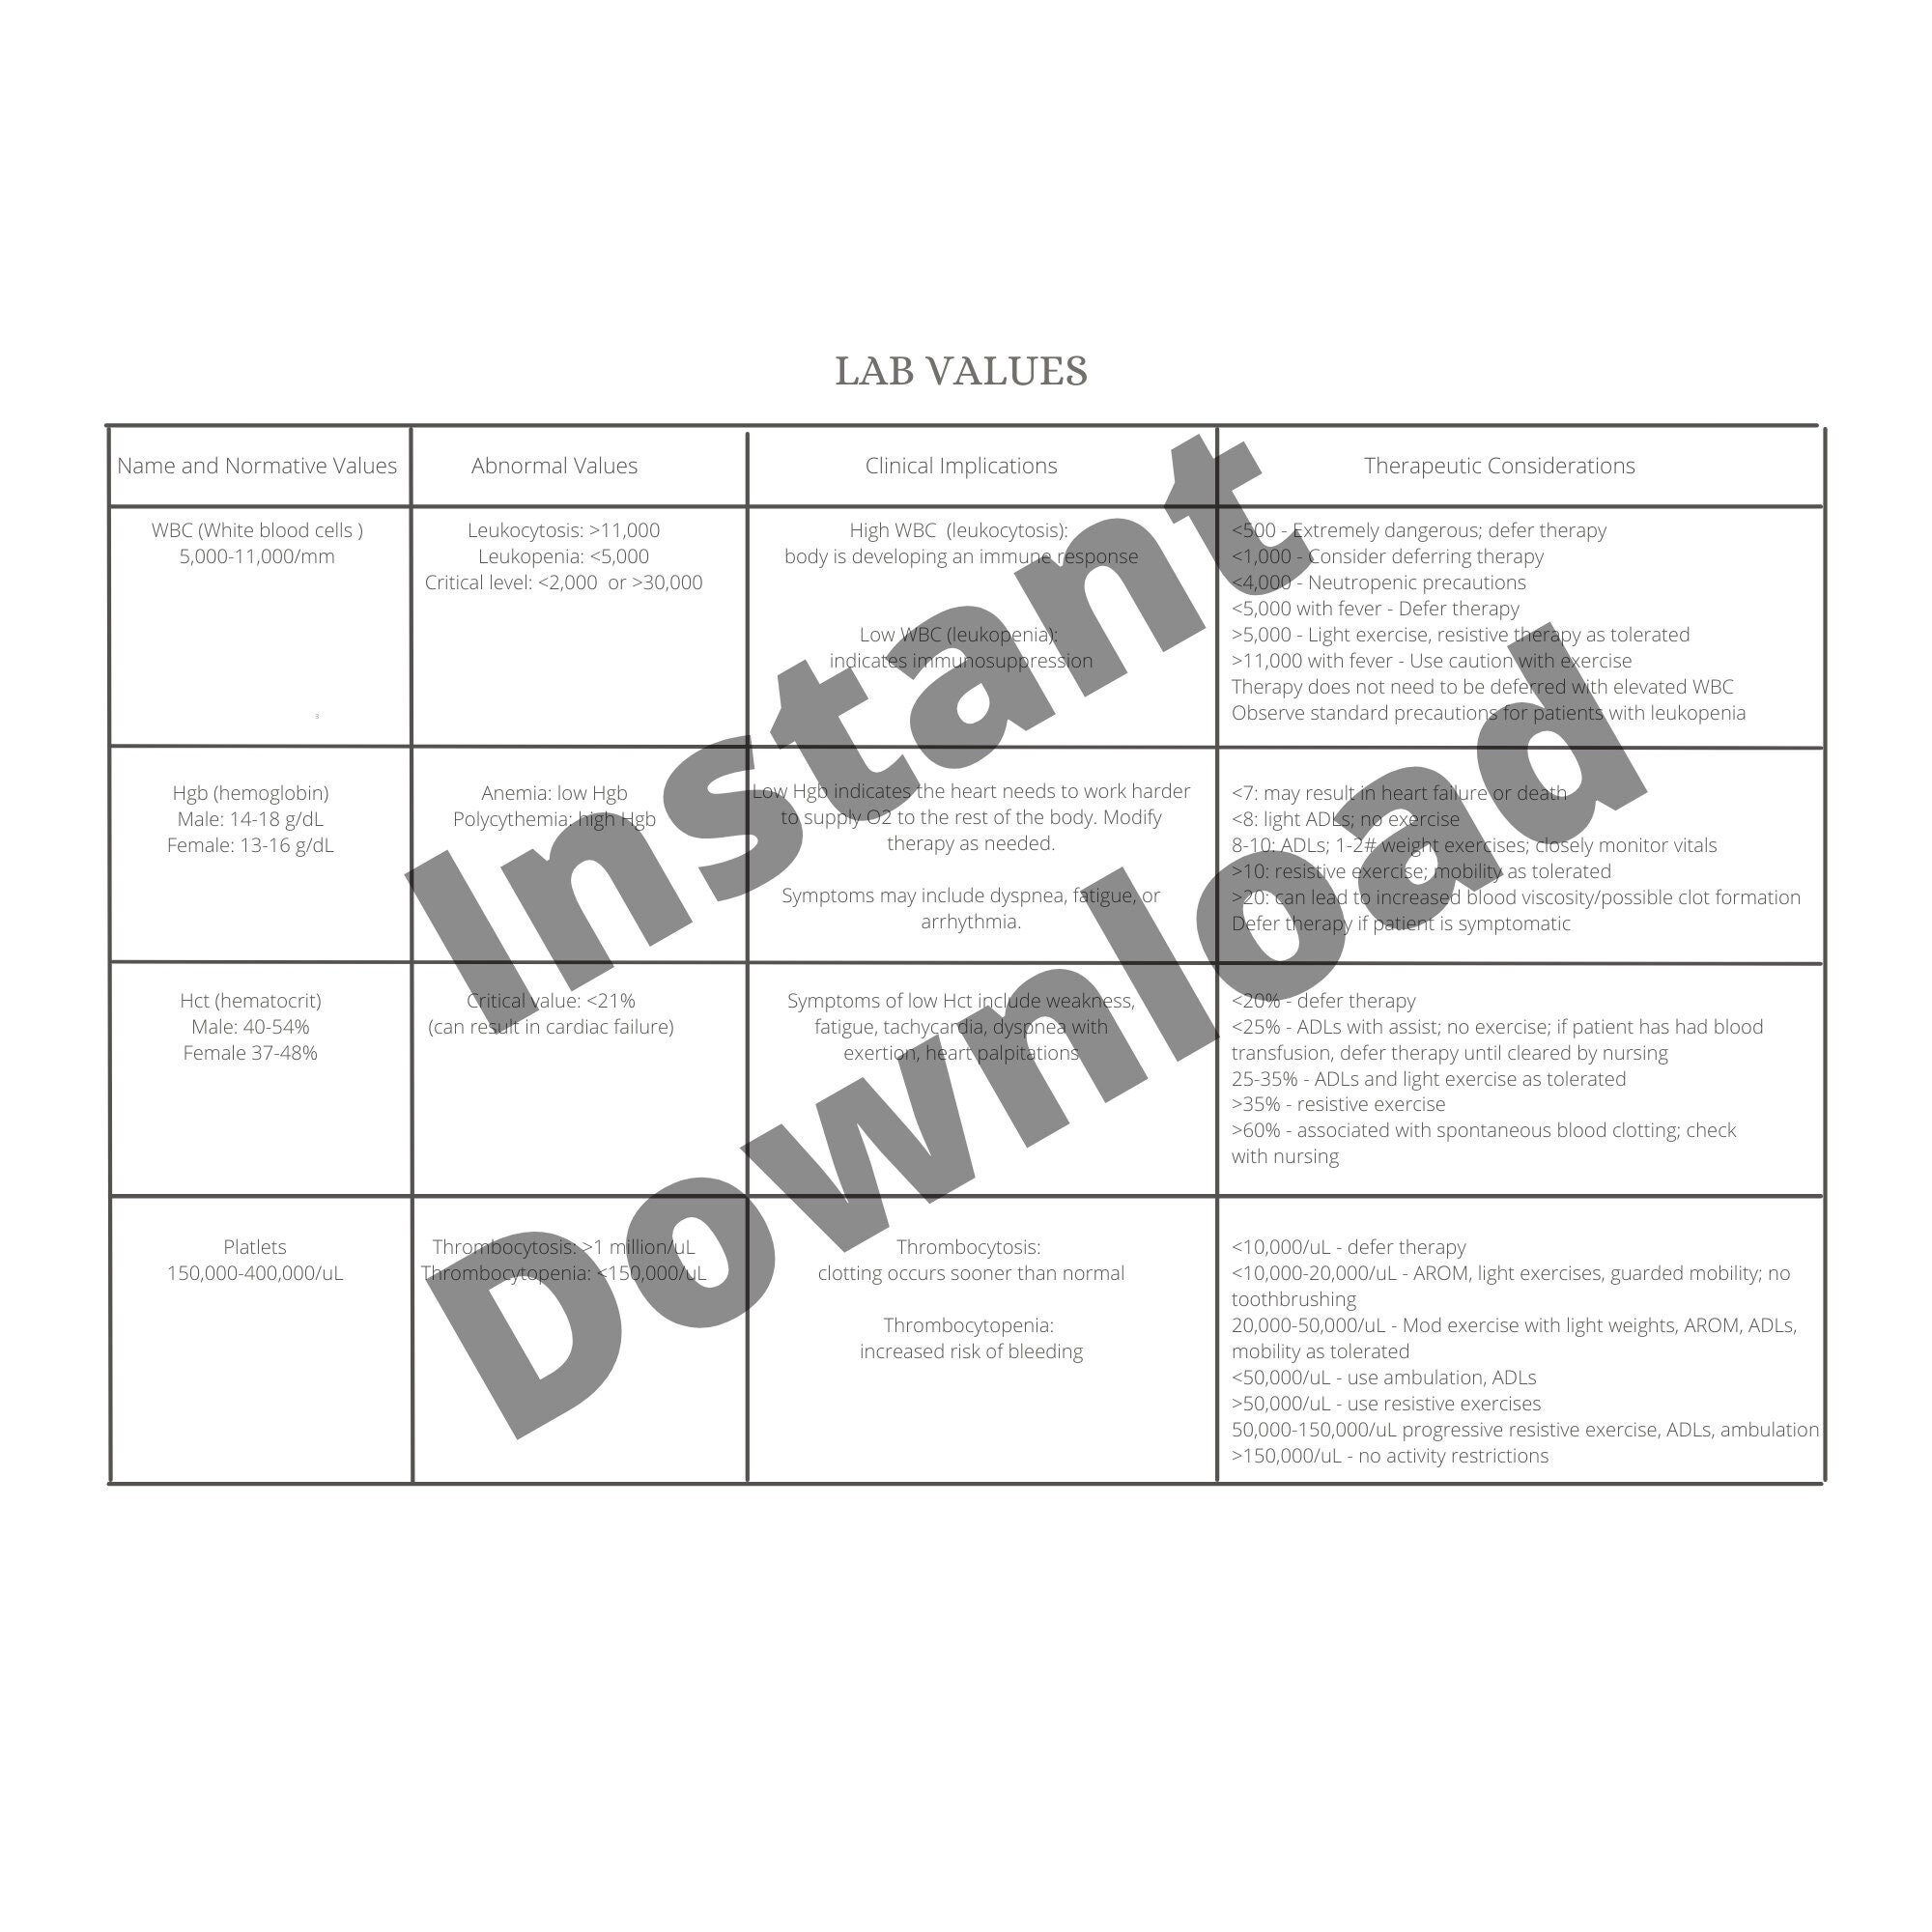
What Lab Values Physical Therapy Actually Means in Your Practice
Most people in PT programs learn what normal CBC values look like and move on. That is not enough. The reality is that patients walk through your clinic with abnormal results scattered across panels they never asked you to interpret, and you need to know which ones matter for treatment decisions and which ones are just background noise. I spent years ignoring lab work until a patient with a creatinine of 2.1 came in for knee pain, and I almost progressed their eccentric loading protocol without thinking about it. That changed how I approach everything. Here is the practical approach. You do not need to memorize every reference range. You need to know which values change your treatment plan and how quickly. The ones that actually matter for physical therapy fall into roughly four buckets: renal function, inflammatory markers, metabolic panels, and coagulation studies. Everything else is interesting but rarely alters what you do in the room. Renal function comes first because it affects everything. Creatinine and eGFR tell you whether your patient can safely handle certain modalities, compressive techniques, or post-exercise soreness that might push them toward acute kidney stress. A creatinine above 1.4 in a woman or 1.6 in a man means you adjust your fluid recommendations and avoid aggressive manual therapy that could cause significant rhabdomyolysis if they dehydrate. Not because you are scared, but because it is a known complication with deconditioned elderly patients who already have compromised clearance.
Inflammatory markers are where most therapists get it wrong. CRP and ESR are not just diagnostic tools for your referring physician. They tell you whether a patient is in an active disease flare. I had a rheumatoid arthritis patient once whose CRP was 45 mg/L during a routine visit. She wanted to start a heavy resistance program. I pushed back, she got frustrated, and she came back two weeks later with a swollen ankle that needed aspiration. Her CRP at that point was 82. The lesson is straightforward: elevated inflammatory markers mean tissue is actively vulnerable. You modify the plan until the numbers trend down. Metabolic panels matter more than people think. Sodium, potassium, and glucose levels affect neuromuscular function directly. A potassium below 3.0 mEq/L can cause real weakness that has nothing to do with your patient's mechanical status. I once attributed severe quad weakness in a post-op hip fracture patient to disuse, only to discover her potassium was 2.6 from diuretic use. We called her physician, corrected it, and her strength came back faster than expected. That is not a PT failure. That is a missed signal. Coagulation studies change your manual therapy choices. INR values above 3.0 mean you avoid deep stripping, aggressive Myofascial release, or any technique that could cause hematoma. It does not mean you stop treating. It means you switch to gentle mobilization, nerve glides, and education. I worked with a patient on warfarin with an INR of 4.1 who had chronic shoulder pain. We spent six weeks doing scapular stabilization and pendulum exercises instead of attempting any manual work on the rotator cuff. He improved significantly. The lab value dictated the approach, not the other way around.
How to Actually Use Lab Values Without Losing Your Mind
The process is simpler than it sounds. When a patient referral includes lab work, spend about five minutes scanning for the four categories I mentioned. Flag anything outside the reference range. Cross-reference the flagged values with your planned interventions. Adjust if needed. Call the referring provider if something is unclear. This usually takes three to five minutes per patient after you have done it a dozen times. Here is a specific workflow that works. Print or screenshot the lab report. Circle the abnormal values. Next to each one, write a single word: modify, caution, or proceed. Modify means you change the treatment plan significantly. Caution means you adjust intensity or technique. Proceed means you treat normally but monitor. I keep a small reference sheet on my desk with the key thresholds I use. It cuts the review time down to under two minutes once I know my own criteria. One common mistake is reading labs in isolation. A single elevated value means very little without context. A CRP of 15 could mean active rheumatoid arthritis or it could mean the patient had a minor upper respiratory infection the week before. Look at the trend, not the snapshot. When I started asking for serial labs on chronic patients, the picture became much clearer. Their inflammatory trajectories matched their clinical presentation far better than any single reading ever did.
Get the Full Details
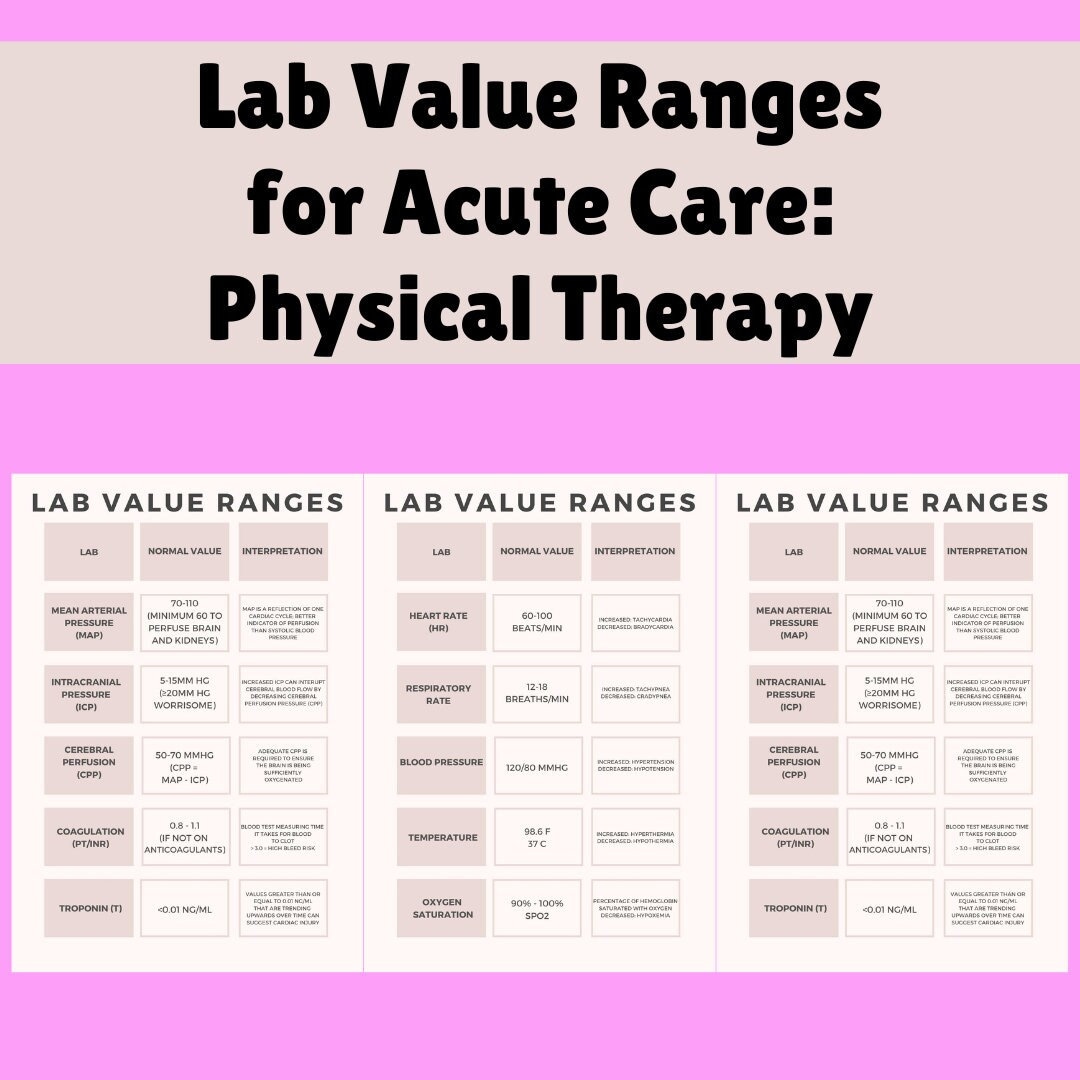
What Lab Value Interpretation Cannot Do for You
This is important enough to state plainly. Lab values do not replace your clinical assessment. They do not diagnose movement dysfunctions. They do not tell you whether a patient will respond to manual therapy versus exercise. Using labs as a substitute for good evaluation is how you end up treating numbers instead of people. The values inform your decisions. They do not make the decisions for you. There are also blind spots. Most patients do not bring their recent labs to appointments. You cannot assume availability. Building a habit of requesting them at intake is the practical solution. Another limitation is timing. A lab drawn today reflects the patient's status at the moment of the draw, which may have been two weeks ago. If their condition has changed since then, the values are already outdated. Always check the date on the report before using it clinically. The biggest bottleneck is that not all physical therapy clinics have a straightforward process for obtaining and interpreting lab work. It usually requires patient consent, a request to the referring provider, and sometimes a phone call to the lab itself. This takes time that most clinicians do not have built into their schedule. The workaround is to standardize it. Add a lab request form to your new patient paperwork. Train your front desk to follow up on results. Budget ten minutes per patient at the end of their first week for review. Once the system is in place, it becomes routine rather than an interruption.



