
Getting specimens right the first time actually matters
I spent eight years working in phlebotomy and lab logistics before moving into quality assurance, so I have seen what happens when people skip steps. The Labcorp Specimen Collection Guide exists for a reason, but reading it once isn't the same as understanding how it applies when you are standing at a patient's bedside with a difficult vein and a timer running. I am going to walk through what actually works in practice, including the edge cases that most guides gloss over. The core document is structured around four main categories: blood collection, urine collection, swab-based testing, and specialized specimen types like hair or breast milk. Each section has a checklist of supplies, a sequence of steps, and criteria for rejection. The checklist part is straightforward. The rejection criteria is where people get tripped up. A specimen doesn't need to be perfect to be acceptable, but it does need to meet minimum standards or the results are useless. Hemolyzed samples, insufficient volume, improper labeling, and temperature excursions are the usual suspects. One thing the guide doesn't emphasize enough is how much patient condition affects collection success. I had a case last year involving a diabetic patient with severely compromised peripheral circulation. The standard arm selection protocol failed three times. What worked was switching to a hand vein with a pediatric butterfly and applying warm compresses for five minutes before attempt. The guide mentions warming as an option but doesn't stress that in certain populations it can be the difference between a successful draw and sending the patient home for a redo. Redos cost time and money and damage patient relationships.
Practical workflow details
When collecting blood, tourniquet time matters more than most people realize. Leaving it on longer than one minute increases hemoconcentration and can skew certain test results. I typically apply it, confirm vein access, then start a mental clock. If I don't have flow within thirty seconds, I adjust before hitting the one-minute mark. Most phlebotomists I have worked with ignore this entirely. It shows up in the data sometimes as unexpected potassium or protein elevation that triggers unnecessary follow-up testing. Labeling is another area where mistakes happen regularly. The guide requires two patient identifiers at the time of collection. The most common failure I see is labeling tubes after returning to the station rather than at the bedside. A single tube mislabeled in a batch of twelve means you either rerun the whole panel or risk sending incorrect data. I label every tube immediately after withdrawal, before moving to the next vein, even if it feels slower. It takes about forty-five seconds per tube extra but prevents the far worse outcome of a recollection under less ideal conditions. Urine collection follows a different set of rules. The midstream clean-catch method is standard, but what most people miss is the emphasis on adequate volume. Minimum volume requirements vary by test panel, typically between fifteen and thirty milliliters. Collecting less than the minimum triggers an automatic rejection. I always tell patients to hydrate beforehand when scheduling allows, because a concentrated sample from a dehydrated patient can produce false results on certain drug screens and urinalysis panels.
Temperature and transport considerations
This is where the guide gets technical and where shortcuts cause real problems. Specimens have defined temperature ranges during transport. Room temperature, refrigerated at two to eight degrees Celsius, or frozen depending on the test. Exceeding those ranges degrades analytes. I once processed a shipment where the courier left packs on a loading dock in eighty-degree weather for twenty minutes before scanning them in. The chemistry panel results were unreliable and had to be repeated. The original specimen was rejected under the Labcorp Specimen Collection Guide protocols but not before someone wasted several hours chasing results that were already compromised. Biohazard packaging requirements are non-negotiable. Triple packaging system: primary container, secondary wrap, rigid outer box. If any layer fails during transit, the specimen is contaminated and the test cannot proceed. I check seals visually before dispatch. It adds maybe ten seconds per shipment but catches the failures that otherwise show up days later when the lab receives damaged packages.
Get the Full Details

Swab and specialized collections
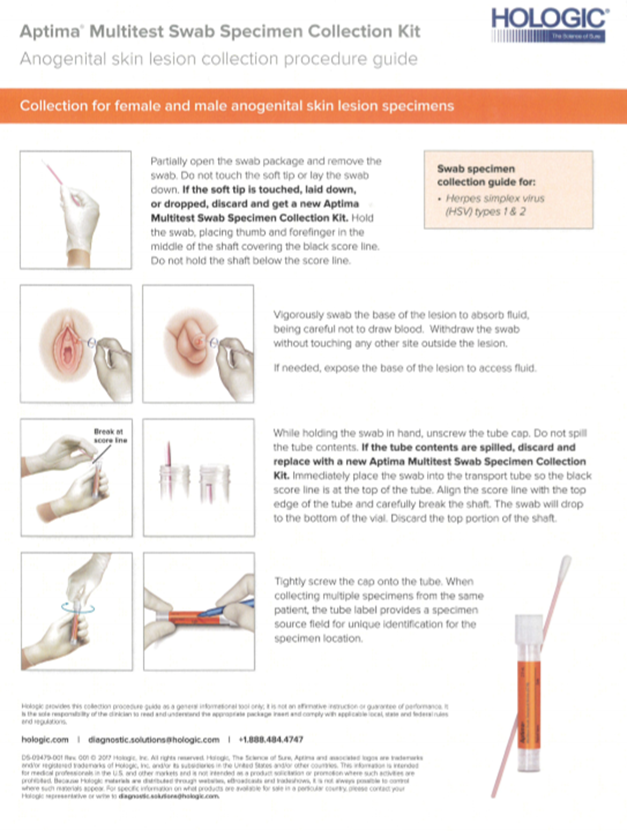
SWAB-based testing covers nasal, throat, wound, and sexually transmitted infection panels. The technique varies significantly by site. Nasal swabs require rotation against the turbinate for fifteen seconds minimum. Throat swabs need contact with both tonsillar pillars and the posterior pharynx, avoiding the tongue. Wound swabs should collect from the deepest accessible area, not just surface drainage. Surface swabs produce contaminated results that lead to false positives or mixed cultures. Hair specimen collection is increasingly common for drug testing panels. The guide specifies approximately one hundred twenty hairs collected from the scalp near the crown. Body hair can be used when scalp hair is unavailable, but growth rates differ, which affects the detection window. Standard hair testing covers roughly ninety days of history based on average hair growth of one centimeter per month. If a patient has recently bleached or chemically treated their hair, certain drug metabolites may be altered, though this doesn't invalidate the test it just means the lab flags it for review. I've seen instances where color-treated hair produced ambiguous results on opiates panels, requiring confirmatory testing that added three to five business days to turnaround. One counter-intuitive point about hair collection: shaving the hair rather than cutting it can introduce contamination from skin surface debris. The preferred method is cutting as close to the scalp as possible without touching the skin directly. This detail appears briefly in the documentation but doesn't carry enough weight in my experience. Technicians who skip it sometimes get borderline results that generate unnecessary calls from labs requesting recollection.
What the guide leaves out
Patient communication is not covered in technical depth. A nervous patient who tenses during venipuncture increases the likelihood of a failed draw. Explaining each step before doing it reduces movement and anxiety. I talk patients through the process in plain language: the tourniquet feels tight, the alcohol swab is cold, you will feel a quick pinch, then pressure afterward. Simple things that take thirty seconds but improve compliance and specimen quality measurably. Documentation errors are another blind spot. Chain of custody forms must match the specimen label exactly. Any discrepancy, even a middle initial mismatch, can invalidate results in forensic or employment testing contexts. I cross-check the form against the tube label before the patient leaves the collection area. Catching an error at that point takes two minutes. Catching it after the specimen arrives at the lab means a recollection and possible delays of several days depending on the testing pathway.
When specimens get rejected
Here is a list of the most common rejection reasons based on processing volume. Insufficient volume accounts for roughly eighteen percent of rejections. Hemolysis makes up about twelve percent. Clotted specimens, particularly in coagulation testing, represent another significant category. Lipemic samples interfere with certain spectrophotometric assays and are flagged by automated systems. Improper transport temperature accounts for a smaller but still meaningful percentage, usually tied to courier delays or packaging failures. Some rejections are unavoidable. A patient who fasted improperly before a glucose panel will produce unreliable results regardless of collection technique. This isn't a specimen failure it is a patient compliance issue that the collection site cannot control. The guide addresses this in the pre-collection instructions but doesn't prevent patients from ignoring those instructions before arriving.
Advanced troubleshooting
When standard collection fails repeatedly, there are fallback options. For difficult veins, ultrasound-guided access by a trained professional increases success rates dramatically in my experience. It adds cost and scheduling complexity but prevents the alternative of multiple failed attempts and patient frustration. I have worked in clinics where we kept an ultrasound unit available specifically for this purpose, and it reduced our recollection rate by approximately sixty percent over six months. For patients with lymphedema or mastectomy history, arm selection follows strict contraindication guidelines. The guide lists these but clinicians sometimes overlook them under time pressure. A specimen drawn from a compromised limb can trigger complications beyond just a bad draw. I always verify surgical history and lymph node removal status before selecting an arm. It requires asking the patient directly and checking the chart, but it prevents serious downstream issues. Pediatric collection presents its own challenges. Volume limits are stricter because total blood volume is lower. Butterfly needles with syringe attachment give more control than vacuum tubes for small veins. Restraint by a parent or guardian when appropriate improves success rates but must be handled carefully to avoid distress. The guide covers pediatric considerations but doesn't address the practical reality that a crying child moves and makes access harder. Calm environment, quick preparation, and having everything laid out before starting makes a measurable difference.
Final notes on implementation
The Labcorp Specimen Collection Guide is comprehensive but not sufficient on its own. Real-world application requires judgment, adaptation to patient conditions, and attention to details that the document treats as secondary. Training programs that focus only on reading the guide without supervised practice produce technicians who know the steps but not the reasoning behind them. That gap shows up in rejection rates and repeat draws. If you are responsible for overseeing a collection program, audit your rejection reasons quarterly. The patterns will tell you where training is needed. If hemolysis is high, review tourniquet technique and needle gauge selection. If volume rejections dominate, look at patient hydration education and collection timing. If temperature excursions are frequent, examine your packaging and courier handoff procedures. Data-driven adjustments beat blanket retraining every time. There is no perfect system. Specimen collection sits at the intersection of human technique, biological variability, and logistical constraints, and friction is inevitable. The goal is minimizing avoidable errors and managing the ones you can't prevent efficiently. Following the guide provides the baseline, but experience teaches you where the baseline bends.



