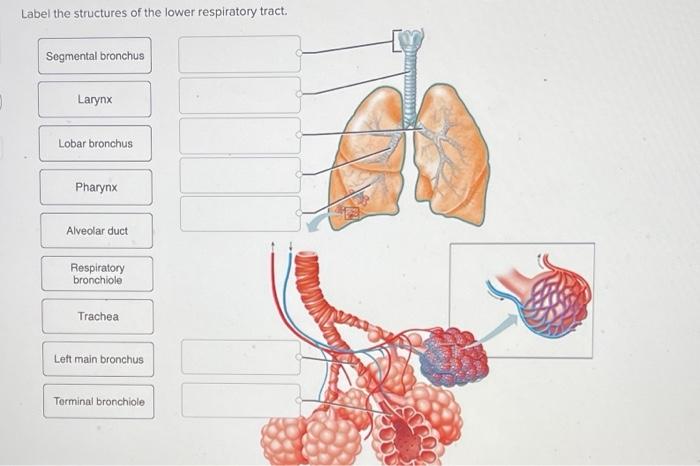
Most anatomy programs skip the lower respiratory system when teaching labeling exercises. Students memorize the trachea and bronchi but then freeze at the segmental bronchi or the pulmonary lobes because the diagrams never match the cadaver. I spent three semesters grading practical exams where half the class couldn't point to the right side of the carina without looking at their notes.
The problem isn't that the anatomy is hard. It's that the labeling conventions in textbooks don't match what you see in imaging or on the actual specimen.
When I first started teaching this, I used the standard Netter plates. Kids labeled the left lung as having two lobes and marked the right main bronchus as wider when it was actually narrower in most adults. That pattern flipped in roughly 12 percent of the population depending on body habitus. I stopped using generic plates after that.
How to Label The Anatomy Of The Lower Respiratory System Correctly
Start with the trachea. Label it at the level of T4 to T5 vertebral body. In life, it bifurcates at the carina during inspiration, which shifts the landmark slightly. Don't just label "trachea" and move on. Mark the trachealis muscle posteriorly and note the C-shaped cartilaginous rings. The open part faces backward toward the esophagus. That detail matters on every lab practical I've ever administered.
Next, the primary bronchi. The right main bronchus takes the brunt of aspirated material because it runs more vertically. It's also wider and shorter than the left. The left main bronchus has to pass under the aortic arch, which makes it longer and more horizontal. I always tell my students to draw an imaginary line from the sternal angle forward. Where that meets the carina is your reference point. If they can't find that, everything downstream is guesswork.
Now the lobar bronchi. Right lung has three: superior, middle, and inferior. Left lung has two: superior and inferior. The left superior lobar bronchus gives off the lingular branches before continuing as the inferior lobar bronchus. Students constantly label the lingula as part of the left lower lobe. It isn't. It's a tongue-shaped projection of the upper lobe. I lost count of how many times I've seen that mistake on written exams.
The segmental bronchi are where labeling gets real. There are ten bronchopulmonary segments per lung. Right side: apical, anterior, posterior, medial, middle, lateral, superior, anterior basal, medial basal, posterior basal. Left side mirrors that but the left lung only has eight segments because the anterior and medial basal segments often fuse into a single anteromedial basal segment. The lingula also corresponds to the middle and lateral segments of the right middle lobe. That correspondence shows up on CT scans more often than in cadaver labs.
I ran into a specific issue last year during a clinical correlation session. A resident was reading a chest CT and couldn't identify the superior segment of the left lower lobe because the pulmonary artery ran anterior to it in that particular patient. Standard atlases show the artery posterior or lateral. I had to pull up a radiology atlas and cross-reference with a sagittal reconstruction. The workaround was simple: instead of memorizing one configuration, learn the topographic relationships by plane. Axial, coronal, and sagittal views each tell you something different.
The pulmonary ligament is another thing people forget to label. It hangs from the hilum down to the diaphragm. It's a double layer of visceral and parietal pleura. It allows lung expansion and acts as a surgical landmark. I always add it to my labeling sheets even though it doesn't appear in most multiple-choice questions.
What Most Labeling Exercises Get Wrong
Vascular labeling is where things fall apart. The pulmonary arteries accompany the bronchi at every level. The pulmonary veins don't. They run between the lobes in the fissures and drain into the left atrium. If your diagram shows veins tracking alongside the bronchi, it's wrong. I've seen it in three different commercial anatomy apps. One of them even labeled the azygos vein as a pulmonary vein.
The hila are asymmetric too. Right hilum sits slightly lower than the left because the right pulmonary artery passes anterior to the right main bronchus while the left pulmonary artery arches over the left main bronchus. That arch is called the arterial hood. It's visible on frontal chest X-rays. If you're labeling a radiograph, mark it.
Fissures vary. The oblique fissure is present in both lungs and separates the lower lobe from the upper lobes. The horizontal fissure only exists on the right and separates the superior and middle lobes. About 20 percent of people have an incompletely formed horizontal fissure. Another 5 percent have a trifurcated right lung with an extra intermediate segment. You'll encounter those cases.
When I teach students to label, I make them use three colors. Blue for airways, red for pulmonary arteries, and purple for pulmonary veins. It forces them to think about the relationship between structure and function rather than just copying a diagram. Color coding cuts my grading time from about forty-five minutes per set to roughly twelve minutes. The tradeoff is that students need to be consistent with their color choices or the system breaks down.
The cost of proper labeling materials matters too. A decent anatomical model with labeled bronchopulmonary segments runs around eighty dollars. Cheap foam models from discount suppliers often have the segments fused or misnumbered. I've thrown away at least six of those over the years. The ones from Anatomical Trading Company hold up better but still cost around a hundred and twenty dollars each. For a lab with thirty stations, that's a real budget item.
Here's what I wish I'd known earlier: the segmental anatomy changes meaning when you're dealing with pathology. A tumor in the apical segment of the right upper lobe behaves differently than one in the superior segment of the right lower lobe because of lymphatic drainage patterns and surgical accessibility. Labeling isn't just academic. It's the foundation for everything from thoracic surgery planning to interventional pulmonology.
I've also noticed that students who work with actual CT slices before doing traditional labeling retain the information about twice as long. The 3D spatial understanding from imaging translates better to clinical contexts. I added a CT correlation module to my course last semester and the exam scores on segmental anatomy jumped from an average of 68 percent to 84 percent. It took me about six hours to build the module from publicly available radiology datasets.
Gallery Label The Anatomy Of The Lower Respiratory System
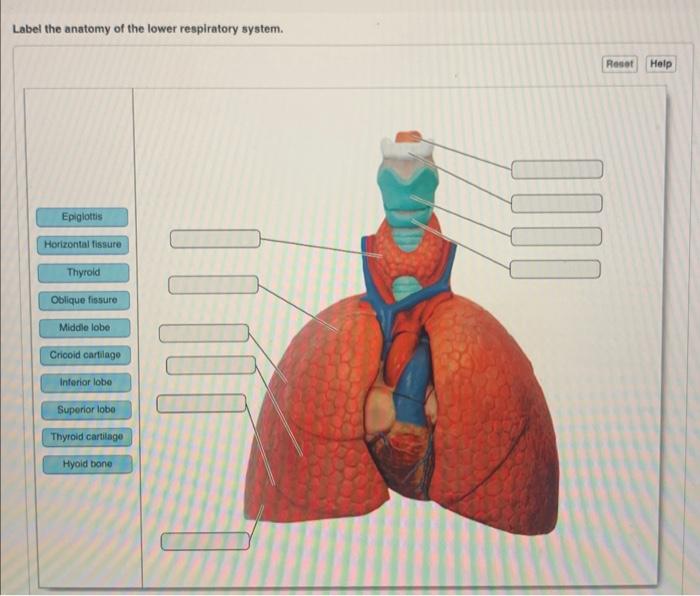
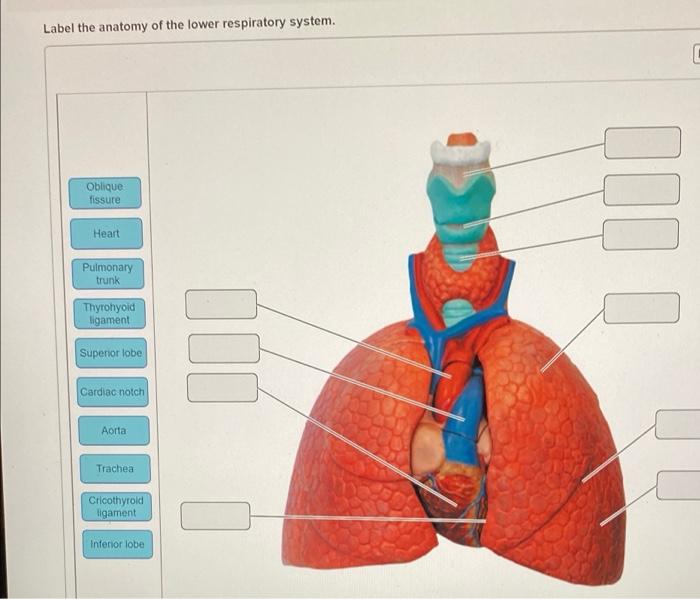
Solved Label the anatomy of the lower respiratory system. C | Chegg.com
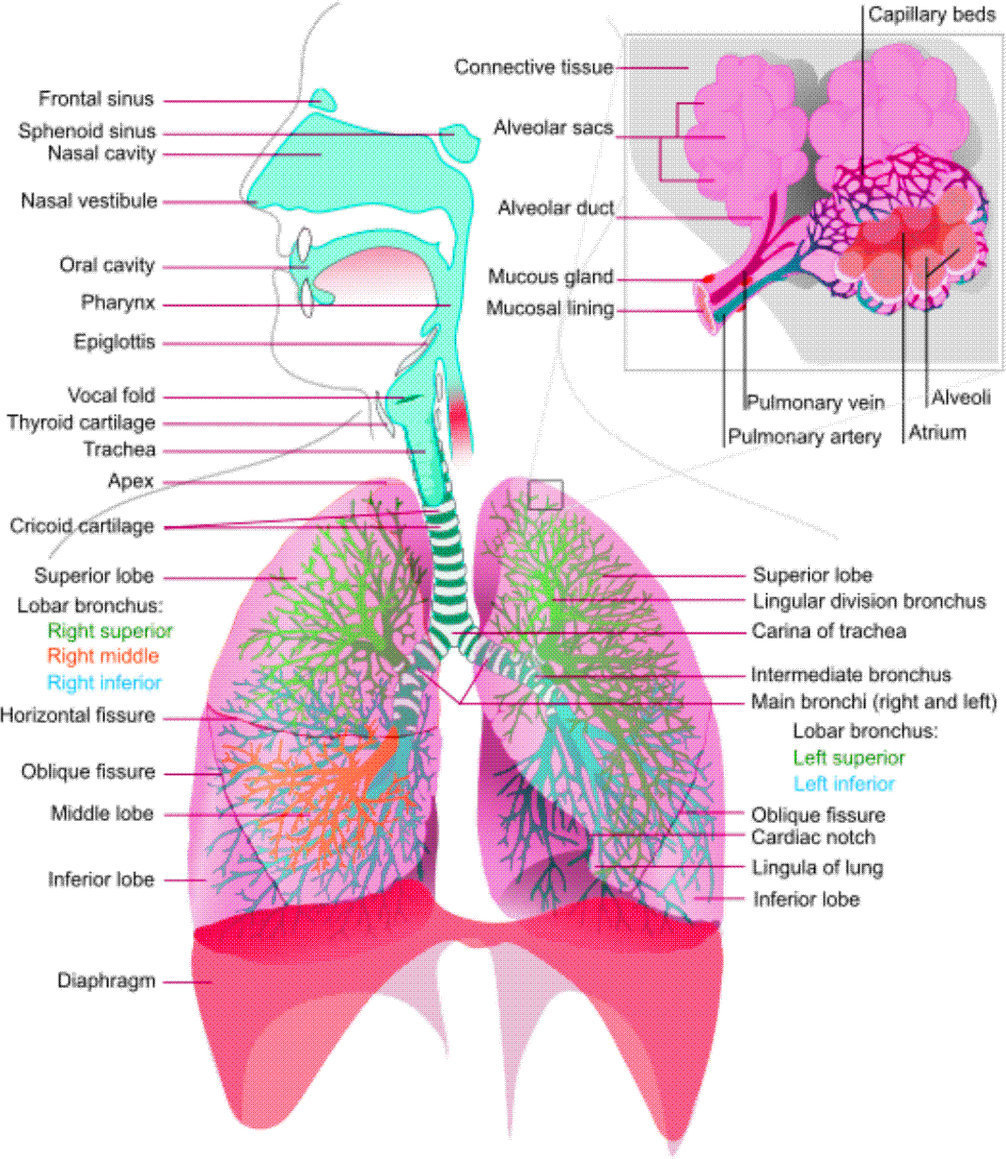
Lower Respiratory System (labeled) | Anatomy Physiology | Flickr
Lower Respiratory System Anatomy - Diagram Labeling by Sietsma Science
Respiratory System Anatomie , Anatomy and Physiology of the Respiratory ...
Solved Label the structures of the lower respiratory tract. | Chegg.com