Labeling Body Organs in Medical Images: A Practical Guide
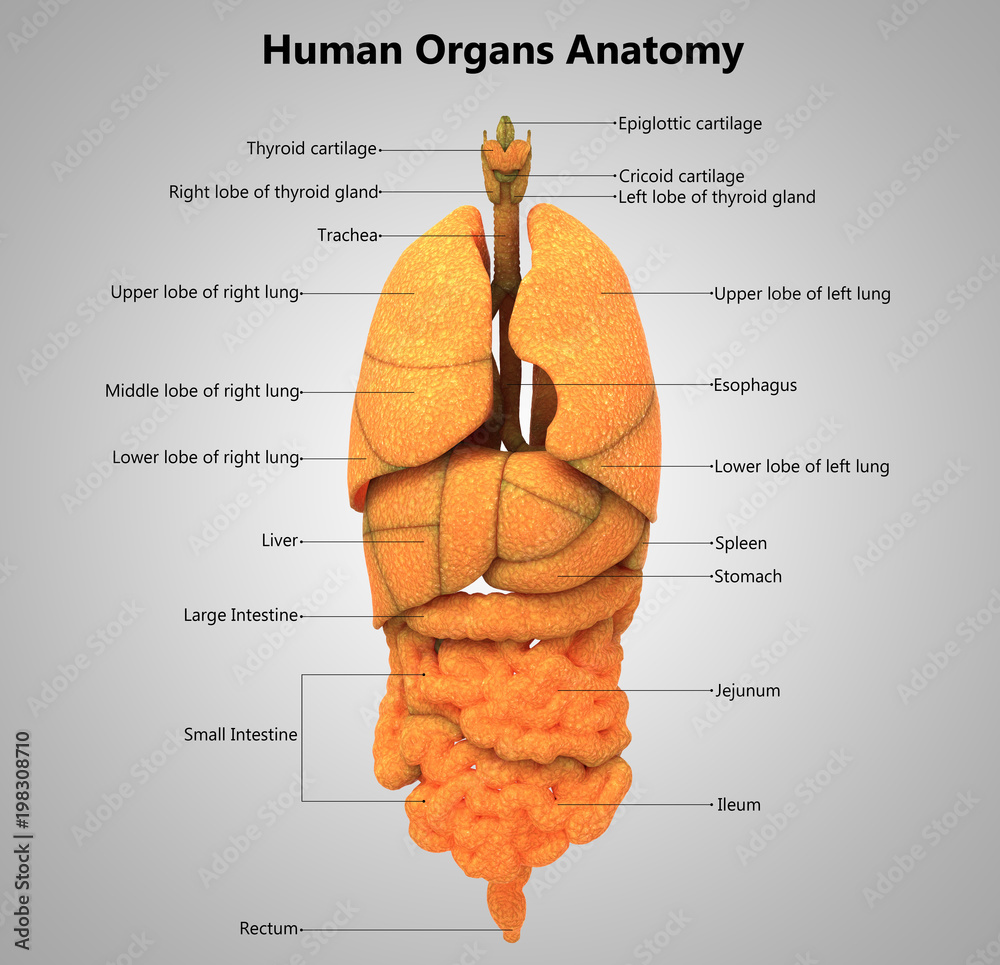
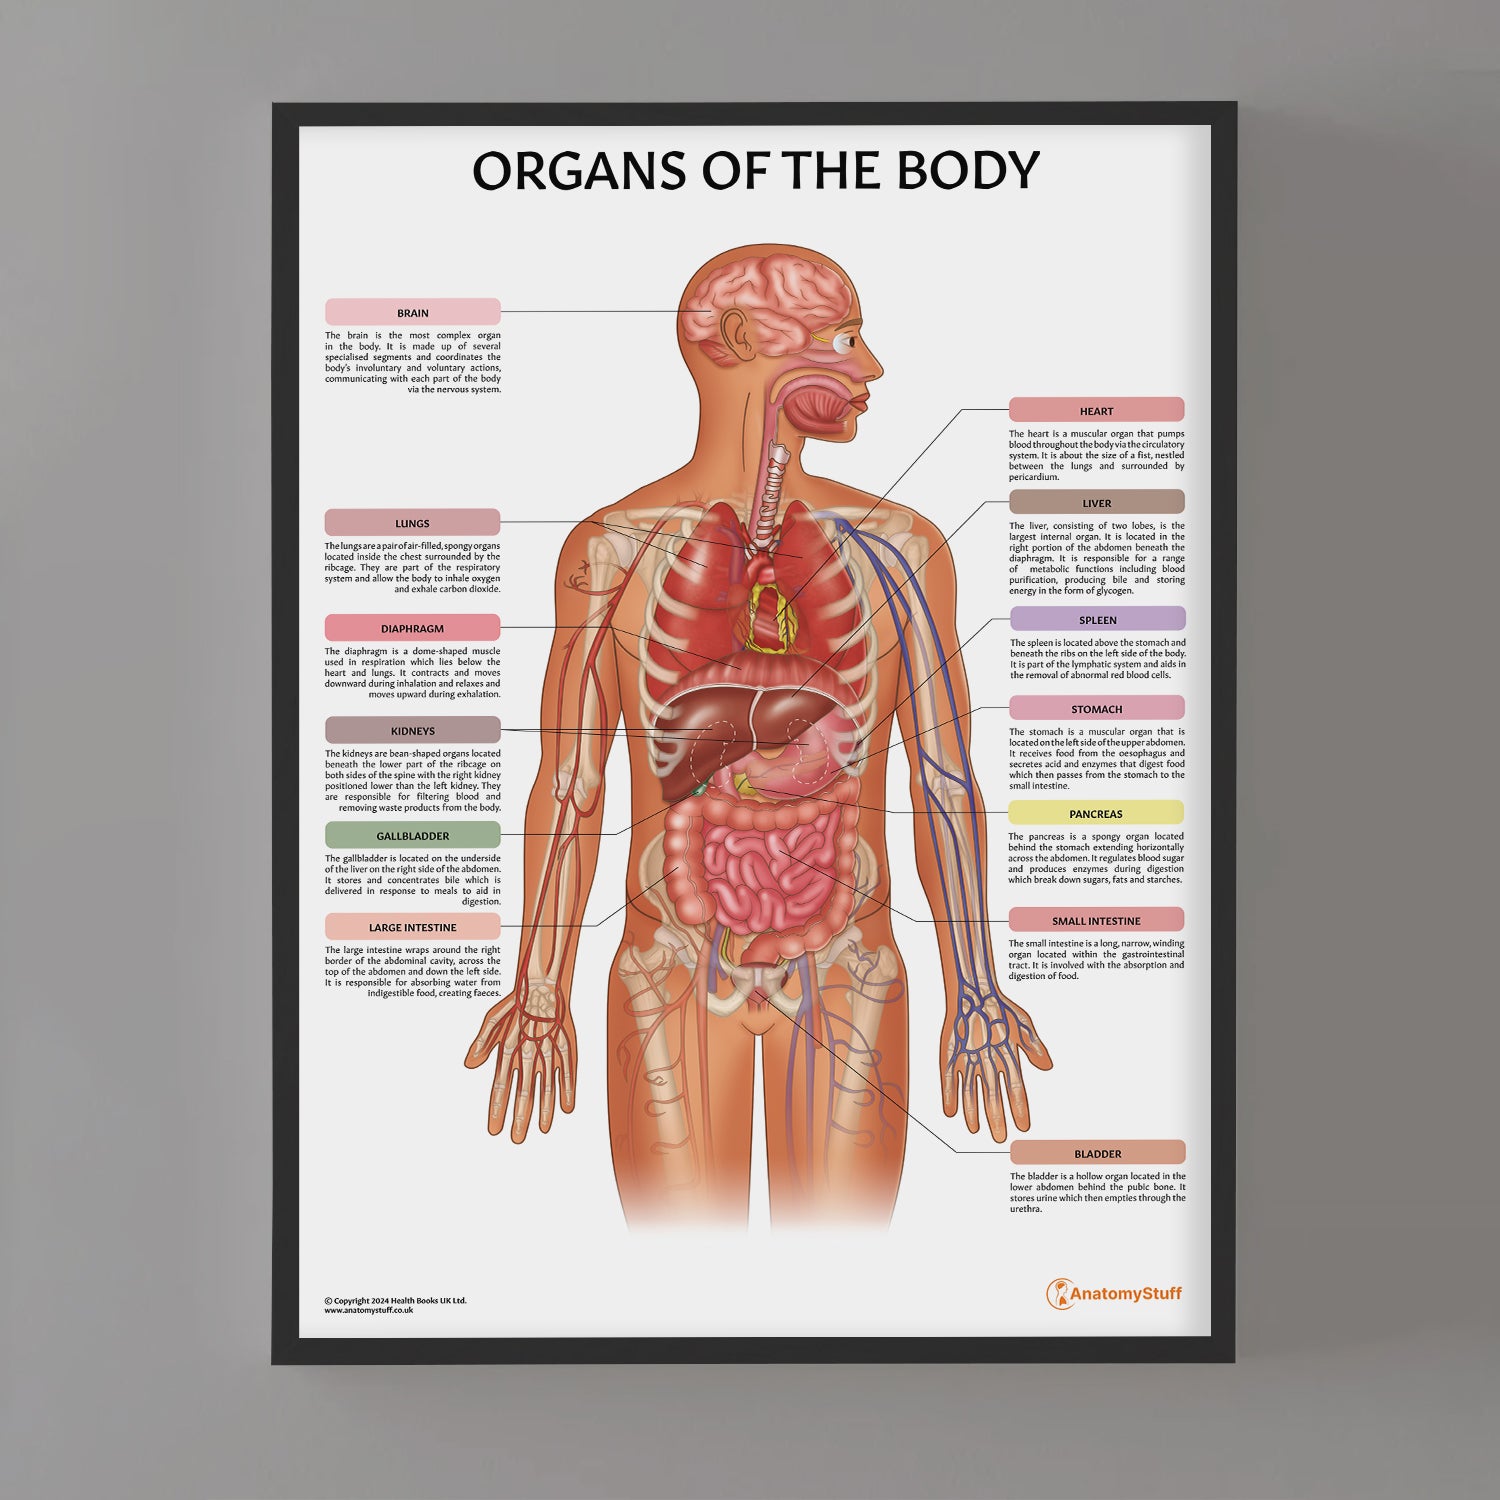
Labeling body organs is one of those tasks that sounds straightforward until you actually open an annotation tool and start clicking around a CT scan. The concept itself is simple enough — you go through medical imagery and tag regions corresponding to lungs, liver, kidneys, heart, spleen, and so on. What makes it non-trivial is everything in between: dealing with ambiguous boundaries, inconsistent organ shapes across patients, and figuring out which tool actually gives you the best return on your time. I've spent more time than I care to admit drawing masks over abdominal CTs and chest MRIs, usually at 11 PM on a Tuesday when someone needs the dataset turned around by morning. The process starts with picking the right annotation format. Most projects end up using eitherpolygon-based segmentation or bounding box labeling, sometimes both depending on whether you're training a detection model or a segmentation model. Polygon segmentation gives you the accuracy you need for organs with irregular borders like the kidneys or spleen, but it's also significantly slower. Bounding boxes are fast but lose detail on edges, which matters when the downstream task is something like surgical planning rather than just classification. For tools, I default to Label Studio or CVAT for larger projects. Label Studio is easier to set up quickly and works fine for smaller teams. CVAT has better handling of volumetric data like DICOM sequences and its interpolation feature alone saves an enormous amount of time — you label a few key slices and it fills in the frames between them, which is incredibly useful when you're working through a full abdominal series where adjacent slices look nearly identical anyway.
Here's a realistic example of the workflow. Say you're labeling liver, spleen, kidneys, pancreas, and gallbladder from an axial CT scan. You open the first slice, turn to multi-label mode, and start drawing. The liver is usually straightforward on the right side. The spleen is smaller but distinct. Both kidneys require more care because their borders can blend into surrounding fat tissue, especially on lower-quality scans. The pancreas is where things get annoying — it's flat, elongated, and its edges barely contrast with adjacent structures. I spent weeks on one project trying to figure out the best approach for pancreatic segmentation, and what actually worked was switching to a different windowing preset. Standard soft-tissue windows made the pancreas nearly invisible. Bone and lung windows helped with some structures but not others. The trick was setting a custom window width and level that sat somewhere between the two, around width 350 and level 40, which gave just enough contrast to trace the pancreas without drowning the rest of the anatomy in noise.
The Counter-Intuitive Stuff Nobody Tells You
Most people approaching organ labeling for the first time spend way too much time perfecting individual organ contours. The bigger problem is consistency across the entire dataset. If you're labeling images from multiple scanners or multiple protocols, the same organ can look completely different between a GE 120kVp scan and a Siemens 140kVp scan. Your labeling guidelines need to account for that before you start, or you'll end up with a dataset where half the kidney masks are tight and the other half are loose, and then your model learns nothing useful. Another thing that catches people off guard: organ adjacency is a major source of errors that nobody plans for. The right kidney sits right next to the liver. The pancreas touches the stomach. When you're drawing masks in 2D slices, it's easy to accidentally extend a liver mask into the kidney or include part of the duodenum in your spleen outline. The workaround I settled on was working in layers and doing a quick overlap check after every case. If the tool lets you visualize mask intersections, use it. If not, just toggle layers on and off and compare. Takes thirty seconds extra per case and probably catches more errors than you'd make before noticing.
Get the Full Details
When Labeling Organ Data Falls Apart
Let me be blunt about the limitations. This approach doesn't work well for pathologically altered anatomy. If you're labeling organs from patients with tumors, post-surgical changes, or severe atrophy, your carefully drawn masks become unreliable fast. A shrunken kidney from chronic disease doesn't follow the same spatial rules as a healthy one, and most pre-built annotation templates won't account for that. You end up either spending three times as long on each abnormal case or accepting lower quality labels, which defeats the whole point. There's also the issue of missing organs. Some scans don't include the full field of view. You might be labeling a chest CT that happens to catch the very top of the liver, or an abdominal scan that cuts off before reaching the kidneys. Deciding whether to include partial organs in your annotations is something you need to agree on with your team upfront, because mixing datasets where some annotators included partial organs and others didn't is a recipe for model confusion. If your project involves a lot of pathological cases or non-standard anatomy, consider using a semi-automated tool like 3D Slicer with Segmentation extension or MITK. These let you seed regions and use region-growing algorithms to generate initial masks, which you then refine by hand. It's not perfect — the algorithms make mistakes, sometimes big ones — but for abnormal anatomy where standard templates fail, they're faster than drawing from scratch and usually produce acceptable results after correction.
The core takeaway is that labeling body organs is less about having the right tool and more about having clear, written guidelines that every person on your annotation team actually follows. Without that, you'll spend more time cleaning up inconsistent labels later than you'd save by rushing through the initial labeling phase.