Running Tests Is Easier Than Getting Them To Mean Anything
I have spent years pulling labs for integrative and functional medicine clients, and the first thing I learned is that standard reference ranges will hide more problems than they reveal. The difference between a routine panel and a functional workup isn't a single specialized assay. It is a different way of reading the same data. Most people ordering these tests start with CMP, CBC, lipid panel, and TSH. That gets you a baseline. It does not get you anywhere useful if the patient is actually symptomatic. This approach treats lab results as a map rather than a yes-or-no checklist. The same value can be normal in one context and clinically significant in another. A TSH of 4.2 sits comfortably inside the lab range. For a patient with fatigue, hair loss, and cold intolerance, it is often the signal worth chasing. That is the fundamental shift. The methodology itself is straightforward enough, but the execution has real pitfalls. The core principle is that functional medicine labs look at physiology, not just pathology. Inflammation markers, oxidative stress indicators, detoxification capacity, gut integrity, hormone metabolite ratios, and micronutrient status all feed into a picture you cannot see from a standard panel. You combine that with detailed history taking. The labs confirm or redirect the clinical hypothesis. They rarely create it from scratch.
I recommend starting with a tiered testing strategy. Tier one covers what every practitioner should have access to: CBC with differential, CMP, fasting glucose and insulin, HbA1c, lipoprotein subfractions including ApoB and Lp(a), hsCRP, ferritin, B12, folate, 25-hydroxy vitamin D, and a full thyroid panel with TSH, free T4, free T3, and reverse T3. That gives you a foundation. Tier two adds the functional layer: organic acid test, food sensitivity IgG panel, heavy metal challenge or baseline urine minerals, stool analysis with intestinal permeability markers, and a comprehensive hormone panel including DHEA-S and morning cortisol. Tier three is situational. Mast cell mediators, methylation panel, Lyme and coinfections, and specialized mitochondrial markers belong here. Ordering them all at once is a mistake. It produces noise. I usually space tier two out by four to six weeks after the first results come back. That gives you time to see which markers actually move and which were just biological static.
Interpretation Is Where Things Fall Apart
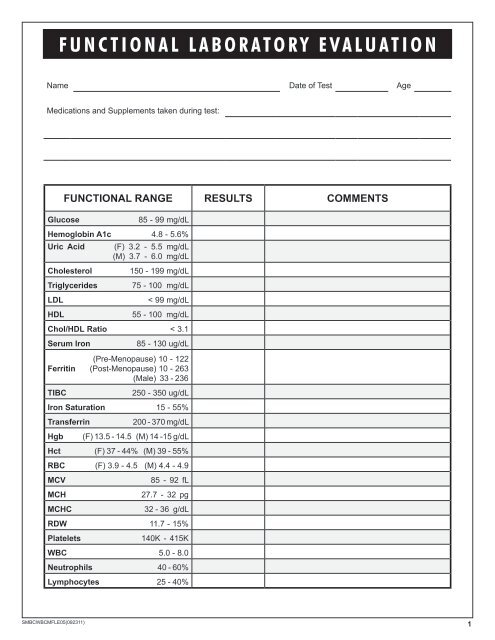
Reference ranges come from population averages, not healthy populations. That distinction matters enormously. The lab's normal range for vitamin D might cap out at 30 ng/mL, but the literature supporting optimal immune and metabolic function generally points toward 40 to 60 ng/mL. When a patient sits at 32, the lab marks it normal. The functional perspective flags it as suboptimal. Both readings are correct within their own frameworks. The question is which framework serves the patient. Hormone metabolism requires the same careful lens. Total testosterone looks fine while free testosterone is clinically low because sex hormone binding globulin is elevated from insulin resistance. Shouting about total T and missing the free fraction is a common error I see. Same pattern with thyroid. High reverse T3 with normal TSH and normal free T4 suggests peripheral conversion issues, not thyroid gland failure. Treating that with levothyroxine alone will not fix the underlying problem. The organic acid test deserves special attention here. It measures microbial metabolites and neurotransmitter breakdown products in urine. It is useful for identifying gut dysbiosis, oxalate issues, and certain neurological patterns. The downside is that it requires a first morning void and strict timing. Contamination, hydration status, and recent supplement use can distort results easily. I always ask patients to avoid high dose biotin for at least 48 hours before collection and to document exactly what they ate and took in the prior two days. Without that context, an OAT result is a puzzle missing half the pieces.
Get the Full Details

A Real Example From Practice
Last year I had a patient whose labs looked completely unremarkable on paper. CBC, CMP, thyroid panel, lipid panel, vitamin D, B12, ferritin, hsCRP, everything fell within reference ranges. She presented with severe brain fog, joint pain, and chronic gastrointestinal discomfort. Standard workups had exhausted her. I ordered a stool test with zonulin and calprotectin alongside a food sensitivity panel and a heavy metal urine test with baseline and chelation collection. The calprotectin was mildly elevated at 68 mcg/g, which most labs flag as normal. The standard range goes to 50, but anything above 30 in a symptomatic patient indicates intestinal inflammation. Zonulin was elevated, confirming increased intestinal permeability. The food sensitivity panel showed reactions to dairy, gluten, and eggs. The heavy metal panel revealed elevated mercury at 14 micrograms per liter against a reference range that capped normal at 8. The trick here was interpreting borderline values through a clinical lens rather than dismissing them. The lab did not flag any of those results as abnormal. Only the clinical context made them actionable. I started a targeted elimination diet, addressed gut permeability with specific nutrients and dietary modifications, and pursued a cautious chelation protocol for the mercury. Symptom improvement became noticeable within six weeks.
Practical Workflow Tips
Timing matters more than most practitioners account for. Cortisol should be collected at 8 AM if you are using serum or saliva. Saliva testing allows four collections throughout the day and gives a much clearer picture of diurnal rhythm. Blood draws for inflammation markers should happen in the morning before exercise or illness, because acute inflammation from a gym session or a mild cold can skew CRP and ESR for days. Fasting glucose and insulin require at least a 12-hour fast. Any deviation inflates insulin independently of actual metabolic health. When ordering through functional medicine laboratories like Doctor's Data, Great Western, or Metrix, request their interpretive comments. Those commentaries often provide context that the automated lab reports miss. They flag patterns rather than isolated numbers. The turnaround time is typically seven to fourteen business days, which is slower than routine labs but worth the wait for the additional analysis. Insurance coverage for functional lab testing is limited. Most organic acid tests, comprehensive stool panels, and food sensitivity tests fall outside standard reimbursement. Expect to pay between 150 and 400 dollars per test out of pocket. Prior authorization sometimes helps for the more expensive panels. Documentation should emphasize medical necessity with clear symptom correlation. Generic statements about functional testing do not pass review. Specific symptoms tied to suspected pathology do.
Limitations That Matter
Functional lab testing has real constraints. Variability between laboratories is significant. Two different vendors can produce different ranges for the same analyte, and the same sample tested at two different functional labs may yield different classifications. This is not necessarily error. It is methodological difference. I always recommend using the same laboratory for repeat testing to maintain consistency across time. False positives are common with food sensitivity IgG panels. These tests detect exposure, not necessarily intolerance. A patient may show reactivity to ten different foods based on the panel, but only three or four drive actual symptoms. Clinical correlation through elimination and reintroduction is mandatory before making dietary decisions. IgA-based food sensitivity testing tends to be more specific for gut-related reactions, but availability is narrower. Heavy metal testing through provocation chelation with DMSA or EDTA is controversial. Baseline urine metal collections without chelation are more reliable for assessing current body burden. Chelation mobilization tests amplify existing levels but introduce variables that make interpretation difficult. I prefer baseline collections for screening and reserve challenge testing for cases where treatment decisions depend on confirming exposure history.

The biggest limitation is overtesting. Ordering five panels at once creates a wall of borderline results that confuses both practitioner and patient. I typically limit myself to three concurrent functional tests maximum. More than that produces diminishing returns and increases the chance of chasing artifacts rather than real pathology.
What Actually Works in the Long Run
The effective use of these evaluations comes down to a focused hypothesis driven by patient history. You order tests to answer specific questions, not to cast a wide net. A patient with chronic GI symptoms gets a stool test and a permeability marker, not a full endocrine and metabolic cascade. A patient with fatigue and cold intolerance gets a complete thyroid panel plus ferritin and B12, not an organic acid test as a first step. Documentation standards also matter if you want sustainable practice. Every test ordered should have a clear clinical rationale documented in the chart. Payors increasingly audit functional lab orders. Random screening without indication gets denied routinely. Linking each test to specific symptoms and suspected pathophysiology keeps denials down and improves claim acceptance rates. Follow-up testing should track intervention response, not just confirm baseline abnormalities. If you identify elevated homocysteine and start methylated B vitamins, retest in eight to twelve weeks to confirm the value moved. Repeating a test that never changed is wasted money. Repeating a test to verify improvement validates the intervention and keeps the patient engaged.