IV Fluids in Practice: What Actually Happens With Lactated Ringers
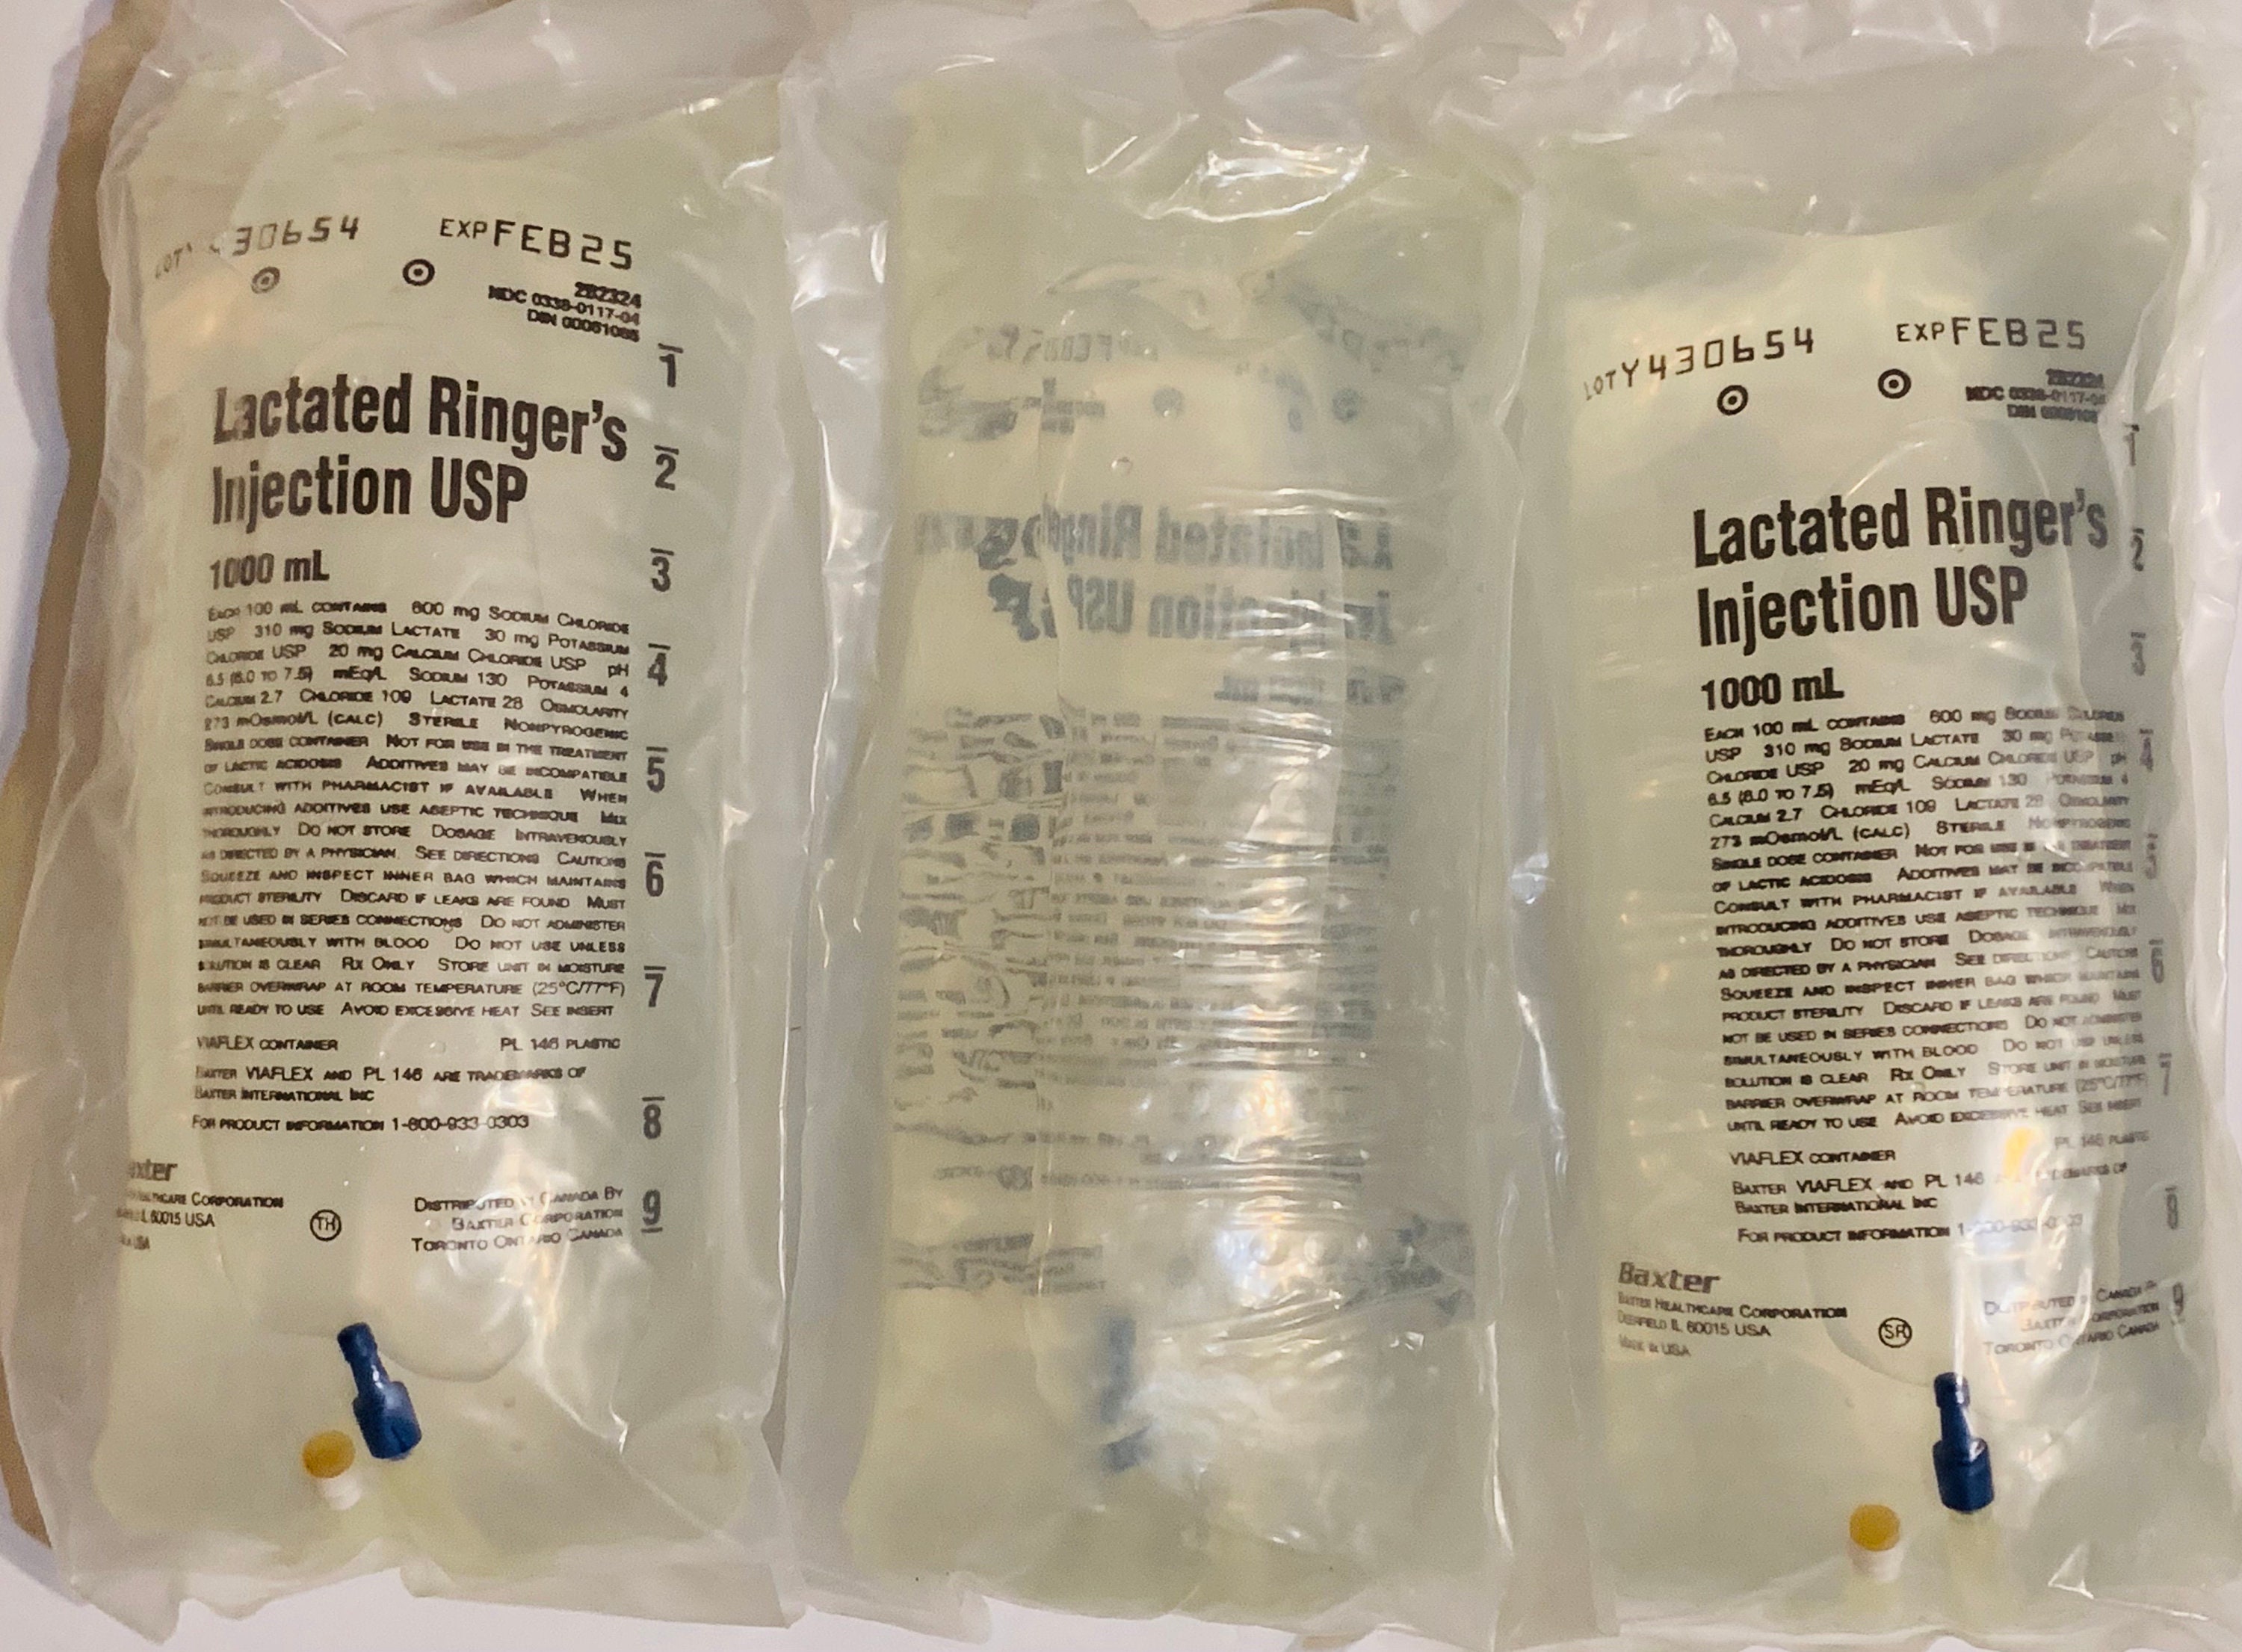
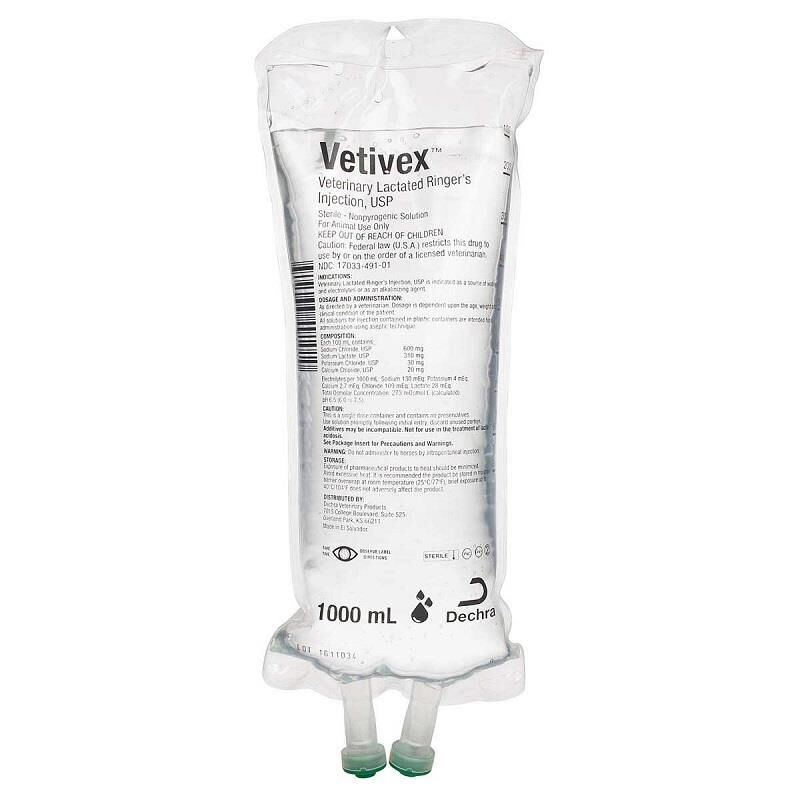
I spend more time dealing with IV complications than I do giving fluid therapy correctly in the first place. Most people reading this want to know whether Lactated Ringers Solution For Dogs is the right call, so let me cut to what matters. LR is a balanced crystalloid. That means its electrolyte composition roughly mirrors what you'd find in canine plasma, and the lactate acts as a buffer precursor. When the liver converts lactate to bicarbonate, it helps correct mild metabolic acidosis without dumping massive amounts of sodium or chloride into the patient. This makes it the go-to first-line fluid for most surgical cases and moderate dehydration scenarios. Not all cases, though. That distinction matters.
Lactated Ringers Solution For Dogs: What It Actually Does
The standard formulation contains approximately 130 mEq/L sodium, 109 mEq/L chloride, 4-5 mEq/L potassium, 3 mEq/L calcium, and 28 mEq/L lactate as sodium or potassium salt. It is isotonic at about 273-275 mOsm/L. For a 25 kg dog under anesthesia, a common maintenance plus deficit rate runs around 5-10 mL/kg/hr. That translates to roughly 125-250 mL/hr. You set the pump, you watch the patient, and you adjust based on blood pressure and capillary refill time. Here's what most guides don't tell you. Lactated Ringers doesn't stay in the intravascular space very long. Roughly 25-30% of the administered volume remains in the vasculature after an hour. The rest equilibrates into the interstitial space. If you're bolusing a hypotensive dog at 90 mL/kg over 15 minutes expecting sustained pressure support, you'll be reloading the IV bag twice. It works for initial resuscitation, but it's not a volume expander in the way synthetic colloids are. Crystalloids are cheap and generally safe. They just demand volume. I ran into a problem last year that still makes me double-check my assumptions. A senior Afghan Hound came in for an orthopedic procedure with chronic kidney disease and had been mildly dehydrated for days. Standard protocol suggested LR at 5 mL/kg/hr. About forty minutes into the case, the dog's blood pressure dropped and the lactate level on the point-of-care analyzer started climbing instead of falling. The kidneys weren't clearing the lactate fast enough, and the ongoing infusion was actually contributing to a mild lactic acidosis. I switched to Plasmalyte and the trend reversed within twenty minutes. This dog's tissue perfusion wasn't failing from hypovolemia. It was failing from impaired lactate metabolism mild renal compromise. LR was the wrong choice, and the numbers told the story if you were paying attention.
When LR Is the Right Call
Healthy or nearly healthy dogs undergoing routine surgery, minor trauma with moderate fluid loss, and post-operative hydration support are where LR shines. It's also reasonable for mild to moderate dehydration in dogs with normal hepatic and renal function. The potassium content is low enough that it won't cause hyperkalemia in most cases, and the calcium won't precipitate issues unless you're running blood products through the same line. Watch the calcium. That 3 mEq/L of calcium in LR will precipitate when mixed with blood products or certain medications. If you need to transfuse or co-administer drugs like amphotericin B or vancomycin, use a separate IV catheter or switch to a calcium-free crystalloid. Mixing LR and whole blood in the same line is one of those avoidable mistakes that shows up on incident reports.
Get the Full Details

Counter-Intuitive Things Nobody Warns You About
First, lactated Ringers is not "neutral" for acid-base status in every situation. In patients with severe hepatic insufficiency, the lactate cannot be efficiently converted to bicarbonate. You're essentially infusing a substance that accumulates rather than buffering. In these cases, Plasmalyte or Normosol-R is preferable because they use gluconate and acetate as buffer precursors, which have different metabolic pathways. The difference isn't dramatic in healthy patients, but it becomes clinically relevant when liver function is compromised. Second, the chloride content is higher than plasma. At 109 mEq/L, LR is slightly hyperchloremic relative to normal canine values of about 102-112 mEq/L. Prolonged large-volume resuscitation with LR can contribute to a non-anion gap metabolic acidosis from the chloride load alone. This is one reason why some critical care protocols favor balanced solutions like Plasmalyte for massive fluid therapy. For typical surgical cases, the effect is negligible. For a 40 kg dog losing blood and receiving three or four liters intra-operatively, it adds up.
Practical Setup and Administration
Set up the IV catheter in the cephalic or saphenous vein. Prime the tubing to eliminate air. Start with a crystalloid rate based on the patient's status. Dehydration correction uses a standard formula: fluid deficit in mL equals body weight in kg multiplied by the percentage dehydration multiplied by 1000. A 20 kg dog at 6% dehydration has a 1200 mL deficit. Replace half in the first four hours, the remainder over the next 20-24 hours, in addition to maintenance and ongoing losses. That's textbook. Real patients don't always follow the textbook. Monitor urine output if possible. A Foley catheter or intermittent bladder expression every few hours gives you real data. Less than 1 mL/kg/hr suggests under-perfusion. More than 5 mL/kg/hr while receiving aggressive fluids suggests you might be overdoing it. Heart rate, mucous membrane color, and capillary refill time are useful too, but they're subjective. Blood pressure is better if you have the equipment. Warm the fluid. Cold IV fluids drop core temperature and trigger shivering, which increases oxygen consumption and complicates anesthesia. A fluid warmer set to about 39°C makes a measurable difference in prolonged surgeries. I've seen normothermic patients become hypothermic during routine procedures simply because the bag was sitting at room temperature and the dog was open and anesthetized. This isn't dramatic. It's just physics, and it's completely preventable.
Limitations and Where LR Falls Apart
LR is not appropriate for dogs with hyperkalemia. The 4-5 mEq/L potassium is low, but it's not zero, and in a patient whose potassium is already elevated, any additional load matters. Renal failure with oliguria, severe hyperkalemia, and conditions requiring restricted sodium intake are scenarios where LR needs careful reconsideration. Some of these dogs do better with 0.9% sodium chloride alone or with a potassium-free balanced solution, depending on the specific electrolyte derangement. It's also not ideal for traumatic brain injury cases where you might want a hypertonic solution. LR is isotonic and won't reduce intracranial pressure. Hypertonic saline or mannitol serves that purpose. Using LR in a head-trauma patient isn't wrong per se, but it's not helping the problem you're trying to solve. There's no universal solution. Lactated Ringers is effective, widely available, and inexpensive. It works well for the majority of common scenarios. It fails predictably in specific conditions, and those conditions aren't always obvious until the numbers start moving in the wrong direction. Know when to switch fluids. That skill separates people who follow protocols from people who actually treat patients.