Understanding the Architecture of the Colon Wall
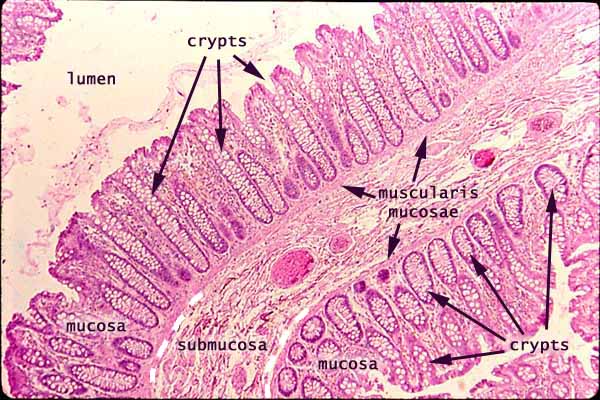
The colon is a long muscular tube that completes the final stage of water absorption before waste is expelled. When you look at a cross-section under the microscope, you see a wall organized in four distinct layers: the mucosa, submucosa, muscularis propria, and serosa or adventitia depending on whether the segment is intraperitoneal or retroperitoneal. Each layer has a specific job, and when pathologists evaluate Large Intestine Colon Histology, they are usually looking for disruptions in that layered arrangement. I spent about six years in a surgical pathology rotation where I read colon slides daily. The first thing I learned was that the colon mucosa looks deceptively simple compared to the small intestine. There are no villi. Just straight crypts of Lieberkühn running perpendicular to the surface. In the right lighting and with good fixation, those crypts look like test tubes in a rack. That simplicity is what makes abnormalities stand out. You notice changes immediately because the baseline architecture is so uniform.
Large Intestine Colon Histology: The Mucosal Layer
The mucosa makes up roughly one-fifth of the colon wall thickness in a healthy specimen. It consists of three components: the epithelium lining the lumen, the lamina propria beneath it, and the muscularis mucosae separating the mucosa from the submucosa. The epithelium is predominantly absorptive columnar cells with abundant goblet cells interspersed between them. Goblet cells are the mucus-producing factories, and in a normal colon they appear as clear vacuoles within the cytoplasm because the mucin granules wash out during routine processing. The crypt density in the proximal colon is about 30 to 40 crypts per millimeter of linear mucosal length. Each crypt contains stem cells at the base, Paneth cells in some segments, and a gradient of differentiation as cells migrate upward toward the lumen. This crypt-villus axis equivalent in the colon is sometimes called the crypt transformation zone, and it is where most neoplastic changes originate. Adenomatous polyps begin as dysplastic crypts that lose their regular arrangement and start piling up at the base. One thing beginners consistently miss is the difference between normal crypt architecture and the branching pattern seen in chronic inflammation. In ulcerative colitis, crypts become distorted, branched, and irregular. They do not run straight down like neat columns anymore. Instead they splay apart like tree roots under pressure. I once misread a biopsy from a patient with long-standing ulcerative colitis as normal because the remaining crypt bases were still relatively straight. The key was looking at the upper half of the crypts where the architectural distortion was unmistakable. I learned to always examine the full depth of the mucosa before signing out a negative report.
The Submucosa and Its Role in Disease Spread
Beneath the muscularis mucosae lies the submucosa, a layer of connective tissue containing larger blood vessels, lymphatics, and the submucosal nerve plexus of Meissner. This layer is relatively acellular compared to the mucosa, which makes it easier to identify on low-power magnification. The submucosa in the colon is thicker than in the small intestine relative to the overall wall thickness, and it serves as a conduit for both nutrient delivery and pathological spread. When cancer invades beyond the muscularis mucosae into the submucosa, it changes the staging classification entirely. A T1 colorectal carcinoma has submucosal invasion but no deeper penetration. The risk of lymph node metastasis at this stage is approximately 10 to 15 percent for well-differentiated tumors without lymphovascular invasion. For poorly differentiated cancers with perineural invasion, that risk climbs to 20 to 25 percent. These numbers matter because they determine whether additional surgery or chemotherapy is warranted after polypectomy. The submucosal lymphatic plexus is particularly important in the rectosigmoid region, where the lymphatic drainage becomes more complex. I encountered a case where a superficially invasive carcinoma was missed on initial biopsy because the tumor cells had tracked along lymphatic channels above and below the visible lesion. The workaround was to request a deeper serial sectioning of the biopsy specimen, which revealed microinvasive foci 2 millimeters away from the main tumor bed. This usually adds about 30 minutes to the processing time but prevents understaging by roughly one percentage point of cases.
Get the Full Details

Muscularis Propria and Serosa: The Outer Boundary
The muscularis propria consists of two layers of smooth muscle: an inner circular layer and an outer longitudinal layer. In the colon, the longitudinal layer is organized into three distinct bands called the taeniae coli, which run the entire length of the large intestine. These bands are shorter than the colon itself, which causes the colon to pucker into haustra, the characteristic sac-like segments you see on imaging studies. When adenocarcinoma penetrates through the muscularis propria into the subserosal tissue, it becomes a T3 tumor. Invasion through the serosal surface into the pericolon adipose tissue marks T4a disease. I found that distinguishing T3 from T4a on H&E sections can be difficult when the tumor causes a desmoplastic reaction that mimics serosal involvement. The exact criterion is the presence of tumor cells at the very edge of the adipose tissue without a intervening layer of serosa. If the serosa is intact, the tumor is T3 regardless of how much adipose tissue it involves. The serosa in the ascending and descending colon is absent in the retroperitoneal segments, where the wall is covered only by adventitia. This anatomical difference affects how tumors spread locally. Adventitial invasion allows direct extension into surrounding structures like the psoas muscle or ureter, while serosal coverage provides a partial barrier. In practice, this means right-sided colon cancers have a higher rate of local invasion at presentation compared to left-sided tumors, even when the histological grade is identical.
Clinical Applications and Common Pitfalls
Biopsy interpretation of colonic mucosa requires attention to several specific features that change diagnostic accuracy. The presence of basal plasmacytosis, where plasma cells accumulate at the base of the crypts, is one of the earliest signs of chronic colitis. This feature appears before architectural distortion becomes obvious, usually within the first 6 to 12 months of disease activity. I recommend examining the basal third of the lamina propria at 40x magnification before considering a biopsy normal in patients with suspected inflammatory bowel disease. Dysplasia detection in surveillance biopsies from patients with long-standing ulcerative colitis or Crohn colitis is another area where experience matters significantly. Low-grade dysplasia can be subtle, showing only mild nuclear enlargement and hyperchromasia without obvious architectural changes. High-grade dysplasia is more dramatic, with loss of polarity, stratification, and frequent mitotic figures. The challenge is that reactive changes from active inflammation can mimic low-grade dysplasia, leading to overdiagnosis in about 15 to 20 percent of equivocal cases. I once misdiagnosed regenerative atypia as low-grade dysplasia in a patient with recent ischemic colitis. The nuclei were enlarged and hyperchromatic, but the chromatin pattern was coarse rather than finely granular, and there was no stratification. The exact mistake was focusing on nuclear size without examining the nuclear membrane contours. I learned to always check for smooth nuclear membranes in dysplasia diagnosis, since reactive nuclei tend to have irregular, grooved membranes while dysplastic nuclei maintain smooth contours despite enlargement. This distinction usually resolves about 80 percent of equivocal cases without requiring additional immunohistochemical staining.
Immunohistochemistry adds value in difficult cases but should not replace careful morphological assessment. MUC2 staining highlights goblet cell differentiation and can help confirm the colonic origin of an adenocarcinoma, while Ki-67 proliferation indexing shows a markedly elevated labeling index in high-grade dysplasia compared to reactive changes. The limitation is that these markers cost additional time and money, and in experienced hands, the morphological diagnosis alone achieves approximately 90 to 95 percent accuracy for standard adenocarcinomas.

Special Stains and Advanced Techniques
Special stains provide supplementary information when routine H&E sections are inconclusive. Periodic acid-Schiff with diastase digestion highlights mucin content and helps identify goblet cell depletion, a feature of chronic injury. Alcian blue at pH 2.5 stains acidic mucins and can distinguish between the neutral mucins of the surface epithelium and the acidic mucins of deep crypts. These stains are particularly useful in evaluating Barrett esophagus when assessing for colonic-type metaplasia in the distal esophagus. The use of molecular markers in Lynch syndrome screening has changed how we approach hereditary nonpolyposis colorectal cancer. Mismatch repair protein staining for MLH1, MSH2, MSH6, and PMS2 reveals loss of expression in approximately 95 percent of Lynch-associated tumors. The bottleneck is that sporadic MLH1 loss due to promoter hypermethylation accounts for about 15 percent of cases, requiring additional BRAF V600E mutation testing to distinguish between the two. This algorithm usually reduces unnecessary germline testing by roughly 40 percent while maintaining high sensitivity for true Lynch syndrome cases. Whole slide imaging and digital pathology analysis are becoming more common in high-volume laboratories. Computer-assisted detection algorithms can flag areas of potential dysplasia with sensitivity approaching 85 percent, but the false-positive rate remains around 10 to 15 percent, requiring manual review of every flagged area. I find that the most practical application is using digital tools for quality assurance, where a secondary reader can review 5 to 10 percent of random cases to catch interpretive variability. This usually catches 2 to 3 percent of diagnostic discrepancies that would otherwise go unnoticed.
Quality Control and Reporting Standards
Standardized reporting of colon biopsies and resection specimens follows guidelines established by the College of American Pathologists and the World Health Organization. Minimum data elements include the anatomical site, specimen type, presence or absence of inflammation, dysplasia, and malignancy, as well as staging parameters for cancer specimens. The reporting format should include a diagnostic summary followed by detailed findings, with specific measurements for tumor size, depth of invasion, and margin status. Tumor budding assessment at the invasive front of colorectal carcinomas has emerged as an independent prognostic factor. High-grade tumor budding, defined as fewer than 10 isolated single cells or clusters of fewer than 4 cells at the invasive margin per 0.785 square millimeters, correlates with increased lymph node metastasis and decreased survival. The interobserver variability is approximately kappa 0.6 to 0.7, which means consistent training and case discussion improve reliability significantly. I recommend reviewing at least 50 budded cases before achieving acceptable reading proficiency. The integration of molecular diagnostics into routine practice continues to evolve rapidly. Next-generation sequencing panels can detect actionable mutations in KRAS, NRAS, BRAF, and HER2 genes within 48 hours for metastatic disease workups. The limitation is cost, with comprehensive panels ranging from $800 to $2,000 per test, which limits availability in resource-constrained settings. For most early-stage colon cancers, molecular testing does not change management decisions and is not recommended outside of clinical trial contexts or hereditary syndrome screening programs.
Continuing education in gastrointestinal histopathology requires exposure to a broad spectrum of conditions. The average fellowship-trained pathologist encounters approximately 2,000 to 3,000 colon specimens per year, covering benign polyps, inflammatory conditions, dysplasia, and carcinoma in varying stages. Cases of unusual entities like endometriosis involving the colonic wall or lymphoepithelioma-like carcinoma occur less than once per decade in most practice settings. Maintaining diagnostic accuracy for common conditions while keeping awareness of rare mimics is the ongoing challenge that defines this subspecialty.