How to Use Laser Therapy For Nerve Pain: What Actually Works
Laser therapy for nerve pain is one of those treatments that gets oversold and undersold in equal measure. It works, but not the way a lot of people expect it to work. The basic mechanism involves delivering low-level laser light—typically in the 600 to 1000 nanometer range—to targeted areas where damaged nerves are causing chronic pain. The light penetrates the tissue, gets absorbed by the mitochondria in your cells, and stimulates ATP production. That cellular energy boost helps reduce inflammation and accelerates repair of the damaged nerve endings. Most protocols use between 300 and 500 milliwatts of power, delivered at dosages around 4 to 6 joules per point. I ran into a case recently where a patient with postherpetic neuralgia from shingles wasn't responding to anything we threw at her—gabapentin, lidocaine patches, even a nerve block. We ended up using a high-powered laser at 808 nanometers, running it directly along the dermatome where the pain was concentrated. The key was actually hitting the nerve itself, not just the skin surface. A lot of clinicians miss that. They're treating the skin when the problem is deeper. We got significant relief after about six sessions over three weeks, and she stayed manageable off the gabapentin for a few months after. That said, this isn't a cure. It's management. And it doesn't work for every type of neuropathic pain.
Laser Therapy For Nerve Pain: Setting Up a Treatment Protocol
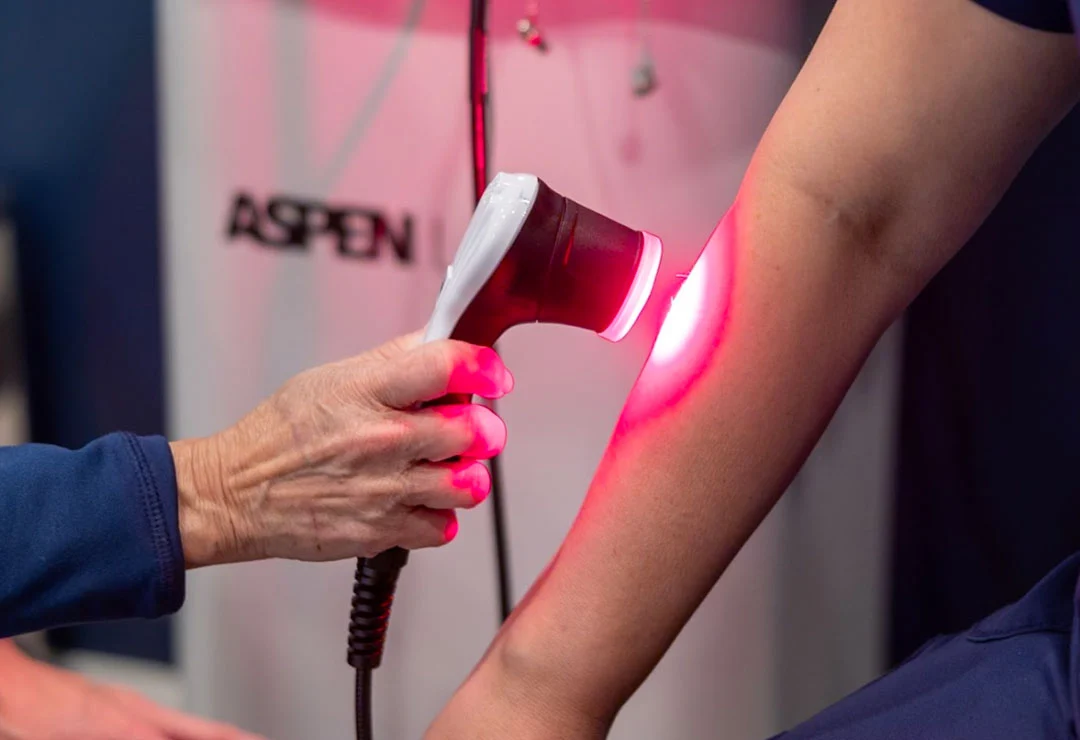
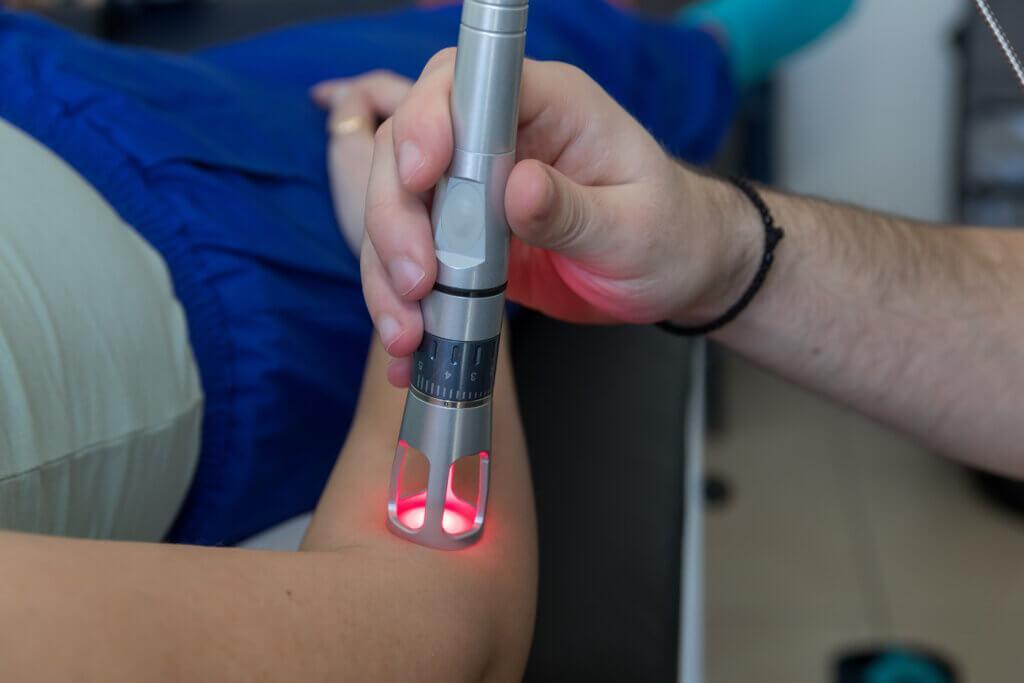
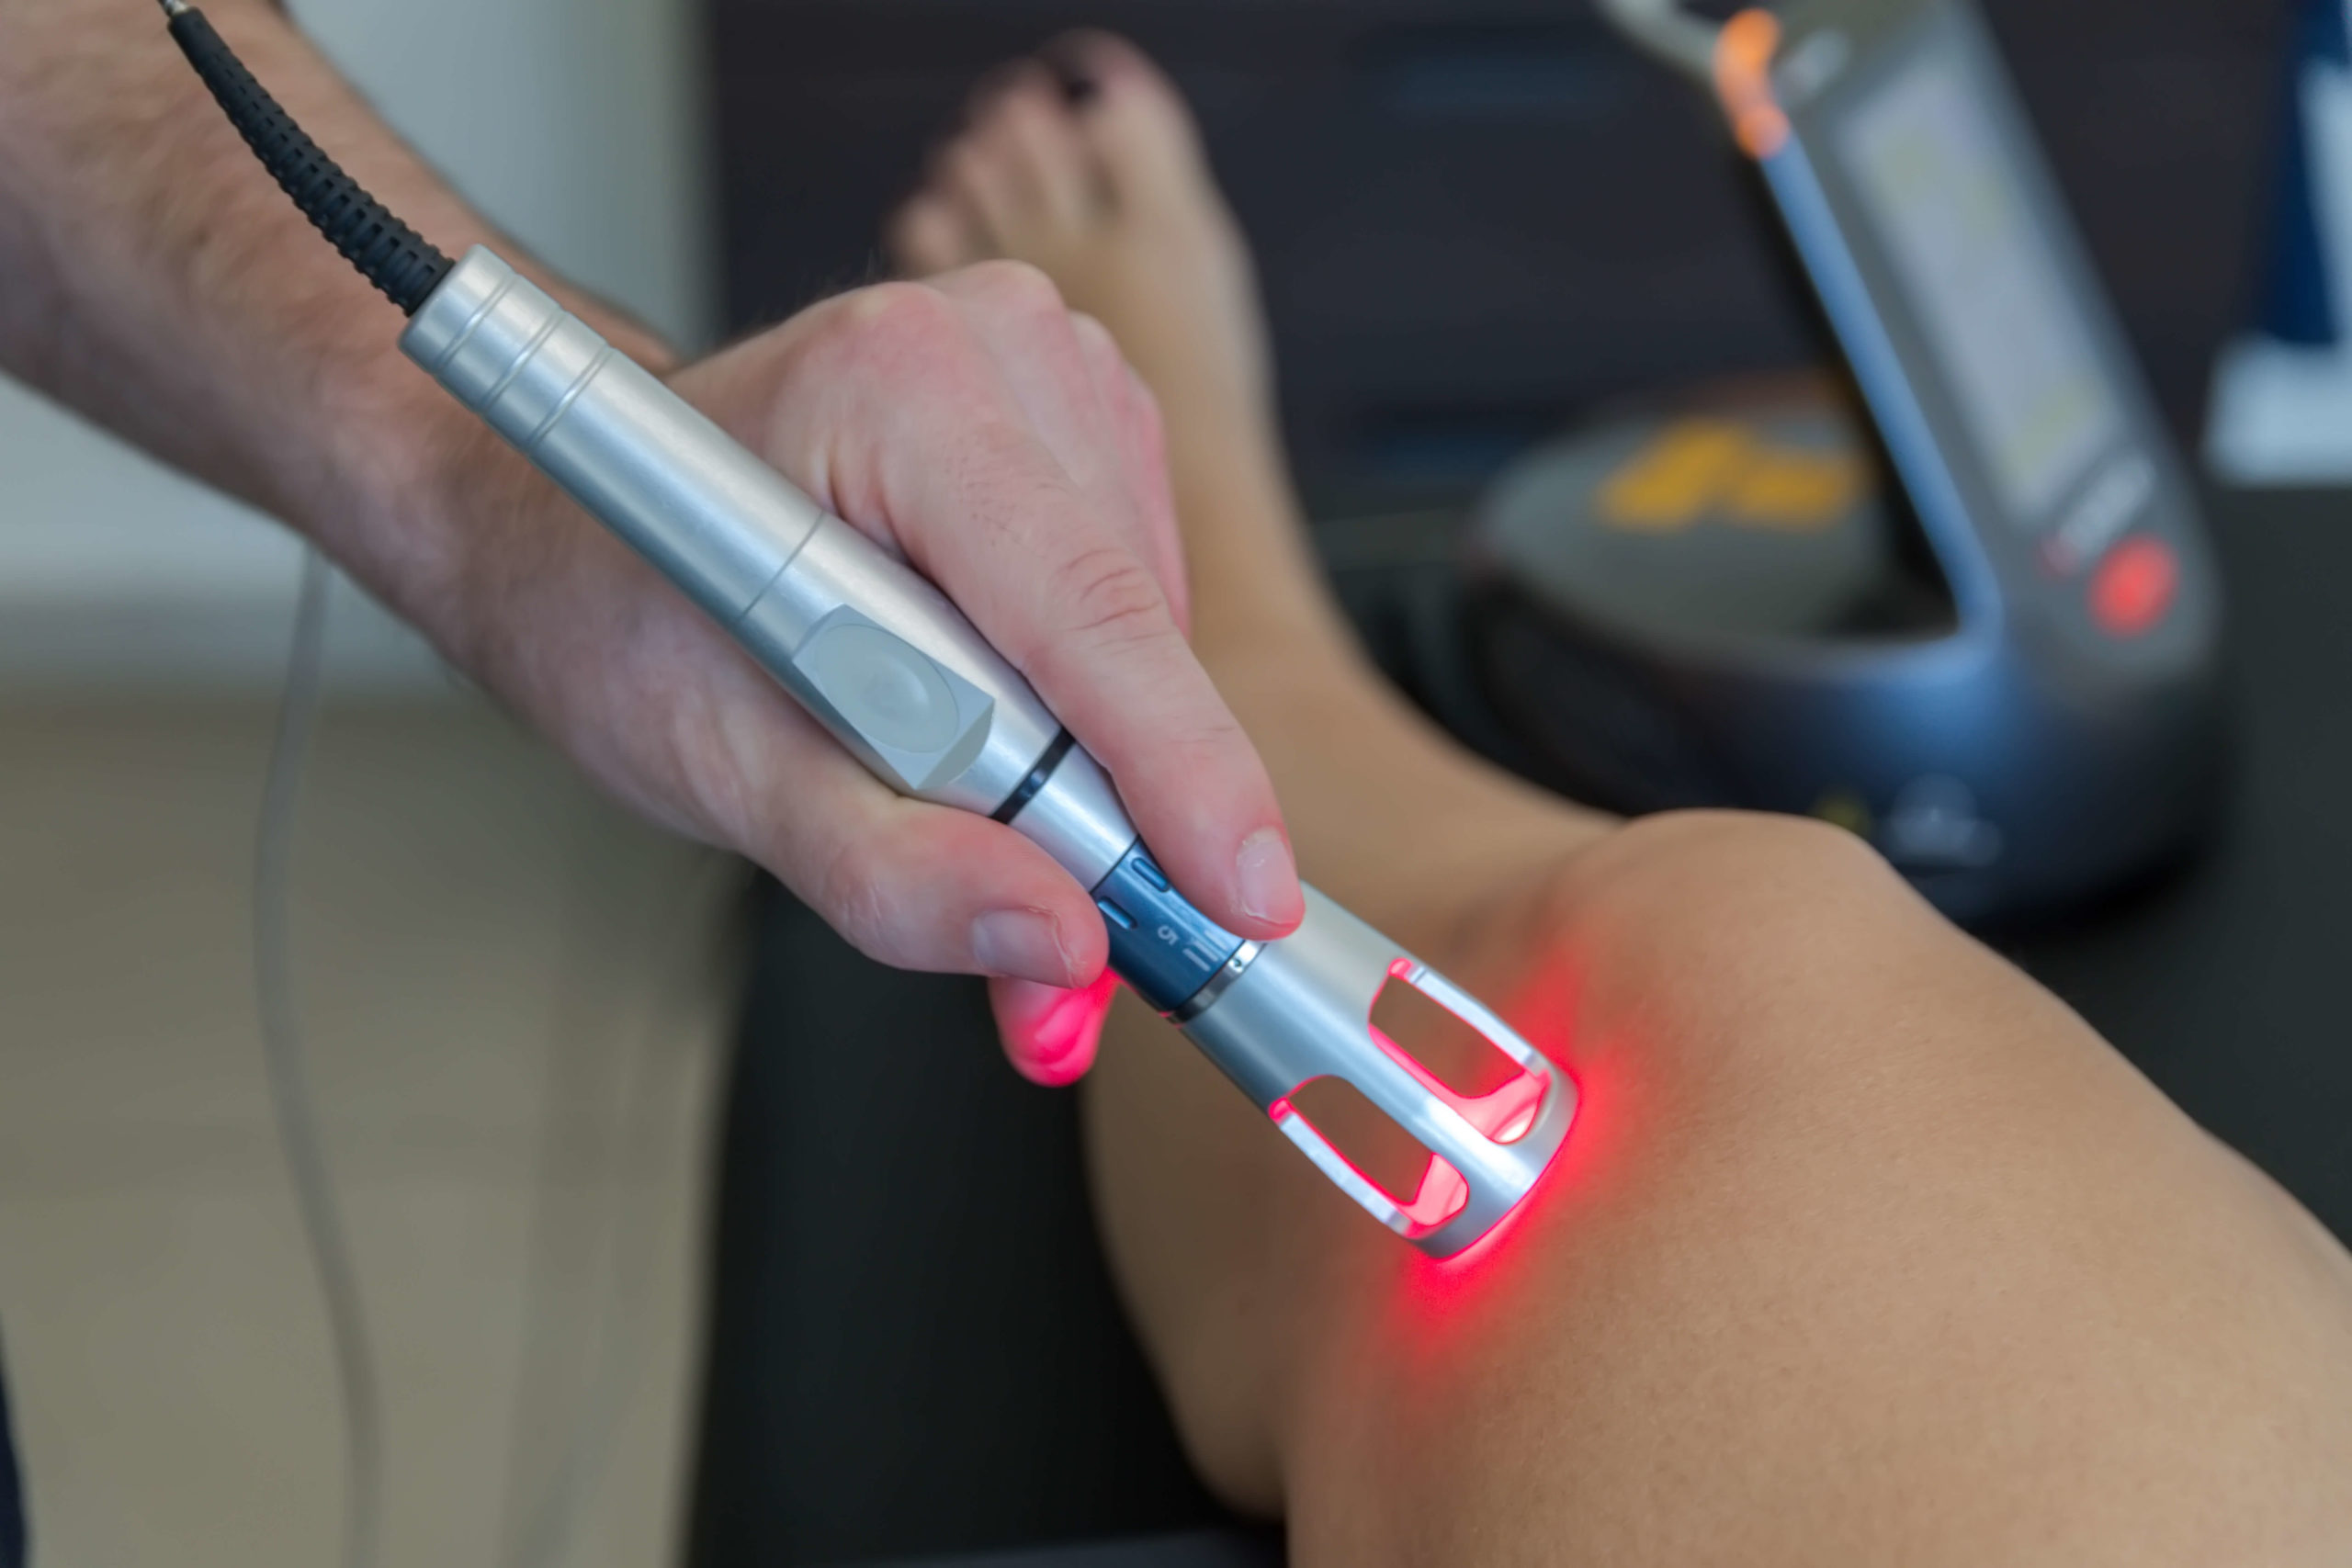
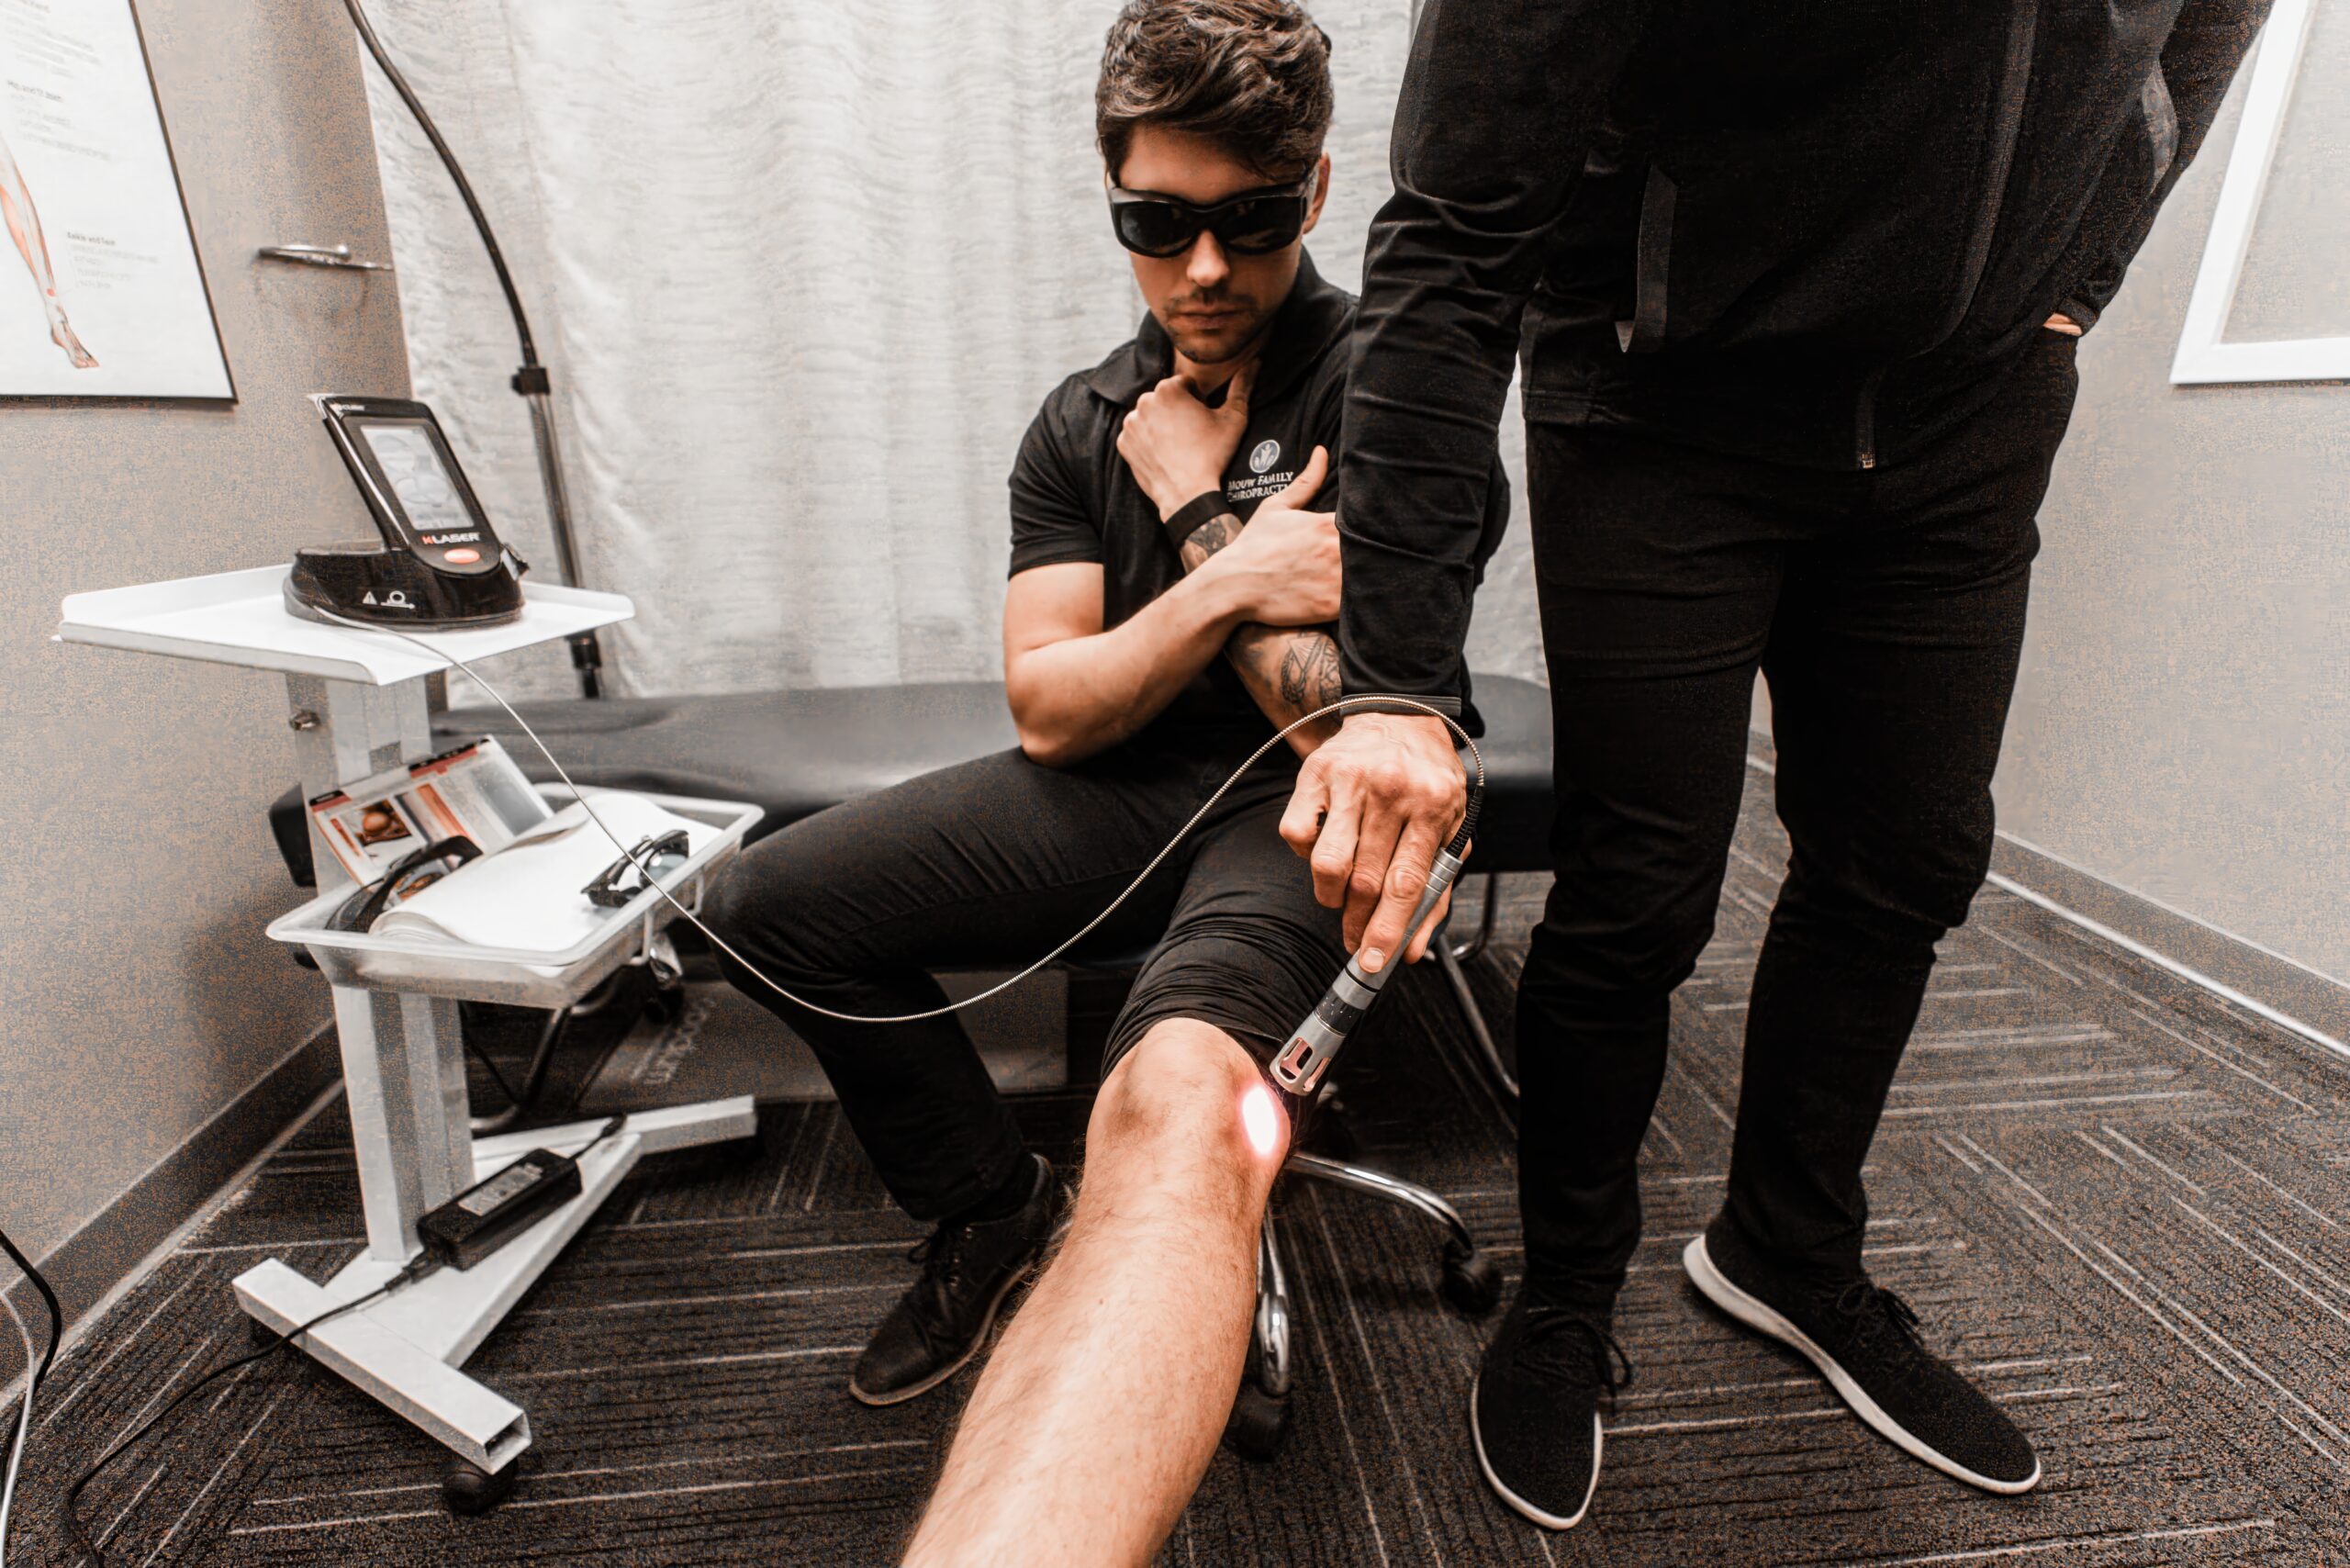
If you're trying this yourself or running a clinic, here's what a standard protocol looks like. Start by identifying the painful area. For peripheral neuropathy in the feet, that usually means treating along the path of the affected nerve—from the ankle up toward the knee or lower back depending on where the compression or damage is originating. Clean the skin, make sure it's free of lotions and creams, then position the laser wand perpendicular to the skin surface. Press it gently against the skin at each point and hold for 30 to 60 seconds per point. Move in a grid pattern covering the entire area. Treat two or three times per week for four to six weeks, then reassess. The wavelength matters significantly. 808 nanometers is the gold standard for deeper nerve penetration. 660 nanometers works better for surface-level issues and skin conditions. A lot of cheap home-use devices cram both wavelengths into a small handheld unit, but the power output is so low—usually under 50 milliwatts—that they barely do anything past the epidermis. If you're serious about this, get a device that can actually deliver 300 milliwatts or more at 808 nanometers. The difference is not subtle. One thing I learned the hard way: nerve pain patients often have reduced sensation in the affected area. That means they can't tell you if the laser is getting too hot. I had a diabetic neuropathy patient develop a mild burn on his shin because he couldn't feel the heat buildup. Now I always keep my fingers on the treatment area next to the laser head to monitor temperature. It takes an extra second and honestly it's such a minor thing I should have caught it earlier.
The real limitation of this approach is that it's a band-aid on a structural problem. If someone has a compressed nerve from a herniated disc or carpal tunnel, laser therapy might reduce the inflammation enough to ease symptoms, but it won't fix the compression. You need to address the root cause. Surgery, physical therapy, posture correction, whatever applies. Laser is adjunctive, not standalone. I've seen too many people get six sessions, feel a little better, and then stop. The effects are temporary unless you're also dealing with what's causing the nerve damage in the first place. There are also contraindications you need to watch. Don't use laser therapy over malignant tumors. Avoid the thyroid gland and the eyes. Pregnant women should steer clear of treatment over the abdomen and lower back. And if someone is on photosensitizing medications—certain antibiotics, retinoids, even some herbal supplements—their skin can react badly to the light. A quick medication review before you start is honestly the most important step in the whole process. For mild to moderate peripheral neuropathy—diabetic neuropathy, chemotherapy-induced neuropathy—laser therapy shows the most consistent results. Studies typically report a 30 to 50 percent reduction in pain scores after a full course of treatment. That's meaningful but it's not elimination of pain. For radiculopathy or entrapment neuropathies, the data is thinner and the outcomes are more variable. You're better off combining laser with decompression strategies and seeing a specialist who can actually diagnose the mechanical issue.
Get the Full Details