Why Your Lateral Chest X-Ray Reads Are Probably Missing the Small Stuff
I spend most of my day looking at lateral chest radiographs, and the honest truth is that most of the important findings hide in places people don't check first. The posteroanterior view gets all the attention because it's easier to grab and faster to read. But laterals tell you something different, and they show it in ways the frontal film never will. A lateral chest x-ray labeled properly starts with correct patient positioning. Feet shoulder-width apart, hands on hips or clasped overhead depending on the protocol, and the patient rotated so the midsagittal plane is parallel to the detector. If that alignment is off by even a couple centimeters, everything past that point becomes an exercise in guessing. I've seen reports describe suspicious opacities that turned out to be artifacts from poor scapular retraction. It happens more often than you'd think.
Lateral Chest X Ray Labeled: What the Annotations Actually Mean
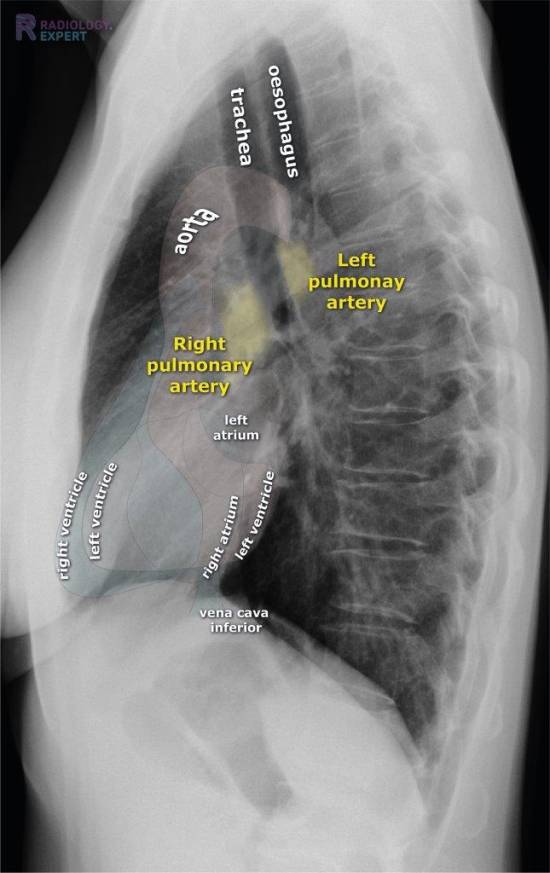
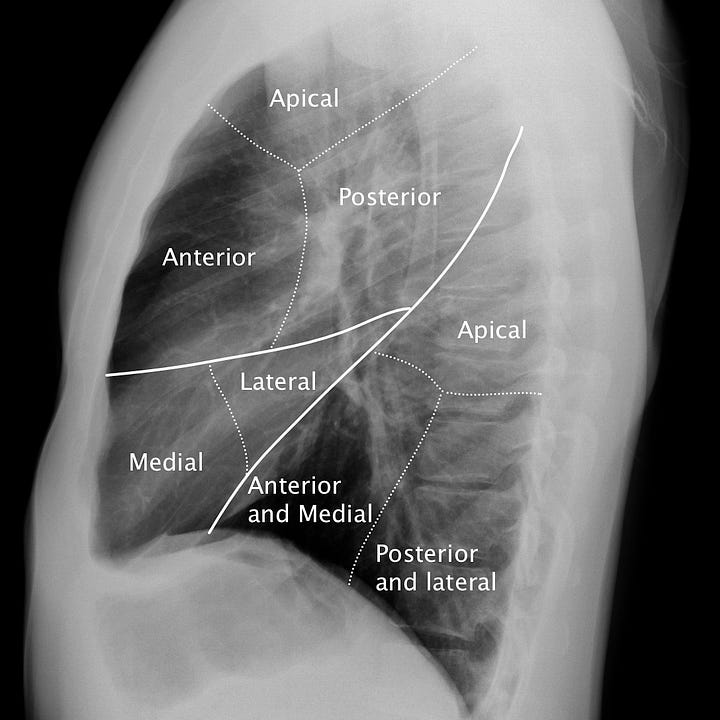
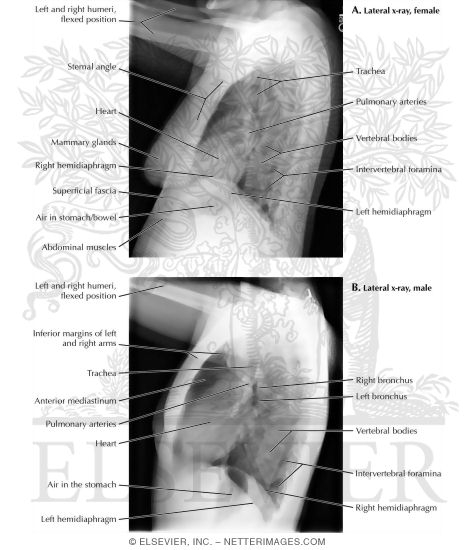
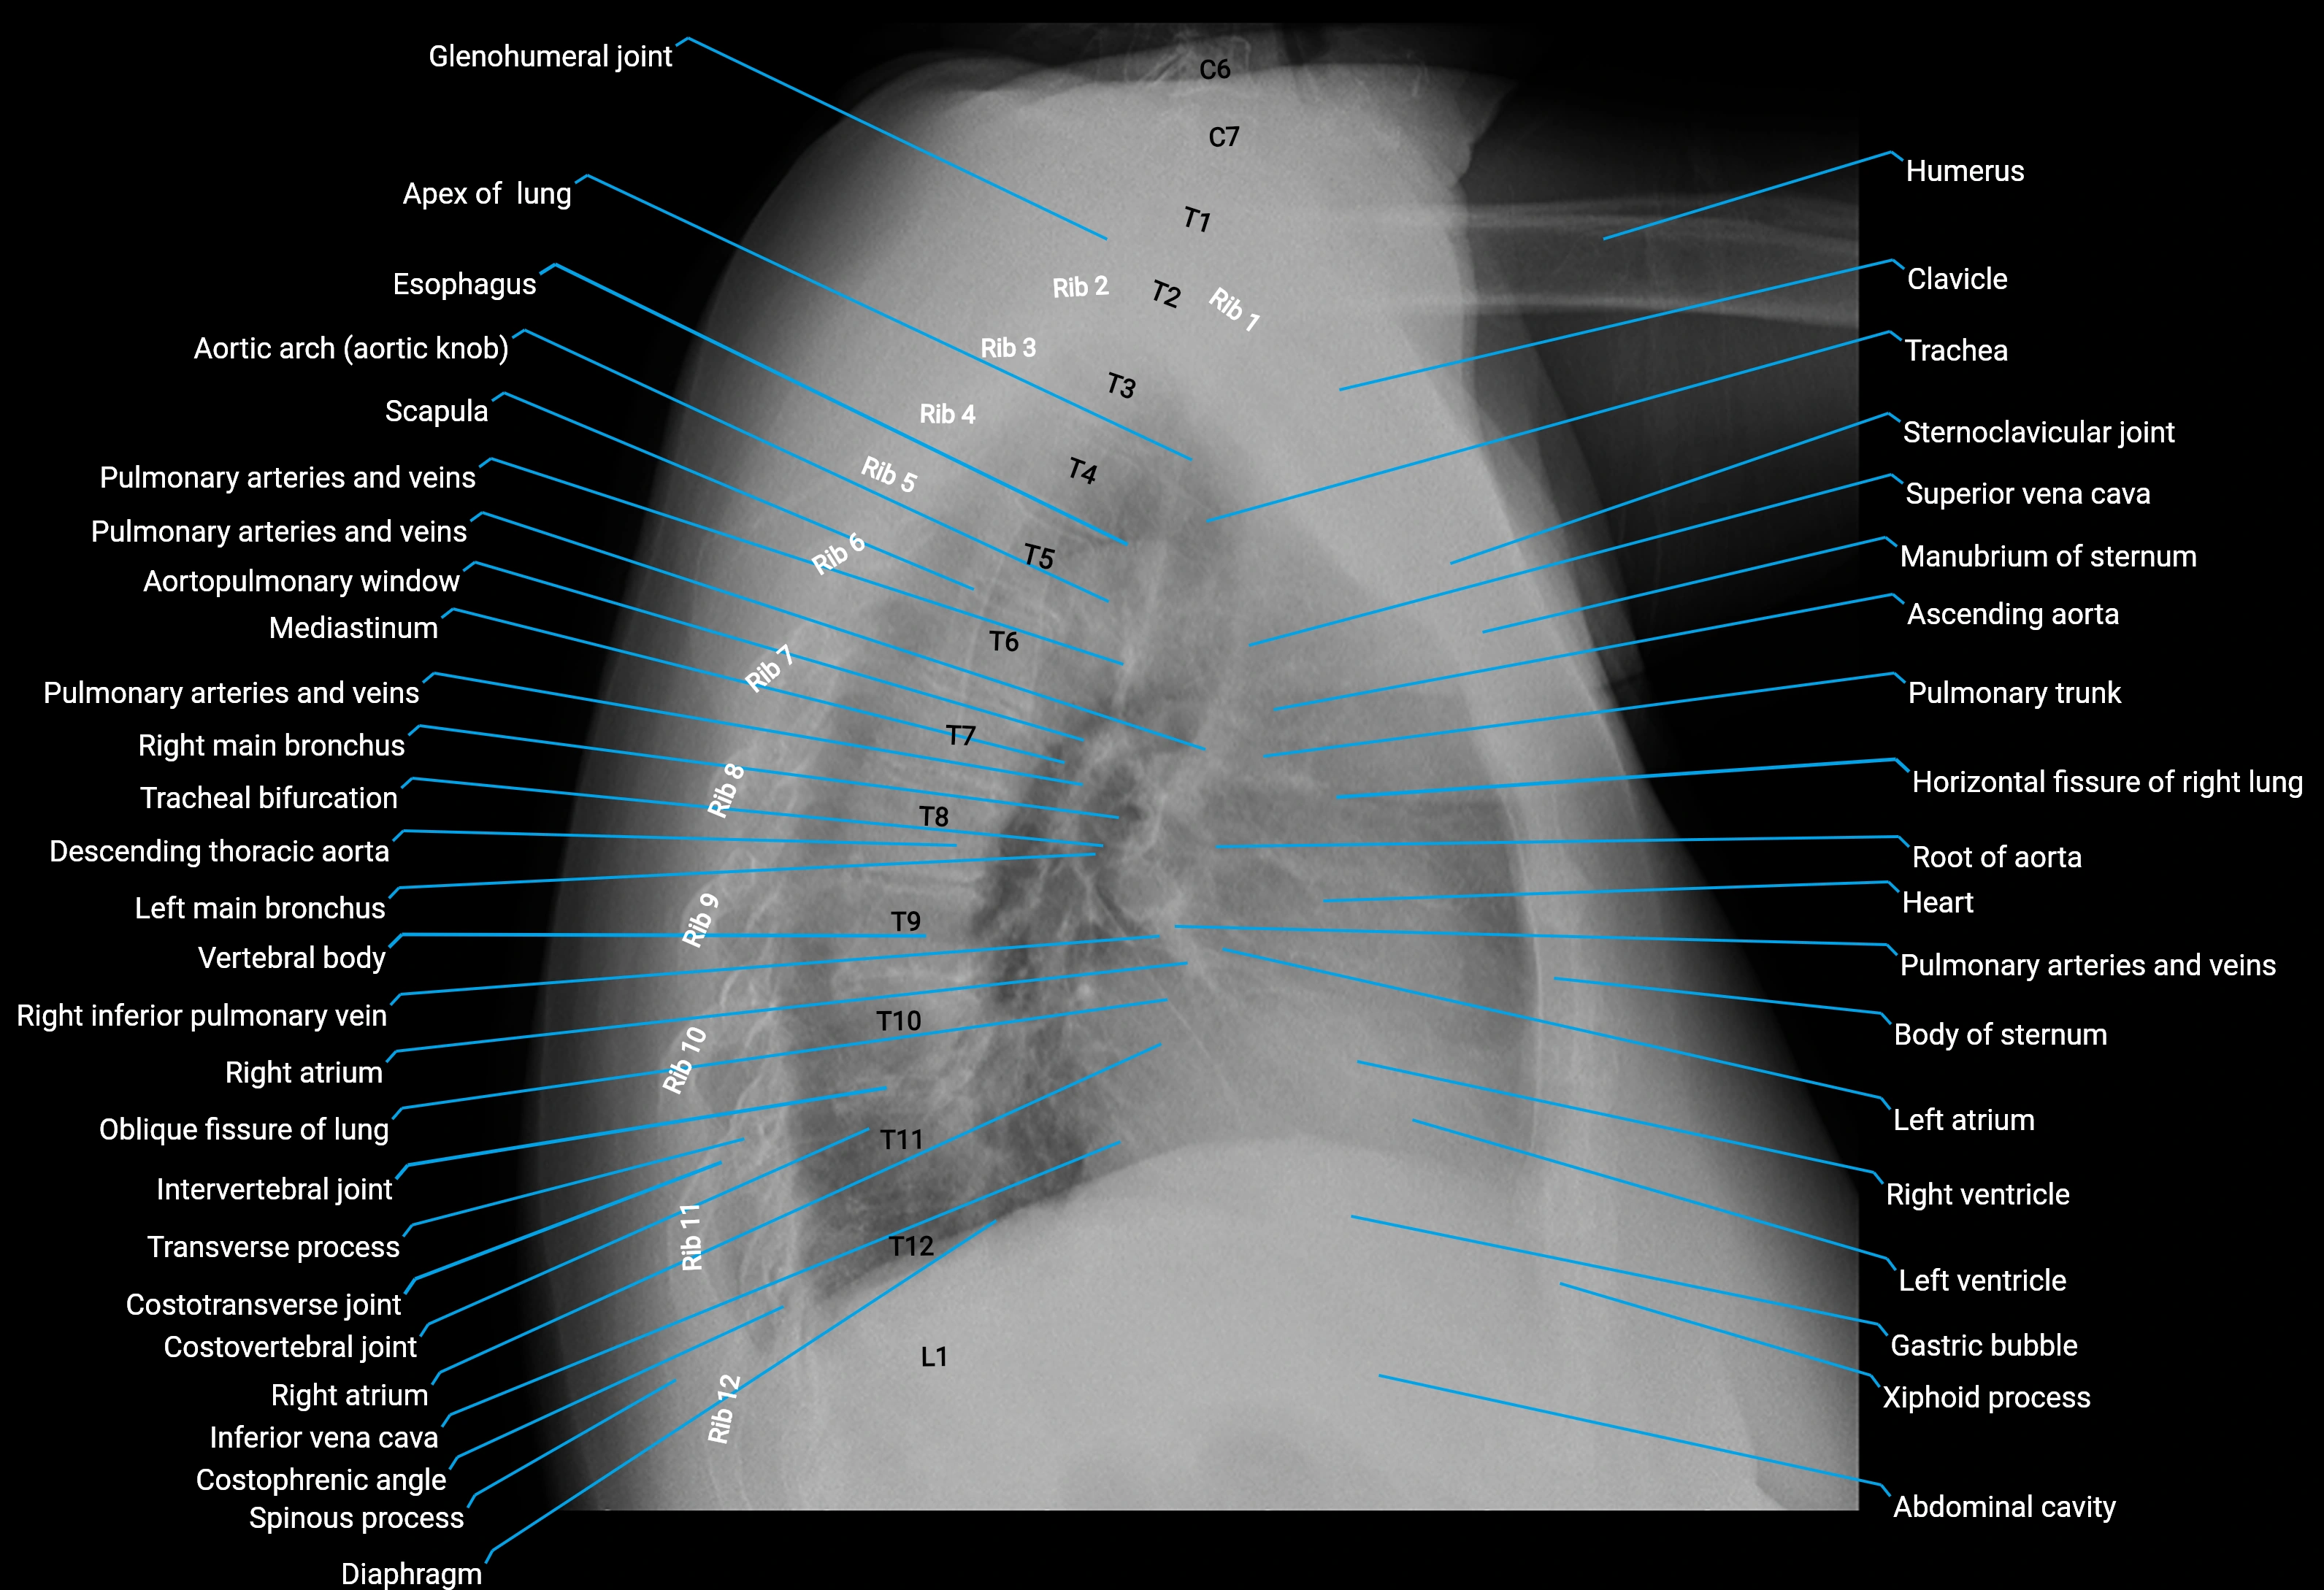
When someone posts a lateral chest x-ray labeled online, they're usually highlighting anatomical landmarks or pathological findings. The standard labels include the retrosternal space, the retrocardiac space, the hemidiaphragms, the posterior costophrenic angles, and the thoracic spine. Each of these has a normal appearance, and each can tell you something specific when it looks wrong. The retrosternal clear space behind the sternum should be mostly lucent. When it fills in, especially in the upper zones, you're often looking at anterior mediastinal pathology. A thymoma, lymphadenopathy, or a large mass pushes into that space first because there's nowhere else for it to go in a lateral projection. The retrocardiac space below the heart shadow is where small pleural effusions hide before they show up anywhere else. I had a patient last year whose frontal film looked completely normal and it was only on the lateral that I caught a tiny meniscus along the posterior diaphragm. By the time it was visible on the PA, they needed drainage. Labels on educational images usually point to the major fissures, the aortic knob silhouette, the tracheal air column, and the vertebral bodies. Getting comfortable with what normal looks like here matters more than memorizing abnormal patterns. You can't spot an abnormality in the spine if you don't know whether a particular vertebra should be casting that shadow.
Reading the Posterior Costophrenic Sulcus
This is probably the single most important area on a lateral film and the one most commonly rushed through. The posterior costophrenic angle should form a sharp, deep recess where the diaphragm meets the posterior chest wall. Any blunting here, even minimal, suggests fluid. The amount of fluid visible on a lateral can be as little as fifty milliliters. On a PA film you're looking at two hundred to three hundred milliliters before you see anything definitive. I learned this the hard way during a residency call night. A trauma patient came in with a normal frontal chest x-ray after a fall. The attending asked for a lateral on a hunch. There it was, a tiny but definite blunting of the posterior costophrenic angle. We watched him for twenty-four hours and he developed a hemothorax large enough to require a tube. That lateral saved him from a delayed presentation.
Get the Full Details
Spine Sign and Density Changes
The thoracic spine on a lateral film should get progressively darker as you move downward through the lung fields. This is because the lower lung has more air and less tissue between the x-ray source and the detector. If the vertebrae get whiter instead of darker as you go down, that's the spine sign, and it indicates pathology in the lower lobes. Consolidation, atelectasis, or a mass in the inferior segment of the right lower lobe will make the lower spine abnormally opaque. Here's something most people don't realize: the spine sign can be subtle in obese patients or those with chronic obstructive pulmonary disease. The baseline lung density is already higher, so a superimposed consolidation doesn't change the picture nearly as much. In those cases you have to compare side to side and look for other clues like fissure displacement or vascular crowding.
Common Pitfalls and Where This Method Falls Apart
Lateral chest x-rays are not a universal solution. If the patient can't stand upright, the diagnostic value drops significantly. A supine lateral is practically useless for detecting pleural fluid because the fluid layers out along the entire posterior chest wall instead of collecting in the costophrenic angle. You'll just see a diffuse increase in density without any sharp landmarks to guide you. In those situations, a decubitus view or a CT scan does more good than another x-ray. Poor inspiration is another major problem. When the patient doesn't take a full breath, the diaphragm sits high, the lung volumes are reduced, and structures overlap in ways that create false impressions. I've seen overlying bowel gas patterns misread as parenchymal disease simply because the patient couldn't hold their breath long enough. The workaround is straightforward: retake the film with better coaching, but if the patient genuinely cannot cooperate, move on to cross-sectional imaging rather than forcing a diagnosis off a suboptimal study. Another limitation that isn't talked about enough is the effect of breast tissue in women. Depending on breast size and positioning, the anterior chest on a lateral can be completely obscured. Small nodules in the anterior segment of the upper lobes simply disappear behind soft tissue density. This is one reason why dedicated CT protocols exist for lung cancer screening rather than relying on x-ray alone.
Practical Tips for Better Image Quality
If you're the one acquiring these images or reviewing them, the exposure settings matter more than most people admit. A lateral chest x-ray needs slightly higher kVp than a PA film to penetrate through the thicker part of the torso near the spine. Most modern machines handle this automatically, but old film-based protocols sometimes produced underpenetrated laterals where the vertebral bodies were completely white and unreadable. Make sure the patient's arms are raised enough to clear the lung fields. I've spent too much time trying to interpret lung bases with arm shadows draped across them. And check that the collimation is tight. A poorly collimated lateral includes unnecessary anatomy that adds scatter and reduces contrast, making subtle findings even harder to see. When you're looking at a lateral chest x-ray labeled for teaching purposes, pay attention to which structures are highlighted. The labels themselves are data. They tell you what the author found noteworthy, and that's worth analyzing independently rather than just accepting at face value. Cross-reference the labeled areas against your own reading before moving on. It's how I caught my first posterior mediastinal mass, and it's still how I catch things now.

There's no substitute for building up a mental library of normal variants. A prominent left atrial appendage, a tortuous descending aorta, a hyperinflated lung pushing the diaphragm flat — these are all normal findings that look alarming if you haven't seen them before. The labeled images you find online are useful for this exactly because they show the range of acceptable anatomy, not just textbook disease patterns.