
Understanding The Structure You Actually Need To Know
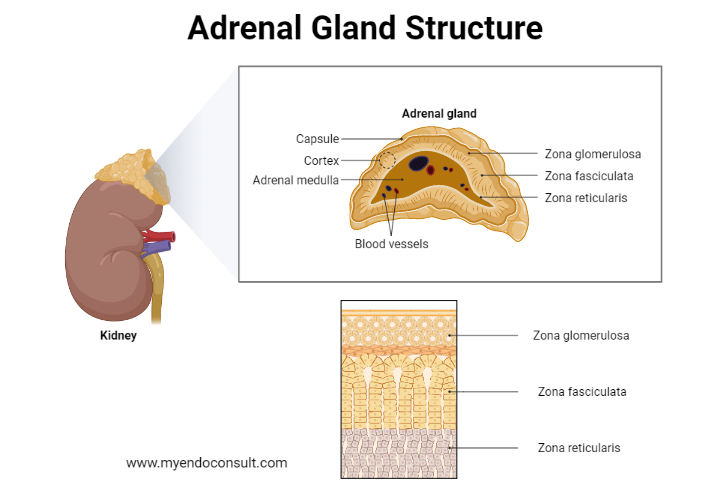
The adrenal gland sits on top of each kidney and has three distinct layers, each producing different hormones. Most textbooks list them from outside to inside: zona glomerulosa, zona fasciculata, and zona reticularis, plus the medulla at the core. That's correct but incomplete for anyone who has actually worked with adrenal tissue. I spent years in a surgical pathology lab reading cross-sections of adrenalectomy specimens. The clean textbook diagram looks nothing like what you see on a real slide. The layers are often distorted, the boundaries blur, and pathological changes can make identification nearly impossible without knowing what to look for.
Layers Of The Adrenal Gland In Practice
The outermost layer is the capsule, a thin connective tissue shell. Under that is the zona glomerulosa. It's a relatively narrow band of cells arranged in small clusters or arcs. Its main job is producing aldosterone, a mineralocorticoid that regulates sodium and potassium balance. In a healthy adult gland, this layer might be only one to two cells thick in cross-section, which makes it easy to miss if you're not looking carefully. Beneath the glomerulosa is the zona fasciculata, and this is by far the thickest layer. It makes up most of the cortex and consists of columns of cells packed with lipid droplets, which is why it appears pale or foamy under standard H&E staining. These cells produce cortisol and small amounts of androgens. When someone has Cushing's syndrome or is on long-term glucocorticoid therapy, this is the layer that hypertrophies or atrophies depending on the direction of the problem. I once reviewed a specimen from a patient on high-dose prednisone for rheumatoid arthritis, and the fasciculata was virtually absent. The gland looked shrunken and pale, almost entirely replaced by the other two layers and the medulla. The zona reticularis sits just inside the fasciculata, forming a network-like pattern of cells. It produces primarily androgens like DHEA and DHEA-sulfate. This layer is thinner than the fasciculata and its cells contain more lipofuscin pigment, giving it a slightly darker appearance microscopically. It's also the layer most commonly involved in adrenal incidentalomas found on CT scans, which is worth noting if you're reading imaging reports.
At the center is the adrenal medulla. It's not part of the cortex at all, embryologically speaking. It derives from neural crest cells, which is why it responds differently to stress and produces catecholamines instead of steroid hormones. The medulla contains chromaffin cells that release epinephrine and norepinephrine directly into the bloodstream. On a standard stain, these cells look quite different from cortical cells, with a more granular cytoplasm. Here's something most people miss: the blood supply creates a functional connection between these layers that isn't obvious from a static diagram. Cortical blood enters through the capsule, percolates down through the cortex in sinusoidal vessels, and then drains into the medullary vasculature before exiting through central veins. This means cortisol-rich blood from the cortex actually bathes the medulla, and this high cortisol concentration is necessary for the enzyme that converts norepinephrine to epinephrine to work properly. If the cortical blood supply is compromised, the medulla doesn't just lose its own blood flow. It loses the hormonal signal it needs for normal function. When you're identifying these layers on a histology slide, the most common mistake I see is confusing the outer zona glomerulosa with the capsule itself. The glomerulosa cells are smaller and more densely packed than fasciculata cells, but they can look almost indistinguishable from the connective tissue capsule if the section is thin or the staining isn't clean. My workaround was always to locate the characteristic arched arrangement of glomerulosa cells and then trace them back toward the capsule rather than trying to identify the capsule first and working inward. It takes more time initially but saves you from mislabeling structures later.
Get the Full Details
Another practical issue: in adrenal nodules and adenomas, the normal layered architecture is usually obliterated. A typical cortical adenoma will show fasciculata-like cells throughout with no clear zonation. Pathologists sometimes try to force the layers back into the description because the textbook says they should be there, but they aren't. The nodule replaces the normal structure. If you're studying this for an exam, remember that loss of zonation is itself a diagnostic finding, not a preparation artifact. The layers also respond differently to ACTH stimulation. The fasciculata and reticularis are highly ACTH-dependent, so they atrophy quickly when exogenous cortisol suppresses pituitary ACTH production. The glomerulosa, however, is primarily regulated by the renin-angiotensin system and potassium levels, not ACTH. This is why patients on chronic steroids don't typically develop the same degree of glomerulosa atrophy as they do in the deeper layers. It's a useful distinction when interpreting hormonal panels alongside imaging findings. One edge case that cost me two hours once: I was reviewing a pediatric adrenal specimen where the zona glomerulosa appeared disproportionately thick, almost mimicking a hyperplastic process. Turned out the child had congenital adrenal hyperplasia due to 11-beta-hydroxylase deficiency, and the backup of precursors caused unusual hypertrophy patterns across multiple zones simultaneously. The standard "thick fasciculata equals Cushing's" rule doesn't apply here. If you're looking at a young patient's gland and the layering seems off, consider whether an enzymatic block might be reshaping the whole cortex rather than a single layer responding in isolation.


