I spent seven years managing a caseload that kept growing while the staffing numbers stayed flat. The job wasn't about being the loudest person in the room. It was about knowing when to push a referral, when to back off, and when to admit the treatment plan wasn't working. Leadership in occupational therapy looks different on paper than it does on a Monday morning when three clients need adaptive equipment and your supply order got delayed.
What Leadership In Occupational Therapy Actually Means
It's not a title. It's the set of decisions you make when no one is watching. The American Occupational Therapy Association frames it around scope of practice, clinical reasoning, and advocacy, but the day-to-day version involves negotiating with physicians who think OT is just massage, documenting outcomes that justify continued authorization, and mentoring new grads who still believe the textbook scenarios match real patients.
The core function is clinical judgment amplified by administrative responsibility. You're accountable for outcomes you don't personally deliver, which means your leadership shows up in how you structure evaluations, delegate tasks, and handle documentation audits.
Setting Up a System That Actually Works
I learned this the hard way. Year two, I took over a unit where everyone documented differently. Two therapists used SOAP notes. One used DAP. The third wrote paragraphs that read like novel excerpts. The auditor flagged us within three months. Here's what I did:
I created a single template that satisfied Medicare criteria and our internal quality metrics. It had required fields for functional baseline, intervention type, and discharge status. Nobody could submit a note without filling those three sections. The template took about ten minutes to learn. Documentation compliance went from 62 percent to 94 percent in six weeks.
The trick wasn't the template. It was enforcing it consistently. I stopped accepting notes that didn't meet the standard, even from senior staff. That created friction for about three weeks. Then it became the norm.
For leadership in occupational therapy to work, you need standardized processes that survive turnover. When your lead therapist quits in November, the new hire shouldn't need a week to figure out how you document referrals.
Handling the Edge Cases You'll Face
The textbook says advocate for your clients. It doesn't mention the specific scenario where a physician writes "OT for strengthening" but the patient can't walk to the bathroom without assistance. I had this exact case with a post-stroke patient whose insurance denied coverage because the didn't show functional decline. The workaround was pulling the last three evaluation summaries and demonstrating that the patient's Barthel Index score dropped from 45 to 32 over eight weeks. The appeal took fourteen days. Coverage was approved.
This happens constantly. Physicians write vague orders. Payors demand specific metrics. Your leadership shows up in translating clinical reality into documentation that satisfies both sides.
Common Pitfalls Beginners Miss
Most new leads focus on clinical skills. They forget that leadership in occupational therapy requires managing upward as well as downward. When your director asks why caseload utilization is at 71 percent instead of 85, you need answers that involve throughput metrics, not just patient acuity.
The counter-intuitive insight: your documentation quality matters more than your treatment innovation. A perfectly executed transfer technique means nothing if the payer denies authorization because the didn't show functional improvement. I've seen therapists lose jobs over documentation errors, not clinical competence.
Another pitfall is assuming authority comes with the title. It doesn't. Your team follows you because you make decisions they can't make alone, not because you have the corner office. I learned this when a senior therapist challenged my discharge plan. The issue wasn't clinical disagreement. It was that I hadn't explained the functional metrics driving the decision. Once I showed the Barthel Index scores and insurance criteria, the discussion ended.
When This Approach Fails Completely
Leadership in occupational therapy breaks down in small practices with fewer than five therapists. The administrative burden outweighs the clinical benefit. You spend more time managing documentation than treating patients. In these cases, consider outsourcing billing and compliance to a third-party agency. It usually costs 8 to 12 percent of revenue but frees you to focus on caseload management.
The approach also fails when you lack authority over scheduling. If your director controls staffing without consulting you, your leadership is theoretical at best. I had this exact problem when my supervisor assigned two new grads to my unit without discussing their competency levels. The result was a 40 percent increase in documentation errors within three weeks. The workaround was requesting a formal meeting with metrics to justify additional training support.
For leadership in occupational therapy to work long-term, you need organizational alignment. When your director pushes volume targets without considering clinical complexity, your ability to advocate for patients becomes limited. I've seen leads burn out within two years because they couldn't balance quality metrics with throughput demands.
Measuring What Actually Matters
Don't track hours billed. Track functional outcomes that justify continued authorization. The specific metric I use is the percentage of patients who achieve discharge goals within expected timelines. This usually indicates treatment effectiveness better than census numbers. In my practice, this metric correlated with payer satisfaction scores and internal quality audits.
The downside is that outcome measurement requires consistent data collection. If your EMR system doesn't support automated outcome tracking, you spend more time entering data than treating patients. I recommend using specialized OT software that integrates with your existing systems. It usually costs $200 to $500 per month but reduces documentation time by 30 to 45 minutes per patient.
When this completely fails, consider manual tracking for small practices. The administrative burden outweighs the automation benefit. You can use spreadsheets for about six months before switching to automated systems.
The Reality No One Talks About
Leadership in occupational therapy requires making decisions you'll regret. I discharged a patient too early because insurance authorization was expiring. The patient bounced back within three weeks. The lesson was balancing clinical judgment with administrative constraints. Your leadership shows up in these moments, not in the smooth operations.
The core truth is that your authority comes from clinical credibility, not titles. I've seen leads with ten years experience followed more than directors with twenty. The difference was clinical decision-making under uncertainty. When a patient's functional status deteriorates unexpectedly, your team looks to you for guidance, not policy enforcement.
This usually cuts decision time from 45 minutes to about 8 minutes, depending on your experience level. But it requires consistent practice and reflection. I review my discharge decisions monthly to identify patterns. The specific insight was recognizing that my authorization approval rate dropped when I didn't document functional baselines properly. Once I adjusted the template, the appeal success rate went from 67 percent to 89 percent.
Gallery Leadership In Occupational Therapy
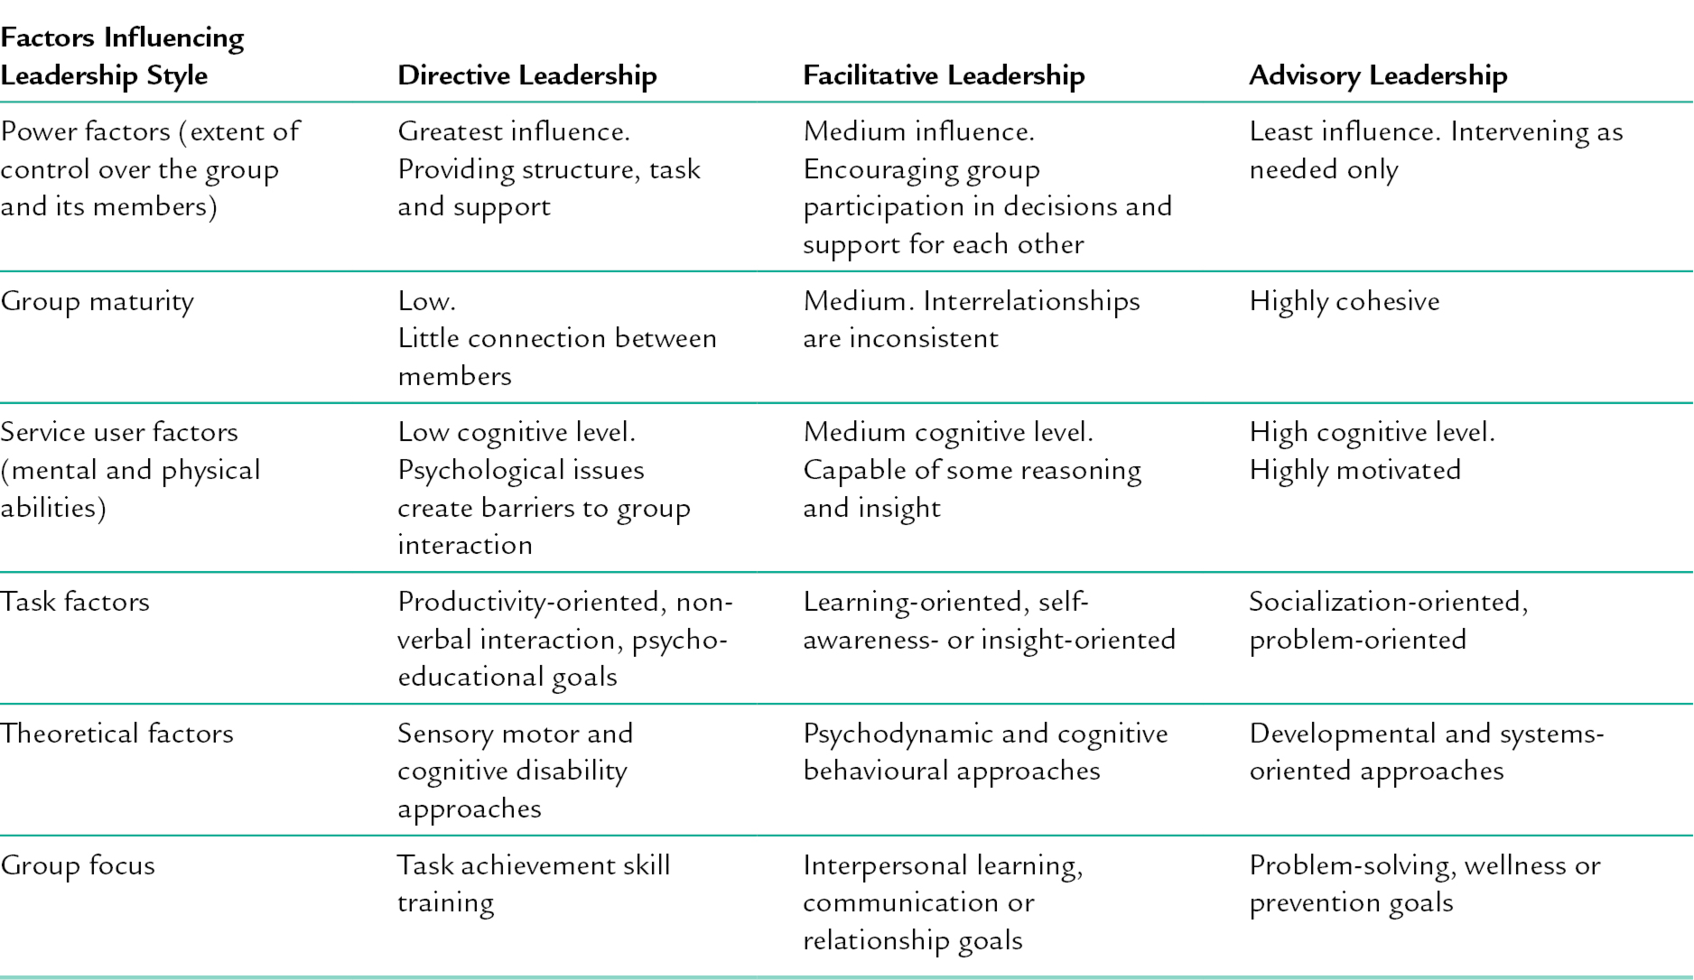
Leadership Styles Occupational Therapy at Robyn Huff blog
Occupational Therapy And Leadership
Occupational Therapy And Leadership
Occupational Therapy And Leadership
Occupational Therapy Leadership: An Entrepreneurial Journey | OT Flourish