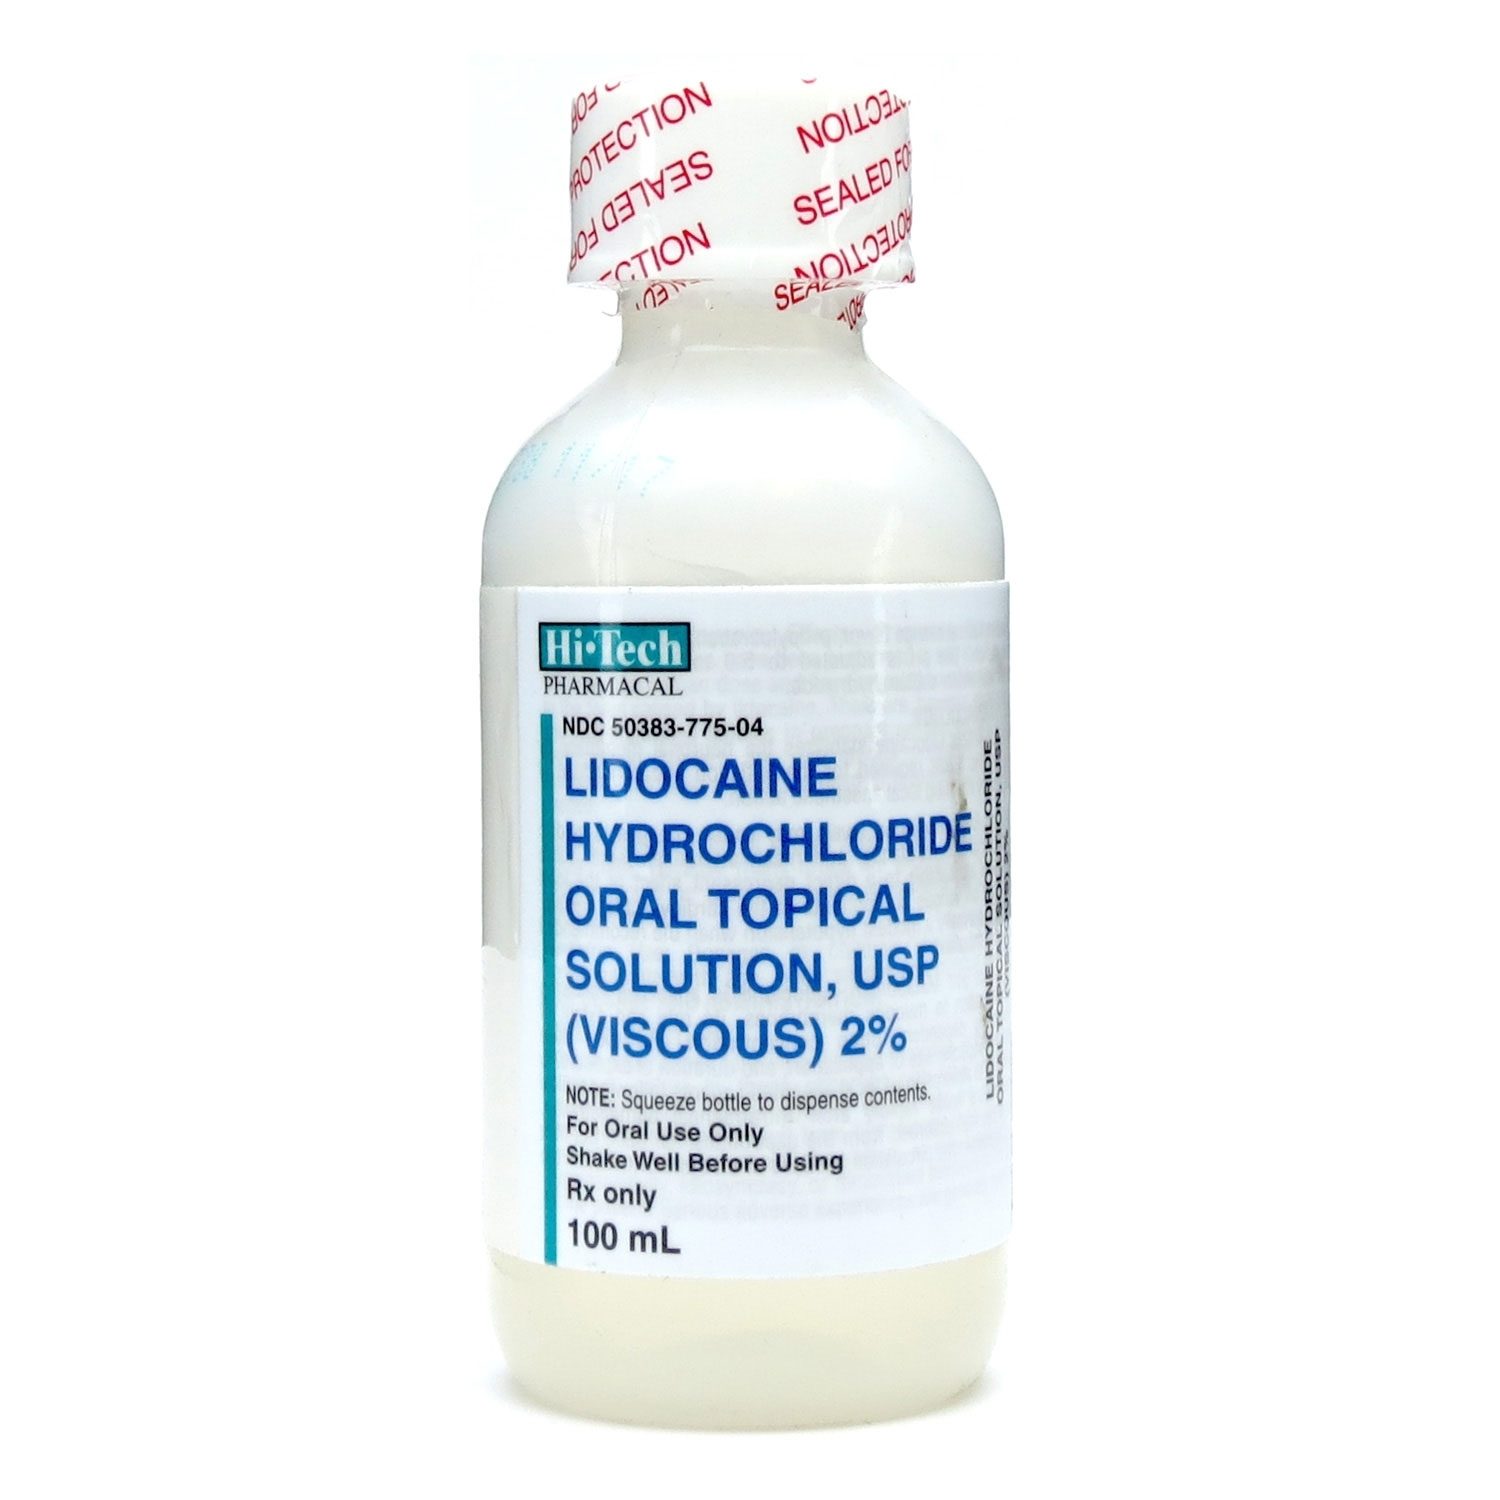
What Lidocaine Viscous 2 Actually Is
Lidocaine Viscous 2 Oral Solution is a prescription topical anesthetic. It contains 2% lidocaine in a viscous base designed to coat the mucous membranes of the mouth and throat. The "viscous" part means it is thickened so it stays where you put it instead of washing away immediately with saliva. I used to dispense this stuff regularly for patients dealing with oral mucositis from chemotherapy, refractory canker sores, and severe pharyngitis that makes swallowing impossible. The idea is straightforward: coat the affected area, wait, and you get numbing that lasts long enough to eat or drink without agony. That is the theory anyway. The mechanism is standard sodium channel blockade. Lidocaine enters the nerve terminal through the cell membrane, binds to the intracellular portion of voltage-gated sodium channels, and stabilizes the membrane. This prevents depolarization and propagation of the pain signal. Nothing mystical about it.
What matters more than the pharmacology is the formulation. The viscous vehicle is typically cellulose-based. It gives the solution that syrupy consistency so it adheres to the mucosa. Plain lidocaine solution without the viscosity just runs right through. You would use the entire bottle in two swigs and get no meaningful contact time. Onset is usually within one to two minutes. Duration ranges from thirty to ninety minutes depending on the surface area covered and how much you move your tongue around afterward. A small ulcer on the buccal mucosa might stay numb for an hour. A diffuse pharyngitis case could wear off in twenty minutes because you are swallowing constantly even when trying not to.
Proper Dosing and Administration
For adults, the typical dose is 15 milliliters (approximately one tablespoon) taken up to four times daily, preferably twenty minutes before meals. Swish it around the mouth for a few seconds and let it pool in the areas that need it most. Do not swallow large amounts intentionally. You want the medication contacting the mucosa, not going straight down your esophagus. If you are using it for throat involvement, tilt your head back slightly after coating the mouth and gargle for about thirty seconds before spitting out the excess. The goal is maximum contact time with minimum systemic absorption. For pediatric patients, dosing is weight-based. The usual recommendation is 0.5 to 1 milligram per kilogram per dose. Children are at higher risk for toxicity because they tend to swallow more of the dose rather than spitting it out. I always tell parents to measure carefully and not to eyeball it. A household teaspoon is not a reliable measuring device.
Get the Full Details

A Problem I Ran Into and How I Handled It
Here is something that catches people off guard. Viscous lidocaine 2% contains 20 milligrams of lidocaine per milliliter. When you take 15 milliliters, that is 300 milligrams of lidocaine in a single dose. If a patient swallows most of it rather than spitting it out, that 300 milligram dose hits the gastrointestinal tract and gets absorbed systemically. For a small elderly woman weighing forty-five kilograms, that is nearly seven milligrams per kilogram. That is getting into dangerous territory. I had a patient last year who kept having breakthrough episodes of severe oral pain despite using the medication exactly as prescribed. Turns out she was swallowing the entire dose because she found spitting gross and wasteful. She was also taking it six times a day instead of four. She was accumulating lidocaine in her system. First sign was tongue numbness that lasted all day, then mild dizziness and metallic taste. Those are early toxicity markers. The workaround was switching her to a smaller dose protocol. Instead of 15 milliliters four times daily, she did 5 milliliters three times daily and focused on swishing and spitting. We also had her sit upright for ten minutes after each dose to minimize reflux-related swallowing. Her pain control held up adequately and the side effects disappeared. Sometimes less medicine actually works better when the delivery method is the problem.
Things People Get Wrong
One common mistake is heating the solution before use. Some people think warming it will make it more effective. It will not. Heat does not increase lidocaine penetration through mucous membranes in any clinically meaningful way. It might thin the viscosity slightly which could actually reduce contact time. Keep it at room temperature. Another issue is using it right before brushing teeth or eating anything abrasive. If you coat your mouth with lidocaine and then immediately brush your teeth or chew hard food, you are going to traumatize tissue you cannot feel. I had a patient who burned the roof of her mouth on hot toast because she used the viscous lidocaine and forgot how numb she was. She ended up with a full-thickness palatal ulcer that took weeks to heal. The medication was helping the underlying condition but caused a new problem through loss of protective sensation. Do not use it for extended periods without follow-up. More than seven to fourteen days of continuous use on intact mucosa is pushing it. On broken or inflamed mucosa, systemic absorption increases significantly because lidocaine accesses the bloodstream directly through exposed capillaries. The labeled maximum daily dose is 300 milligrams for healthy adults, but that number assumes normal absorption through intact tissue. With ulcerated mucosa, you can exceed that without realizing it.
Drug Interactions Worth Noting
Cimetidine and propranolol both inhibit hepatic metabolism of lidocaine. If a patient is on either of these and also taking viscous lidocaine regularly, their clearance drops. Cimetidine reduces hepatic blood flow and inhibits CYP1A2 and CYP3A4. Propranolol has a similar effect on hepatic extraction. In practice, this means standard doses can accumulate to toxic levels in patients taking these medications concurrently. Other local anesthetics should not be used simultaneously. Adding benzocaine gel on top of viscous lidocaine is a recipe for methemoglobinemia risk, especially in children. The combination also increases total local anesthetic load without adding meaningful benefit. It just increases toxicity risk.

When This Approach Fails Completely
Viscous lidocaine is a surface anesthetic. It does not penetrate deep tissue. If the pain source is submucosal or deeper, like a dental abscess or trigeminal neuralgia, this medication will do nothing meaningful. I saw a patient who insisted her jaw pain was from mouth sores and kept requesting refills of viscous lidocaine. She had been using it for three weeks with no relief. The actual problem was an impacted molar causing osteomyelitis. The lidocaine was masking symptoms enough to delay diagnosis by two weeks. Surface anesthetics do not diagnose. They only treat superficial mucosal pain. Systemic absorption of even topical lidocaine can cause cardiac conduction abnormalities at high doses. QT prolongation and arrhythmias have been reported, particularly in patients with pre-existing conduction defects or those taking other QT-prolonging medications. If a patient has a history of heart block or is on Class IA or Class III antiarrhythmics, you need to be cautious about cumulative dosing.
Practical Storage and Handling Notes
Store at controlled room temperature, between 20 and 25 degrees Celsius. Do not freeze it. Freezing can alter the viscosity base and cause phase separation. Once opened, the bottle is stable for about ninety days. After that, preservative effectiveness declines and contamination risk increases. Write the opening date on the label with a marker. I know it seems petty but I have seen patients keep opened bottles for months and then wonder why the solution looked cloudy. The solution is slightly acidic with a pH around 4.3. Do not mix it in alkaline solutions or foods. Baking soda mixed into the solution will raise the pH, which increases the fraction of non-ionized lidocaine. That sounds like it would improve penetration but it actually causes unpredictable absorption kinetics and can precipitate the lidocaine out of solution. Stick to taking it straight or mixing with cool water if the taste is unbearable.
Bottom Line
Lidocaine Viscous 2 Oral Solution is useful for its niche. Superficial oral and pharyngeal pain where coating the tissue makes sense. It is not a cure for anything. It does not treat infection, inflammation, or deep tissue pathology. It numbs. Use it appropriately, measure carefully, watch for systemic absorption in patients with ulcerated mucosa, and do not let it delay diagnosis when the pain pattern does not match a superficial source. The margin between effective dosing and toxicity is narrower than most people expect, especially in vulnerable populations.


