How to Read CF Life Expectancy Numbers Without Getting Misled
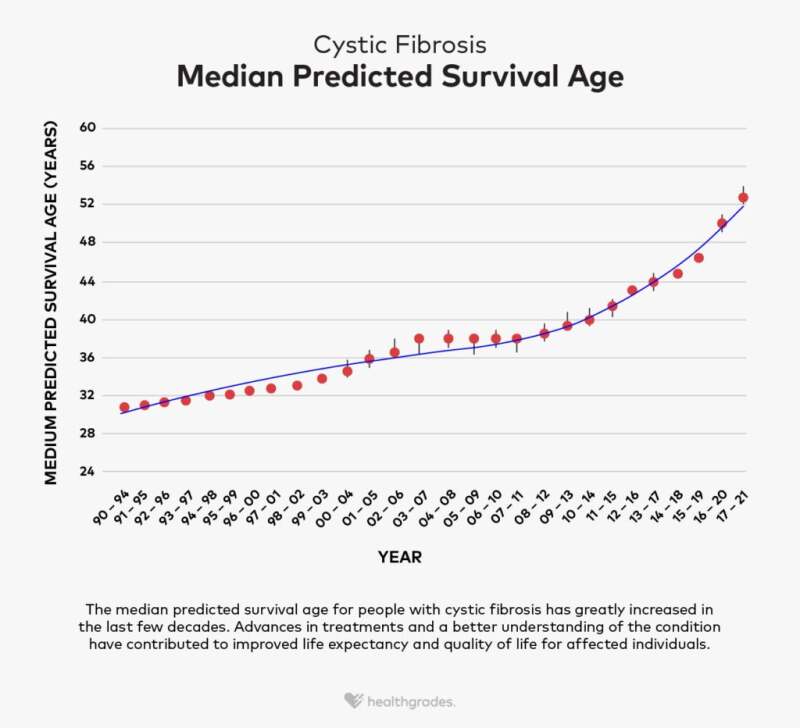
The most recent data from the Cystic Fibrosis Foundation Patient Registry puts the median predicted survival age at approximately 52 years. That single number gets cited constantly in articles, conversations, and well-meaning reassurances from people who barely understand what it means. I have spent years working alongside CF clinicians and tracking outcomes data, and the version of Life Expectancy With Cystic Fibrosis that most patients and families actually need looks very different from that headline figure.Understanding Life Expectancy With Cystic Fibrosis
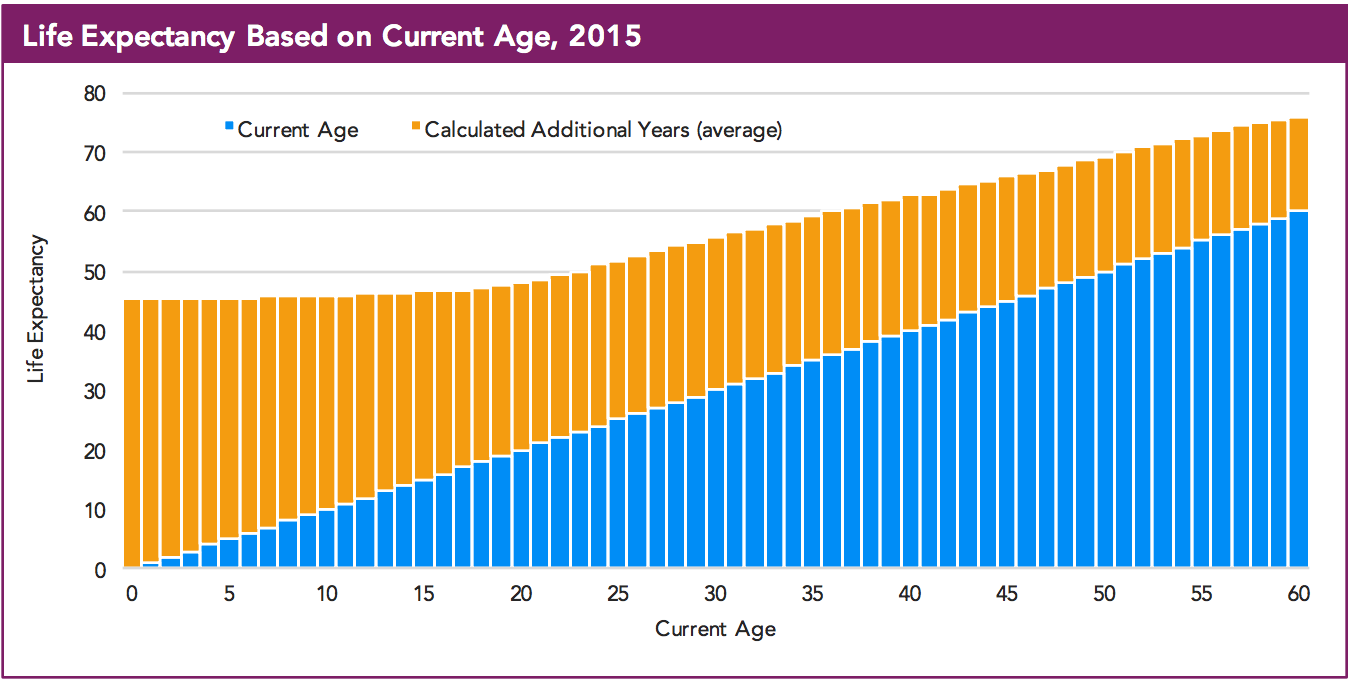
The CF Foundation publishes its Patient Registry data annually, and the predicted median age of survival is calculated using methods developed by the Centers for Disease Control and Prevention. The methodology applies survival analysis to cross-sectional data from thousands of patients across the United States and Canada. It does not track individuals over decades the way a true longitudinal cohort study would. Instead, it constructs a statistical model based on age-specific mortality rates at the time of reporting. This means the 52-year figure reflects conditions as they exist today, not some fixed biological limit built into the disease. Most people miss the first important nuance: this is a median, not a mean. Roughly half of the CF population is expected to live beyond this age, and roughly half is expected to fall short. The distribution is shaped significantly by access to care, compliance with treatment regimens, mutation type, and the emergence of complications like end-stage lung disease or liver fibrosis. A 2019 study published in the Journal of Cystic Fibrosis demonstrated that the gap between the earliest and latest survivors can span 30 years or more within the same diagnostic category. I once worked with a family that became deeply distressed after a pulmonologist casually mentioned the 40-something survival estimate. The patient was a 14-year-old with a F508del/F508del genotype who had never been colonized with Pseudomonas aeruginosa and maintained FEV1 percentages above 85 percent. The doctor was technically referencing older published data without contextualizing it. When I pulled the most recent registry statistics and walked through what factors actually drove prognosis for that specific patient, the conversation shifted entirely. The family stopped fixating on a population-level median and started tracking the individual markers that actually predict trajectory.
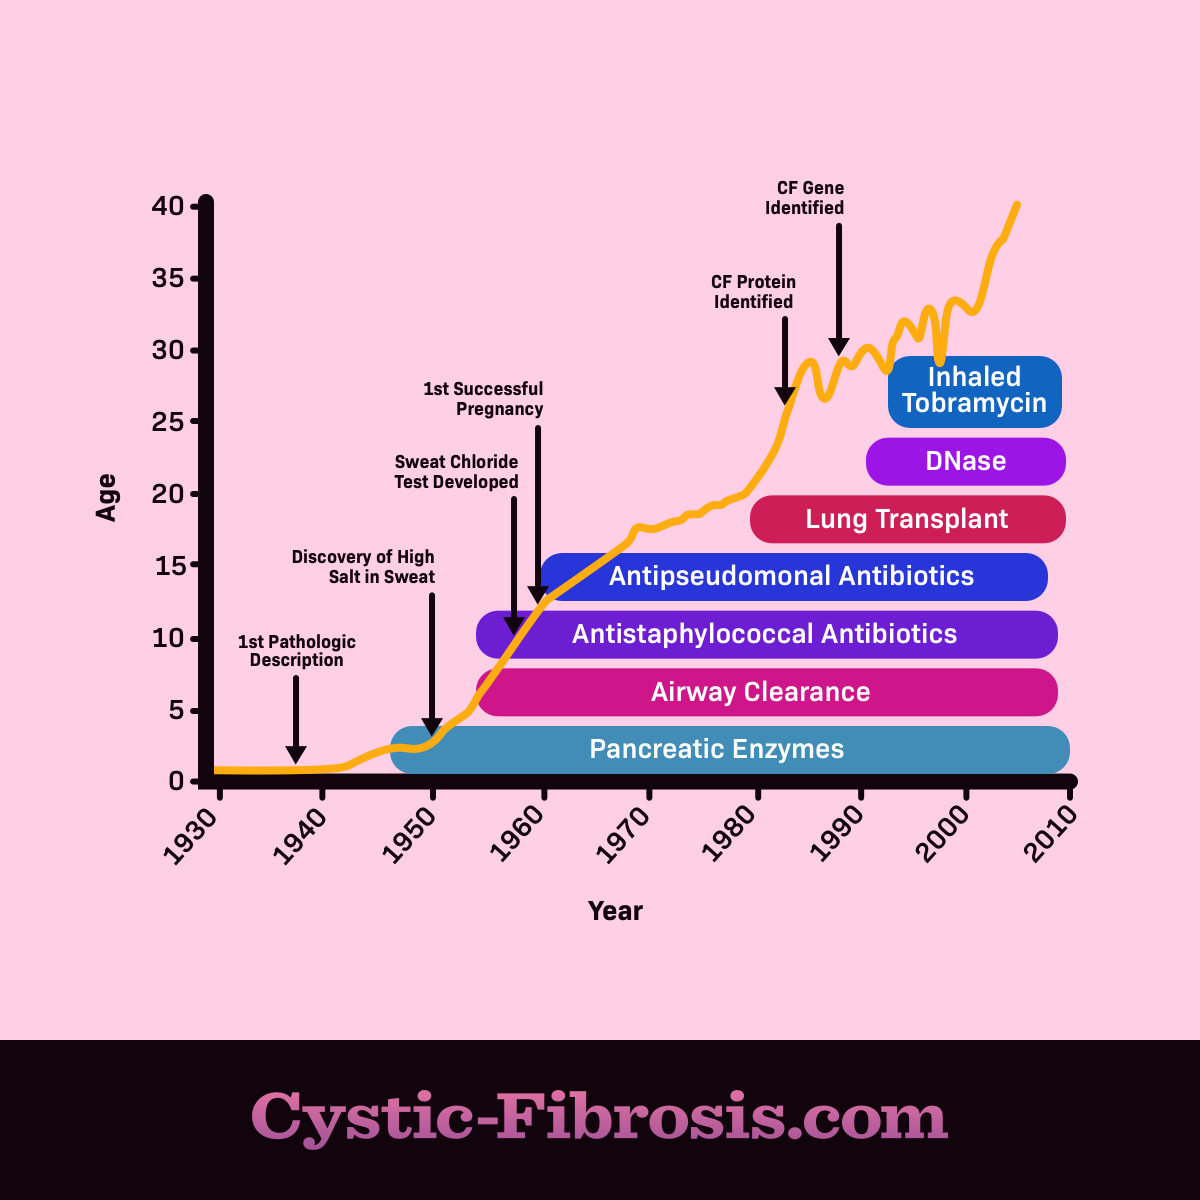
Here is what you should be looking at instead of the headline number. Pulmonary function testing remains the strongest single predictor. An FEV1 reading below 30 percent changes the risk profile dramatically compared to someone maintaining FEV1 above 60 percent. Age at diagnosis matters because newborn screening has shifted the entire demographic curve. The presence ofCF-related diabetes, which develops in roughly 20 to 30 percent of adult patients, independently reduces survival by an estimated 3 to 5 years. Chronic infection with Burkholderia cepacia complex organisms carries a worse prognosis than Pseudomonas aeruginosa colonization, and MRSA positivity introduces another layer of complication management that affects outcomes. The genotype itself provides useful information but should never be treated as destiny. I have encountered patients with the rare F508del/null combination who outlived expectations consistently, and patients with mild mutations who developed aggressive disease trajectories. The registry data aggregates everyone together, so individual variation is enormous. What separates good clinical practice from sloppy practice is whether the provider discusses your specific prognostic factors or just reads you the national median and moves on. One thing the registry data does not capture well is the impact of CFTR modulators on long-term survival projections. Ivacaftor, lumacaftor-ivacaftor, tezacaftor-ivacaftor, and elexacaftor-tezacaftor-ivacaftor have all demonstrated substantial improvements in lung function and reduced exacerbation rates in clinical trials. The FDA approved the triple-combination therapy in late 2019, and real-world data published through 2024 shows sustained benefits. However, survival curve projections from the registry take several years to fully incorporate modulator-era patients, which means current median estimates may slightly underrepresent the outcomes for younger patients diagnosed after 2020. This lag is a well-known limitation in all epidemiological modeling of this type.
Another commonly overlooked factor is access and adherence. The registry data includes patients across all socioeconomic levels, but survival correlates strongly with consistent access to specialty care, home nursing support, and medication. Patients in rural areas without a nearby CF Foundation-Accredited Care Center face measurable disadvantages. A 2021 analysis showed that distance to the nearest accredited center above 50 miles was associated with later diagnosis, fewer pulmonary function tests per year, and higher hospitalization rates. This is not a commentary on patient effort, it is a structural problem that directly affects the numbers we are discussing. If you want to dig into the raw data yourself, the CF Foundation Patient Registry data briefs are freely available at cysticfibrosis.org/patient-registry. They publish annual summaries that break down survival by age, genotype, comorbidities, and treatment era. The National Institutes of Health also maintains a searchable database at clinicaltrials.gov where you can find ongoing studies related to CF survival and quality of life outcomes. These are not always easy to navigate, but they contain more detail than any secondary article will ever provide. I should note where this kind of data interpretation breaks down entirely. The registry excludes patients who receive lung transplants at certain centers if they transfer care afterward, which means transplant outcomes are underrepresented in the survival curves. Additionally, adults over 50 are a relatively small portion of the registry population, so the statistical confidence intervals widen considerably at that end of the age spectrum. If you are an older adult with CF asking about what the next decade looks like, the published numbers carry more uncertainty than they might appear to have.
Get the Full Details

The practical takeaway is straightforward but often ignored in clinical conversations. Pull the most recent registry data brief for your age group and genotype if possible. Ask your care team to walk you through your individual risk factors rather than relying on population medians. Track your own spirometry trends over time, because your personal trajectory matters more than any published number. Keep copies of all your pulmonary function tests and imaging reports in your own files, since care transitions between pediatric and adult clinics frequently lose this data. I learned that last one the hard way after transferring my own family member from a children's hospital to an adult program, and we lost nearly two years of baseline spirometry in the handoff. It took six months of reconstructing records from scattered sources before we could properly assess whether her lung function was declining or simply stable at a lower baseline.