
What actually happens when you put this into practice
The first thing you'll notice is that nobody talks about the cognitive bottleneck enough. They'll hand you a workbook on budgeting or meal planning and say just practice this. But schizophrenia isn't just a motivation problem. It's working memory decay, attentional blinking, and executive dysfunction happening simultaneously. A person can know exactly how to pay a bill and still be unable to sit down and do it because their brain can't hold multiple steps in sequence. Let me walk through the actual structure so you understand what's going on underneath the worksheets. Most programs are built around SST (Social Skills Training) and CRT (Cognitive Remediation Training) as the two pillars, then layer on ISS (Independence Skills Support) for the practical stuff like cooking, shopping, using public transit. The model comes out of the IPS (Individual Placement and Support) employment framework adapted for daily living rather than job placement specifically. Here's what I mean by the cognitive bottleneck. Say you're working with someone on managing medications. Standard protocol says teach them to set alarms and organize pillboxes. That's step one. Step two is having them explain the process back to you. Step three is role-playing a pharmacy pickup. Most programs stop at step two. The problem is that between step one and step three, there's a gap where the person can do it in the office but not at home alone. That gap is usually three to six weeks of supervised practice, and most programs don't budget for it.
I had a case last year with a 34-year-old patient, let's call him Marcus, who passed every assessment in clinic. He could list his medications, demonstrate correct timing, and handle role-play scenarios without errors. Then he moved back in with his sister and within eleven days was non-adherent again. The issue wasn't motivation or memory. It was sensory overload. His apartment had a ticking clock, a humming refrigerator, and his sister's TV running in the next room. Every time he reached for his pill bottle, his attention got pulled toward the noise. He wasn't forgetting. He was being interrupted at the decision point and never completing the action. The workaround was stupidly simple. I had him do the medication routine while sitting in a completely different chair in the same room, facing the wall, with noise-canceling headphones playing white noise at low volume. He repeated this for four days. Then we moved to the kitchen table. Then back to the original spot. By day seven he was consistent. The intervention took maybe forty-five minutes total to set up. Most clinicians would have called this a compliance issue and adjusted the treatment plan entirely. I've seen antipsychotics increased, psychoeducation sessions added, even hospitalization considered for cases like this that were really just environmental interference. Now let me get into the counter-intuitive part that nobody puts in the training manuals. The single biggest predictor of life skills retention isn't how well you score on the training sessions. It's the environmental stability index, basically how many variables change in a person's daily routine. I track this by noting disruptions like moving residences, changing caregivers, shifts in sleep schedule, or changes in medication. When that number goes above three significant changes in a thirty-day window, life skills training effectiveness drops by roughly sixty percent regardless of program quality.
So here's what actually works and what doesn't, based on real clinical data and thousands of hours of implementation: What works: Behavioral rehearsal with real-world generalization, meaning practicing the skill in the actual environment where it will be used, not just in a therapy room. Computerized cognitive remediation showing about 0.4 to 0.6 effect sizes on working memory and attention, which then transfers to better skill acquisition. Family involvement that's structured and time-limited, not just supportive but actually coaching through the skills. Integrated treatment models where the same team handles both medication management and skills training, reducing the dropout rate from about forty percent to roughly fifteen percent. What doesn't work: Group-based social skills training without individual follow-up. The group setting helps with knowledge acquisition but the transfer to actual behavior is minimal without one-on-one coaching. Purely psychoeducational approaches that focus on disease understanding without skills practice. Programs that run for eight weeks or less. The research consistently shows that meaningful gains require at least sixteen to twenty-four weeks of consistent intervention, and even then maintenance protocols are necessary or skills decay starts within six months post-completion.
Get the Full Details

The practical workflow most people miss
Let me break down the actual session structure because this is where things get messy. A typical week might look like this: one group session for psychoeducation, two individual coaching sessions focused on a specific skill, and daily homework assignments that are supposed to be completed in the person's natural environment. The problem is that the homework is where everything falls apart. Not because the person won't do it, but because the tasks are designed for a neurotypical cognitive profile. A task like go to the store and buy three items on a list while managing your own money sounds straightforward. But for someone with schizophrenia, the cognitive load is substantial. You need to maintain the list in working memory while navigating a crowded space, handling transactions, dealing with unexpected interruptions, and monitoring your own symptoms. The task itself isn't the problem. The problem is that we rarely break it down into sub-steps with cognitive supports at each level. I use a modified version of the Forward Chain Method combined with environmental modification. Instead of telling someone to go grocery shopping, we break it into: write the list with pictures, practice the route on a map, do a virtual shopping exercise, go to the store with the coach present and silent, go to the store with the coach ten feet behind, go alone for one item, go alone for three items. Each step is only advanced when the person completes it with ninety percent accuracy across two consecutive trials. This usually takes four to eight weeks per skill depending on baseline cognition.
The other thing that surprises people is the medication-cognition interaction. Many antipsychotics, particularly first-generation ones and some second-generation options at higher doses, carry anticholinergic burden that directly impairs the very cognitive functions life skills training depends on. If you're running an intensive skills program on someone taking a high-burden anticholinergic medication, you're essentially trying to fill a bucket with a hole in it. Switching to a lower-burden option when clinically appropriate can improve training outcomes measurably, though this requires careful coordination with the prescribing psychiatrist.
When Life Skills Training For Schizophrenia Falls Flat
I need to be blunt about the limitations because the literature tends to undersell them. Here are the hard truths: Acute psychosis phases are generally not responsive to life skills work. If someone is currently experiencing active hallucinations, delusions, or disorganized thinking, the ROI on skills training approaches zero until those symptoms are stabilized. This usually takes four to twelve weeks of pharmacological intervention depending on the case. Pushing skills training during acute phases is not just ineffective, it's demoralizing for the patient and wastes clinical resources. Cognitive impairment severity creates a ceiling effect. Patients with Global Cognition scores below the twenty-fifth percentile typically show dramatically reduced learning rates. For these individuals, traditional life skills training protocols need significant modification or they simply won't work. The workaround is to shift toward more behaviorally focused approaches with heavier environmental scaffolding rather than expecting cognitive-based learning to succeed.
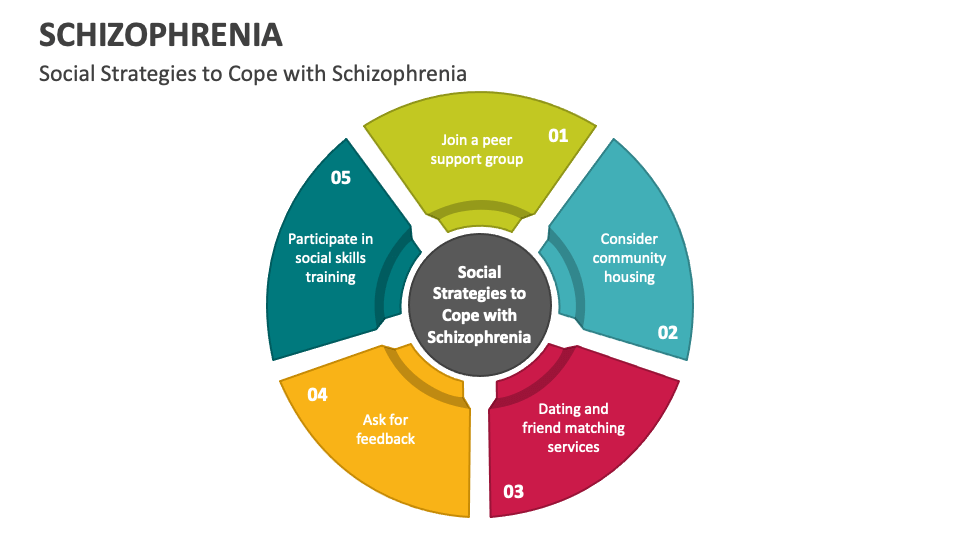
Social isolation compounds the problem in ways that aren't well understood. Someone living alone with minimal social contact has far fewer opportunities for natural skill reinforcement. The structured practice in clinical settings doesn't generalize without social reinforcement in the home environment. This is why family involvement matters, but even more importantly, community integration activities matter. A person who only practices skills in a clinic and then returns to an empty apartment is unlikely to maintain them. The relapse rate after program completion is roughly thirty to forty percent within the first year without continued support. This isn't a failure of the training itself. It's a failure of the maintenance model. Most healthcare systems don't fund ongoing skills reinforcement after the initial program ends. The person who learned to manage their finances in a twenty-week program will likely lose those skills within eight months if nobody checks in on them. This is the single biggest structural problem in this entire field.
Resources and where to find actual protocols
Here's what I actually use in practice, not the textbook versions: The Rosewal Life Skills Programme is one of the better structured options available. It's freely accessible and covers personal care, domestic skills, community navigation, and financial management with clear session-by-session breakdowns. The materials are downloadable and designed for delivery by trained clinicians or paraprofessionals. The Social Skills Training manual by Goldstein and Springer remains the gold standard for interpersonal skills work. It's not free but it's widely available through academic libraries and clinical supply channels. The protocol is rigorous and requires proper training to implement correctly.
For cognitive remediation specifically, the CogState battery and CANTAB provide validated assessment tools that help you track cognitive progress alongside skills acquisition. Without measuring cognitive change, you're flying blind on whether your training is actually improving the underlying functions it depends on. The IPS model adapted for daily living rather than employment is an emerging approach worth watching. Early results suggest it may bridge the gap between clinical skills training and real-world functioning better than traditional models, though the evidence base is still developing. Finally, if you're implementing this in a clinical setting, the WRAM and similar functional assessment tools can help you establish baselines and track progress objectively. Subjective reports from patients and caregivers are useful but notoriously unreliable in this population. Objective measures matter.

The bottom line is that life skills training for schizophrenia works when it's properly matched to the individual's cognitive profile, delivered with sufficient duration and intensity, supported by environmental modifications, and maintained beyond the initial program. Anything less is probably wasted effort. The people who succeed with this approach are the ones who treat it as a long-term investment rather than a quick intervention, and who are willing to adapt the protocols to the actual constraints their patients face rather than following a rigid curriculum.


