Understanding What Actually Helps When the Ligamentum Flavum Thickens
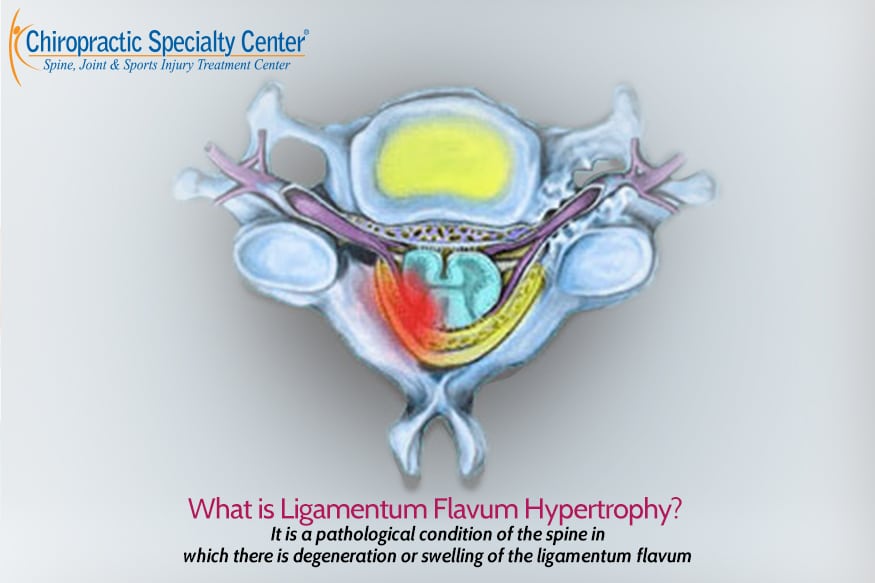
The ligamentum flavum sits between the laminae of adjacent vertebrae and its job is to help maintain upright posture and assist in returning the spine to neutral after flexion. When it hypertrophies, usually from chronic mechanical stress and age-related changes, it can encroach on the spinal canal or neural foramina. This is most common in the lumbar spine but shows up in the thoracic and cervical regions too. The thickening itself is structural tissue change, so no amount of stretching will dissolve it. What you can do is manage symptoms, improve neural mobility, and slow further degenerative loading through targeted movement strategies. I work with patients who have confirmed hypertrophy on MRI, and the ones who get meaningful relief follow a very specific protocol. It is not about aggressive stretching or trying to "open up" the canal through extreme flexion. That approach actually increases compressive forces on the already compromised ligament. Instead, the focus is on creating neural glide, improving segmental mobility in the unaffected motion segments, and reducing the mechanical load that drives further hypertrophic response. The core exercises break down into four categories. First, neural mobilization. Not the aggressive flossing you see on social media, but gentle, pain-free oscillations of the sciatic nerve and femoral nerve depending on which level is involved. A typical sequence is five repetitions of seated nerve glides held for two seconds, performed three times daily. Second, flexion-based positioning. Since flexion opens the spinal canal, static held positions in a comfortable flexed posture for 30 to 60 seconds can provide symptomatic relief. A supine position with knees bent over a chair or pillows works for most lumbar cases. Third, core stabilization through the transverse abdominis and multifidus. These muscles act as a natural corset and reduce the shear and compressive loads that contribute to ligament stress. I prescribe three sets of ten slow prone holds, holding each contraction for eight seconds. Fourth, hip and thoracic mobility work. When the hips and upper spine are stiff, the lumbar region compensates and the ligamentum flavum takes more repetitive strain than it should.
Here is something most people miss. The hypertrophy is often most problematic not at the level with the most thickening but at the level immediately above or below it, where compensatory motion creates additional stress. I had a patient last year with L4-L5 hypertrophy whose primary symptoms actually came from L3-L4 and L5-S1 taking on extra motion. We shifted the exercise focus to those adjacent segments and his walking tolerance improved within three weeks. The hypertrophy at L4-L5 did not change on follow-up imaging, but his functional capacity did because the adjacent levels were no longer fighting against each other. Another counter-intuitive point: extension-based exercises, which are standard for many disc problems, can actually worsen symptoms in ligamentum flavum hypertrophy. The posterior element compression during extension narrows an already compromised canal. If a patient presents with neurogenic claudication, meaning leg pain that worsens with walking upright and improves when sitting or leaning forward, extension work should be avoided or used very cautiously. A practical test is to have the patient walk while maintaining a flexed trunk posture versus an extended one. If symptoms clear significantly in flexion, that confirms the mechanical pattern and guides exercise selection. There are limitations to this approach that need to be stated clearly. Exercise will not reverse established hypertrophy. The ligament tissue has remodeled and the change is permanent without surgical intervention. What exercise does is improve the surrounding biomechanics enough that symptoms become manageable. Patients who expect their hypertrophy to shrink through any exercise program will be disappointed. The realistic outcome is improved function, reduced symptom frequency, and slower progression.
Surgical decompression remains the only intervention that directly removes the hypertrophied tissue. For patients with progressive neurological deficits, bowel or bladder dysfunction, or severe refractory pain that does not respond to conservative management after eight to twelve weeks, referral for surgical evaluation is appropriate. The exercise protocol described here is for stable, non-progressive cases managed conservatively. A practical progression timeline: weeks one through four focus on neural mobilization and flexion positioning only, introducing core stabilization in week three if pain allows. Weeks five through eight add hip and thoracic mobility work. By week eight, most patients can assess whether the conservative program is providing adequate symptom control or whether further intervention is warranted. Reimaging is rarely necessary unless there is a clear change in neurological status. Consistency matters more than intensity. The exercises should be performed daily, not pushed to fatigue. Aggressive movement in a spinal stenosis pattern creates more inflammation and swelling around the already compressed neural structures, which sets patients back. The goal is maintenance and gradual improvement, not a workout that leaves you sore. If symptoms increase during or after the exercises, the volume or intensity needs to be reduced, not pushed through.
Get the Full Details