
Getting Wound Beddown With Low-Level Light
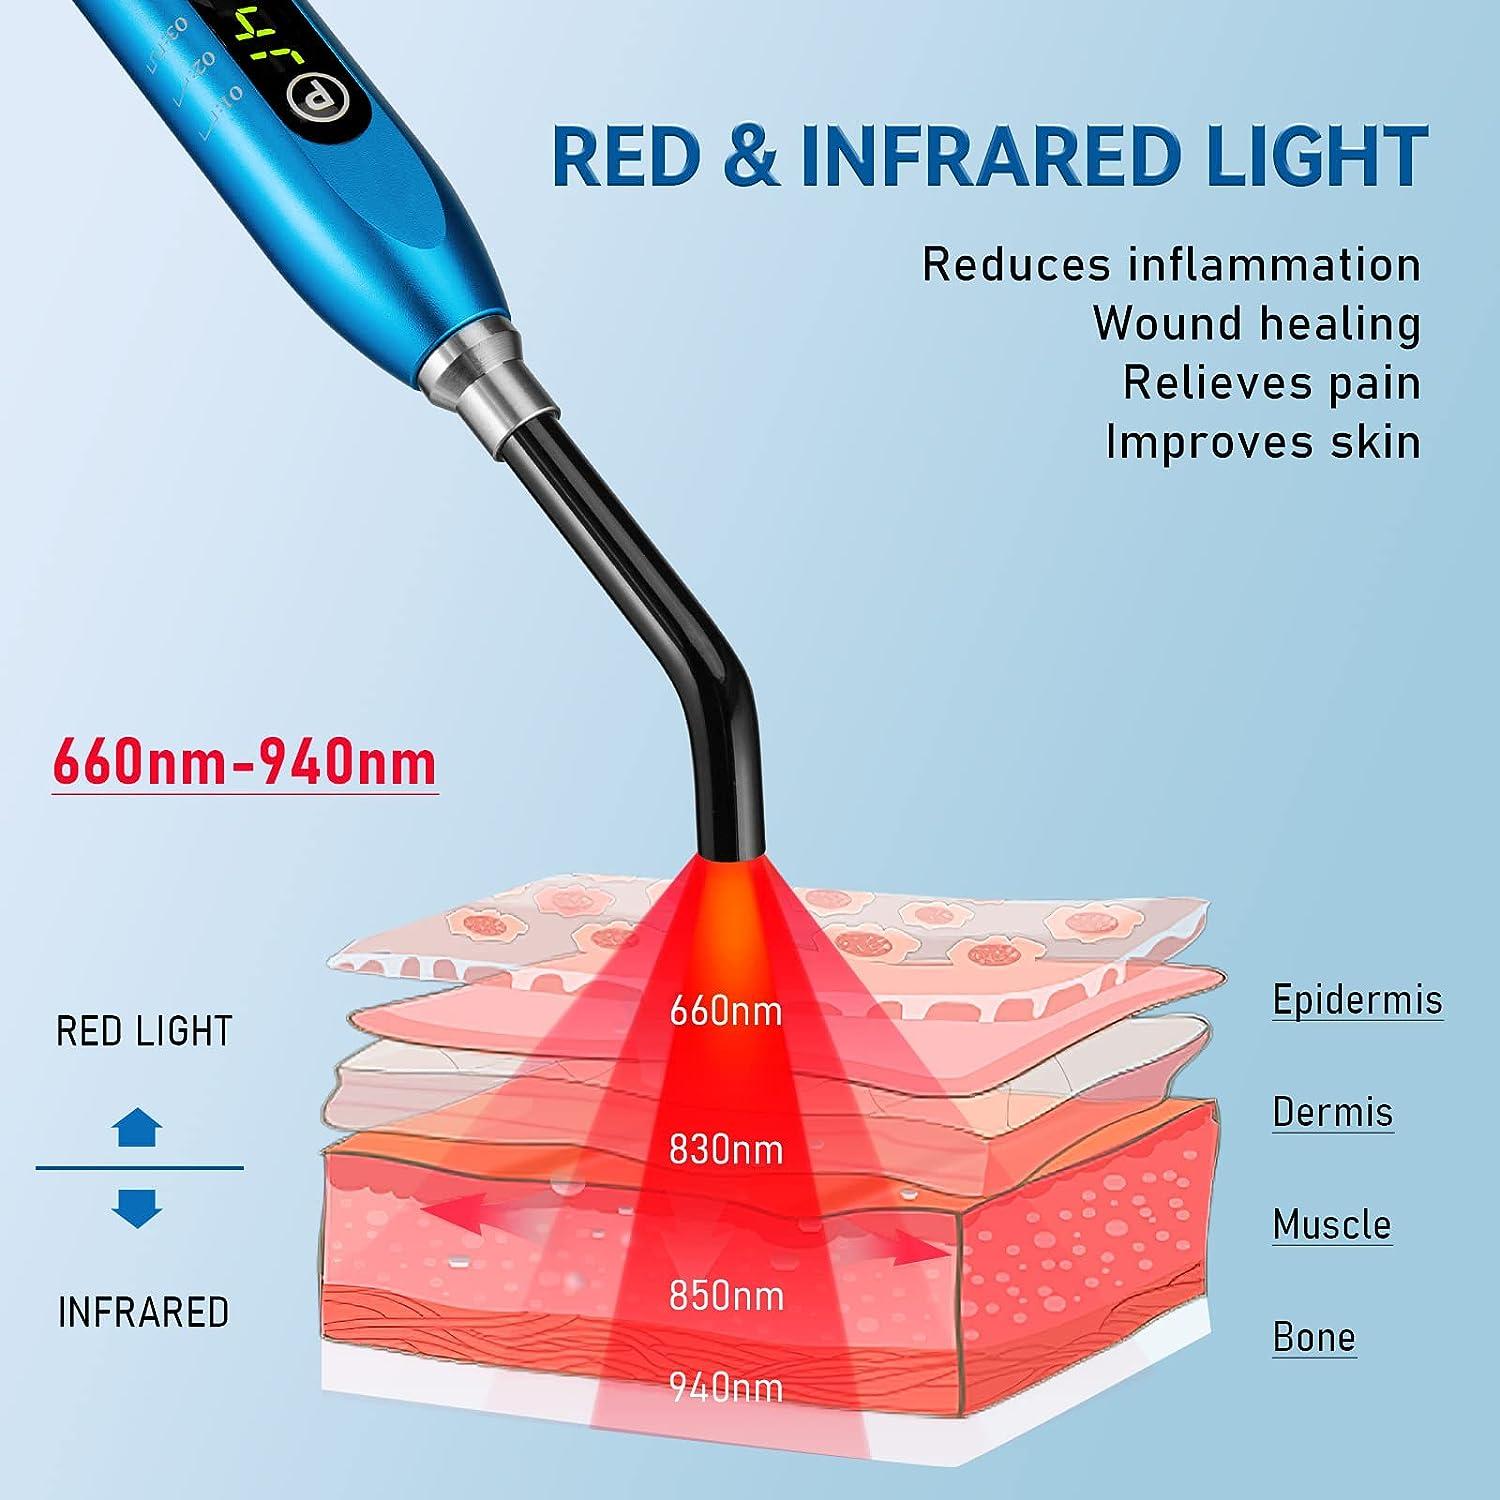
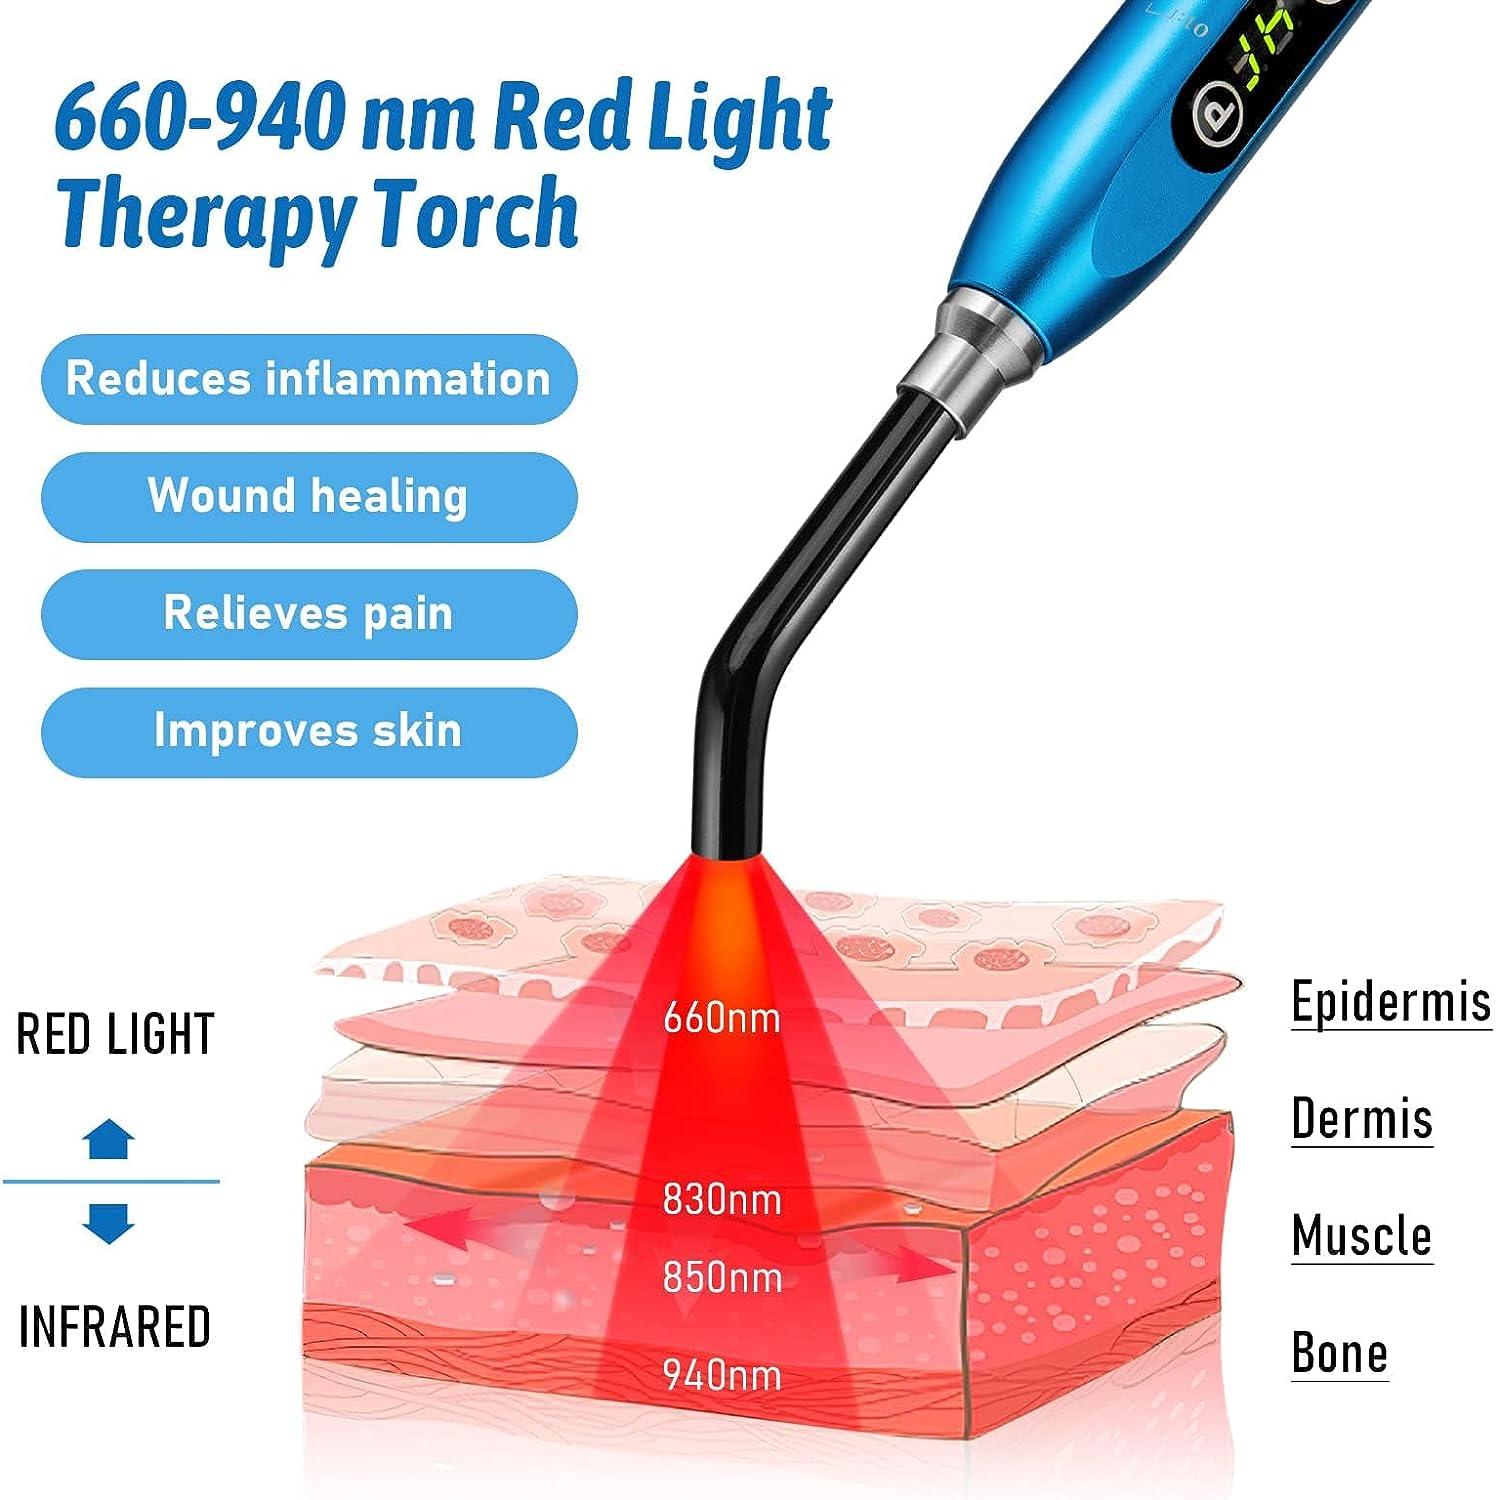
Most clinicians reach for light therapy when pressure ulcers stall out on standard wound care. The idea is straightforward enough. You apply low-intensity red and near-infrared wavelengths to the wound bed, and the photons get absorbed by mitochondria in the cells around the ulcer. That boosts ATP production, nudges inflammatory cytokines down, and speeds up collagen synthesis and angiogenesis. It is not magic. It is photobiomodulation, and it works best as an adjunct, not a replacement for offloading and proper dressing selection. I run protocols using devices that sit somewhere between 5 and 50 milliwatts per diode, typically in the 630 to 670 nanometer range for red light and 810 to 850 nanometers for near-infrared. Near-infrared penetrates deeper, which matters for stage 3 and stage 4 ulcers where the damage extends past the dermis into subcutaneous tissue or muscle. Red light handles more superficial healing. Here is how I dose it in practice. Energy density matters more than raw power output. A typical target falls between 4 and 10 joules per square centimeter delivered to the wound surface. If your device puts out 20 milliwatts per spot and you need 6 joules per square centimeter over a 4-square-centimeter wound, you are looking at roughly 3 minutes and 12 seconds of exposure per session. That math changes fast if your device spreads light across a wider field or uses multiple wavelengths simultaneously. Read the output specs carefully before you commit to a schedule.
Sessions usually run three to five times per week. I tend to stick with four days on, two days off just to keep things manageable without overdoing the cumulative dose. Some patients see faster granulation by week two. Others need closer to six weeks before the wound area shrinks noticeably. The ulcer stage, perfusion status, and nutrition all play bigger roles than the device itself. I had a patient with a stage 3 sacral ulcer that refused to close despite good offloading, regular debridement, and appropriate moist wound dressings. The wound was shallow but wide with a lot of undermined edges. I loaded the near-infrared channel at 850 nanometers and cranked the fluence to about 8 joules per square centimeter, aiming slightly past the wound margin onto the surrounding tissue where fibroblast activity needed a push. After three sessions the undermining started rolling inward. The breakthrough came when I stopped trying to treat the entire perimeter evenly and instead concentrated energy on the stalled lateral edges. Those were the places where perfusion was weakest. Treating the wound bed center directly was actually wasting photons because granulation tissue was already well perfused. That edge-targeting shift cut my total treatment timeline by roughly a week and a half.
What the Research Actually Says
The evidence base is mixed but leans positive. Systematic reviews from the last several years consistently show that low-level light therapy can reduce time to complete closure for pressure injuries compared to standard care alone. The effect sizes are moderate, not dramatic. You are looking at roughly a 20 to 30 percent reduction in healing time across most published trials, assuming the patient meets the right selection criteria. The Cochrane review on interventions for pressure ulcers gave light therapy a low-to-moderate quality rating. The studies were small, often underpowered, and heterogeneous in their parameters. That does not mean the therapy is useless. It means you should not expect miracles and you should not ignore the confounding variables like nutritional status, diabetes control, and compliance with repositioning schedules.
Get the Full Details
Who This Actually Helps and Who It Does Not
Stage 2 and early stage 3 ulcers respond best. The tissue is close enough to the surface that photon penetration hits the target cells without excessive scatter or absorption by overlying structures. Stage 4 ulcers with exposed bone, tendon, or fascia are a different problem. Light therapy can still help the surrounding granulation tissue and the wound edges, but deep skeletal involvement requires surgical intervention, not photons. If the ulcer is frankly infected with systemic involvement, you need antibiotics and possible debridement first. Light does not kill bacteria at the doses used for healing, and pushing photons into a purulent wound without source control just hides the problem longer. Patient selection matters enormously. Diabetics with peripheral vascular disease heal slower regardless of the modality. Malnourished patients will not close wounds efficiently no matter how many joules you throw at them. Serum albumin below 3.0 grams per deciliter is a red flag. Smokers carry a significant penalty due to vasoconstriction and carbon monoxide reducing oxygen delivery to tissues.
Device Selection and Avoiding Common Mistakes
Do not buy a device based on wavelength alone. The power output, beam profile, and stability matter more for clinical outcomes. Cheap LED panels often have significant drop-off at the edges of the treatment field. A wound that measures 5 by 5 centimeters might only receive full-dose irradiation across the central 3 by 3 centimeters. The rest gets diluted exposure. That leads to inconsistent results that make it look like the therapy does not work when the real issue is uneven dosing. Another common mistake is treating through dressings that absorb the target wavelength. Standard opaque gauze blocks most of the useful spectrum. Transparent film dressings like Tegaderm are mostly transparent to red and near-infrared light, so you can treat through them if direct contact is not practical. Hydrocolloids and alginates scatter and absorb significantly. Remove them before treatment and replace after. I also cannot stress enough how important skin protection is around the wound. Near-infrared produces heat even at therapeutic power levels. I use a thin layer of petroleum jelly on the periwound skin and keep the treatment time conservative. One patient developed a first-degree burn on the adjacent sacral skin because I extended the exposure to chase a higher fluence target without accounting for the reflective tray we were using. The metal tray bounced near-infrared back onto the surrounding skin. I switched to a black absorptive pad under the wound and the issue resolved completely.
Contraindications and Limitations
Absolute contraindications include active malignancy in the treatment field, pregnancy over the lumbar or sacral region, and direct exposure to the eyes without proper protection. Relative contraindications involve areas of reduced sensation where the patient cannot report excessive heat, thyroid tissue direct exposure, and hemorrhagic tendencies. If the patient is on photosensitizing medications like certain tetracyclines or thiazide diuretics, proceed with lower fluence and monitor closely. The biggest limitation nobody likes to admit is cost and access. Quality devices run anywhere from $800 to over $5,000 depending on the specifications and whether they include both red and near-infrared channels with adjustable dosimetry. Insurance coverage is inconsistent. Some payers cover it with the right documentation and ICD codes. Others deny it outright as investigational. If you are a home care provider, factor in the travel time and setup complexity. A typical home visit with light therapy adds about 20 to 30 minutes to the standard wound care visit duration. For advanced stage 4 ulcers with osteomyelitis suspicion, light therapy should never delay imaging and orthopedic consultation. I have seen too many cases where prolonged light treatment masked progressive tissue destruction that ultimately required surgical intervention anyway. The therapy buys time and can improve wound bed preparation, but it does not replace surgical judgment.
If you are considering this for your practice or a family member at home, the key is setting realistic expectations. Light therapy for bed sores is a solid adjunct for appropriate wound stages in appropriately selected patients. It is not a standalone cure and it will not compensate for poor nutrition, uncontrolled diabetes, or failure to offload pressure. Get the basics right first, then add the light.



