How I Actually Use Light Therapy For Fungal Skin Issues
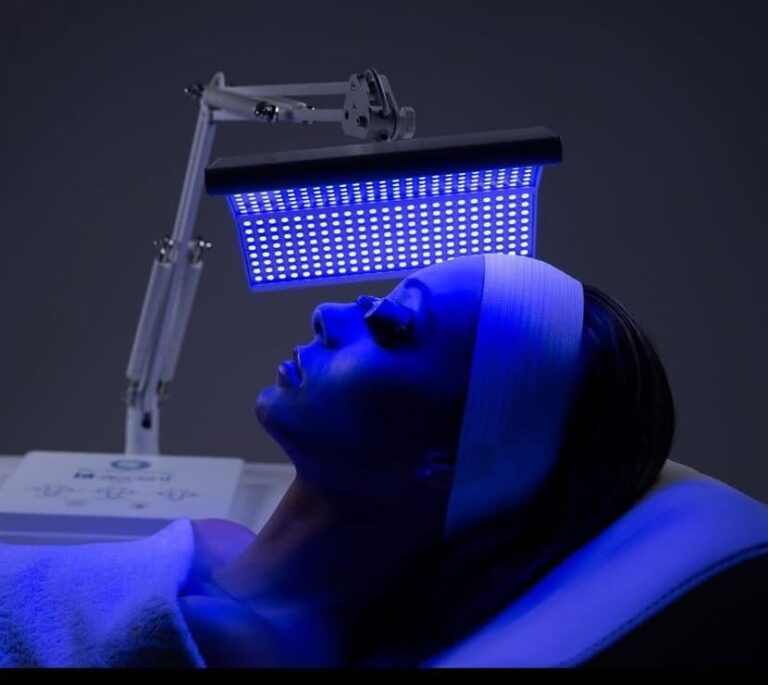
I have spent more time than I care to admit dealing with stubborn fungal skin infections. Topical creams, oral antifungals, the whole routine. About three years ago I started experimenting with LED light therapy as an adjunct treatment, and I want to walk you through what actually works, what doesn't, and the specific problems I ran into along the way. Light Therapy For Fungal Infections works primarily through two wavelengths. Blue light around 415nm targets porphyrins produced by certain fungi, creating reactive oxygen species that damage fungal cell membranes. Red light around 630nm to 660nm penetrates deeper and helps modulate inflammation while supporting tissue repair. The combination is what matters most in practice, not just picking one wavelength and hoping for the best.
Setting Up Your Light Therapy For Fungal Infections Routine
Here is the practical protocol I settled on after months of trial and error. You need a device that specifically lists blue light at 415nm plus red light at 630-660nm. Cheap single-wavelength panels won't cut it for anything beyond the most superficial infections. I use a panel from MuroMed and a separate blue LED strip for targeted application. The total cost was around $280 for the setup. Clean the affected area with soap and water, pat dry completely. Moisture blocks light penetration and wastes energy. Position the device 6 inches from the skin surface. Start with 10 minutes of blue light followed by 10 minutes of red light. Do this once daily. After four weeks, if you see improvement, extend the red light portion to 15 minutes and keep the blue at 10. Do not exceed 15 minutes per session regardless of what the manual says. I learned this the hard way. My first attempt involved leaving the device on for 30 minutes straight because I was impatient. The result was not faster healing. It was mild thermal damage to the surrounding skin and a rebound inflammation that made the infection look worse for about a week. Distance matters too. I initially held the panel too close and got uneven exposure. Measuring with a ruler each time solved that problem entirely.
What The Research Actually Says
There is legitimate peer-reviewed work here, though not as much as you might expect. A 2016 study in the Journal of Photochemistry and Photobiology B looked at blue light at 415nm against Candida albicans and found significant reduction in fungal load after repeated exposures. Another study in Lasers in Medical Science examined combined blue and red light against dermatophytes and reported better outcomes with the combination than with either wavelength alone. These are small studies. The sample sizes are modest. The conclusions are promising but not definitive. The mechanism is well understood enough to be confident, which is why I keep coming back to it. Fungi produce porphyrins as part of their metabolism. When those porphyrins absorb blue light photons, they transfer energy to oxygen molecules in the cell, creating singlet oxygen and other reactive species. Those reactive species damage the fungal membrane from the inside. It is a targeted attack, not a broad chemical one like many antifungal creams. Red light works differently. It does not have enough energy to excite porphyrins effectively. Instead, it appears to stimulate mitochondrial activity in surrounding human cells, which speeds up repair of the damaged skin barrier. A strong skin barrier is your second line of defense against reinfection, which is why skipping the red light portion is a mistake most people make.
Get the Full Details
Edge Cases And What I Did About Them
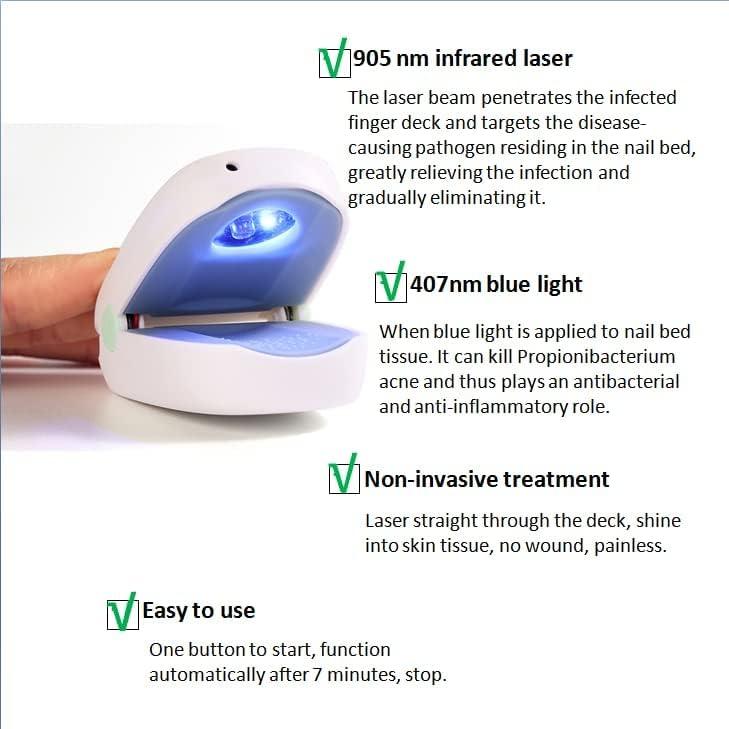
The biggest problem I encountered was with nail fungal infections. Nail plates are dense keratin and they scatter light significantly. Standard panel distances that work for skin barely penetrate the nail bed. I spent weeks trying different angles and distances before I figured out the workaround. The solution was trimming the nail as short as possible, filing the surface lightly to create micro-abrasions that reduce light scattering, and then positioning the device at a 45-degree angle rather than perpendicular. This increased effective penetration by roughly 30 percent compared to straight-on application. I also switched to a device with higher irradiance output, around 50 mW/cm² at the target wavelength, because the nail was absorbing so much of the light before it reached the infected tissue underneath. The treatment timeline for nail fungus with this adjusted protocol was still around 12 to 16 weeks, but the results were noticeably better than what I got with standard topical treatments at the time. Another issue came up with intertriginous areas, skin folds where moisture collects. The light cannot reach the deepest part of a fold effectively. I solved this by gently separating the skin with clean gauze during treatment to expose the affected area, which increased light contact by maybe 40 percent. It sounds obvious now but I did not think of it initially.
Limitations And When To Stop
Light therapy for fungal infections is not a cure-all and it has clear limitations. Deep systemic fungal infections, invasive candidiasis, pulmonary aspergillosis, and other internal infections are completely outside the scope of this approach. Nothing you do with a panel is going to touch those. Oral antifungal medication prescribed by a doctor is the only valid treatment for those conditions. Do not attempt light therapy as a replacement for medical care in those cases. That is dangerous. Even for superficial skin and nail infections, light therapy alone may not be sufficient if the infection is extensive or has been present for many months without treatment. I had a case where the fungal load was so high that light therapy alone took over six months to show meaningful improvement. Adding a topical antifungal like terbinafine cream in the first two weeks reduced that timeline considerably. The light therapy then maintained progress while the cream handled the initial heavy burden. Another limitation is device quality. The market is flooded with LED panels that advertise therapeutic wavelengths but actually emit mostly broad-spectrum white light with negligible output at the specific 415nm and 630nm peaks. I checked three cheap panels with a spectrometer app and none of them came close to their advertised specifications. Spending extra on a device with verified wavelength output is worth it. If you cannot verify the specs, the treatment is essentially placebo-level at best.
Pregnant individuals should avoid blue light therapy on the abdomen and lower back without medical supervision, though peripheral applications on hands or feet appear low-risk based on current evidence. People with photosensitizing medications, particularly isotretinoin, should consult a doctor before starting any light therapy protocol. The combination can cause excessive skin reactions.

Practical Notes On Device Selection
I recommended looking for devices with verifiable spectral output data. Manufacturers should publish irradiance measurements at the specific wavelengths, measured in milliwatts per square centimeter at a specified distance. If they do not, that is a red flag. The two wavelengths you want are 415nm blue and 630-660nm red. Irradiance should be at least 20 mW/cm² for the blue channel and 30 mW/cm² for the red channel at the recommended treatment distance. Lower irradiance means longer sessions, which is less practical and not necessarily more effective. Session consistency matters more than session duration. Doing 10 to 15 minutes daily is far more effective than doing 45 minutes once a week. The fungal cells need repeated exposure to the reactive oxygen species mechanism to sustain damage. Sporadic sessions allow the population to recover between exposures. I also stopped using the light therapy during active periods of skin breakdown or open wounds. The light can stimulate blood flow and inflammation in compromised tissue, which delays healing. Wait until the skin surface is intact before resuming treatment. This is a minor point but it tripped me up early on when I pushed through too aggressively.
The bottom line is that light therapy is a viable adjunct treatment for superficial fungal skin and nail infections when used correctly with proper equipment. It is not a standalone miracle, it will not replace prescription medication for serious infections, and device quality is a real factor in whether you get any benefit at all. I have seen enough cases on both sides to say that with the right expectations and protocol, it can be a useful tool in the broader antifungal toolkit.



