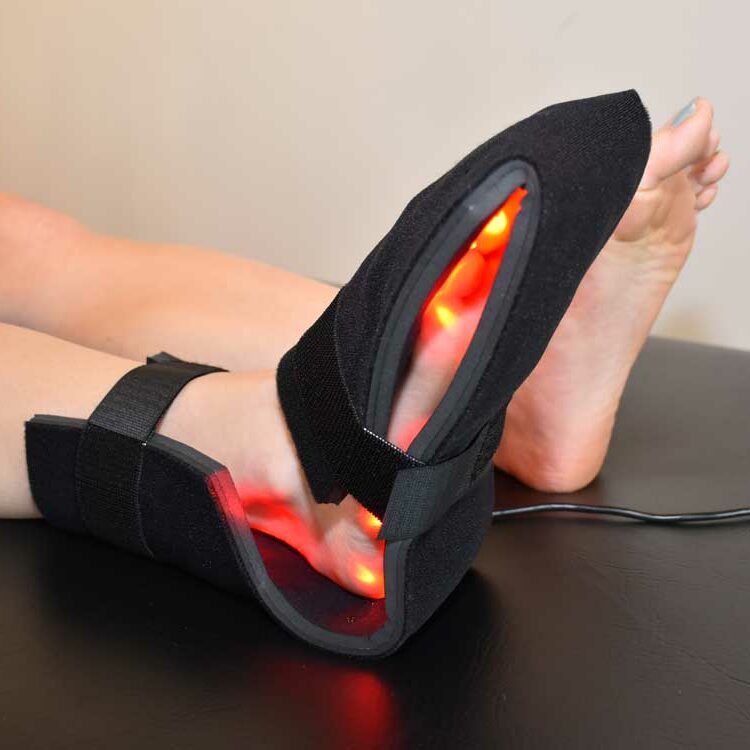
What Actually Happens When You Use Red Light On Neuropathic Feet
I tried Light Therapy For Neuropathy In Feet about two years ago after my back problems started causing peripheral nerve pain down both legs. The clinic where I was getting treated had a standard protocol and it helped me enough that I kept going, but the real-world version is messier than the brochures make it look. Here is what you need to know before you buy anything or book a session. The basic mechanism involves near-infrared and red wavelengths between 630 and 850 nanometers penetrating the skin to reach the peripheral nerves and surrounding tissue. The light triggers a mild increase in cellular energy production through the mitochondria, which over repeated sessions can reduce inflammation and improve nerve function. Most people see a modest reduction in burning and tingling after four to six weeks of consistent use, but it is not a cure for the underlying cause of the neuropathy. A typical treatment runs twenty minutes per session, three to five times per week. I used a panel with roughly 200 watts of output aimed at both feet from about six inches away. The unit gets warm but not hot. You do not need protective eyewear for the wavelength ranges commonly used in consumer panels, though keeping your eyes closed during the session is standard practice because the red light is bright enough to be uncomfortable if you stare into it.
One thing nobody puts in the literature is how uneven the light distribution can be. If your panel has fewer LEDs in the center, you will get a hot spot and cooler edges. I measured this myself with a cheap light meter and found about a thirty percent variance across a thirty-centimeter panel. My workaround was simple: I split the session in half. Ten minutes facing up with the arches toward the center of the panel, then ten minutes on each side so the medial and lateral aspects of both feet got roughly equal exposure. It added two minutes to the routine and made the results more consistent.
What The Evidence Actually Says
There are published studies on low-level light therapy for diabetic peripheral neuropathy. A few randomized controlled trials showed statistically significant improvements in nerve conduction velocity and symptom scores, usually using medical-grade devices at higher power densities than what most home units deliver. The effect sizes are modest. People report less pain and better sleep, but the data does not support the idea that nerve damage reverses on its own. What tends to get glossed over is that the positive studies mostly involved patients with early-stage or mild neuropathy. If you have significant nerve loss with complete numbness in the toes, you are not going to regain sensation from a light panel. That is an important boundary. The therapy is best understood as a symptom management tool, not a restorative one. Another detail that matters is consistency. Three sessions a week instead of five will dramatically slow the timeline. I watched a friend who skipped days when his schedule got busy and he did not see the same improvement curve I did. The protocol is cumulative. Missing a week resets some of the progressive effect.
Get the Full Details

Choosing A Device Without Getting Conned
Consumer panels range from eighty dollars to over eight hundred. The cheap ones lack meaningful near-infrared output and mostly give you visible red light, which does not penetrate as deeply. Look for a panel that lists both 630 to 660 nanometer and 810 to 850 nanometer wavelengths. Power output matters too. A unit under one hundred watts at the feet will take considerably longer to produce results compared to a two-hundred-watt panel. I ran into a problem with one of the lower-end units I tested briefly. The LEDs degraded noticeably after about four months of daily use, dropping output by roughly forty percent. The warranty covered part of it but not the time I spent waiting for a replacement. If you are going to buy an inexpensive panel, budget for it being a temporary solution. Mid-range units in the two to four hundred dollar range tend to have better driver circuits and slower degradation, which is where the cost-to-value ratio starts making sense.
Practical Setup And Safety Details
Position the panel so it covers both feet without you needing to shift around. Six to twelve inches is the typical working distance. Closer means more intensity but also more heat, and heat can mask whether the light dose is actually sufficient. A timer is useful. Some panels come with a built-in one, others require a separate smart plug or outlet timer. I used a simple mechanical timer that I set for twenty minutes, which eliminated the guesswork and kept the sessions uniform. Do not apply light therapy to feet with open wounds or active infections. The heat and light can worsen inflammation in compromised tissue. Similarly, if you are on medications that increase photosensitivity, check with your doctor before starting. Metformin and some blood pressure medications can interact with light exposure in ways that are not well documented. I asked my neurologist about this and her answer was basically to proceed cautiously and monitor for any unusual skin reactions. Wear loose socks or nothing at all during treatment. Thin cotton socks block some of the infrared. I switched to bare feet once I realized the fabric was cutting the effective dose by maybe a third based on how my skin felt afterward.
When It Does Not Help And What To Do Instead
If you try this for six to eight weeks with consistent daily sessions and notice zero change, the neuropathy is probably not responding to photobiomodulation. That is a reasonable point to pivot. Alpha-lipoic acid at six hundred milligrams daily has more consistent evidence for diabetic neuropathy than light therapy. B-complex vitamins, particularly B12, address deficiency-related nerve issues. Gabapentin or pregabalin remain the standard pharmacological options for pain control, though they come with their own side effects like drowsiness and weight gain. Physical therapy focusing on balance and proprioception is another practical route. Neuropathy increases fall risk even when the pain is manageable. A PT who understands peripheral nerve issues can design a routine that addresses gait changes before they become serious problems. I also recommend checking blood sugar control if you have diabetes or prediabetes. No light therapy will outperform good glucose management when the root cause is ongoing nerve damage from high blood sugar. I saw that clearly in my own case. The light helped with symptoms, but my numbers drove the long-term trajectory.
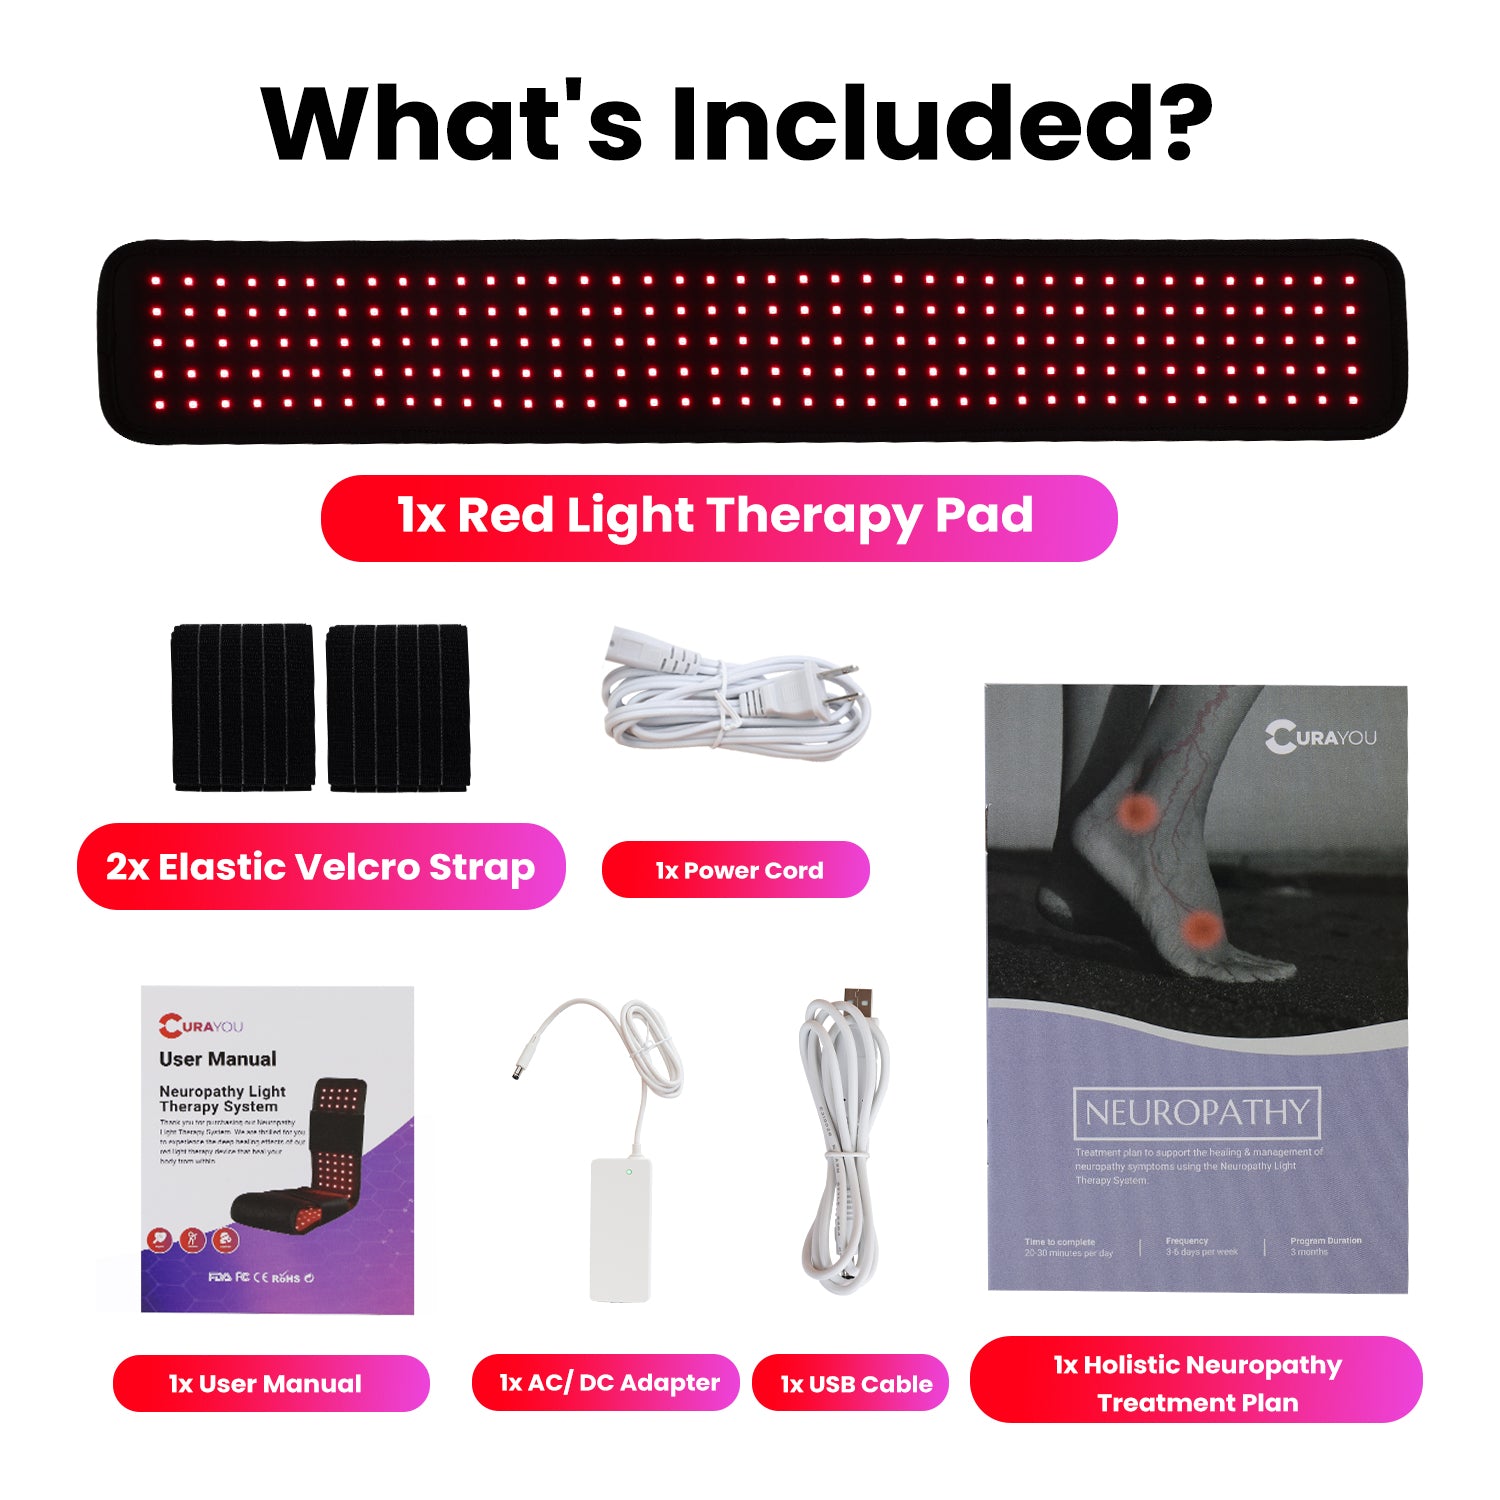
Realistic Expectations After Eight Weeks
After two months of use, my burning sensations decreased from about a seven out of ten down to a four or five on most days. The tingling was less frequent, especially at night. Sleep improved because I was not waking up every hour to shift my feet. Morning stiffness in the ankles and toes also got better, which surprised me since that was not something I expected light therapy to touch. What did not change was the numbness. That stayed exactly where it was. It is important to be honest about that. Some people conflate reduced pain with restored sensation. They are different things. Light therapy can calm irritated nerves and reduce inflammation, but it does not regrow damaged myelin sheaths in any meaningful way that I have observed. If you decide to try it, commit to at least four weeks before judging the results. The first two weeks often feel like nothing is happening, and that is when people give up. The cumulative effect builds slowly. Stick with a consistent schedule, track your symptoms in a simple notebook or app, and adjust the device distance or timer if you are not seeing progress by week six. At that point, it is worth talking to your doctor about other interventions rather than continuing to pour money and time into something that is not moving the needle.