Understanding CSF Circulation Through The CNS Ventricular System
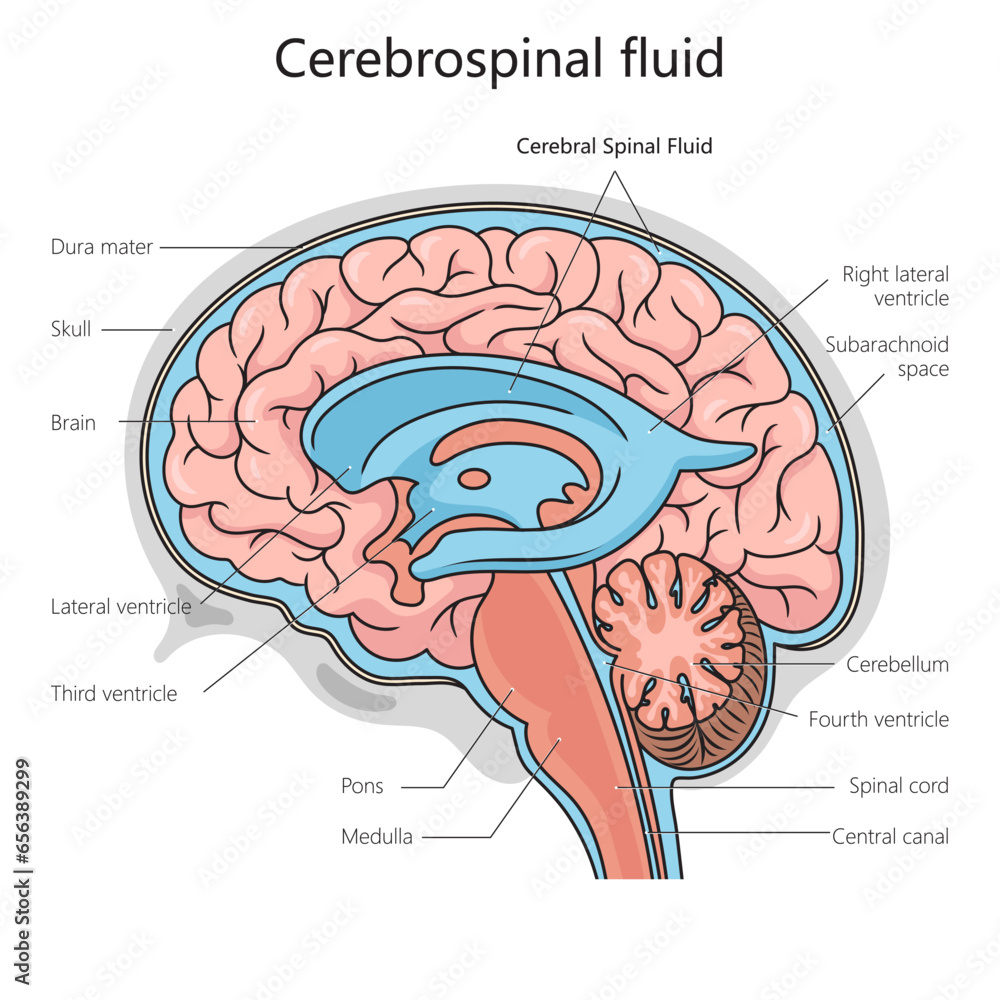
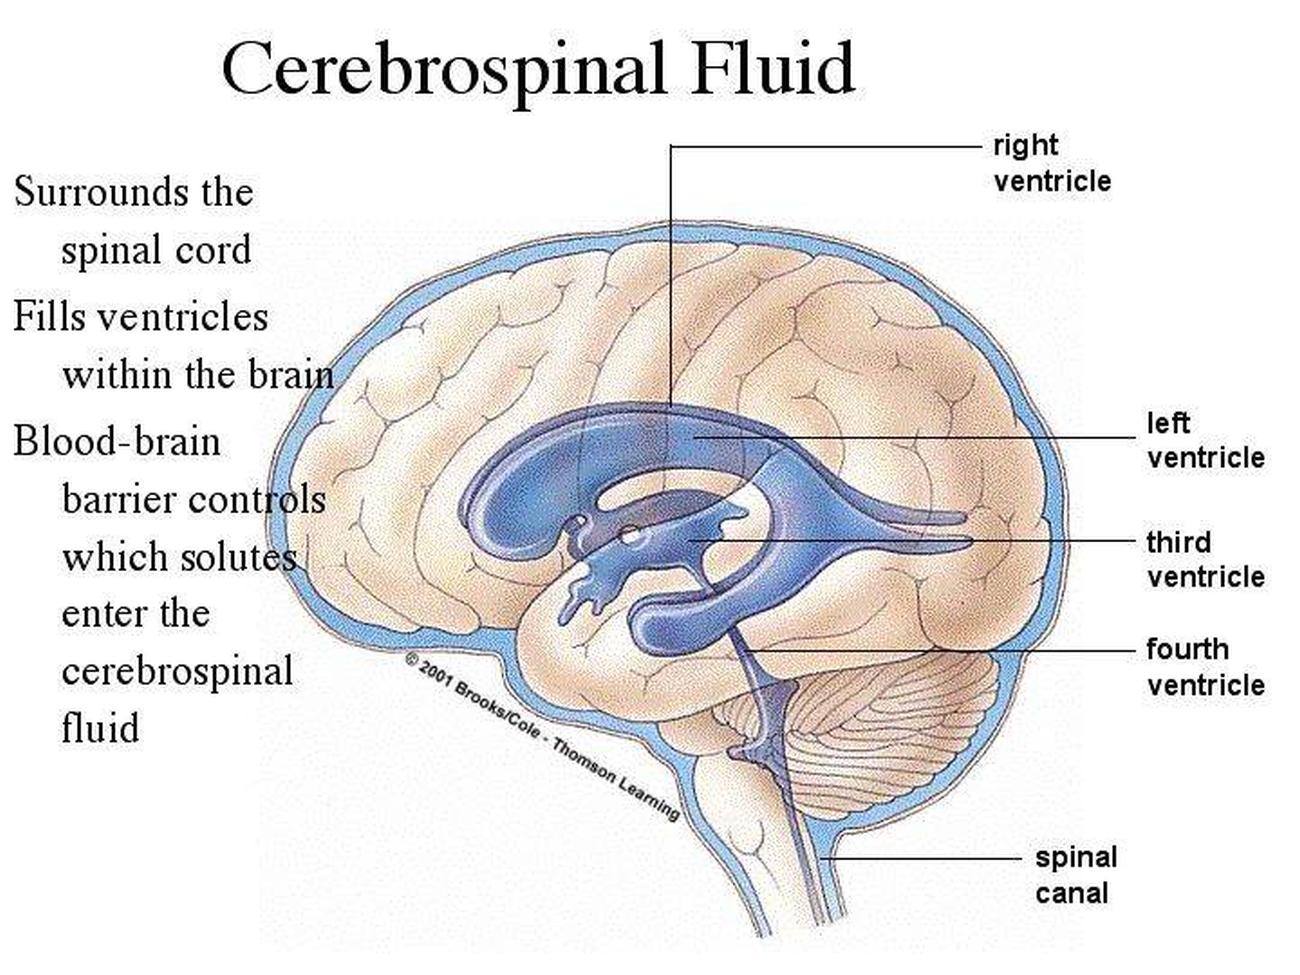
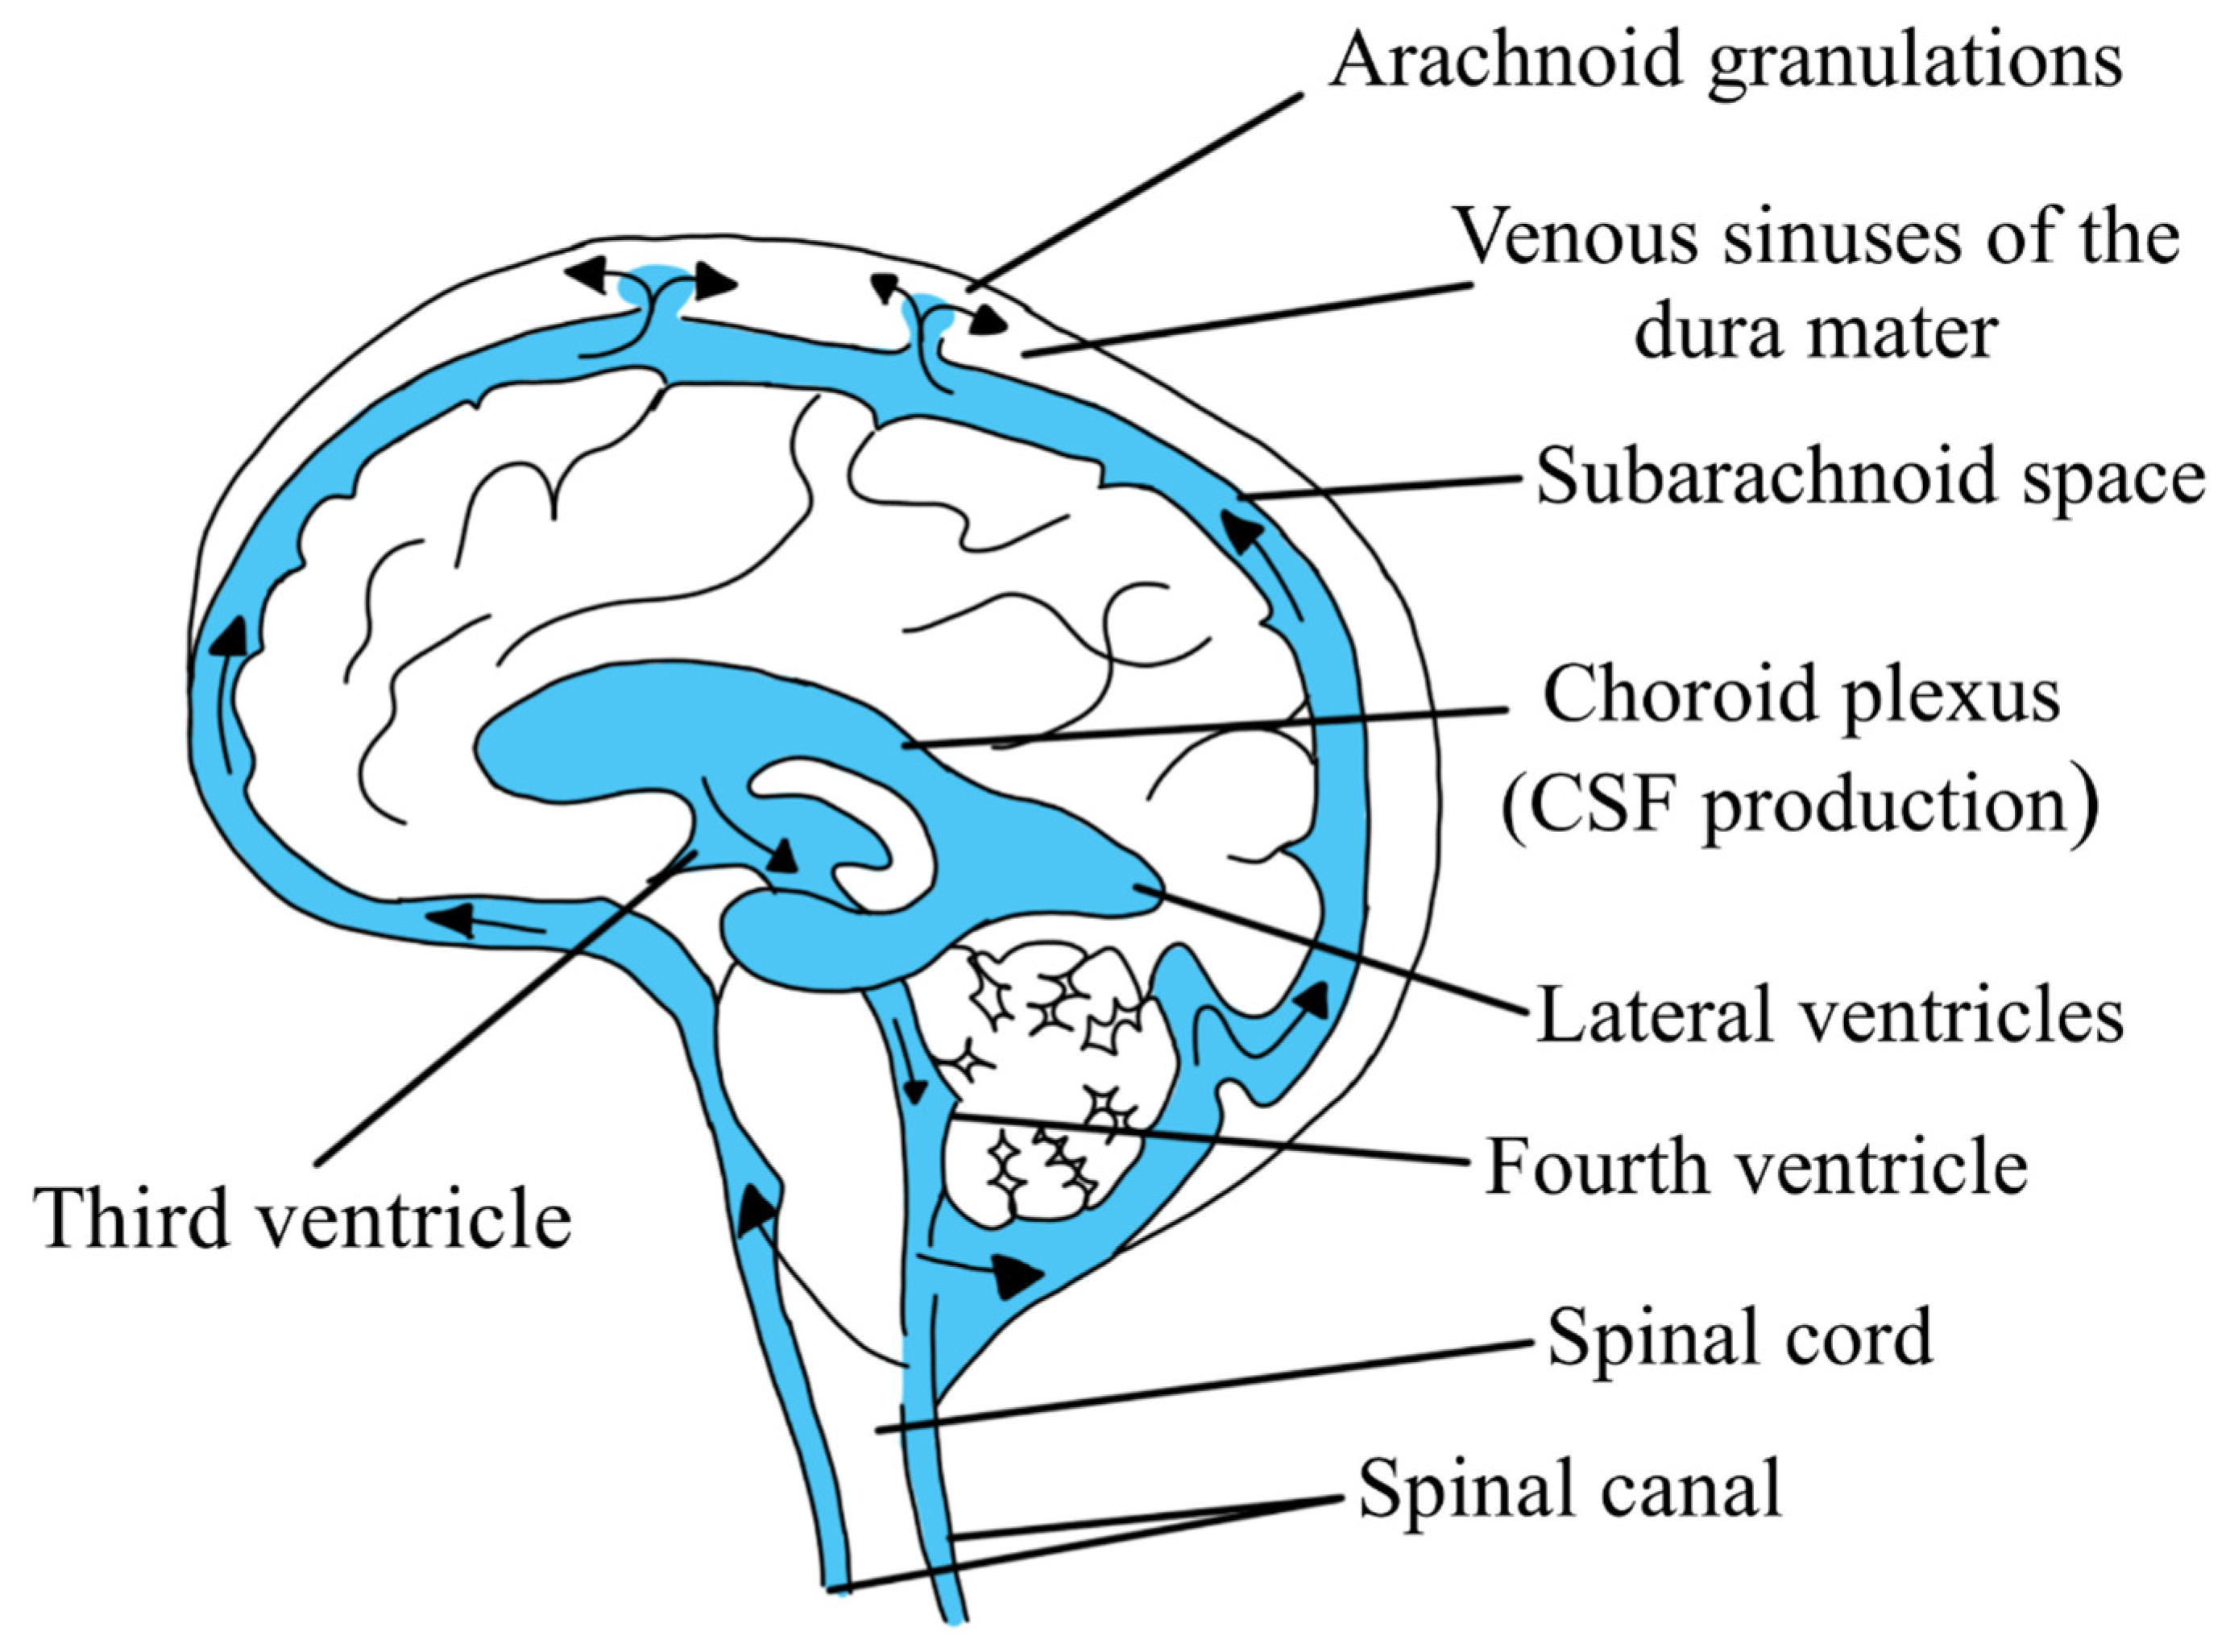
The brain makes its own plumbing, and most of it happens inside a series of interconnected cavities called the ventricular system. These cavities produce, carry, and drain cerebrospinal fluid, which floats the brain, cushions it, and flushes waste. When you study the lines the cns cavities and circulates cerebrospinal fluid, you are looking at a closed loop that operates under low pressure and depends on a few narrow bottlenecks to function properly. Choroid plexus tissue lines the lateral ventricles, the third ventricle, and the fourth ventricle. It is where CSF gets made. Each lateral ventricle contains a choroid plexus through the body and the atrium, with a small portion extending into the inferior horn. The third ventricle has a paired choroid plexus along its superior margin. The fourth ventricle has a more complex setup with the tela choroidea folding inward to form plexus tissue on both lateral recesses. The typical adult produces around 500 milliliters of CSF per day, which means the entire 150-milliliter volume turns over roughly three times daily. Choroid plexus cells use active transport to move sodium and chloride into the ventricular space, and water follows osmotically. This is not a simple filtration process. The blood-cerebrospinal fluid barrier formed by tight junctions between those epithelial cells is what keeps the composition stable. You can damage that barrier with systemic inflammation or certain infections, and the protein content of the CSF will spike as a result.
The Flow Path
Fluid moves from each lateral ventricle through the interventricular foramen, also called the foramen of Monro, into the third ventricle. From there it passes through the cerebral aqueduct, the narrow channel of Sylvius, into the fourth ventricle. The aqueduct is about 2 millimeters wide and maybe 15 to 18 millimeters long in an adult. It is easily compressed or obstructed. From the fourth ventricle, CSF exits through three openings: the median aperture, or foramen of Magendie, and the two lateral apertures, or foramina of Luschka. Once those apertures are cleared, the fluid enters the subarachnoid space. It bathes the external surface of the brain and spinal cord, then travels upward along the convexity of the brain toward the superior sagittal sinus. Absorption happens primarily through arachnoid granulations, which protrude into the dural venous sinus and act as one-way valves. When ventricular pressure exceeds venous pressure, fluid gets pushed through the granulations into the bloodstream. At normal intracranial pressures, the majority of CSF absorption occurs through these structures, though there is growing evidence that some drainage also goes through olfactory nerve pathways and along perivascular spaces.
A Practical Problem I Encountered
I once worked with a case involving an adult patient who presented with progressive headache and mild gait disturbance. Imaging showed lateral ventricle enlargement out of proportion to the third and fourth ventricles, which pointed directly to obstruction at the level of the foramen of Monro. The challenge was that the obstruction was subtle on standard T1 and T2 sequences. I switched to cine phase-contrast MRI flowing through the aqueduct and could actually see the signal void disappear at the foramen due to the blockage. That imaging approach made the difference between ordering an unnecessary lumbar puncture and going straight to endoscopic third ventriculostomy planning. The key takeaway here is that not all obstructive hydrocephalus presents with uniform ventricular enlargement. When the lateral ventricles are disproportionately large compared to the rest of the system, you should suspect a unilateral or bilateral foramen of Monro issue rather than assuming generalized blockage. Standard radiology reads sometimes miss this because they focus on overall ventricular size instead of the relative proportions.
Get the Full Details

Counter-Intuitive Points Beginners Miss
One thing that consistently trips people up is the assumption that CSF production is constant. It is not. Production actually decreases when intracranial pressure rises significantly above normal levels. The choroid plexus responds to increased pressure by reducing secretion rate, which is partly why mild to moderate increases in intracranial pressure do not immediately cause dangerous fluid accumulation. The system has built-in feedback. Another misconception is that the arachnoid granulations are the only absorption route. They dominate under normal physiological conditions, but when intracranial pressure climbs into the pathological range, granulations can become less efficient or even reverse flow temporarily. In those situations, alternative drainage pathways through cervical lymphatics and perineural routes become clinically relevant. This matters when you are managing a patient with obstructive hydrocephalus who is not responding to standard shunt placement because the absorption capacity through granulations is already maxed out.
Where The System Fails
Obstructive hydrocephalus happens when any part of the pathway from the lateral ventricles to the subarachnoid space gets blocked. Aqueductal stenosis is the most common single-level obstruction in adults and can be congenital or acquired from prior hemorrhage or infection. The fourth ventricle outlets can be blocked by tumors, arachnoid scarring, or post-meningitic adhesions. The clinical presentation varies depending on where the blockage sits, but the underlying mechanism is always the same: fluid backs up behind the obstruction and dilates the upstream cavities. Communicating hydrocephalus is a different problem entirely. The pathways are open, but absorption is impaired. This commonly follows subarachnoid hemorrhage, bacterial meningitis, or chronic alcoholism. In these cases, placing a shunt to divert fluid into the peritoneal cavity is the standard approach, but shunt failure rates are significant. About 30 to 40 percent of pediatric shunts require revision within the first two years. Adults fare slightly better but still experience meaningful complication rates from overdrainage, underdrainage, or infection. If shunt dependency is a concern, endoscopic third ventriculostomy offers an alternative for certain types of obstructive hydrocephalus. A small opening is made in the floor of the third ventricle, allowing CSF to bypass the obstruction and drain directly into the prepontine cistern. This avoids implanted hardware and eliminates shunt-related complications, but it is not suitable for communicating hydrocephalus or cases where the subarachnoid space itself is scarred. The success rate drops considerably if the cisternal absorption pathways are compromised.
Practical Notes On Imaging And Assessment
When evaluating the ventricular system, axial CT is fast and readily available, but it underestimates the extent of periventricular edema that accompanies chronic obstruction. FLAIR MRI sequences show the subependymal interstitial edema much more clearly, which correlates better with symptoms and helps guide the urgency of intervention. If you are working with a patient who has borderline ventricular enlargement on CT but normal cognition and gait, do not rush to surgery. Track the Evans index over time. An index above 0.3 suggests significant enlargement, but the trajectory matters more than a single measurement. For understanding actual flow dynamics, cine phase-contrast MRI remains the most useful tool. It quantifies flow volume through the aqueduct and can reveal abnormal bidirectional flow patterns that indicate early obstruction even before ventricular enlargement becomes obvious. I rely on this sequence whenever standard imaging is equivocal and the clinical picture does not fully align with the radiological findings.
Why This All Matters In Practice
The ventricular system is not just an anatomical curiosity. It is a functional network that maintains brain homeostasis, and disruptions to it have cascading effects. Glymphatic clearance, which removes metabolic waste including beta-amyloid, depends on proper CSF movement through perivascular spaces. Impaired flow correlates with increased risk of neurodegenerative conditions. The anatomy you learn in textbooks translates directly into clinical decision-making when a patient presents with unexplained headache, cognitive decline, or gait disturbance. Knowing which bottleneck to look for and which imaging sequence will actually show you the problem is what separates a careful evaluation from a missed diagnosis.