ACE Inhibitors: The Practical List and What Actually Matters
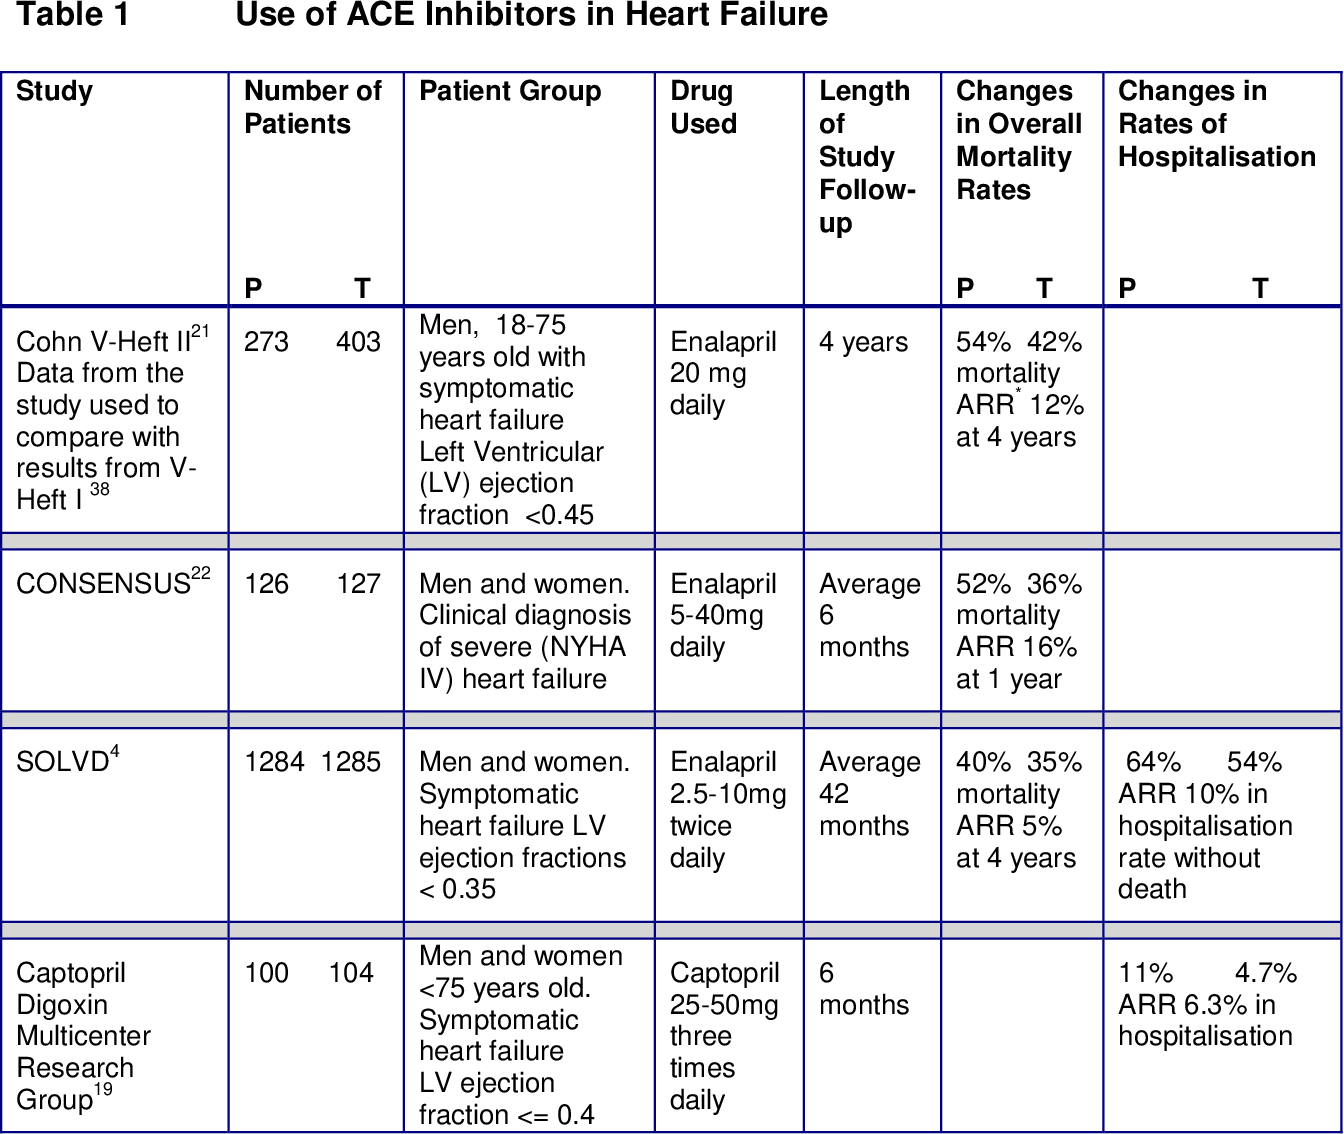
Angiotensin-converting enzyme inhibitors are one of those drug classes everyone learns about in med school but only really understands after watching a few patients react to them. They block the conversion of angiotensin I to angiotensin II, which drops blood pressure, reduces afterload, and slows the progression of kidney damage in diabetic patients. That's the textbook version. The version that matters is longer. Here's the working list most clinicians actually use in practice: Captopril — the original. Short-acting, TID dosing, sulfhydryl group (which relates to the taste disturbance and rash some patients report). Rarely first-line anymore because of the dosing frequency, but useful in acute settings where you need rapid on/off control.
Lisinopril — hydrophilic, renally excreted unchanged, once-daily dosing. This is probably the most commonly prescribed ACE inhibitor in the US right now. No hepatic activation needed. Dose adjustment required in renal impairment. Enalapril — prodrug converted to enalaprilat in the liver. Twice-daily dosing usually. Enalaprilat is the active form and comes IV for hypertensive emergencies when oral administration isn't possible. Ramipril — once-daily, dual renal and hepatic elimination. The HOPE trial gave this drug a lot of its reputation for cardiovascular risk reduction beyond just blood pressure lowering. Often the go-to when there's established coronary disease.
Benzacepril — once-daily, prodrug. Less commonly used now but still in the formulary. Dual biliary and renal excretion means less dosing adjustment in isolated renal impairment compared to lisinopril. Quinapril — prodrug, once or twice daily depending on indication. Moderate hepatic activation. Not much different clinically from the others in this class. Fosinopril — prodrug with dual hepatic and renal clearance. Useful in patients with moderate renal dysfunction because you don't have to adjust the dose as aggressively. That said, you still monitor creatinine.
Get the Full Details

Trandolapril — once-daily, post-MI and heart failure evidence base. More commonly used in Europe than the US. Perindopril — once-daily, prodrug. Strong evidence in the EUROPA and ASCOT trials for cardiovascular outcomes. Available in the US but not as widely prescribed as lisinopril or ramipril. Molindipril — long-acting, once-daily. Available in some markets, less so in others.
How These Actually Behave in Patients
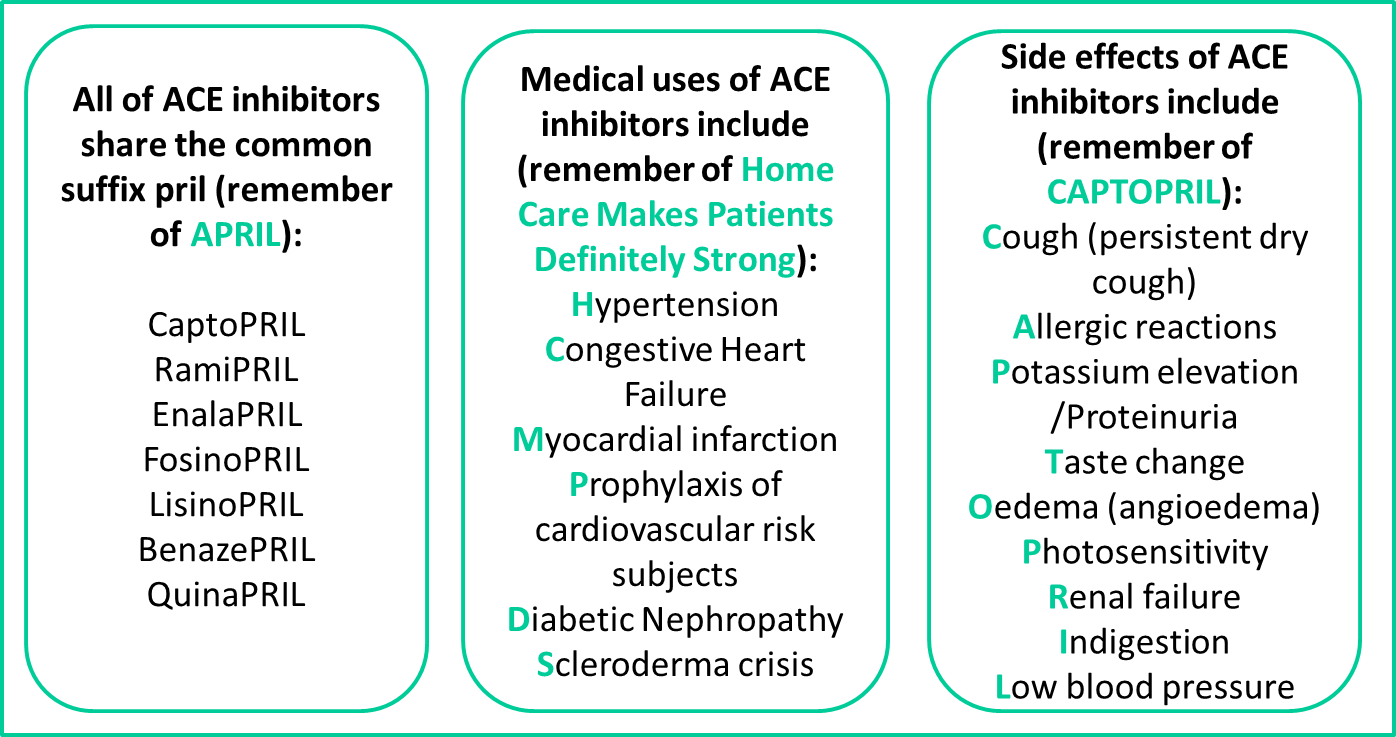
The thing about ACE inhibitors that doesn't come through in the drug comparison tables is how much the individual patient's physiology changes which one works. I once had a patient on lisinopril 40mg daily whose creatinine jumped from 1.2 to 2.1 within two weeks. Switching to fosinopril 20mg daily brought the creatinine back down to 1.4 without losing blood pressure control. The dual-excretion pathway made the difference. That's not something you'd predict from the prescribing information alone. Another practical point: the dry cough. It happens in roughly 5 to 20 percent of patients depending on the study and the population. It's not an allergy. It's bradykinin accumulation in the respiratory tract — the same enzyme that makes angiotensin II also breaks down bradykinin, and when you block it, bradykinin builds up. Some patients switch to an ARB and the cough disappears within days. Others need to push through it for a couple weeks before it settles. There's no reliable predictor of who gets it, which is annoying. Angioedema is the rare but serious counterpart. About 0.1 to 0.5 percent of patients. It can happen on the first dose or after years of uneventful use. The lips, tongue, and airway swell. If a patient on an ACE inhibitor presents with breathing difficulty and facial swelling, stop the drug immediately and don't restart it. Cross-reactivity with ARBs is low but not zero, so monitor closely if you switch.
What the Guidelines Don't Emphasize Enough
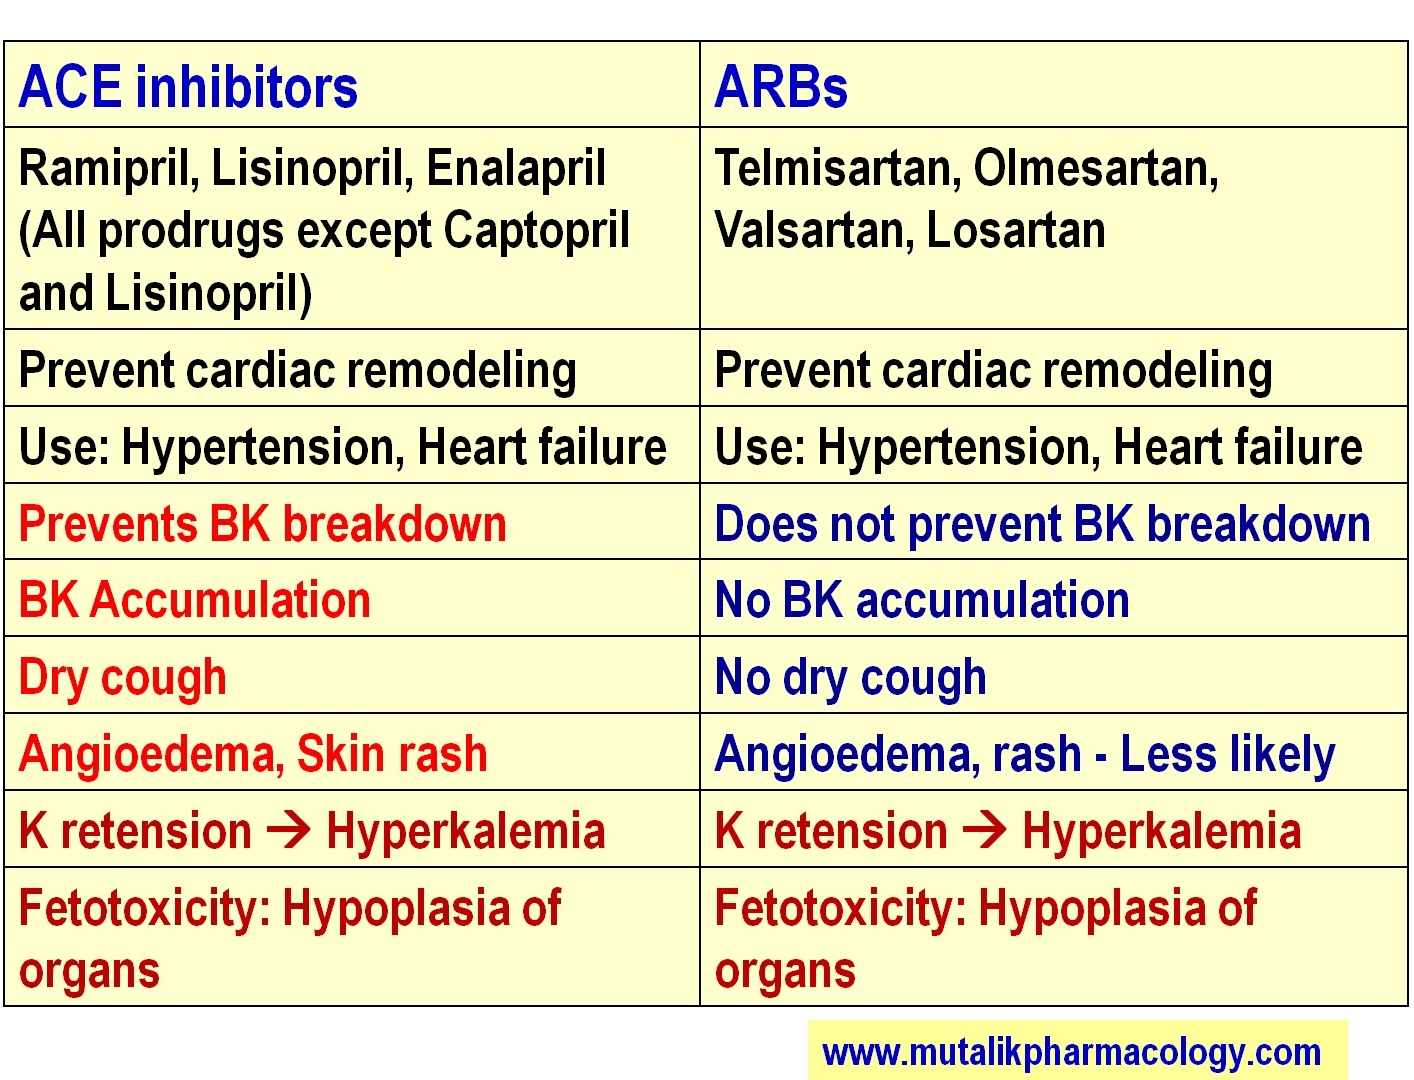
Kidney function monitoring is standard, but the timing matters more than people think. Check baseline creatinine and potassium, then recheck at one to two weeks after starting or dose escalation. A rise in creatinine of up to 30 percent from baseline is acceptable and expected. Beyond that, investigate — renal artery stenosis, dehydration, NSAID use, or concurrent potassium-sparing diuretics are the usual suspects. Potassium monitoring is equally important. ACE inhibitors reduce aldosterone, which means less potassium excretion. In patients with diabetes, chronic kidney disease, or those on spironolactone or trimethoprim, hyperkalemia can develop quietly. I've seen potassium levels climb to 6.0 in patients who were asymptomatic until they developed arrhythmias. Check potassium at the same visit as creatinine. There's a misconception that ACE inhibitors are inferior to ARBs. They're not. For hypertension, they're equivalent. For heart failure with reduced ejection fraction, both classes have outcome data. The choice often comes down to side effect profile, cost, and formulary availability. Lisinopril is available as a generic for pennies per tablet. Some of the newer agents in this class aren't on every formulary.
When ACE Inhibitors Don't Work
High-renin states respond best. Patients with volume-dependent hypertension — the elderly, those with salt sensitivity, chronic kidney disease with volume overload — often need a thiazide diuretic added before the ACE inhibitor reaches its full potential. The combination is synergistic: the diuretic raises renin, which makes the ACE inhibitor more effective, while the ACE inhibitor blunts the reflex tachycardia and potassium loss from the diuretic. Bilateral renal artery stenosis is a hard contraindication. Blocking angiotensin II in that setting removes the compensatory constriction of the efferent arteriole, and GFR collapses. Always ask about abdominal bruits and check a renal ultrasound if there's suspicion before starting, particularly in patients with flash pulmonary edema or unexplained renal failure. Pregnancy is another absolute. ACE inhibitors cause fetal renal dysgenesis, oligohydramnios, and skull hypoplasia. If a patient becomes pregnant, stop the medication immediately and switch to a pregnancy-safe alternative like labetalol or nifedipine.
A Note on Dosing Philosophy
Start low, go slow. This applies especially to elderly patients, those with pre-existing renal impairment, or patients on diuretics who may be volume-depleted. A typical starting dose for lisinopril is 2.5 to 5mg daily, not the 10mg or 20mg that some prescribers reach for out of habit. Titrate based on blood pressure response and renal function at two-week intervals. Most patients end up on 10 to 20mg daily, but some achieve control on 5mg. More isn't always better. The list above covers the agents you're likely to encounter. The ones that matter in practice are lisinopril, enalapril, and ramipril by prescription volume. The rest fill niche roles — fosinopril for renal impairment, captopril for acute situations, perindopril where outcome data drove formulary inclusion. Understanding why you'd pick one over the other matters more than memorizing the full roster.