Where The Kidneys Actually Sit
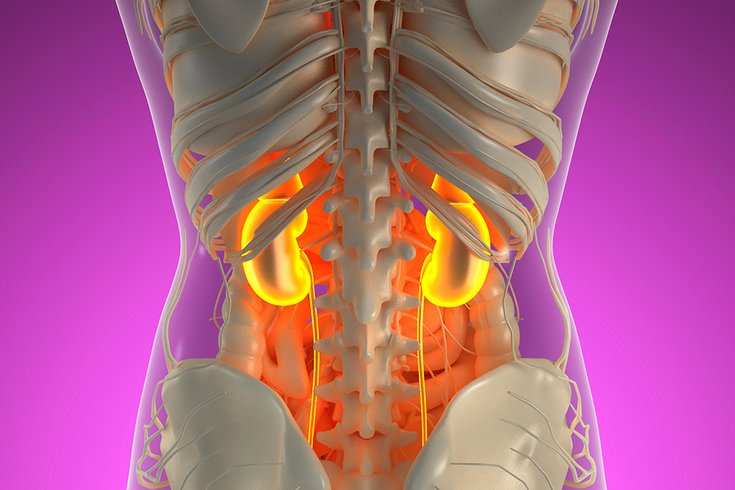
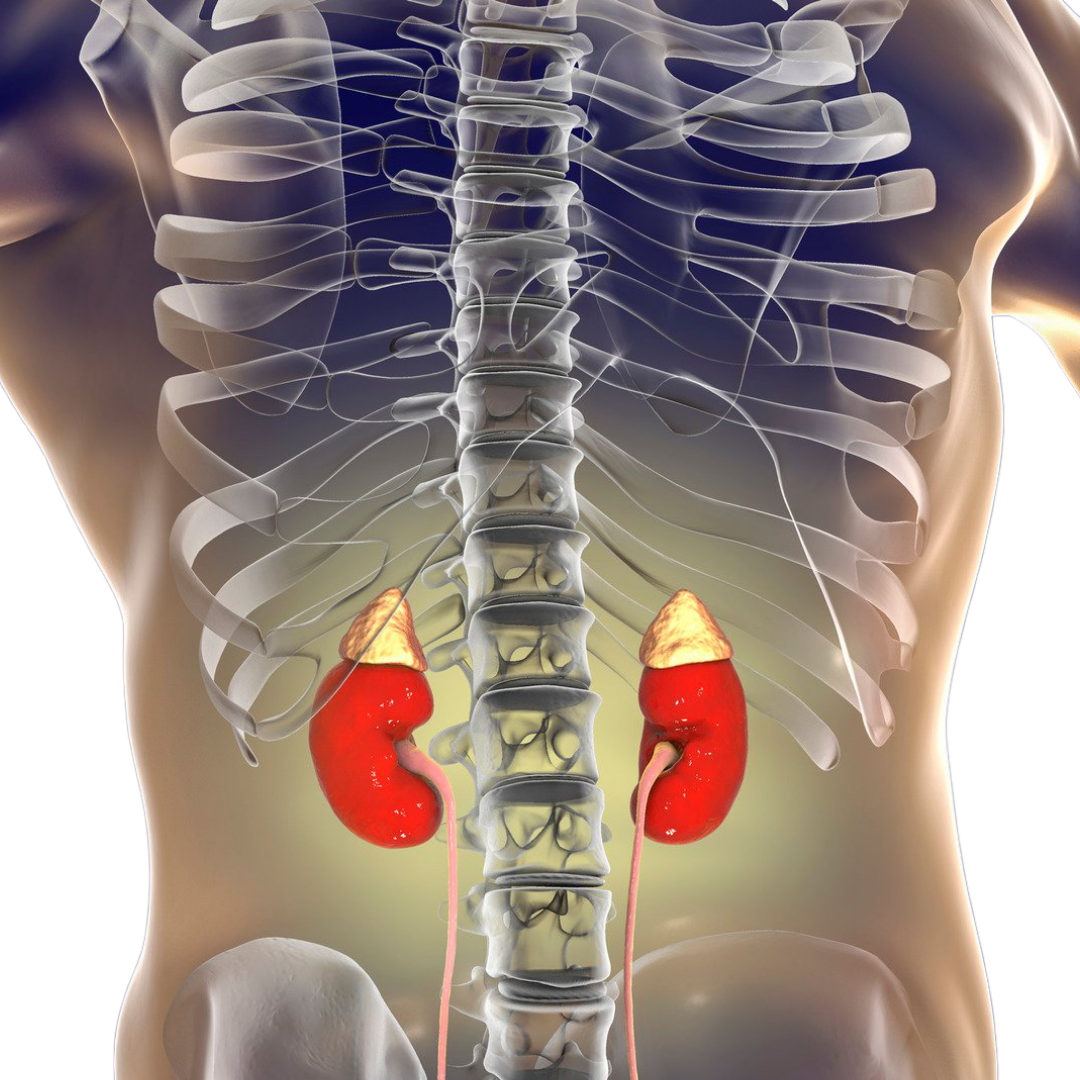
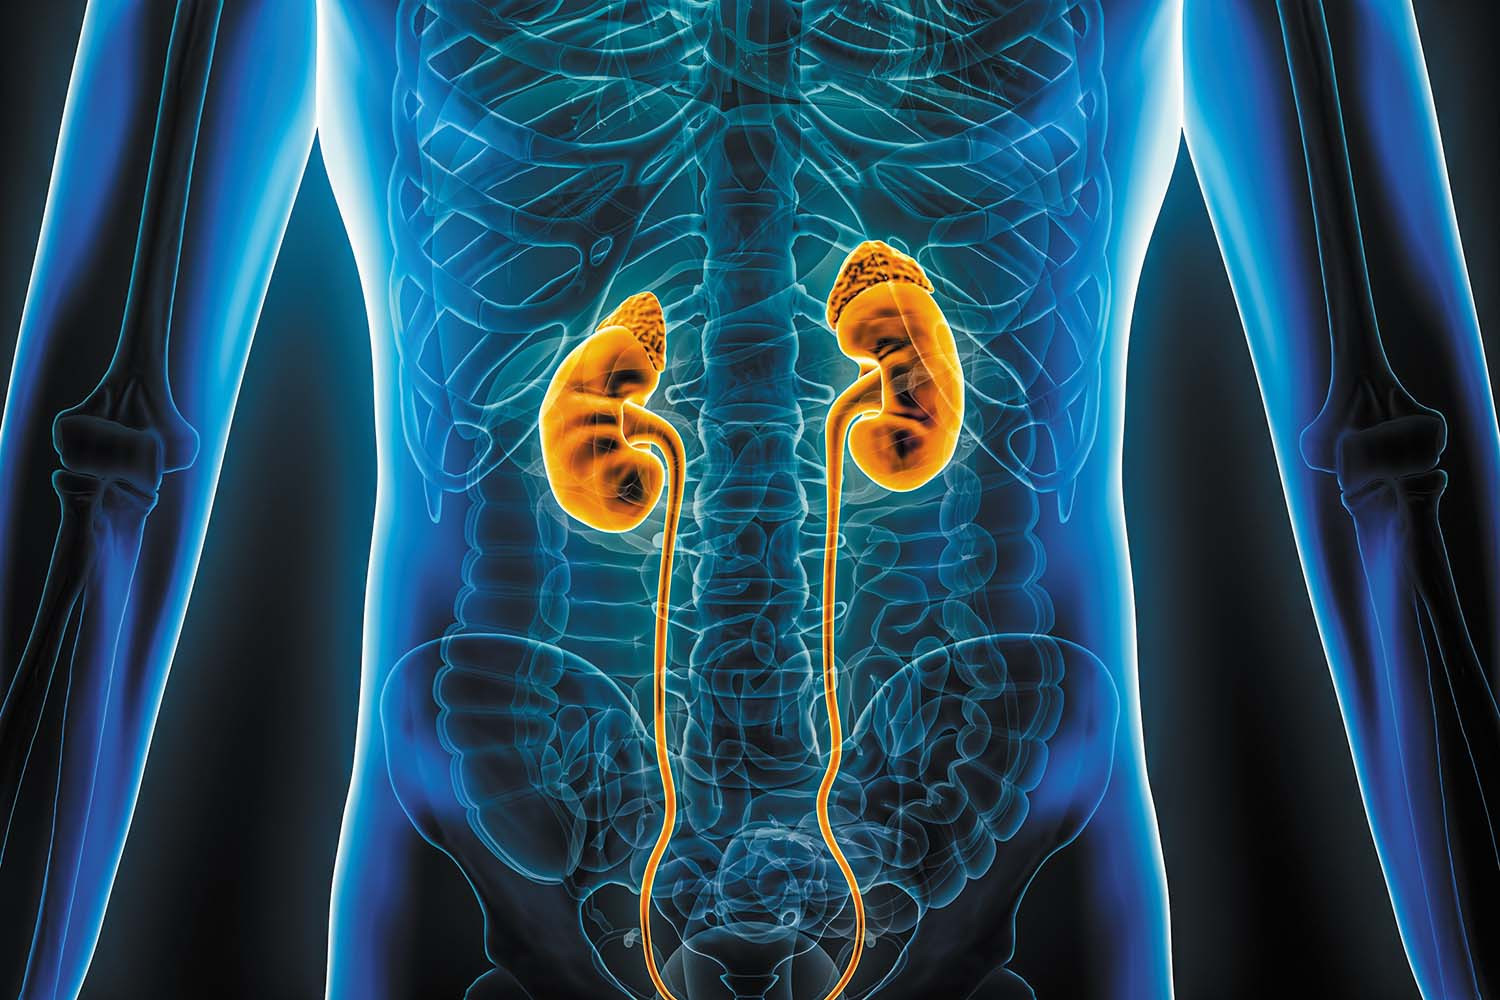
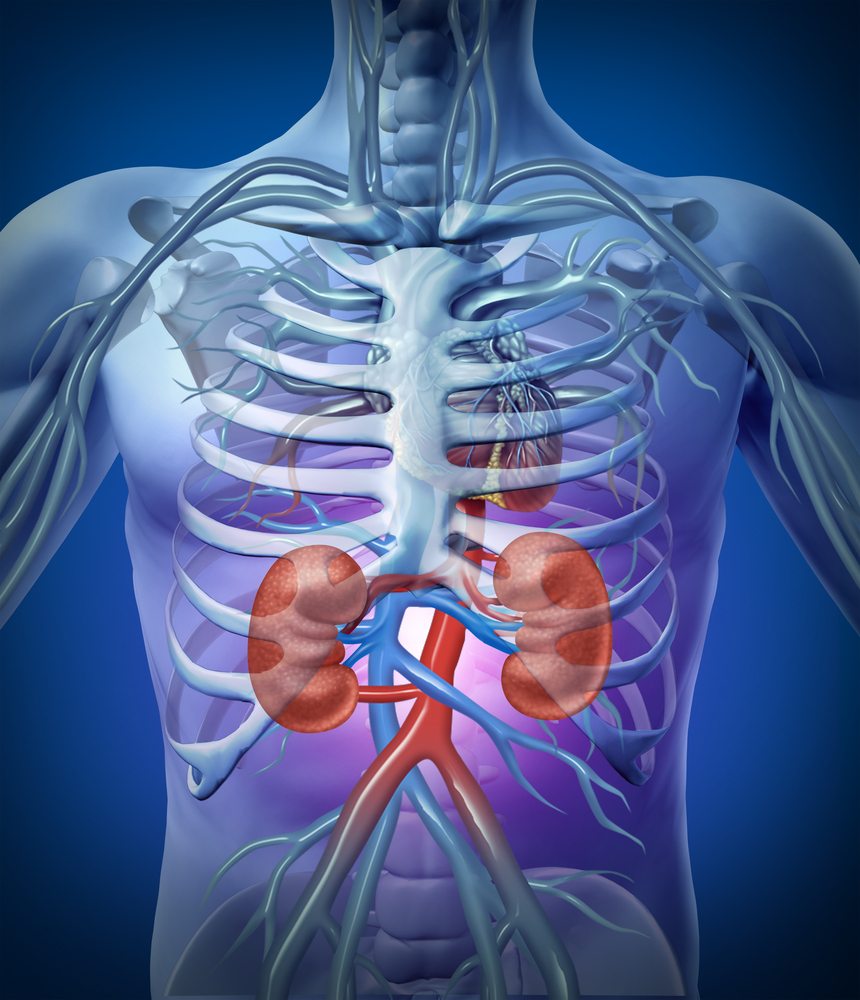
The kidneys sit retroperitoneally on either side of the spine, roughly between the T12 and L3 vertebrae. They are not in the front of your abdomen where most people assume. If you press along your lower rib cage from the side or back, the organ just behind that area is where they rest. The right kidney sits slightly lower than the left because the liver occupies space above it. This is standard anatomy, but the variations show up more often than you might expect when you are actually trying to locate them on a living person. When I first started working in clinical imaging, I made the mistake of searching too far anterior. I was scanning a patient for renal colic and kept coming up empty on the right side. The ultrasound technician beside me pointed out that I was looking at bowel loops and the inferior edge of the liver. The right kidney had slipped down into the pelvis during that scan because the patient was in a supine position with a very bulky abdomen. That taught me to track the IVC and aorta first, then work laterally. Once I shifted my approach, the kidney appeared consistently. It is the same principle regardless of whether you are palpating, scanning, or reviewing cross-sectional anatomy. Find the vascular landmarks, then move outward. The costal margin protects both kidneys to some degree, but the left kidney extends slightly higher, often reaching the level of the eleventh rib posteriorly. The right is usually around the twelfth rib or just below it. This asymmetry matters if you are studying radiological scans or attempting manual palpation. Both organs are bean-shaped and roughly the size of a fist, weighing about 120 to 170 grams each in adults. They sit in the pararenal fat, which gives them a degree of mobility. That mobility is useful during surgery but can be misleading on imaging if you are comparing a supine scan to an upright one.
In practice, the most reliable surface landmark is the tip of the twelfth rib. Draw an imaginary line horizontally from that tip toward the midline and you will pass directly over the upper pole of each kidney. This is not a perfect mapping tool, but it is accurate enough for rough clinical estimation. For precise localization, cross-sectional imaging remains the standard. A contrast-enhanced CT shows the kidneys clearly against the surrounding fat and muscle, while an ultrasound requires skill to navigate past the ribs and bowel gas. One detail that beginners often miss is the relationship to the psoas major muscle. Both kidneys lie anterior to the psoas, which runs vertically along the lumbar spine. This relationship holds even in cases of significant weight fluctuation. However, patients with severe cachexia or massive ascites can displace the kidneys anteriorly, making them more superficial and easier to palpate but also more vulnerable to trauma. I had a patient with advanced cirrhosis where the kidneys were surprisingly accessible on exam because the abdominal wall was distended but the organs themselves were pushed forward. It changed how I approached the physical examination for that individual. The innervation comes from the renal plexus, drawing fibers from T10 to L1. That is why kidney pain often presents as flank pain that can radiate to the groin. The referred pain pattern follows those same nerve roots. When a patient describes pain under the lower ribs that wraps around to the front, the source is frequently the kidney rather than a musculoskeletal issue. Mistaking renal colic for a muscle strain is one of the most common errors I see in urgent care settings, and it usually traces back to incomplete attention to the anatomical location.
There are known variants that complicate the standard picture. Horseshoe kidney occurs in roughly one in four hundred births, where the lower poles fuse across the midline. The fused organ sits lower than normal, often around L4, and the ureters must pass over the isthmus to reach the bladder. Another frequent variation is a duplicated collecting system, which can appear on imaging as two separate renal pelves on one side. These are usually asymptomatic but they change the surgical landscape completely. If you are planning a procedure near the kidney without acknowledging a variant, the consequences can be serious. For self-examination or general awareness, understanding this anatomy is useful, but it has clear limits. You cannot reliably determine kidney health through location alone. Conditions like polycystic kidney disease, renal tumors, and chronic kidney disease do not produce noticeable positional changes in the early stages. The organs stay in place while function deteriorates silently. Blood tests and urine analysis are the tools that actually detect those problems, not physical location assessment. Imaging confirms structural issues, but it requires trained interpretation. If you want to study this further, standard anatomical references like Gray's Anatomy or Netter's Atlas of Human Anatomy provide detailed illustrations. Online resources such as Radiopaedia offer extensive case libraries with CT and MRI correlations that show the kidneys in thousands of real clinical scenarios. The difference between textbook anatomy and live anatomy becomes apparent quickly once you start reviewing actual scan data. The fat planes, the fascial boundaries, and the relationship to adjacent structures are all visible in ways that diagrams simplify away.
Get the Full Details