Palpating the Axilla
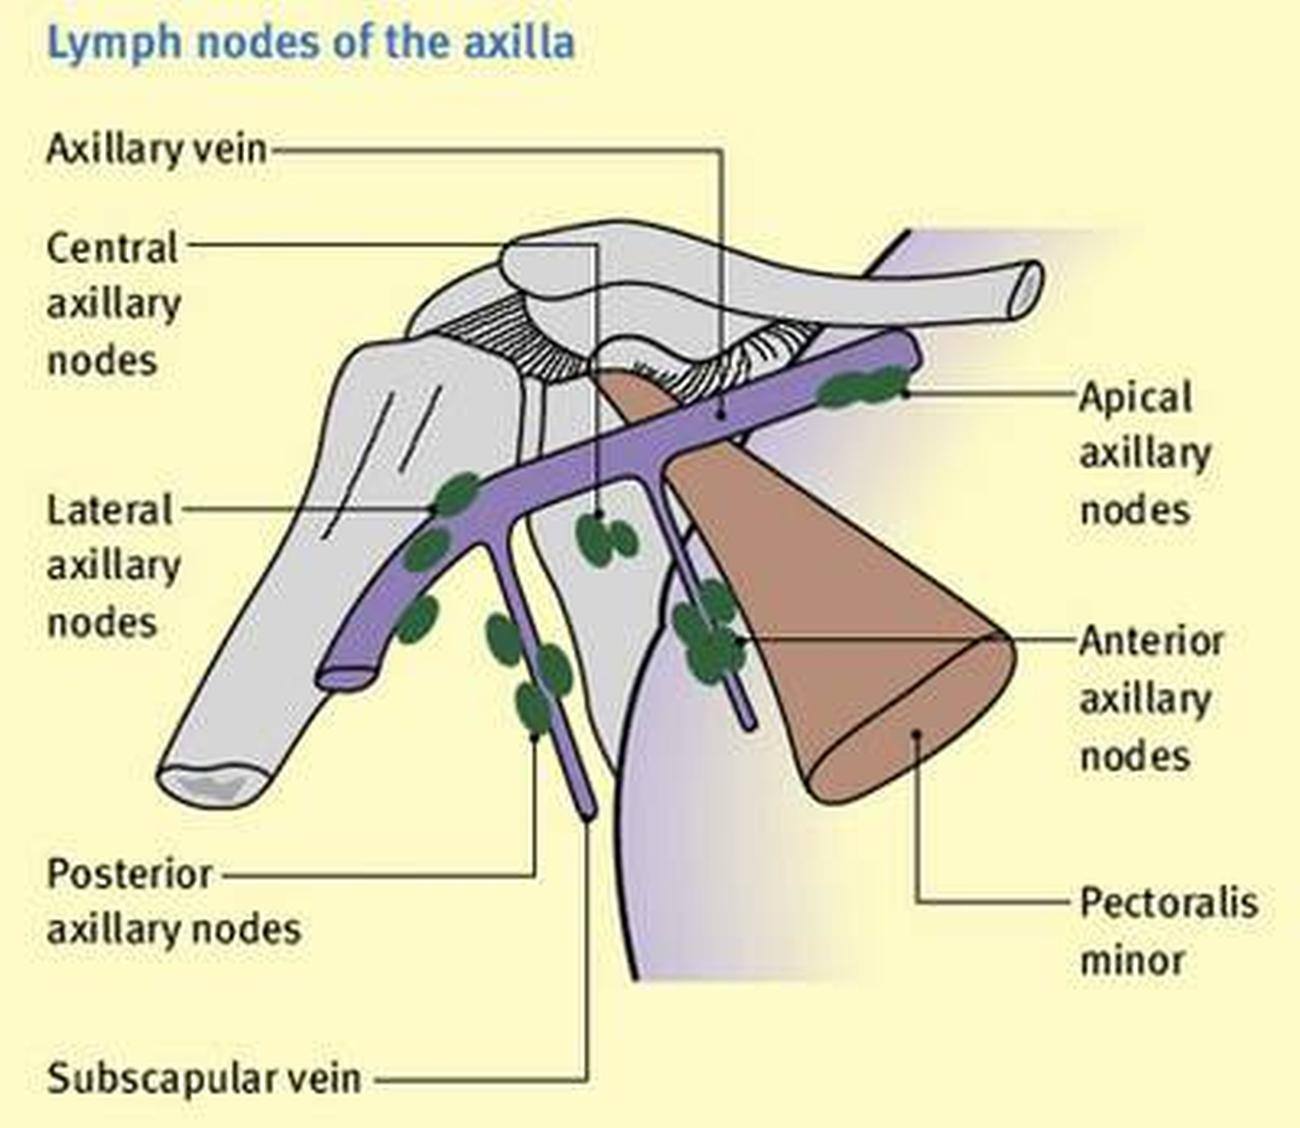
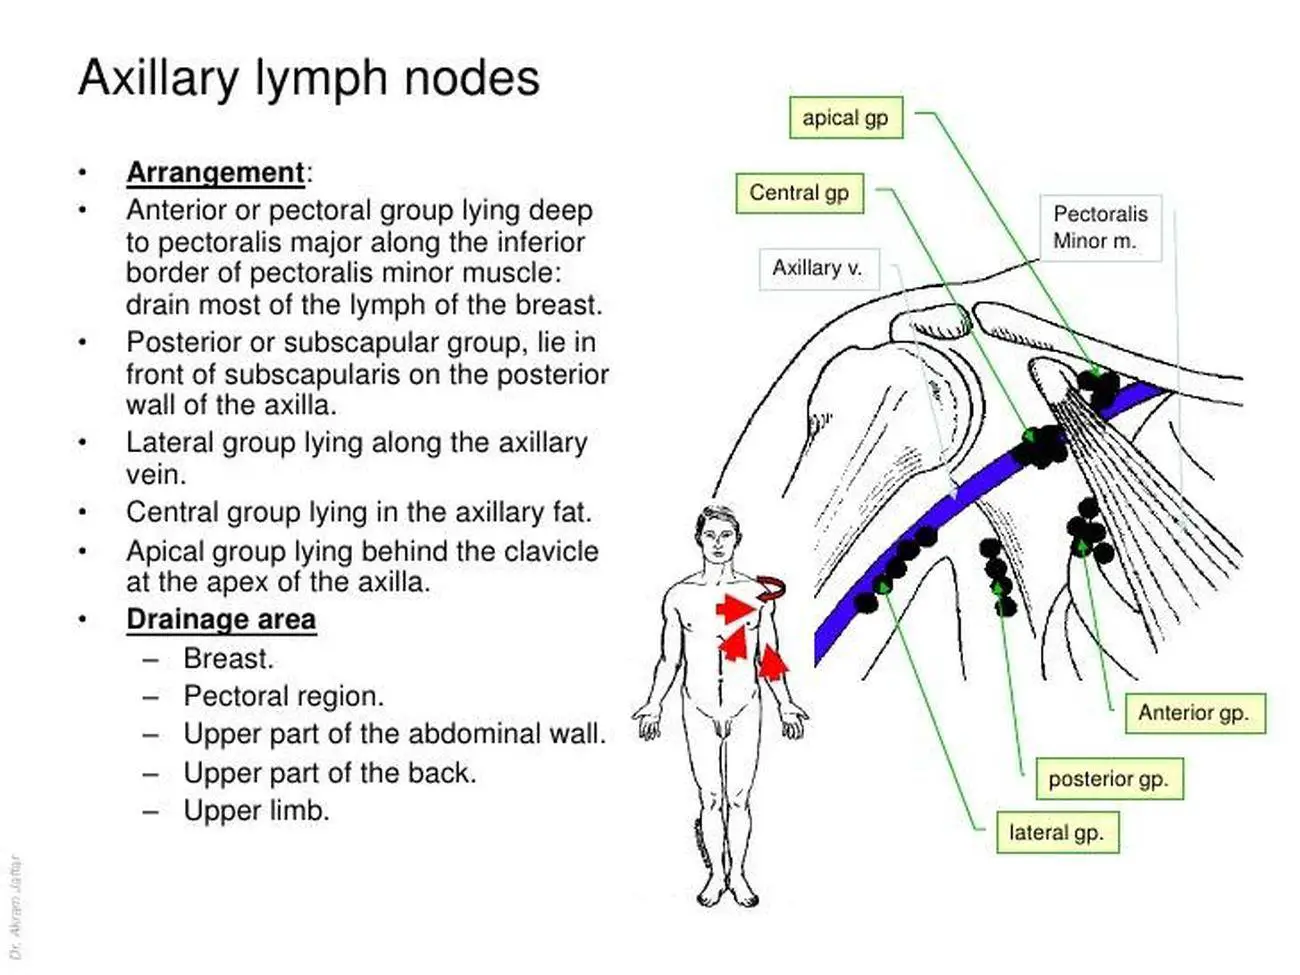
The axillary lymph nodes sit in the armpit, arranged in several groups that run along the walls of the axillary fossa. They receive drainage from the breast, upper limb, and superficial chest wall. A thorough exam requires you to check each group systematically, not just the most obvious spot. I found this out the hard way early on when I missed a level II node in a patient with breast cancer because I was only pressing into the anterior fold where level I sits. You position the patient seated or supine with the arm abducted and externally rotated. Your fingers should be flat, not curled, and you press in a circular fashion at each landmark. Start at the anterior axillary wall along the pectoralis major ridge, then move to the lateral wall where the nodes hug the axillary vein. The posterior wall is often neglected, but the subscapular group runs there right next to the latissimus dorsi. Finally, check the central cluster near the axillary fat pad, which is where most of the efferent drainage eventually collects before heading to the apical nodes.
Location Of Lymph Nodes Under Arm
The exact location matters because these nodes are divided into three levels by the pectoralis minor muscle. Level I nodes lie lateral to that muscle, Level II sits deep to it, and Level III extends medial to it toward the clavicle. When you're clinically palpating, Level I is the most accessible and the most commonly enlarged. Level II is deeper and usually only palpable when significantly enlarged. Level III nodes are rarely felt on exam unless there is substantial pathology, and they require you to press above the clavicle in the supraclavicular area. The actual tissue consistency gives you more information than the size alone. Reactive nodes from a recent vaccination in the same arm are typically firm but mobile, tender, and often have a rounded shape. Malignant nodes tend to be hard, fixed, and irregular. I remember one case where a patient had multiple small mobile nodes in level I after a flu shot, and they resolved completely within six weeks. Don't biopsy reactive nodes. Wait and re-examine. One practical detail that nobody mentions in textbooks: you need good lighting and a warm room. Cold causes arm hair to rise and muscles to tense, making palpation much harder. I always ask the patient to remove their shirt completely rather than pushing fabric aside, and I make sure the room isn't blowing cold air directly on them. This small adjustment made a noticeable difference in how many nodes I could actually feel during my residency rotations.
When Imaging Becomes Necessary
Ultrasound is the first-line imaging modality when clinically palpable nodes are suspicious. A standard lymph node shows a fatty hilum in the center with a thin cortices rim. When the cortex thickens past 3 millimeters or the hilum disappears entirely, that node needs further workup. Mammography and breast MRI also visualize the axillary nodes, though they're less sensitive for detecting isolated nodal disease outside the breast context. CT scans show the Location Of Lymph Nodes Under Arm with decent clarity but cannot reliably distinguish between reactive hyperplasia and metastatic involvement based on size alone. A node can be 2 centimeters and benign, or 8 millimeters and frankly malignant. PET scans add metabolic information but suffer from the same limitation: infection and inflammation light up just as brightly as tumor. The imaging findings always need to be correlated with clinical context. I once had a situation where ultrasound showed a 1.5 centimeter node that looked benign on every criterion, but the patient had a known history of melanoma. We biopsied it anyway and found metastatic deposits. Pathology proved that even a perfectly benign-appearing node can harbor microscopic disease in high-risk patients. Don't let reassuring imaging stop you from investigating when the clinical picture says otherwise.
Get the Full Details
Common Pitfalls in Examination
The most frequent mistake is examining the node-quiet arm. If you're checking axillary nodes on a patient who had a lumpectomy and sentinel node biopsy on the right side three months ago, do not use a vigorous technique on that side. The surgical dissection disrupts normal lymphatic channels and can create lymphoceles or fibrotic tissue that feels like a node but isn't. I learned this after mistaking a post-surgical scar for a recurring tumor in a follow-up patient. A careful ultrasound confirmed it was just scar tissue. Another pitfall is conflating the axillary tail of Spence with lymph nodes. This is normal breast tissue that extends into the armpit, and it can feel lumpy and irregular. It's not pathological. The key difference is that breast tissue moves with the breast when you gently compress the chest wall, while true lymph nodes sit deeper and maintain their own distinct mobility. Patients sometimes describe what they feel as "lumps under my arm" and assume the worst. Most of the time these are accessory breast tissue, lipomas, or inflamed hair follicles from shaving. A sebaceous cyst near the skin surface that's red and tender is almost never a lymph node. Lymph nodes sit deeper, beneath the subcutaneous fat layer, and aren't typically red or painful unless acutely infected.
What Enlarged Axillary Nodes Can Indicate
Infection is by far the most common cause. Any bacterial skin infection on the ipsilateral arm or hand can drain into these nodes. Cat scratch disease from Bartonella is a classic cause of isolated axillary lymphadenopathy that can persist for months. Toxoplasmosis also frequently presents with axillary enlargement. Tuberculosis of the lymph nodes, though less common now, produces matted nodes that feel like they're stuck together in a clump rather than separate discrete units. Malignancy remains the concern clinicians worry about most. Breast cancer is the leading cause of malignant axillary lymphadenopathy in women. Lymphoma typically produces bilateral, painless, rubbery nodes that seem disproportionately large compared to the rest of the patient's clinical presentation. Lung cancer and melanoma can also metastasize to the axilla. The pattern of involvement sometimes gives clues: isolated unilateral Level III enlargement with an otherwise clear exam raises suspicion for lymphoma more than metastatic carcinoma. The drainage pattern is important enough to memorize. The lower lateral group drains the lower quadrants of the breast and the lateral abdominal wall. The pectoral group receives drainage from the upper and medial breast. The subscapular group handles the posterior trunk above the iliac crest. The humeral group drains the arm. The central group collects from all of the above before passing drainage to the apical nodes. Knowing which quadrant a breast mass is in helps you predict which nodal group is most likely involved.
Biopsy Decisions
Not every enlarged node needs a biopsy. The general rule I followed during my clinical years was to observe for four to six weeks if the node lacks suspicious features and there's a plausible infectious explanation. If the node is progressively enlarging, persistently hard, fixed to surrounding tissue, or accompanied by systemic symptoms like fevers and night sweats, you proceed to biopsy without waiting. Fine needle aspiration is faster and less invasive but can miss the architecture that's needed for lymphoma diagnosis. Core needle biopsy preserves more tissue and is the preferred initial approach when malignancy is suspected. Excisional biopsy remains the gold standard when lymphoma is on the differential because pathologists need to see the entire nodal architecture to classify the subtype accurately. I had a patient with persistent axillary lymphadenopathy who kept coming back for reassurance visits every three months. The nodes were slightly enlarged but mobile and not growing. When I finally biopsied them at the eight-month mark, it turned out to be a low-grade lymphoma that had been quietly progressing through all those visits. Delaying biopsy in that case was the wrong call. I used to think watchful waiting was always the safe choice for stable nodes, but I changed my practice after that case. Low-grade lymphomas can smolder for a long time without obvious progression signs.

Self-Examination Considerations
You can palpate your own axillary nodes, though it's less reliable than having a clinician do it. Raise your arm and press your fingers firmly into the armpit, moving from front to back and top to bottom. Check both sides. Normal nodes, if palpable at all, are small, bean-shaped, and not tender. If you find something that concerns you, don't wait. Getting it evaluated promptly is better than monitoring it for weeks at home and hoping it resolves on its own. The reality is that most people will never seriously examine their axillary nodes until they feel something unusual. That's fine. What matters is knowing what's normal for you so you can notice when something changes. I've lost count of how many patients told me they found a lump during a routine activity and had never checked that area before. There's no shame in that, but there is a benefit to doing a quick check once in a while, especially if you have risk factors for breast cancer or a history of infections in the arm.