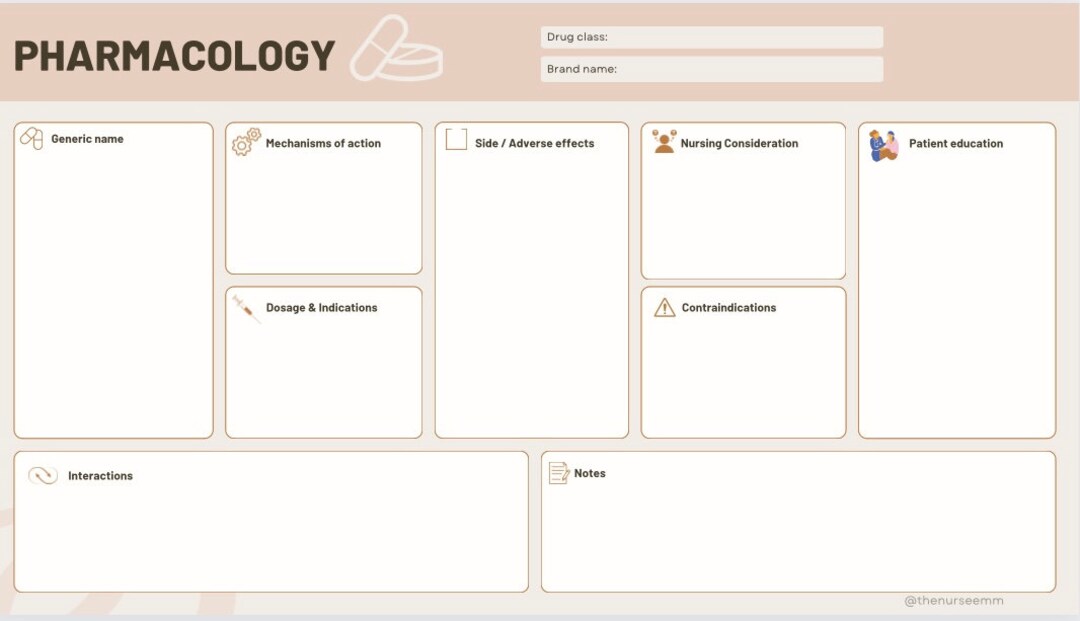
Most people I work with end up drowning in PDFs, scattered highlights, and notebooks they never actually reference after the first month. The problem isn't interest, it's retrieval. You learn something, you file it somewhere, and six weeks later you can't find the half-life of amiodarone when you actually need it.
I used to build massive spreadsheets for drug interactions. They looked impressive. They were also useless because nobody updates them. The version I keep now is much dumber and it works better.
Logbook For Pharmacology Minimalist
The Logbook For Pharmacology Minimalist is just that — minimal. It strips away everything except what you need to recall under time pressure. No color-coded folders. No tagging systems that require three clicks to navigate. One entry per drug, three fields, repeated exposure over spaced intervals.
The structure goes like this. Drug name. Mechanism or class. Key clinical point. That's it. Most beginners add side effects, dosing ranges, and interactions all at once. Don't. Those belong in reference material, not in your memory system. You can look them up. Half-lives and mechanisms are harder to reconstruct from scratch.
When I started using this approach, I made the mistake of putting dosing on the card. Within two weeks I had thirty entries full of microgram ranges I'd never remember anyway. I stripped those out and kept only the mechanistic anchors. Everything else lives in a separate lookup file that I access when clinically necessary.
The workflow is simple. Write one card. Review it within twenty-four hours. Review again after three days. Then seven. Then fourteen. If you miss a review, don't add extra sessions — just pick up where you left off. The system tolerates gaps better than people expect.
I ran into a specific problem with antiarrhythmics. Class III drugs all share potassium channel blockade as a mechanism, which makes them nearly indistinguishable on recall. I ended up confusing sotalol with dofetilide twice during a rotation. The fix was adding a distinguishing clinical feature to each card — something like sotalol's beta-blocking activity or dofetilide's lack of it. That single addition cut my confusion rate down to basically zero.
There are limitations worth acknowledging. This system doesn't handle complex clinical reasoning. It won't teach you when to start an anticoagulant or how to adjust dosing in renal failure. For those things, you still need textbooks and guidelines. The Logbook For Pharmacology Minimalist is a memorization aid, not a clinical decision framework.
Another issue is initial time investment. Building your first fifty cards takes about four hours if you're careful. Most people rush it and produce entries so vague they're useless later. Take the time to write precise mechanisms. "Beta-blocker" is insufficient. "Non-selective beta and weak alpha-1 blockade" tells you why carvedilol behaves differently than atenolol.
The method has one counter-intuitive advantage that surprises people. Because you're limited to three fields per entry, you naturally distill information down to what actually matters. This forces you to understand the concept rather than copy-pasting textbook paragraphs. The compression process itself is where learning happens.
I recommend pairing this with a simple spaced repetition tool. Anki works, but any basic flashcard system will do. The specific app doesn't matter. What matters is the review schedule and the consistency of your entries.
If you decide to try it, start with drugs you're currently studying. Don't build ahead of your curriculum. The cards age differently depending on your review pattern, and pre-built decks usually become outdated before you finish them.
The system isn't magic. It's just disciplined reduction. You strip pharmacology down to its essential recall points and expose yourself to them at increasing intervals until they stick. Everything else is reference material.