Getting the Long Buccal Block Right
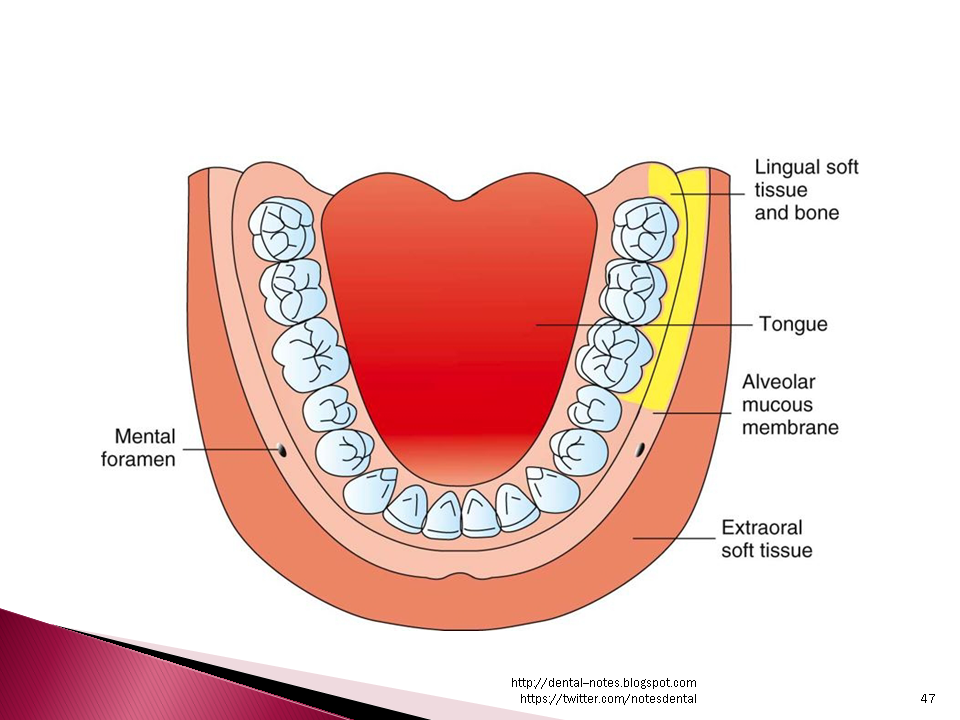
The long buccal nerve block is one of those injections dentists learn early and rarely think about again until they mess it up. It's straightforward when you know what you're doing, which apparently nobody admits until they watch a student fumble through it on their first Saturday shift. This nerve provides sensory innervation to the buccal mucosa, skin of the cheek, and buccal gingiva from the second premolar region back to the retromolar pad. The inferior alveolar nerve block won't touch it, which is probably the most common reason this injection fails to land properly. Students sit there waiting for the lower lip to go numb while the patient complains about cheek sensation, completely forgetting the long buccal nerve has its own separate pathway entirely.
Long Buccal Nerve Block Technique
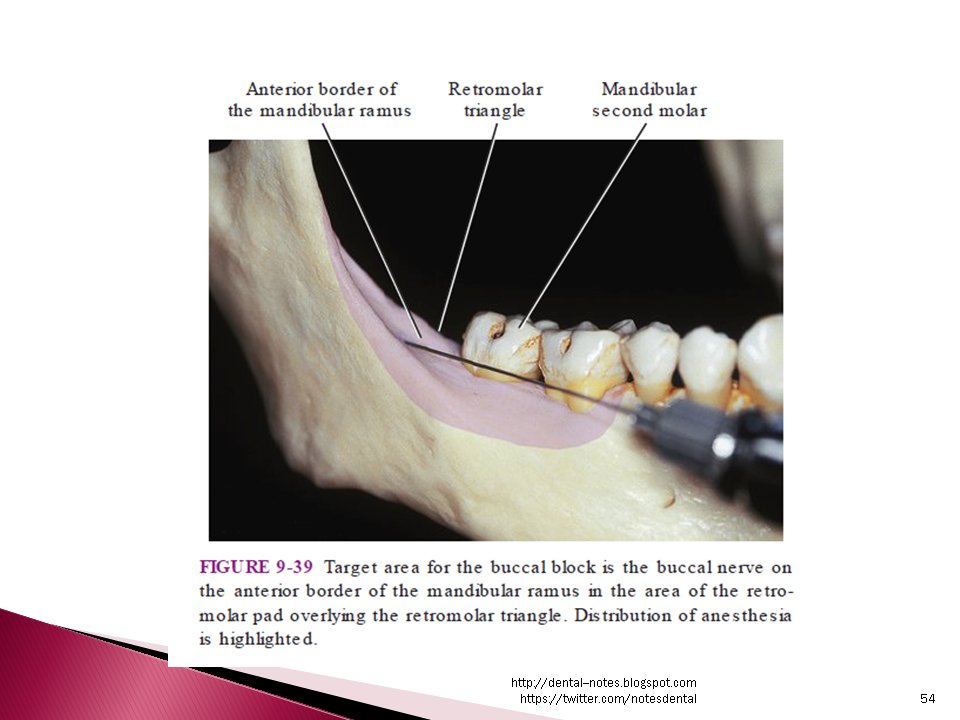
Have the patient open wide. Palpate the anterior border of the ramus and the coronoid notch. The injection site is roughly at the level of the occlusal plane of the maxillary molars, about 1 centimeter medial to the anterior border of the ramus. You're aiming for the pterygomandibular space lateral to the medial pterygoid muscle. The needle enters just anterior to the masseter and passes medially until you hit bone, then you walk off the bone about 5 millimeters and deposit 1 to 1.5 milliliters of local anesthetic. I spent years using the classic approach described in textbooks, which works fine most of the time, until I ran into a patient whose masseter was so hypertrophied from bruxism that I literally couldn't palpate the anterior border of the ramus through the muscle bulk. Had three attempts, got nothing but tissue trauma and a very unhappy patient. The workaround was switching to an intraoral approach where I located the buccal Shelf of the mandible between the second premolar and first molar, then advanced the needle posteromedially at a 45-degree angle to the occlusal plane, stopping about 15 millimeters deep without ever touching bone. Hit the long buccal nerve on the second attempt and the patient was numb within three minutes. The bevel orientation matters more than most people bother with. Position the bevel facing the bone when you walk off it. This orients the anesthetic deposition toward the nerve rather than into free space medially where it dissipates uselessly into the pterygoid plexus. I learned this the hard way after wasting three carpules on a patient who never got properly anesthetized and kept moving on the drill.
Depth is another detail that gets overlooked. Going too shallow deposits anesthetic into the masseter or lateral pterygoid and you get nothing. Going too deep risks hitting the maxillary artery or entering the infratemporal fossa. The sweet spot is usually 15 to 20 millimeters from the mucosal insertion point in an average adult. For larger patients, you might need to go slightly deeper. For children, significantly less. I typically aspirate before depositing any solution because a positive aspiration in this area could mean intravascular injection, and the long buccal region has a rich vascular network close to the injection path.
Get the Full Details

When It Fails and What to Do Instead
The long buccal block simply doesn't work well for patients with acute inflammation in the target area. The tissue tension and pH changes around an infected site neutralize the anesthetic before it can block the nerve. I've seen multiple cases where clinicians kept trying the standard injection on a patient with pericoronitis around a lower wisdom tooth, wondering why the buccal tissue never went numb, when the answer was right there in the swelling. In those situations, supplemental infiltration directly into the buccal tissue distal to the affected area, away from the inflammatory zone, usually achieves acceptable anesthesia in about five minutes. Another scenario where this block underperforms is in patients with significant anatomical variation in the nerve's course. The long buccal nerve can take unpredictable paths through the buccinator muscle or even loop around structures that change its surface landmark location. If you're consistently failing the block in certain patients despite proper technique, consider a supracrestal infiltration approach targeting the specific teeth involved rather than relying solely on the nerve block. The onset time is typically three to five minutes for a successful injection, though some patients report full numbness closer to seven or eight minutes depending on the anesthetic agent used. Articaine with epinephrine tends to work fastest, while plain lidocaine takes a bit longer but provides a more prolonged duration for procedures that run extended. A successful block should give you complete anesthesia of the buccal soft tissues from the second premolar posteriorly. If the patient still feels pressure or sharp sensation in that region after eight minutes, the block didn't take and you'll need to supplement rather than keep injecting.
Complications are rare but worth knowing. Hematoma formation can occur if you nick the pterygoid plexus, which is why aspiration is important. Trismus can result from injecting into the medial pterygoid muscle, which happens if your needle path angles too far posteriorly. Nerve injury is extremely unlikely with this block compared to the inferior alveolar nerve block, but it's not impossible if you use a needle that's too large or advance with excessive force. Standard 27 or 30 gauge needles are appropriate here, and you should never advance faster than you can control the depth. For the actual procedural documentation and patient consent forms, I keep a digital checklist on my workstation that covers the injection site, volume, needle gauge, aspiration result, and onset time. It's not glamorous but it keeps things organized when you're running a full day of extractions and need to track which blocks you've already given and which still need attention. I don't have a public download link I'm comfortable sharing since practice protocols vary so much by state and clinic, but the core elements are consistent everywhere.