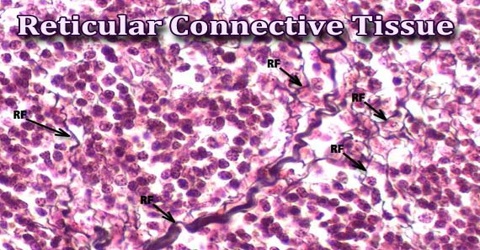
Working With Loose Reticular Connective Tissue Under the Microscope
You pick up a slide of splenic white pulp and you're looking at reticular connective tissue. That is basically what it is. A three-dimensional network of type III collagen fibers, produced by reticular cells, creating a loose scaffold that holds parenchymal cells in place. It is not dramatic. It does not look like anything except a faint gray web if you are using standard H&E stain. The problem most people run into is that this tissue is nearly invisible without the right staining method. I have spent more hours than I care to admit staring at a spleen section, convinced the pathologist missed a lesion, only to realize the reticular framework was completely washed out because the fixative had been sitting around too long before processing. Formalin fixation degrades reticular fibers over time. Not all at once. Gradually. You lose definition over weeks in the jar.
Staining and Visualizing Loose Reticular Connective Tissue
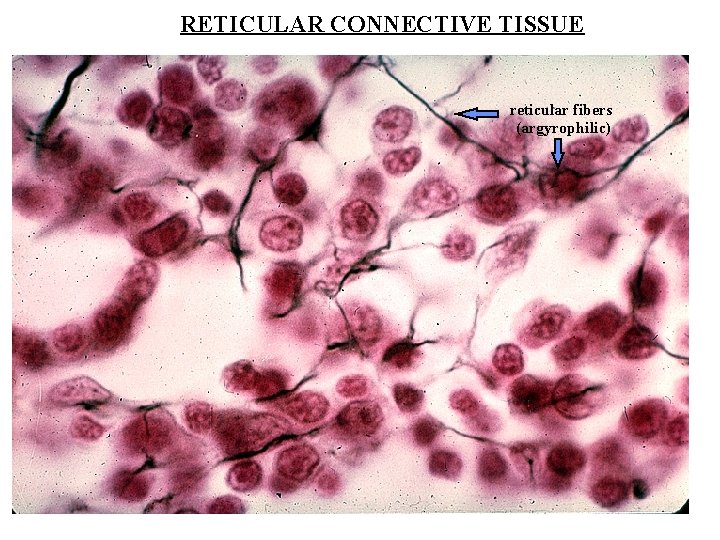
If you need to see this tissue properly, you cannot rely on routine H&E. The reticular fibers are too thin and too translucent. You need a silver impregnation method. Warthin-Starry or Gomori methenamine silver (GMS) are the standard options. The silver deposits on the reticular fibers and turns them black against a lighter background. The protocol usually takes about 45 to 60 minutes from rehydration to coverslip, depending on your lab's temperature and humidity conditions. Cold labs slow the development reaction noticeably. Here is a practical workflow that works consistently: Start with formalin-fixed, paraffin-embedded sections cut at 4 to 5 microns. Thinner sections make the fiber network harder to parse. Four microns is the sweet spot for most lymphoid organs. Dehydrate through graded alcohols, clear in xylene, and rehydrate through descending alcohols to water. Then proceed with the silver stain according to the manufacturer's instructions, but do not skip the pre-irradiation or pre-reduction step if your kit includes one. That step sensitizes the fibers and makes the difference between a faint blush and a crisp black reticular network.
After staining, you counterstain lightly. We usually use nuclear fast red or light green. You want the background pale so the black fibers stand out. If your counterstain is too dark, you will miss the finer reticular strands in the marginal zones of the spleen or the hepatic sinusoids.
Get the Full Details
What This Tissue Actually Does in the Body
Reticular connective tissue is the structural scaffolding for soft organs. It is not contractile. It does not store energy. It exists to hold cells in the correct spatial relationship to one another while still allowing fluid and cells to move through it freely. That permeability is the whole point. Blood, lymph, and immune cells all traffic through these fiber networks. In the lymph node, the reticular framework defines the subcapsular sinus, the medullary cords, and the follicular dendritic cell zones. In the liver, reticular fibers surround each sinusoid and define the space of Disse. In bone marrow, they create the cellular highway that hematopoietic cells migrate along before entering circulation. Remove the reticular scaffold and the organ collapses into an unorganized puddle of cells. That is why reticular fibers are critical in metastasis workups. Tumor cells often hijack these pathways to invade vessels.
A Real Problem I Faced and How I Solved It
I was reviewing a lymph node biopsy that showed partial effacement of the architecture. The H&E looked nondiagnostic. The reticular pattern was blurred, and I could not tell whether the effacement was due to fibrosis or just artifact from poor processing. I ran a Gomori silver stain on an adjacent section and the reticular framework came back clean. The disruption was real, not artifactual. It turned out to be an early Hodgkin lymphoma case where the fibrotic bands were sparing the reticular network in some areas and destroying it in others. Without the silver stain, I would have called it reactive hyperplasia and sent the patient home. The workaround was straightforward: request silver staining whenever architecture is ambiguous on H&E and the clinical question involves lymphoid tissue. It adds roughly one working day to turnaround time, but it prevents misdiagnosis in cases where the stromal pattern is the key diagnostic feature.
Common Pitfalls and Where This Approach Fails
Silver stains are finicky. They degrade quickly. A freshly prepared working solution of ammoniacal silver lasts maybe two weeks before it loses sensitivity. If your stock has been sitting on the shelf for a month, your reticular fibers will stain weakly and inconsistently. Always run a positive control section alongside your unknowns. Spleen is the easiest control tissue. It has abundant reticular fibers in the white pulp and is forgiving even if your timing is slightly off. Another issue: over-fixation. If the tissue sits in formalin for more than 72 hours before processing, the reticular fibers become cross-linked and resistant to silver deposition. You will get patchy staining. The solution is to process tissue within 24 to 48 hours of fixation whenever reticular fiber evaluation is anticipated. If you are working with an outside lab that does not follow this timeline, flag it on the requisition form. The biggest limitation is that reticular staining does not distinguish between type III collagen and other argyrophilic structures. Reticulin-positive fibers can include elastic fiber fragments, basement membrane material, and sometimes even bacterial cell walls if there is an infectious process present. Correlation with H&E and clinical context is mandatory. Silver stain alone is never diagnostic.

When to Use This and When to Look Elsewhere
Use reticular fiber staining when you need to assess architectural integrity in lymphoid organs, liver, or bone marrow. It is most valuable in evaluating lymphomas with fibrotic components, staging hepatic fibrosis, and assessing marrow fibrosis in myeloproliferative disorders. Do not use it as a general screening tool. Running silver stains on every biopsy is wasteful and generates noise. Reserve it for cases where the H&E architecture is equivocal and the differential diagnosis depends on distinguishing true stromal disruption from processing artifact. In those situations, it usually resolves the question within a week. If your concern is quantitative fibrosis assessment rather than architectural mapping, consider picrosirius red staining instead. It targets type I and type III collagen with better quantification potential under polarized light. Reticulin silver is qualitative by nature. It tells you where the fibers are, not how much collagen is present overall.