Bioidentical Hormone Replacement Therapy: What It Actually Looks Like In Practice
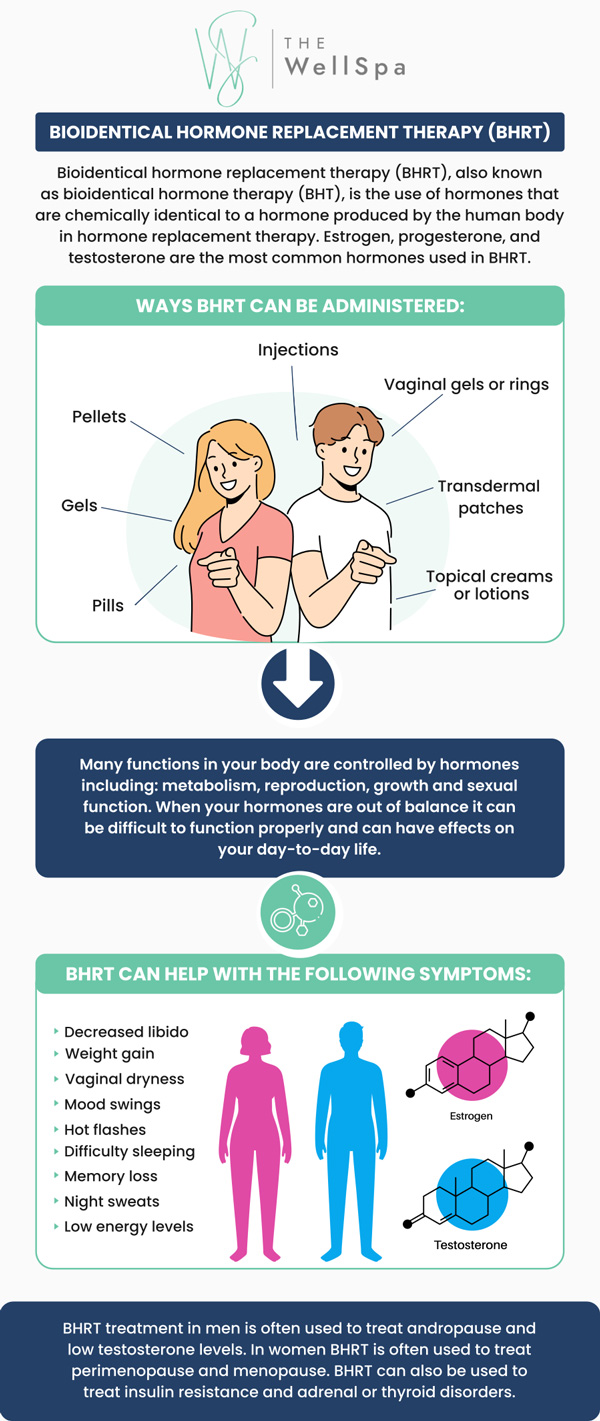
BHRT isn't a single treatment. It's a whole category of hormone replacements made from plant-derived steroids that are structurally identical to what your body produces. That "bioidentical" label matters more in compounding pharmacy circles than it does in mainstream endocrinology, but the underlying principle is straightforward: replace what your body has lost rather than what it never made. I got pulled into this space years ago when a colleague was dealing with unexplained fatigue, weight stagnation, and mood fluctuations that standard synthetics didn't seem to touch. We went down the BHRT rabbit hole, and honestly, the practical realities are less glamorous than the marketing suggests.
The Reality of Loss Bioidentical Hormone Replacement Therapy
When people search for Loss Bioidentical Hormone Replacement Therapy, they're usually looking at one of three scenarios: postmenopausal estrogen and progesterone depletion, androgen decline in aging men, or adrenal insufficiency. The treatment approach differs significantly across these. I've seen more damage done by treating the wrong deficiency than by any dosing error, frankly. The process starts with comprehensive baseline testing. Salivary or serum hormone panels, thyroid workups, and metabolic markers. Standard labs often miss subclinical deficiencies that BHRT targets. I learned this the hard way when a patient's symptoms persisted despite seemingly "normal" lab ranges on conventional synthetic T3/T4. Her free T3 was in the low quarter of the reference range, which is technically normal but functionally insufficient for her metabolism.
How Compounded BHRT Differs From Pharmaceutical Alternatives
Big Pharma BHRT products exist, but they're limited. Estradiol pills, patches, and creams from companies like Sogroya or Evamist. Bi-Test for testosterone. These are FDA-approved versions of bioidentical hormones. The compounding route opens up combinations and delivery methods that off-the-shelf options don't cover. Compounded preparations typically use micronized progesterone and estradiol from wild yam or soy. The bioavailability profiles can differ from synthetics like medroxyprogesterone acetate or conjugated equine estrogens. This isn't just semantics — the metabolic pathways change, and so do the side effect profiles. Here's where beginners usually get tripped up: dosing symmetry. Everyone wants to match their hormone levels perfectly to physiological ranges, but hormones interact in nonlinear ways. Throwing more estrogen at a patient without addressing progesterone opposition increases breast tissue stimulation and thromboembolic risk. The opposite problem shows up with testosterone: cranking up T without adequate estrogen conversion management causes aromatization issues and patient discomfort. I once saw a protocol where someone was prescribed 50mg of progesterone and 1mg of estradiol daily. The ratio was wildly off. Symptoms actually worsened before we recalibrated. That took about three weeks and two follow-up blood panels to sort out.
Get the Full Details

Practical Dosing Considerations That Matter
Transdermal delivery generally produces more stable serum levels than oral administration because it bypasses first-pass hepatic metabolism. Estrogen patches or gels applied to the abdomen or thighs tend to give steadier results than pills, which spike and crash through the digestive system. For progesterone, oral micronized versions like Prometrium remain the gold standard for sleep support, but transdermal compounded versions offer more consistent absorption for some patients. Testosterone replacement in men typically uses transdermal gels or subcutaneous pellets. Pellets last three to six months, which sounds convenient until you realize you can't adjust the dose mid-insertion. If a patient's levels overshoot or undershoot, they're locked in. I prefer starting with gels for this reason. Monitoring frequency depends on the hormone and the delivery method. Most protocols check levels at four to six weeks after any dosage change, then quarterly once stabilized. Some practitioners push for biweekly checks, which is overkill for stable patients and wastes resources. The sweet spot is individualized but rarely needs to exceed monthly intervals after the first few months.
Where This Approach Fails and What to Do Instead
BHRT isn't a solution for everything that goes wrong with hormonal decline. Patients with active hormone-sensitive cancers — breast, ovarian, prostate — are generally poor candidates regardless of whether the hormones are bioidentical or synthetic. The evidence base for some symptom improvements, particularly in men using testosterone for age-related decline, remains contested. The TEA trial and subsequent studies show modest benefits at best for quality of life in older men with borderline-low testosterone. The biggest practical limitation is insurance coverage. Compounded formulations rarely qualify for coverage, and even FDA-approved bioidentical products face prior authorization hurdles. A typical three-month supply of compounded estradiol and progesterone runs $80 to $250 out of pocket depending on the pharmacy. Pellet insertions run $600 to $1,200 per procedure. This isn't trivial for chronic use. If you're considering this route, the most important step is finding an endocrinologist or functional medicine provider who actually reviews lab work rather than prescribing from a protocol template. I've seen too many cases where a patient gets put on a standard BHRT stack without checking SHBG, free versus total hormone ratios, or inflammatory markers. The result is usually more symptoms, not fewer. Get second opinions if your provider doesn't order baseline testing before writing a prescription.
The other thing nobody tells you: lifestyle factors matter more than the hormone dose. Sleep quality, resistance training, and protein intake can shift cortisol and testosterone levels more than a modest estradiol adjustment. I had a patient whose symptoms resolved after six weeks of consistent weight training and seven hours of sleep, despite being on a subtherapeutic BHRT dose. The hormone replacement provided a floor, but the lifestyle work built the house.