How the Low Cholesterol Diet Plan Actually Works in Practice
I spent about three months mapping out a proper eating routine based on the Mayo Clinic's approach to lowering cholesterol. The basic framework is straightforward but easier to mess up than you'd expect. The core principle is reducing saturated fat to less than 7% of your daily calories and replacing it with monounsaturated and polyunsaturated fats. For a 2,000-calorie diet, that means roughly 15 to 16 grams of saturated fat per day. Most people accidentally eat twice that before they start tracking labels properly. The Mayo Clinic version emphasizes soluble fiber as the primary mechanism for actually moving the needle on LDL numbers. Soluble fiber binds to bile acids in the digestive tract and pulls them out of the body. Your liver then has to pull LDL cholesterol from the bloodstream to make new bile acids. That's the whole loop. The recommended daily target is around 10 to 25 grams of soluble fiber. Oats, beans, lentils, apples, and Brussels sprouts are the most efficient sources. You can't really get there by accident. Here's what the typical day looks like on paper. Breakfast is oatmeal with walnuts and berries instead of bacon and buttered toast. Lunch is a lentil soup or a chicken salad with olive oil dressing instead of a deli sandwich on white bread. Dinner is baked salmon with quinoa and roasted vegetables instead of a steak with creamy sauce. Snacks are apples, carrots, or a handful of almonds. It's not complicated. It's also not particularly exciting if you're used to eating convenience food.
I hit a wall around week two when I realized how much sodium is hiding in the "heart-healthy" processed foods. Reduced-fat packaged meals often compensate with salt and refined carbohydrates. I started reading nutrition labels on everything, which took maybe 10 extra minutes during each grocery trip but eliminated about half the stuff I used to buy. The workaround was sticking to the perimeter of the grocery store and buying raw ingredients instead of prepared items. Pre-cut vegetables, pre-cooked quinoa bags, and canned beans in low-sodium versions exist now, which cut prep time from about 40 minutes to roughly 12 minutes per meal. One thing nobody tells you about this approach is that not all saturated fat is equal in its effect on LDL. Coconut oil and palm oil are plant-derived but still raise LDL significantly, which surprises a lot of people who assume "natural" means "safe for cholesterol." The Mayo Clinic guidelines don't single these out specifically, but the data is clear enough that you should treat them like butter, not like olive oil. Another counter-intuitive point: extremely low-fat diets aren't necessarily better. You need some fat intake for nutrient absorption, and the type of fat matters far more than the total amount. Swapping saturated fat for refined carbs actually makes your lipid profile worse. That's a mistake I see people make constantly. The timeline for results is another area where expectations get distorted. Most people checking their numbers after two weeks are disappointed. LDL changes typically become measurable around the 4-to-6-week mark, and significant shifts often take 8 to 12 weeks of consistent adherence. If you're combining dietary changes with exercise, you might see results a little faster. Statin medications change the equation entirely and should be discussed with your doctor regardless of diet.
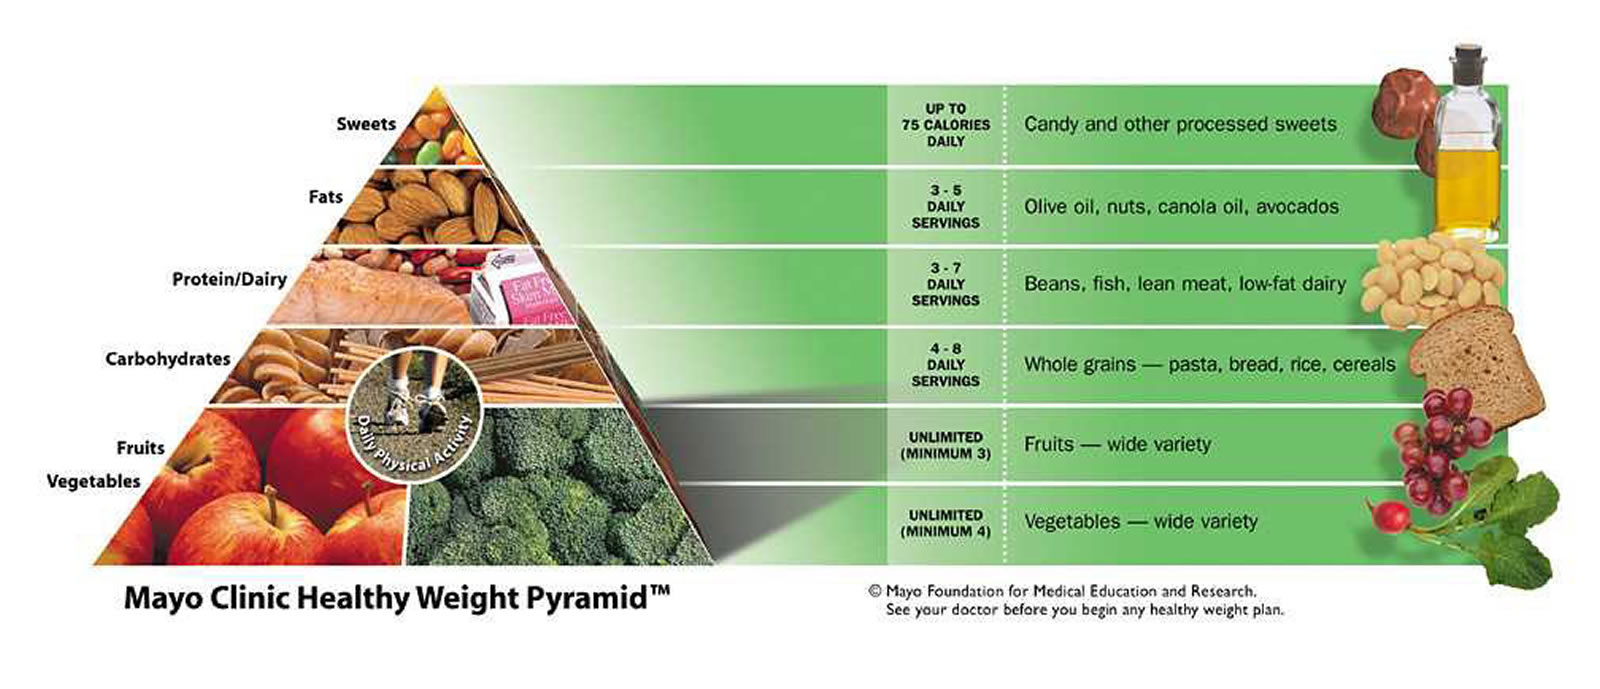
There are real limitations to this plan that the materials don't always emphasize. Social situations are the biggest practical problem. Restaurant menus are almost never designed with sub-7%-saturated-fat in mind. Even "healthy" menu items at chain restaurants often contain 8 to 12 grams of saturated fat per serving. You end up cooking most dinners at home unless you're willing to ask detailed questions about preparation methods. Another limitation is cost. Fresh produce, lean proteins, and quality oils run about 20 to 30 percent more than a standard grocery bill if you're buying everything fresh rather than relying on processed foods. Canned beans, frozen vegetables, and bulk grains bring that gap down considerably. If you have familial hypercholesterolemia or severely elevated LDL readings above 190 mg/dL, diet alone won't get you to target. In those cases, the Mayo Clinic itself recommends medication alongside lifestyle changes. No amount of oatmeal is going to overcome a genetic condition. For moderately elevated numbers in the 160 to 189 range, this plan is worth a serious attempt before jumping to medication. Track your numbers. Give it three months. Recheck. If you're not moving, talk to your doctor about next steps. The actual food list breaks down into simple categories. Foods to emphasize include oat bran, barley, nuts like almonds and walnuts, soy products, vegetables, fruits, fatty fish such as salmon and mackerel, and olive oil. Foods to limit include red meat, full-fat dairy, butter, lard, processed meats like bacon and sausage, baked goods made with tropical oils, and anything with partially hydrogenated oils on the ingredient list. Trans fats should be avoided completely regardless of what the label says, since even small amounts raise LDL and lower HDL simultaneously.
Get the Full Details
Meal planning on a Sunday takes me about 25 minutes. I write out three dinner options, check what I already have in the pantry, and make a shopping list. That list usually fits on one page. I shop once a week and eat the same three or four breakfast and lunch options on rotation. Rotation is not glamorous but it removes the daily decision fatigue that causes most people to abandon these plans within the first month. The fewer decisions you make about what to eat, the more likely you are to stick with it long enough to see results.