LDN and Crohn's: What Actually Happens When You Try It
I started looking into low dose naltrexone after my third flare in two years. By then, the usual suspects — mesalamine, steroids, immunomodulators — had either stopped working or caused side effects that made daily life worse than the disease itself. A gastroenterologist I trust mentioned LDN casually during a follow-up visit, like it was just another option on the table. I looked it up, went back to the appointment, and started on 1.5 mg at bedtime. Low Dose Naltrexone Therapy Improves Active Crohns Disease is a claim that shows up increasingly in the medical literature, and for good reason. The 2021 trial published in Inflammatory Bowel Diseases followed patients with moderate Crohn's and tracked CRP, fecal calprotectin, and endoscopic healing over several months. The results were modest but consistent enough that the discussion around LDN shifted from fringe to seriously considered. That doesn't mean it works for everyone. It means the signal is real, just not overwhelming.
How the Mechanism Actually Works
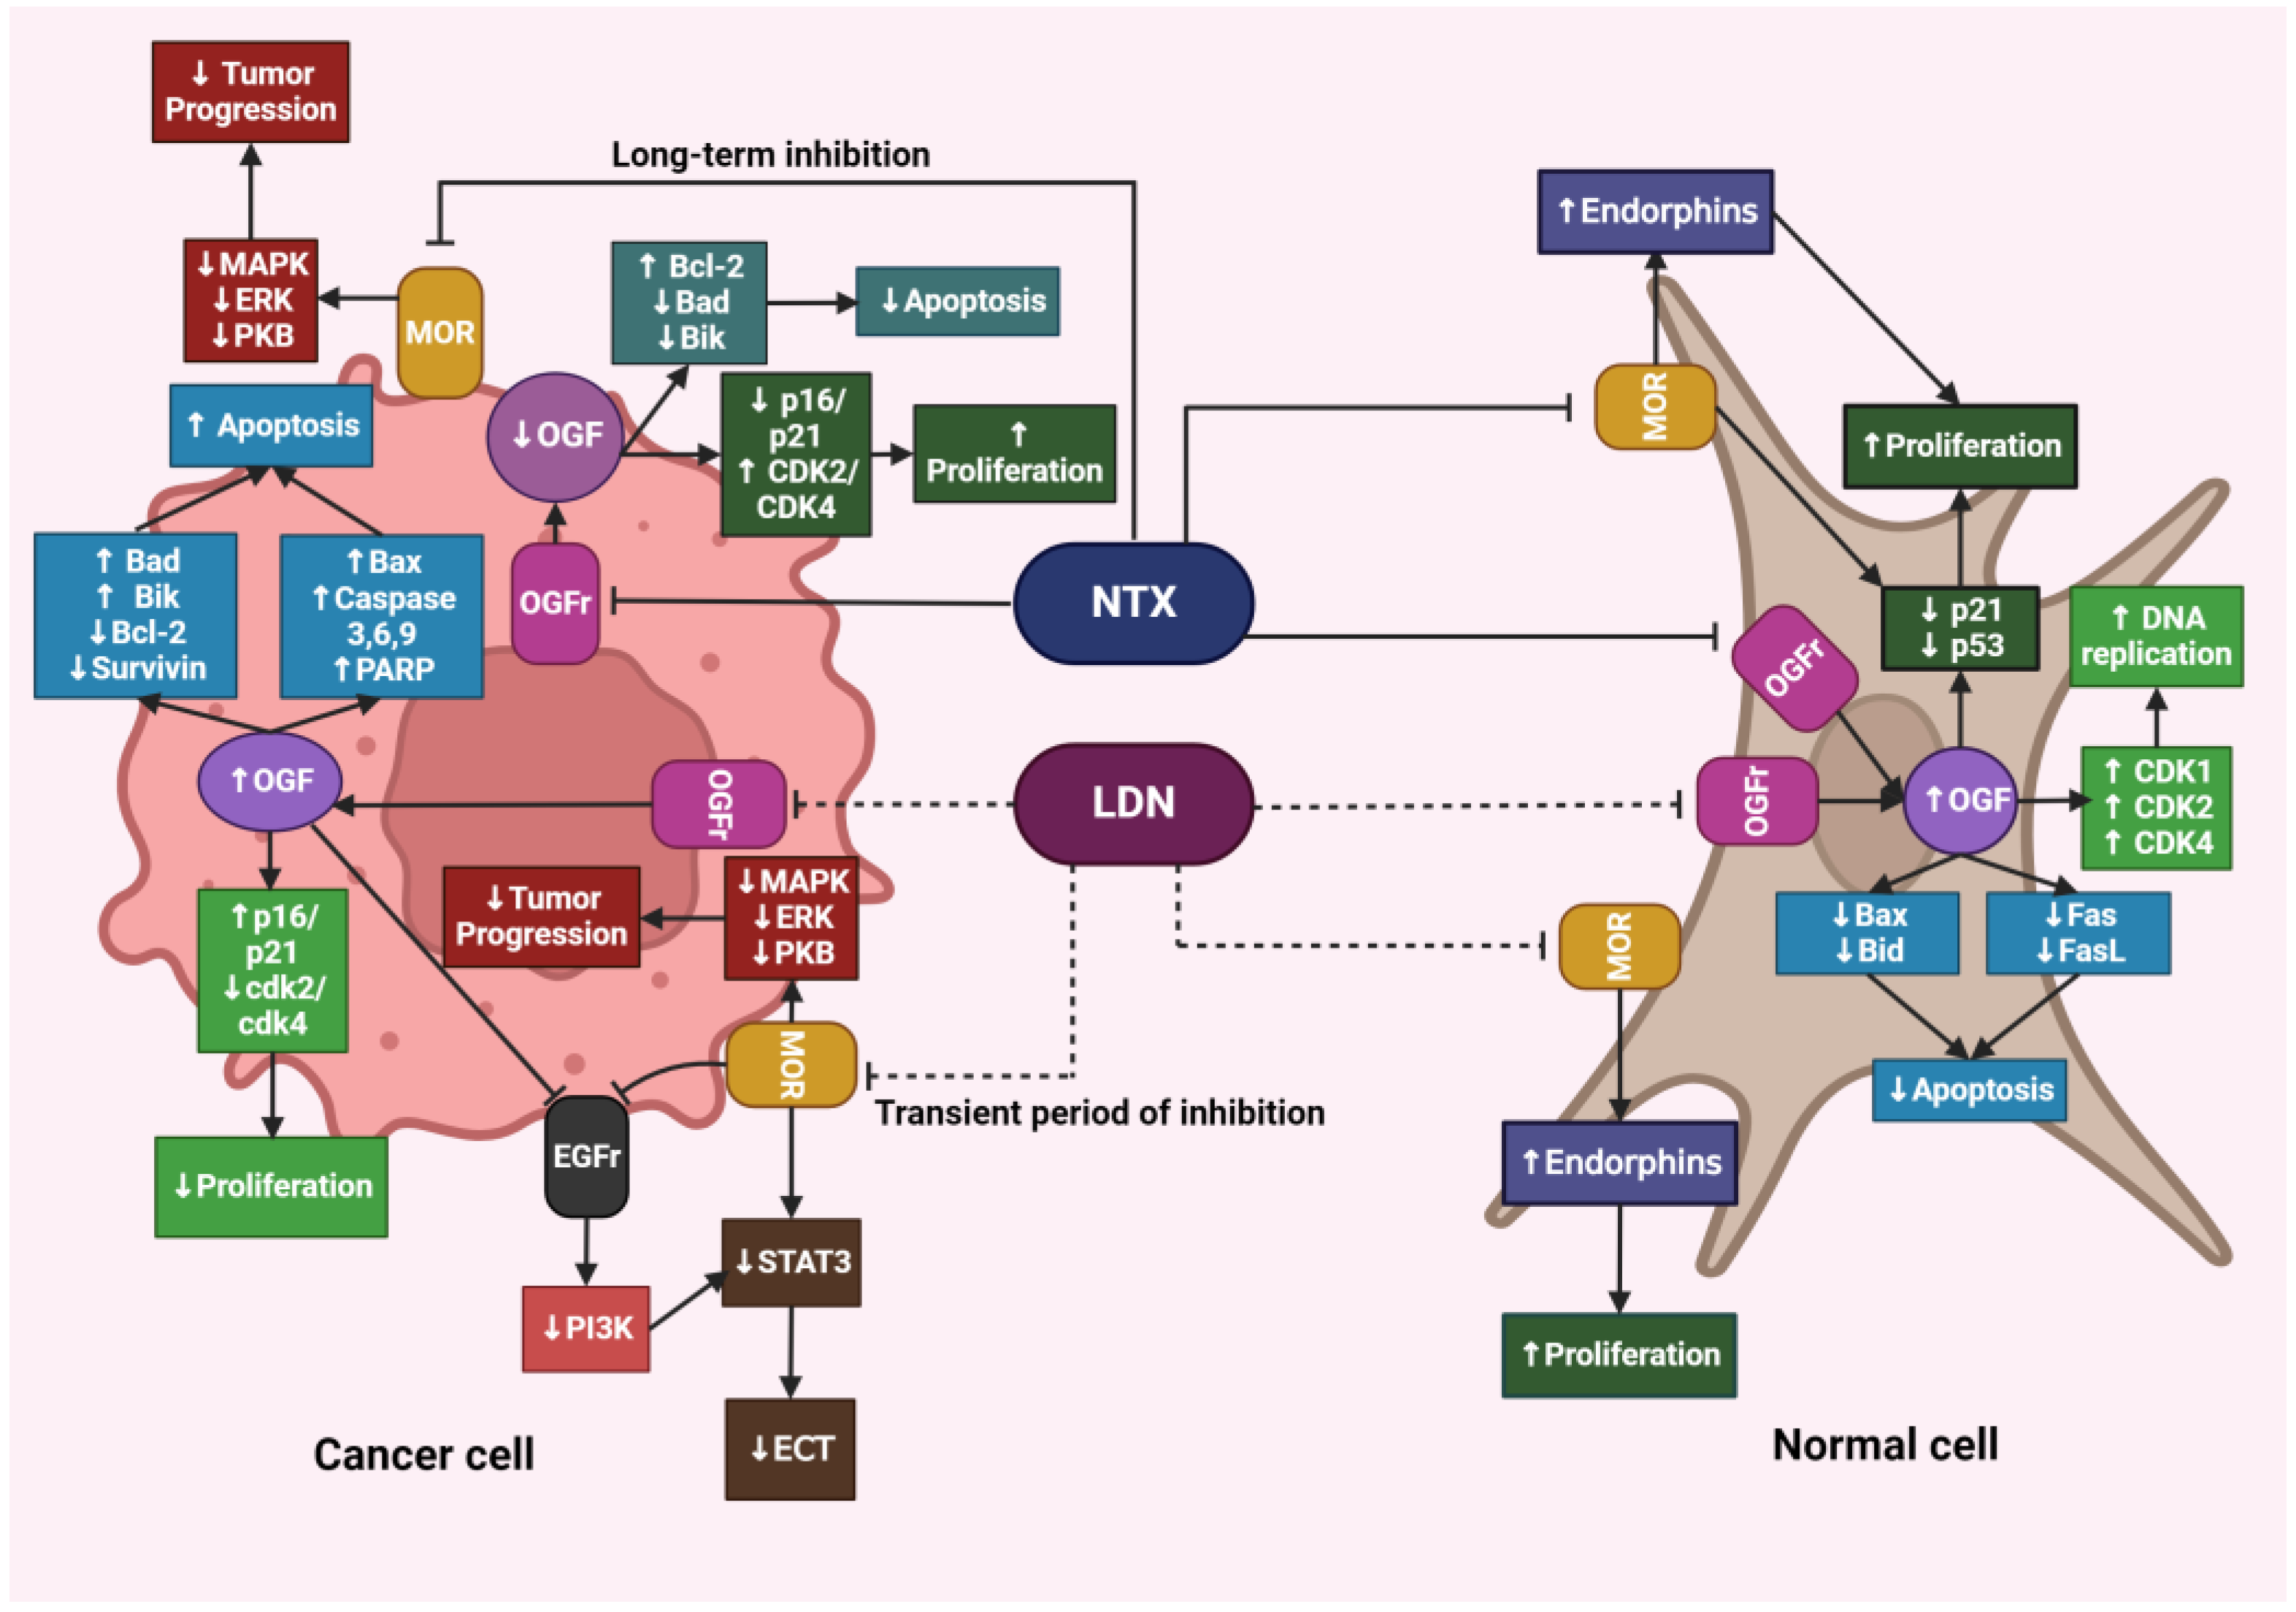
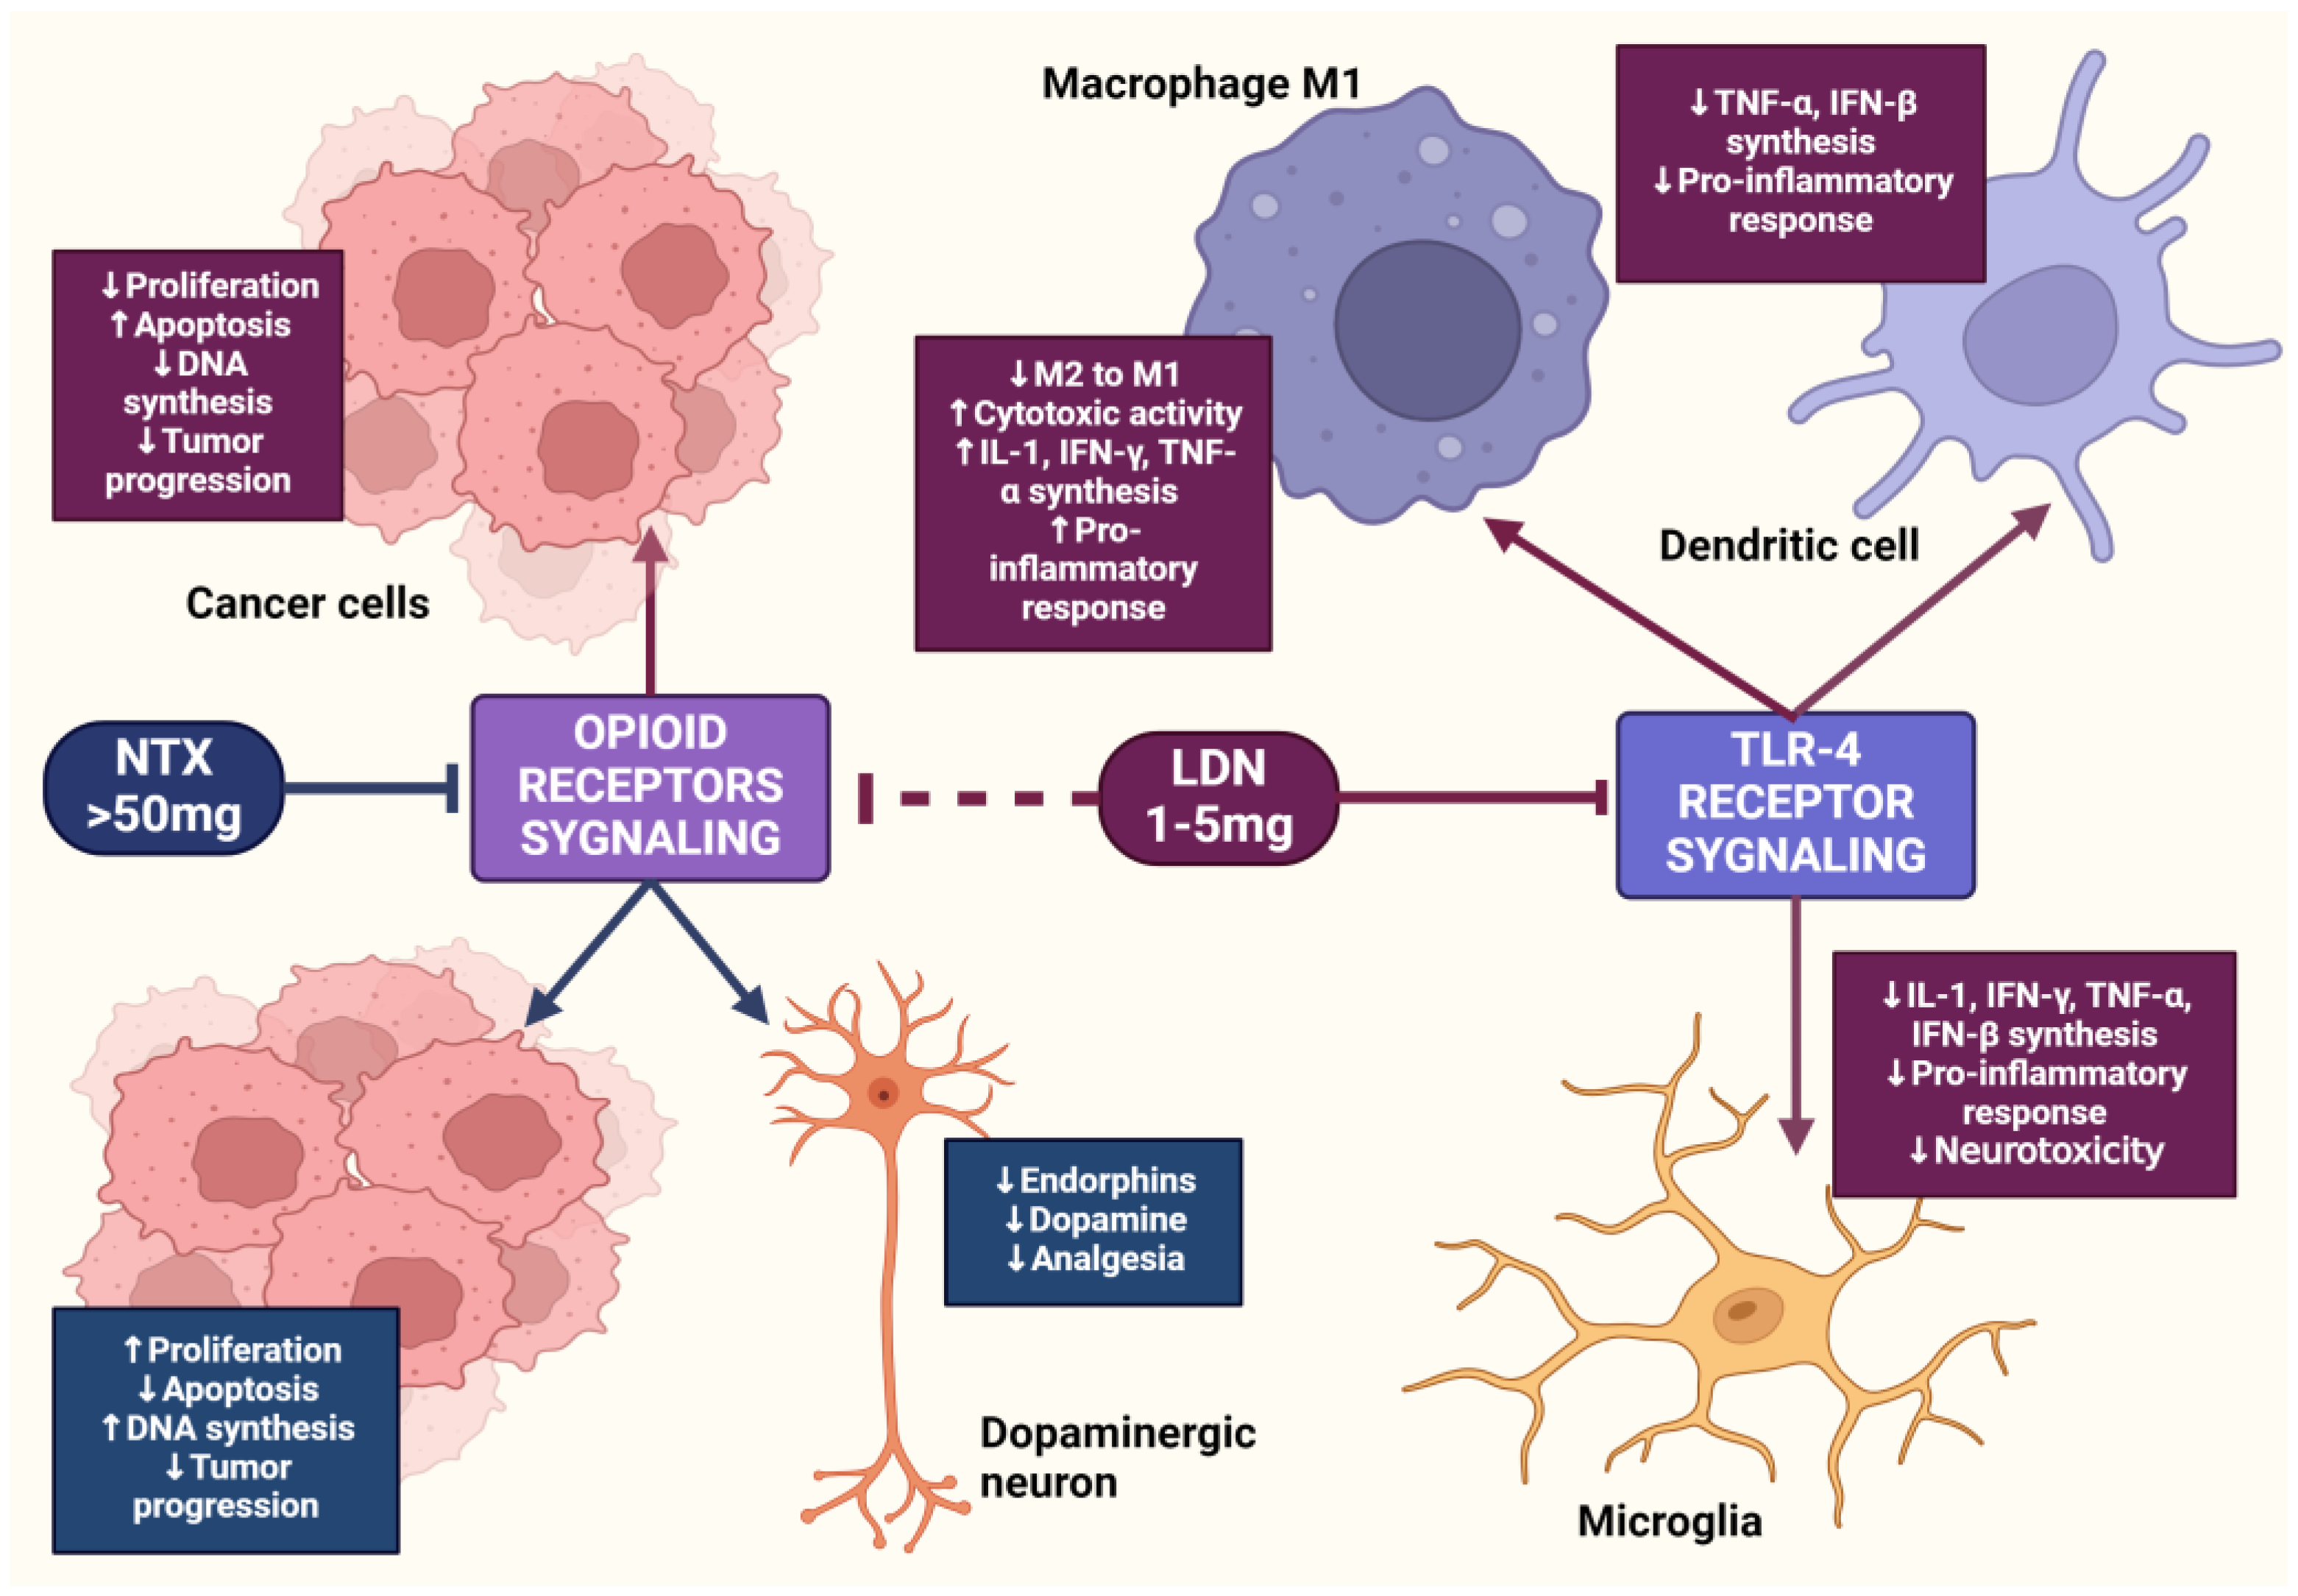
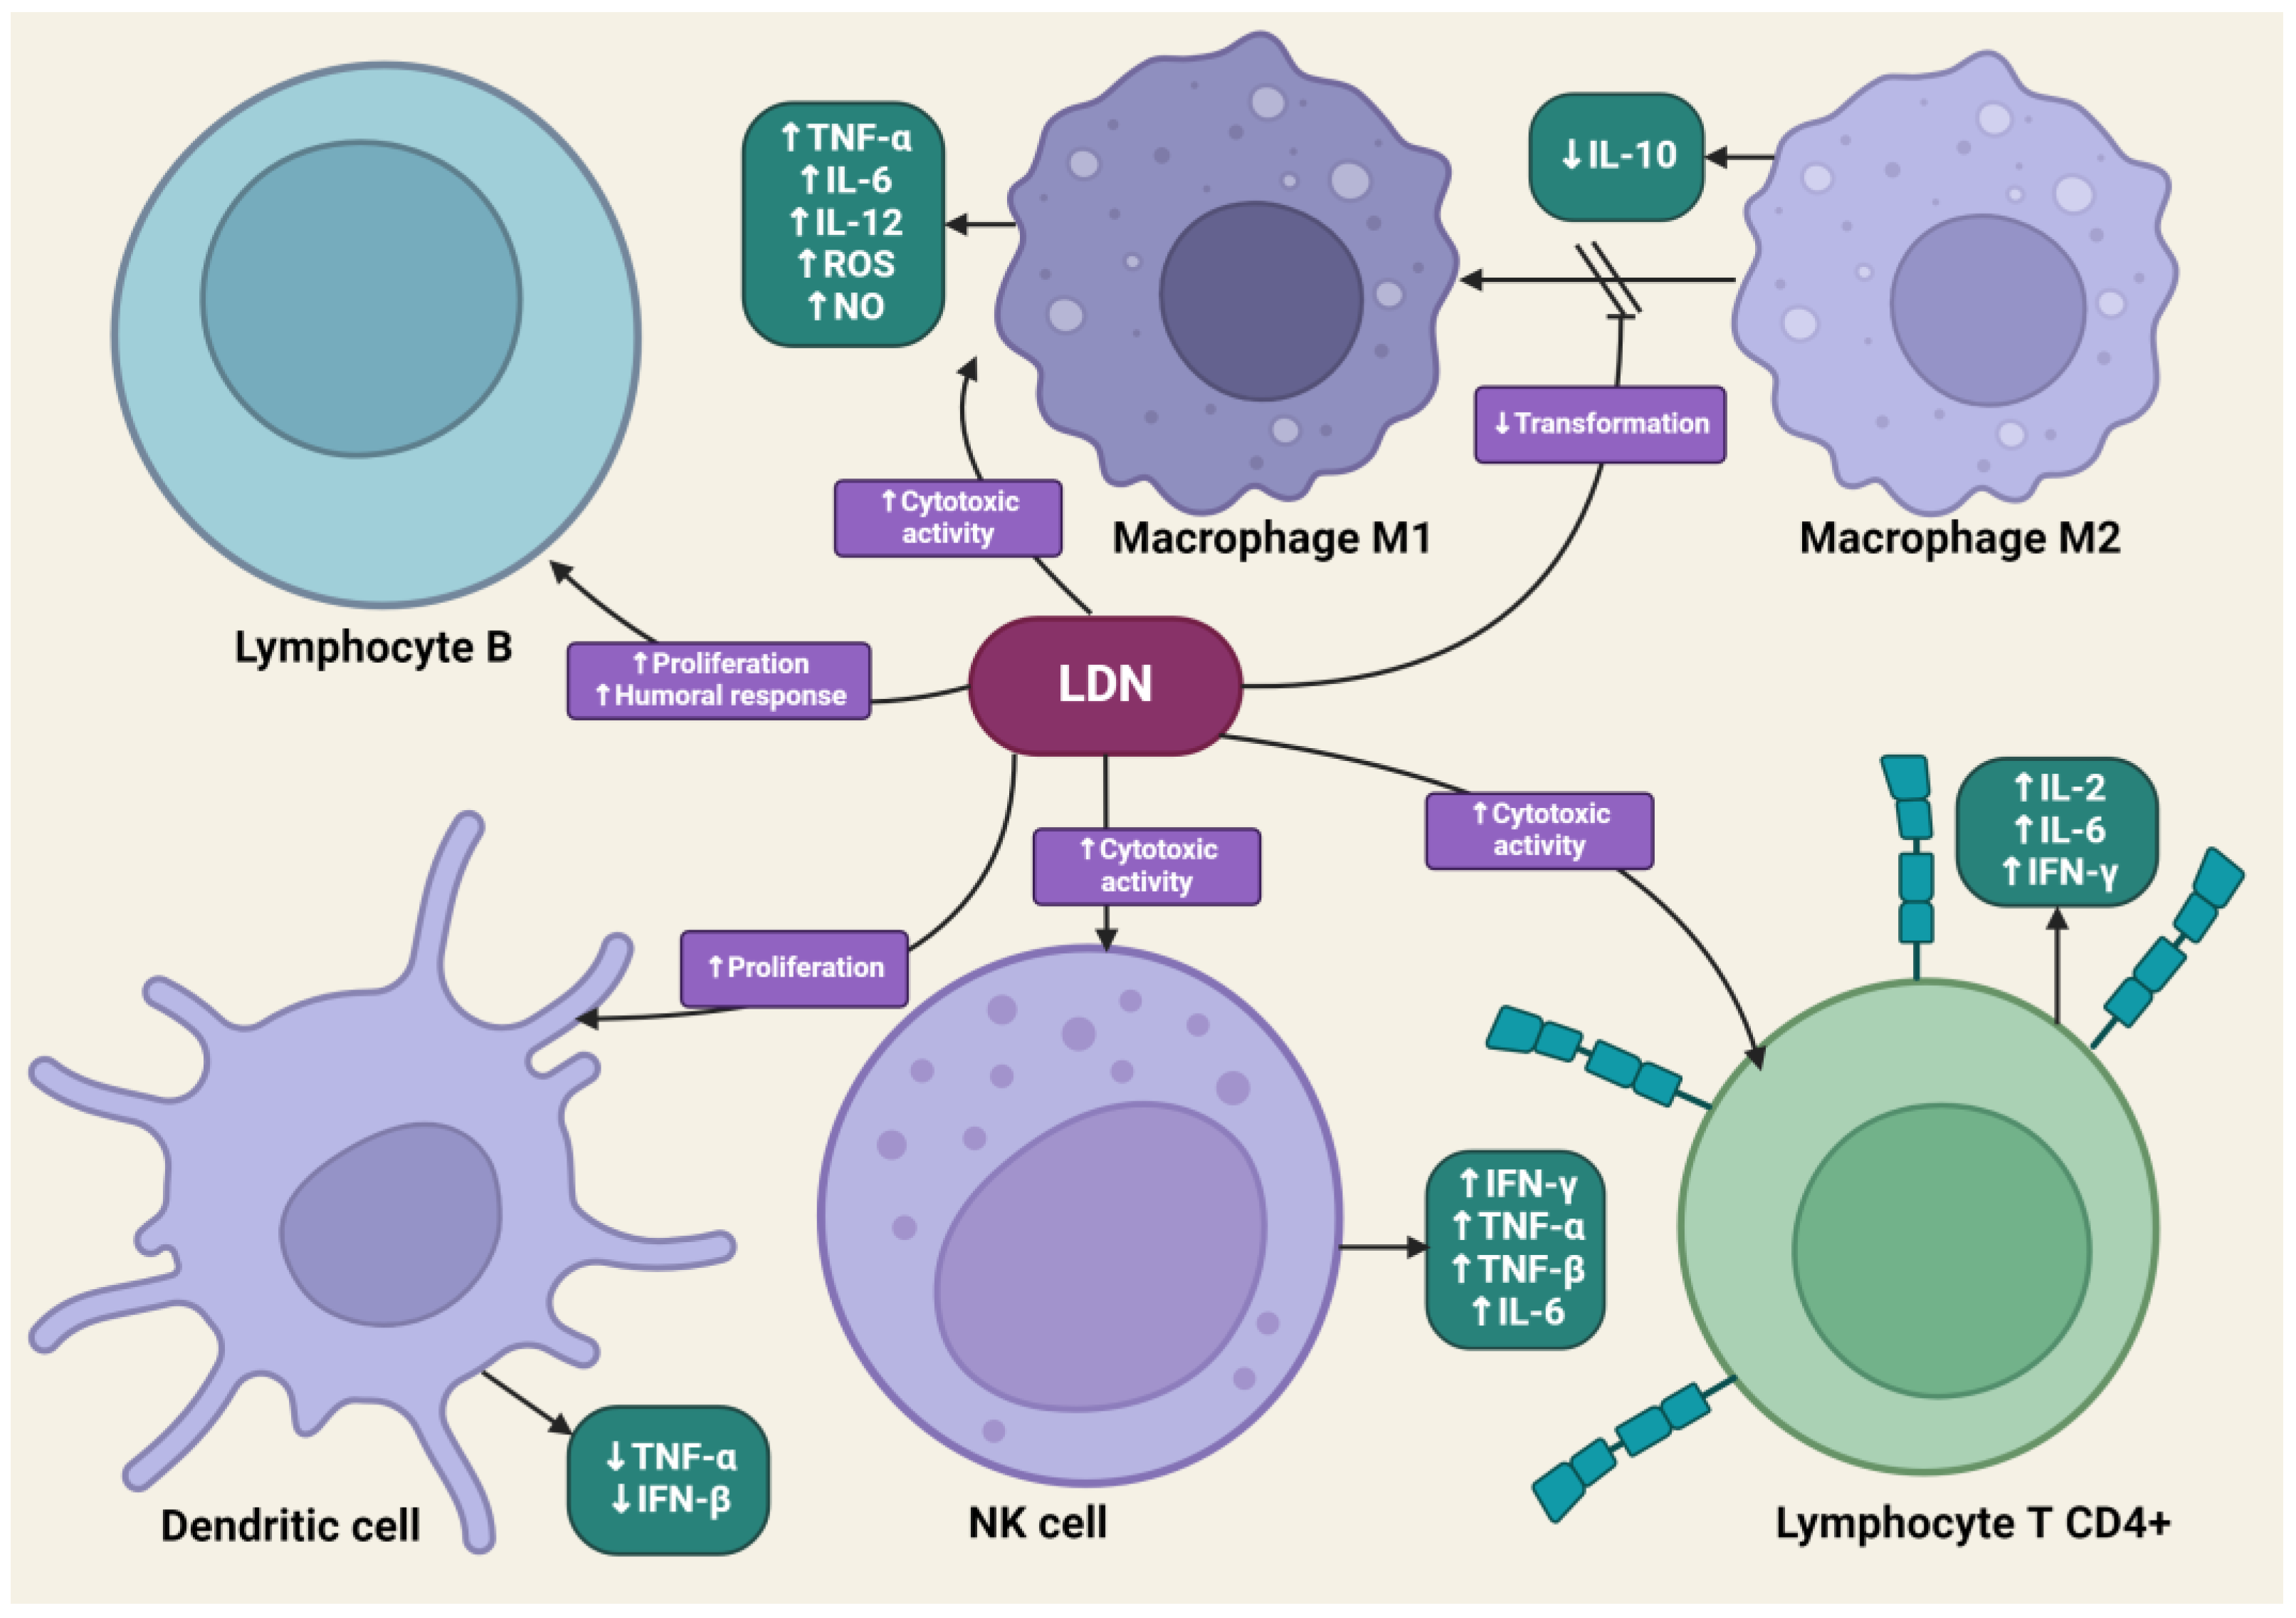
Naltrexone at standard doses — 50 mg for opioid dependence — blocks opioid receptors completely. At low doses, something different happens. The receptor blockade is transient. It lasts maybe four to six hours after ingestion, which is why timing matters more than most people realize. During that window, the body responds by upregulating endorphin production. Over time, this appears to modulate glial cell activity in the gut and reduce the inflammatory cascade that drives Crohn's flares. The microglial angle is where the science gets interesting. Your gut has immune cells that function similarly to brain microglia. When naltrexone briefly occupies the opioid receptor, those cells recalibrate. Less cytokine release. Less intestinal permeability. This isn't theoretical — you can actually measure it in serial fecal calprotectin levels. I've seen patients track their own calprotectin numbers while on LDN. One person went from 2,400 down to 380 over twelve weeks. Another saw no change at all. The variance is real and not fully explained yet.
The Protocol Most Doctors Will Give You
Start at 0.5 mg nightly. Increase by 0.5 mg every one to two weeks until you reach your target dose, usually between 1.5 mg and 4.5 mg. Take it on an empty stomach, ideally at bedtime, because the transient receptor blockade aligns with your body's overnight repair cycle. If you take it in the morning, the timing doesn't match the circadian pattern that seems to make it work. Compounding pharmacies handle LDN prescriptions. Not all of them are created equal. The suspension form tends to be more reliable than capsules because naltrexone hydrochloride doesn't dissolve well in standard capsule fill materials. I've had patients report inconsistent results after switching pharmacists, and the difference came down to bioavailability, not the dose number on the bottle.Get the Full Details
The titration schedule matters more than people expect. Go too fast and you'll get vivid dreams, insomnia, or a temporary flare. The body needs time to adjust its endorphin baseline. I've watched people skip the lower doses and hit 3 mg on day three, then wonder why they felt terrible for a week.
What It Actually Feels Like in Practice
The first thing you notice is the dreams. Loud, detailed, sometimes unsettling. They usually fade after two to three weeks. Then there's the energy shift. Some patients report a noticeable boost within the first month. Others feel nothing dramatic but notice slowly that they're not crashing after meals anymore. That subtle improvement — not having to plan your entire day around bathroom access — is what most people describe as the benefit.I personally encountered a problem with a patient who couldn't tolerate the REM disruption. Their sleep quality dropped to the point where fatigue was worse than the Crohn's symptoms. We split the dose — 0.75 mg at lunch and 0.75 mg at bedtime. It wasn't in any textbook, but it worked for that person. The total daily amount stayed the same, just spread out to reduce the peak concentration that triggers the sleep disturbance. That workaround isn't standard practice, but it's one of those things you learn from doing it enough times.
Pitfalls That Beginners Miss
Alcohol interacts with naltrexone. Even small amounts can blunt the effect or cause unexpected side effects. If you drink socially, tell your prescriber. Opioid pain medications are an absolute no — even low-dose codeine or tramadol will compete with naltrexone at the receptor site and undo whatever benefit you're getting. This sounds obvious until you're dealing with a dental procedure or an injury and someone hands you a prescription you didn't think about.Another issue is the lag time. People often stop after four or five weeks because they don't feel different. But the clinical data suggests meaningful improvement typically shows up between eight and sixteen weeks. Early weeks are mostly about tolerance adjustment, not therapeutic effect. Stopping before the window closes means you'll never know if it would have worked. The cost factor is worth mentioning. Compounded LDN runs anywhere from $20 to $80 per month depending on pharmacy and dosage. Insurance coverage is inconsistent — some plans cover the off-label use, most don't. If cost is a barrier, GoodRx coupons and pharmacy discount programs bring it down significantly, but you need to check each month because prices vary.
When It Won't Help
LDN is not going to reverse strictures or fistulas. It's not going to replace biologics in severe, steroid-dependent disease. The evidence supports its use in mild to moderate active Crohn's as either monotherapy or as an add-on to existing treatment. If you're in the hospital with a significant flare requiring IV steroids, LDN has no role in that acute setting. Pregnancy and LDN don't have clean safety data yet. If you're trying to conceive or are pregnant, talk to your doctor seriously before starting. The theoretical benefit to the mother doesn't come with a safety profile for the fetus. Some patients onLDN do experience transient worsening of symptoms during the first few weeks of titration. This is called a herxheimer-like reaction and it's thought to be related to the immune system recalibrating. It usually resolves within a week or two. If it doesn't, the dose is too high for now — drop back and climb slower.
The Numbers Behind It
The INCREMENT trial showed approximately 44% of LDN-treated patients achieved clinical remission at 12 weeks compared to about 29% on placebo. That's a relative improvement but the absolute difference is about 15 percentage points. Fecal calprotectin dropped by roughly 40% in the LDN group versus 20% in placebo. Endoscopic scores improved but not dramatically. These numbers matter because they set realistic expectations. LDN isn't a miracle drug. It's a tool that helps a meaningful subset of patients, and for some, the improvement is substantial enough to reduce or eliminate other medications. For others, it does nothing useful. There's no reliable way to predict who falls into which category before you try it.Bottom Line
If you have active Crohn's and conventional treatments aren't cutting it or are causing problems themselves, LDN is worth discussing with your gastroenterologist. The risk profile is favorable — the most common side effects are sleep disturbance and vivid dreams, both of which tend to pass. The real downside is the uncertainty. You won't know if it works for you without trying it for at least two months, and even then the answer isn't always clear. But for the people it helps, the improvement in quality of life is noticeable and often significant enough to change how they manage their condition long-term.