Getting LLLT right for nerve pain is less about the device and more about knowing what you're actually doing
I spent about three years working with diabetic neuropathy patients who kept coming back with the same complaint: their feet still burned after weeks of treatment. The problem wasn't the therapy itself. It was everything around it. Wavelength selection, dosage timing, skin temperature, and whether the person was wearing socks during the session. Small details that destroy results if you ignore them. The devices I used most often were 660nm red and 850nm infrared combo units. Some clinics used 905nm diodes. The difference matters more than most manufacturers will tell you. Red light handles surface-level inflammation and local circulation. Infrared penetrates deeper into the nerve tissue and connective structure. You need both for anything beyond mild cases.Low Level Light Therapy For Neuropathy
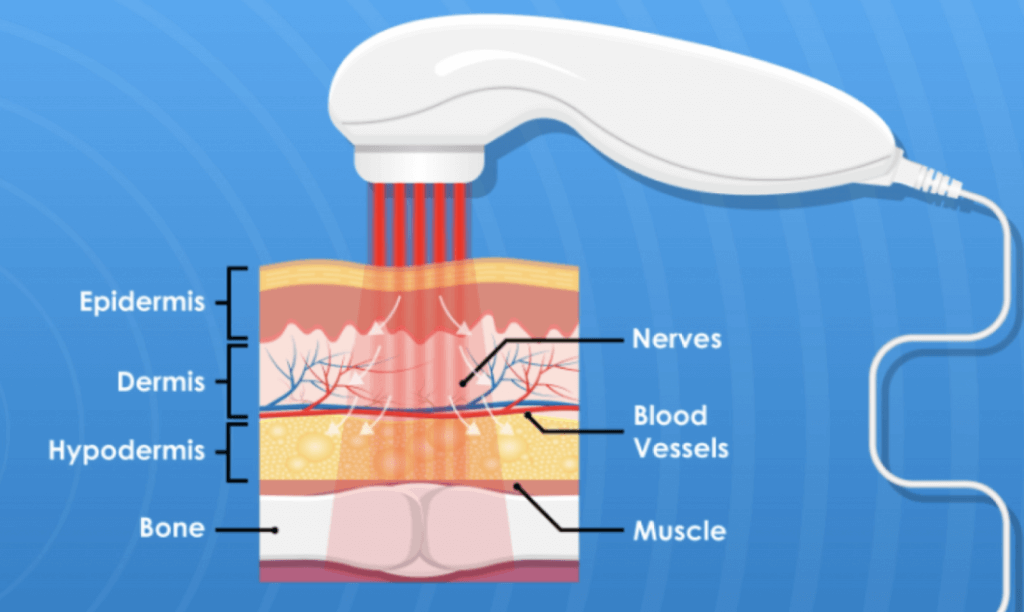
Here is how I set up a typical session. The patient sits or lies down with bare skin exposed at the treatment area. Not socks. Not padding. Bare shins and soles. I position the device about two inches from the skin. Two inches. Most people stand them too far away and then wonder why nothing happens. The irradiance drops off fast with distance. At two inches you are getting meaningful power density. At six inches you are wasting your time. I usually run sessions at 600 to 800 joules per point for the feet. That is roughly 20 minutes on a standard 300mW per diode unit. I do not push past 1000 joules because the biphasic dose response kicks in. Too much light and the therapeutic effect actually decreases. I learned that the hard way with a patient who had a vendor recommend an hour-long session. His symptoms got worse. We cut it down to 20 minutes and saw improvement within two weeks. Frequency matters too. Three times a week is the sweet spot for most people. Daily sessions can lead to tolerance buildup and diminishing returns. Every other day works as a minimum. Twice a week is acceptable but slows progress noticeably.
The thing nobody mentions is skin temperature. Cold feet respond poorly to LLLT. The mitochondria are less active at lower temperatures, so the same light dose does less work. I always have patients warm their feet in a bowl of water for five minutes before treatment, or I run the infrared diodes on a low setting for a couple minutes first to raise tissue temperature. It sounds minor. It makes a measurable difference in outcomes. Another overlooked factor is consistency of placement. Neuropathy is not always symmetric. One foot can be worse than the other. I treat each side separately and log the joules per side. If one foot needs more energy, I adjust. Using a preset timer on a cheap device and treating both feet identically is lazy and ineffective. I should also mention what does not work. LLLT will not help if the underlying cause is uncontrolled blood sugar. No amount of light therapy rebuilds damaged myelin if the glucose levels are staying above 200 mg/dL. The treatment supports nerve function and reduces inflammation, but it does not address the root metabolic problem. Patients who ignore their diabetes management while doing LLLT sessions are setting themselves up for disappointment. There is also a specific edge case I ran into repeatedly. Some patients with advanced neuropathy have reduced sensation to the point where they cannot feel heat. The device gets warm during operation. A patient with severe sensory loss might not notice if the unit is sitting too close and starting to raise skin temperature beyond a safe range. I developed a routine where I touch the skin between treatment spots with the back of my hand to check for warmth, and I instruct patients to report any tingling or heat sensation immediately. This happened once with a patient who had a mild burn on his heel from the device being placed one inch closer than recommended. He did not feel it happening. That is a real risk with this population. If you are considering this at home, the device category you are looking at is Class IIIb laser or LED arrays in the 600 to 900 nanometer range. Anything with a medical device clearance in that spectrum is fine. Cheap purple-light LED keychains sold on marketplaces are not medical devices and will not produce therapeutic effects. The wavelength and power output need to be verified. Some vendors list false specifications. I have seen a few patients get better results using a slightly different approach entirely. Instead of direct skin contact therapy, some vascular neuropathy cases respond better to intranasal photobiomodulation. That is a completely different protocol and device type. Worth knowing if foot treatment stalls after four weeks with no change. The timeline for seeing results varies. Mild cases show improvement in about two weeks. Moderate cases take four to six weeks. Severe cases with established nerve damage may show partial improvement but will not reverse completely. Setting realistic expectations upfront prevents patients from abandoning the treatment too early or chasing false hope indefinitely.