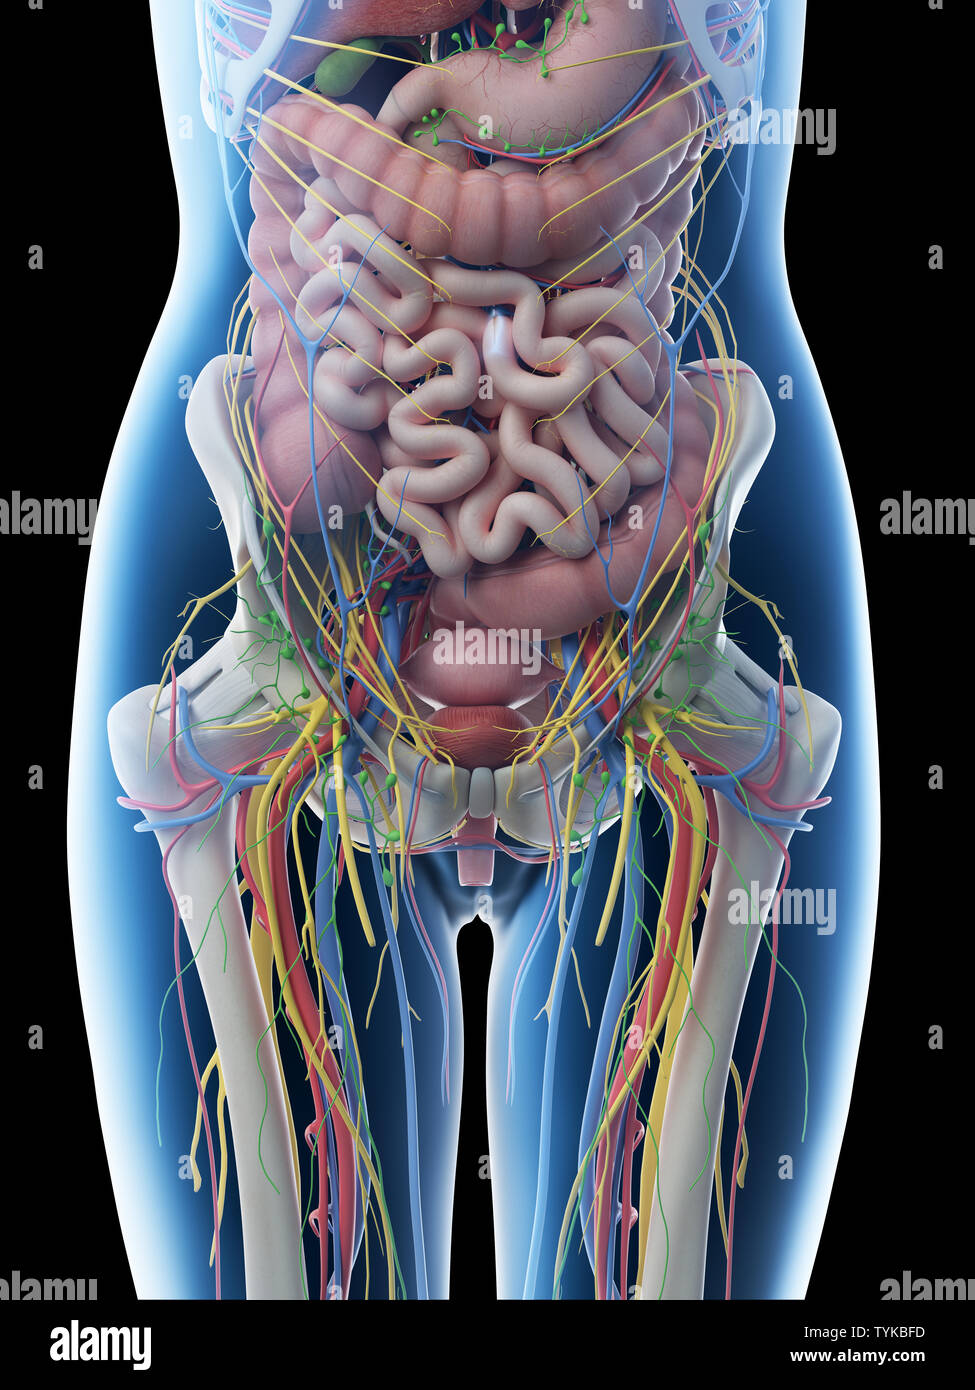
Lower Abdominal Anatomy Female
The lower abdomen isn't a single organ system. It's a cramped crossroads where the bowel, urinary tract, reproductive organs, and major blood vessels all sit within inches of each other. If you're studying this region for clinical purposes, dissection, or imaging interpretation, you need to understand spatial relationships, not just memorize labels. The pelvis compresses everything vertically and horizontally, and small anatomical variations change surgical approaches entirely. Start with the peritoneal cavity and what sits inside it. The uterus occupies the central pelvic space, positioned between the bladder anteriorly and the rectum posteriorly. It's held in place by ligaments, some of which are genuine connective tissue bands and others are just peritoneal folds that look important on diagrams but mean very little surgically. The round ligament, broad ligament, uterosacral ligament, and cardinal ligament are the ones that matter. The ovary sits laterally, suspended by the infundibulopelvic ligament containing the ovarian vessels. That's where the ovarian artery branches off the abdominal aorta just below the renal arteries, and where the ovarian vein drains differently on each side. Left goes to the left renal vein. Right goes directly to the inferior vena cava. That asymmetry matters for understanding spread of ovarian pathology. The fallopian tubes run from the uterine cornua laterally toward the ovaries but don't actually attach to them. The fimbriae hover near the ovarian surface. This gap is clinically relevant because ectopic pregnancy can implant in the tube, and ovarian follicles release eggs into the peritoneal space where the fimbriae sweep them into the tubal lumen.
Anterior to the uterus is the urinary bladder, sitting in the retropubic space. When distended, it rises above the pubic symphysis and can be accessed suprapubically without entering the peritoneal cavity. That's why suprapubic catheter placement works. Posterior to the uterus is the rectovesical pouch, also called the pouch of Douglas or rectouterine pouch. It's the most dependent part of the female peritoneal cavity when standing. Fluid, blood, or pus tracks there. That's also where transvaginal ultrasound probes sit for optimal visualization of the ovaries and uterus.
Walls and Support Structures
The anterior abdominal wall in the lower region consists of skin, subcutaneous tissue (Camper's and Scarpa's fascia), the rectus abdominis muscles enclosed in the rectus sheath, and the transversalis fascia before the peritoneum. The arcuate line marks where the posterior rectus sheath ends, usually around the level of the anterior superior iliac spine or slightly below. Below that line, all three aponeuroses pass anterior to the rectus muscle. That makes the wall thinner and more vulnerable to hernias. Spigelian hernias occur along the semilunar line at this level, and they're difficult to diagnose on physical exam because they push through the deep layer without creating an obvious bulge. The inguinal canals are another key landmark. In females, the round ligament passes through the deep inguinal ring, traverses the canal, and exits through the superficial ring into the labia majora. The canal itself contains the ilioinguinal nerve. Femoral hernias pass through the femoral canal below the inguinal ligament, and they're more common in females than males partly because of the wider pelvic anatomy. The ratio of femoral to inguinal hernias in women is roughly 2:1 compared to about 1:5 in men. The pelvic floor muscles, primarily the levator ani complex, form the muscular diaphragm of the pelvis. The pubococcygeus, puborectalis, and iliococcygeus support the pelvic viscera. Weakness here leads to prolapse. It's not dramatic in most cases until it is, and by then the patient has often normalized symptoms that could have been addressed earlier with targeted pelvic floor rehabilitation.
Get the Full Details
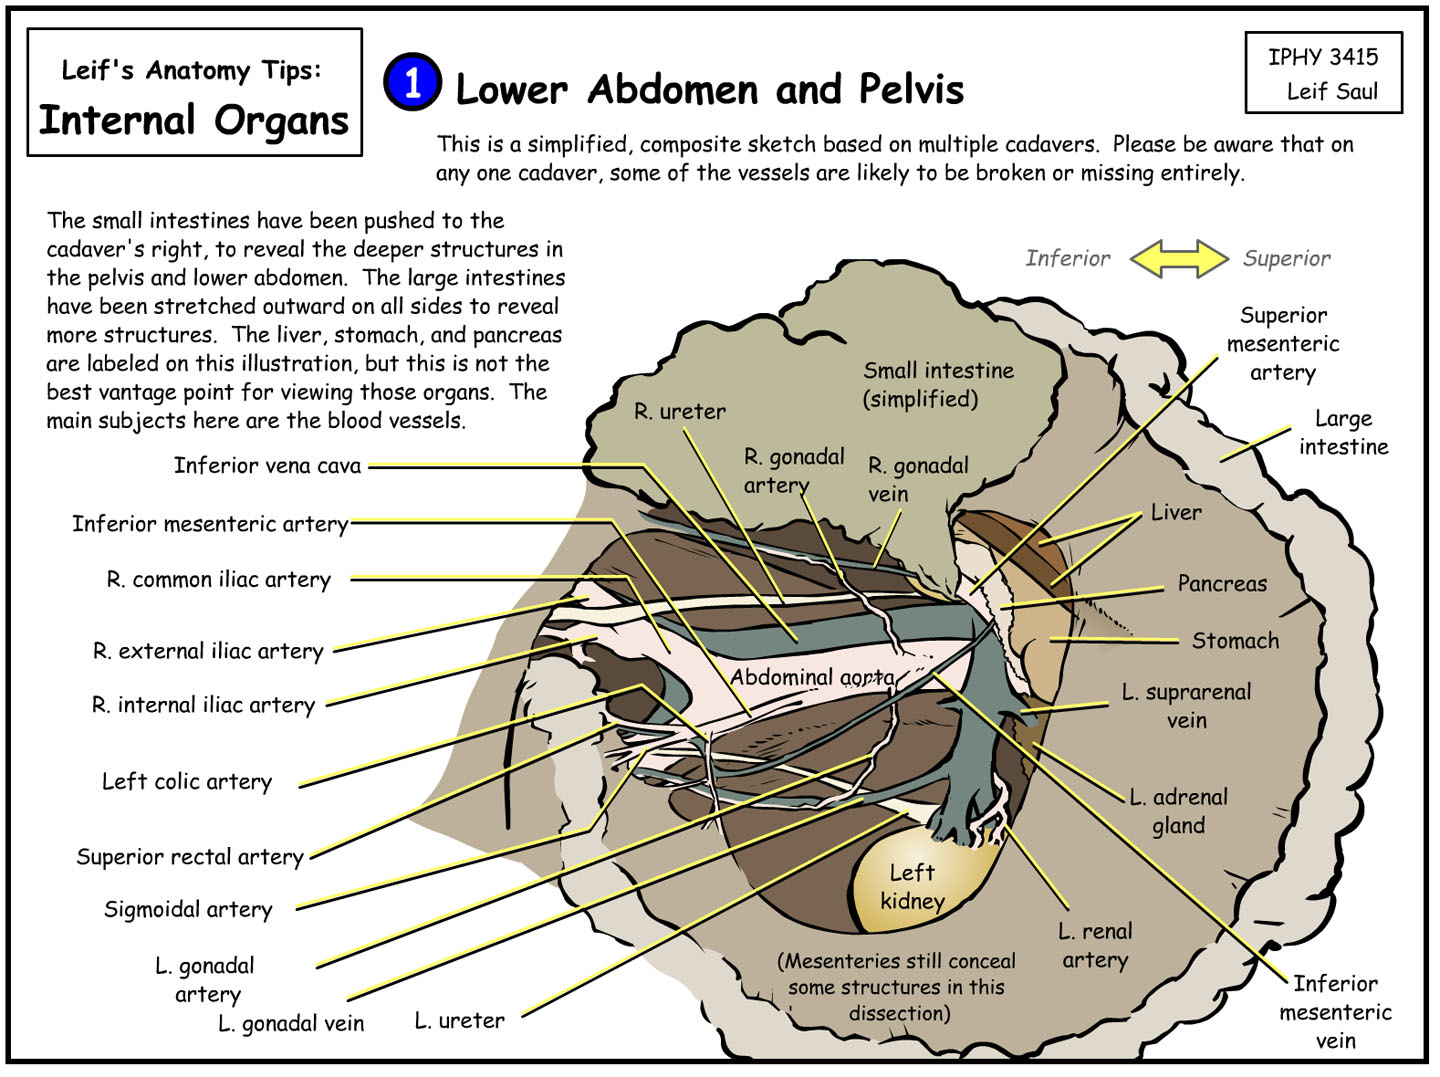
Blood Supply and Lymphatic Drainage
The uterus receives its blood from the uterine artery, a branch of the anterior division of the internal iliac artery. It runs medially through the base of the broad ligament, passing underneath the ureter about 1.5 centimeters lateral to the cervix. That relationship is why ureteral injury is a known complication during hysterectomy. Surgeons call it "water under the bridge," where the ureter is the water and the uterine artery is the bridge. Clamping the artery without identifying the ureter first is how injuries happen. The ovaries are supplied by the ovarian artery from the aorta and receive collateral flow from the ovarian branch of the uterine artery. Venous drainage follows the arterial pattern with the asymmetry I mentioned earlier. Lymph from the uterus drains to the external and internal iliac nodes, sacral nodes, and para-aortic nodes depending on the region. The fundus and tubes drain to para-aortic nodes via the ovarian vessels, which is why ovarian cancer commonly presents with retroperitoneal lymphadenopathy rather than pelvic node involvement alone.
A Specific Problem I've Dealt With
I once had a case involving a patient with chronic pelvic pain where standard imaging showed nothing. The pain was localized to the right lower quadrant, and appendicitis was initially suspected. After ruling that out, I mapped the anatomy carefully and identified a long, redundant sigmoid loop that was tracking into the right paracolic gutter. It was mimicking right-sided pathology. The workaround was a combination of positional maneuvers during examination and targeted MRI with the patient in both supine and left lateral decubitus positions to see how the bowel shifted. Static imaging had missed it because the loop settled back into the left lower quadrant when she was flat on the table. This isn't a rare finding, but it's easy to overlook when you're focused on the classic presentations. Another issue that comes up frequently is adnexal torsion in women with ovarian cysts. The suspensory ligament provides enough mobility for the ovary to twist on its pedicle, cutting off blood flow. The ovarian artery can keep the ovary perfused longer than you'd expect because of collateral circulation, but venous congestion causes swelling that makes untwisting difficult. I've seen cases where the ovary looked viable after detorsion but became necrotic 48 hours later because microvascular thrombosis had already occurred. The workaround is intraoperative Doppler assessment after detorsion and sometimes temporary fixation if viability is questionable.
Counter-Intuitive Points Beginners Miss
One thing that consistently trips people up is the relationship between the ureter and the cardinal ligament. On diagrams, the ureter looks like it passes underneath the uterine artery near the cervix. In practice, the distance varies significantly between individuals, and in some cases the ureter can be draped over the artery rather than beneath it. During pelvic surgery, assuming a fixed relationship is how you injure the ureter. Always identify it before clamping anything in that region. Another point: the bladder doesn't just sit in front of the uterus. The vesicouterine pouch of peritoneum reflects from the bladder onto the uterine body, creating a shallow depression. During a cesarean section, this pouch has to be dissected down to access the lower uterine segment. Bladder distension pushes the peritoneal reflection upward, giving more working space. That's why catheterization and gentle bladder filling are standard steps before incising the abdomen for a C-section. A third nuance is the clinical significance of the uterine venous plexus. It communicates with the vertebral venous plexus (Batson's plexus), which has no valves. That's one pathway by which endometrial cells can reach the vertebral column and cause metastatic disease in the spine, even without going through the lungs first. It's a rare route but well-documented in gynecologic oncology literature.
Practical Approaches to Studying This Region
If you're learning this anatomy, don't start with atlases. Start with cross-sectional imaging. Axial CT and MRI slices through the pelvis show you how these structures actually relate to each other in three dimensions. Coronal and sagittal views help too, but axial is where the spatial relationships become clear. The ureter crossing the bifurcation of the common iliac artery is easier to spot on axial cuts than on any diagram. Same with identifying the obturator nerve running along the lateral pelvic wall beside the internal iliac vessels. Transvaginal ultrasound should be on your list as well. It's the workhorse imaging modality for female pelvic anatomy and pathology. Learning to identify the uterus, endometrial stripe, ovaries, and surrounding structures in real time builds spatial understanding that static images don't provide. The probe position changes the anatomy on screen, and that's intentional. Tilting anteriorly brings the bladder into view. Tilting posteriorly visualizes the pouch of Douglas. Palpation is another skill that's often skipped in formal training. A bimanual pelvic exam teaches you about uterine position, adnexal masses, and tenderness patterns that no scan can fully replicate. The anterior fornix is where you palpate the cervix against the bladder. The posterior fornix gives access to the pouch of Douglas. Lateral fornices let you assess the parametrium. This is basic but essential, and it's declining in medical education despite being highly informative.
Limitations and Where This Knowledge Falls Short
Studying lower abdominal anatomy in females from textbooks has a fundamental limitation: most anatomical references are based on cadaveric dissection, which doesn't account for living tissue dynamics. Organs move. The bladder changes volume. The uterus shifts position with pregnancy, menopause, and uterine pathology. Ligaments stretch. Static anatomy books present a frozen version of a dynamic system. Imaging has its own blind spots. Ultrasound is operator-dependent. CT involves radiation and poor soft tissue contrast for pelvic organs. MRI is excellent but expensive and not always available in urgent settings. None of these modalities reliably show nerve pathways at the detail level needed for surgical planning. Intraoperative identification remains necessary. The biggest gap is in understanding individual variation. The standard anatomical descriptions cover the majority of cases, but a meaningful minority have atypical vessel courses, accessory ligaments, or organ positioning that don't match textbook diagrams. Surgeons who rely solely on anatomical references without developing intraoperative diagnostic skills will have complications. It's a known issue across specialties, not unique to gynecological anatomy.
Quick Reference for Common Clinical Correlations
Right lower quadrant pain: appendicitis, ovarian torsion, ruptured ovarian cyst, ectopic pregnancy, endometriosis, Mittelschmerz. The differential is broad because multiple structures occupy that space. Suprapubic pain with urinary symptoms: cystitis, interstitial cystitis, bladder tumor. The bladder is the first organ to consider with anterior lower abdominal pain and urinary changes. Dysmenorrhea with pelvic mass: endometrioma, fibroid, adenomyosis. Imaging usually clarifies, but clinical correlation with cycle timing is essential.

Pelvic pressure and bulge sensation: prolapse of the bladder (cystocele), uterus (procidentia), or rectum (rectocele). These reflect weakening of the pelvic floor support structures, often postpartum or postmenopausal. Referred shoulder tip pain with pelvic symptoms: hemoperitoneum from ruptured ectopic pregnancy. Blood irritating the diaphragm refers pain via the phrenic nerve to the C3-C5 dermatome in the shoulder. It's an emergency sign that shouldn't be missed.


