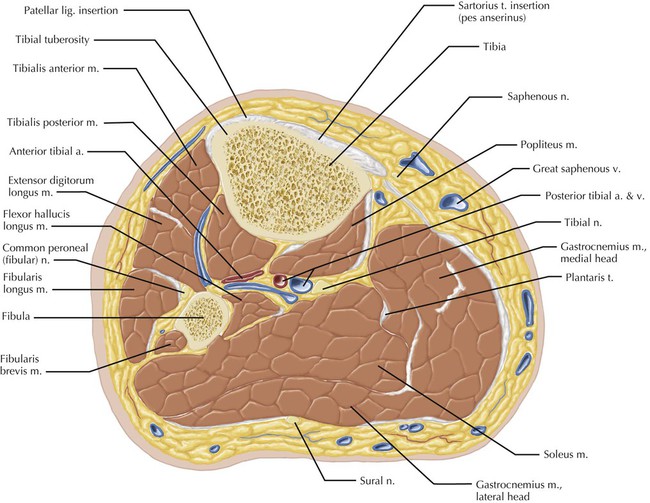
What You Actually See When You Slice the Lower Leg
Working with lower leg anatomy cross section images came up in my daily practice when I was mapping out surgical approaches for chronic exertional compartment syndrome. I spent hours poring over axial CT and MRI slices, trying to match clinical symptoms to specific structures. It's not glamorous work, but it teaches you something textbooks don't always convey clearly. The lower leg has three main compartments separated by the interosseous membrane and fascial septa. The anterior compartment sits between the tibia and fibula, packed with muscles responsible for dorsiflexion and toe extension. The lateral compartment houses the peroneal muscles that evert the foot. The posterior compartment splits into superficial and deep layers dealing with plantarflexion and toe flexion.
Reading a Lower Leg Anatomy Cross Section Like a Radiologist
I started with plain axial cuts at three levels: upper leg just below the knee, mid-shin, and lower leg above the ankle. Each level tells a completely different story. At the upper level, the tibia and fibula are close together. The anterior compartment muscles are well developed and clearly visible around the interosseous membrane. The peroneal vessels and deep peroneal nerve sit in that groove between the tibia and fibula where beginners often miss them. At the mid-shin level, the fibula becomes much smaller. The anterior compartment starts to look different because the muscles taper. The deep peroneal artery here is thin and easy to overlook on lower resolution scans. I learned this the hard way during a case where a surgeon was planning a vascular graft and nearly missed a compressed artery because he was looking at the wrong imaging slice. Always verify the exact anatomical level. A scan labeled "mid-leg" on the machine might actually be three centimeters higher or lower than where you think it is. Verify with bony landmarks before making any decisions based on it. Below the midpoint, the posterior compartment takes over visually. The gastrocnemius bellies merge into tendons. The soleus becomes the dominant muscle mass. The flexor hallucis longus runs along the fibula and can be confused with other structures if you aren't paying attention. I once saw a trainee misidentify the FHL as a ganglion cyst because it looked like a round structure next to the fibula on a single axial slice. You need multiplanar correlation to avoid that kind of mistake.
The key structures to track consistently are the neurovascular bundles. The posterior tibial neurovascular bundle runs behind the medial malleolus in a very specific space. If you're doing ultrasound-guided procedures in that area, knowing the exact cross-sectional anatomy saves time and prevents complications. I had a colleague who missed the posterior tibial vein on ultrasound because he was only looking for the artery. Both vessels sit in the same sheath. The vein is usually more superficial and posterior. Missing it during a central line approach in the leg is a real risk if you're not familiar with the layering. For learning this material, I recommend using CT angiography datasets rather than plain CT. The contrast makes the vascular structures immediately obvious and trains your eye to find them on non-contrast studies too. There are several free anatomical atlases online with downloadable DICOM datasets. Visible Body and Complete Anatomy are decent but paid. For free options, check out the National Institute of Biomedical Imaging and Bioengineering resources or the NCBI's Visible Human Project data. One thing nobody emphasizes enough: the interosseous membrane isn't just a flat sheet. It has fibers running in multiple directions and creates subtle compartments within the anterior and posterior spaces. When I was studying recurrent shin splints in runners, this detail mattered. Inflammation in the interosseous region shows up differently on MRI than periosteal irritation along the tibia. Getting the cross-sectional anatomy right meant I could distinguish between two conditions that present almost identically on casual inspection.
Get the Full Details

If you're building 3D models or doing computational simulations, the fascial planes are where most people mess up. The fascia between compartments isn't uniform thickness. It's thinner near the interosseous membrane and thickens around the bony prominences. I spent a week debugging a finite element model because I assumed uniform fascial thickness across the entire cross section. The model behaved completely unrealistically until I mapped the actual variations from histological data. For clinical reference, the cross-sectional areas of the major muscles change significantly from proximal to distal. The tibialis anterior is largest proximally and diminishes quickly. The soleus maintains its bulk longer. This matters for things like muscle flap design in reconstructive surgery. If you're planning a free muscle transfer, you need to know exactly where the vascular pedicle enters the muscle belly on cross section to avoid devascularizing the flap. I keep a printed set of axial lower leg cross sections from a standard anatomy atlas at my desk. Digital is convenient but the paper version doesn't lag, doesn't need power, and you can flip between levels in seconds while looking at a patient scan on screen. There's something about physical atlases that helps with spatial memory that screens just don't replicate.
The deep peroneal nerve at the ankle is another structure people get wrong. On cross section it's tiny, about 2 millimeters in diameter, sitting between the tibialis anterior and extensor digitorum longus tendons. Compressive neuropathy here from tight shoelaces is real and often missed. I've seen multiple cases where patients were told they had stress fractures when the actual problem was nerve compression visible on high-resolution ultrasound cross sections.
Practical Applications and Where This Knowledge Breaks Down
Using cross-sectional anatomy for injection guidance works well for the common peroneal nerve near the fibular head. You can visualize the nerve as a round hypoechoic structure on ultrasound and avoid the nearby peroneal artery. The accuracy rate is decent but operator dependent. If your needle approach isn't perfectly aligned with the axial plane, the nerve can disappear from view and you might inject into adjacent tissue instead. For fracture fixation planning, cross-sectional imaging of the distal tibia and fibula helps determine screw trajectories. The medullary canal shape varies considerably between individuals. What looks like a straightforward anterior approach on a standard lateral X-ray might actually require a more lateral trajectory when you see the actual cross-sectional canal geometry on CT. I've revised fixation plans based on cross-sectional CT findings that contradicted what plain radiographs suggested. One limitation worth noting: cross-sectional anatomy from cadaver studies doesn't always match living tissue. Edema, fat distribution, and muscle tone all change the appearance. A cross section from a thin cadaver will look very different from the same level in an obese patient. I had a resident get confused when his preoperative scans showed much more subcutaneous fat than the textbook cross sections he was referencing. Just remind him that real patients don't conform to idealized anatomy diagrams.

When studying lower leg anatomy cross section for exam preparation, focus on relationships rather than memorizing isolated structures. Know what sits next to what at each level. The bone-to-bone relationship changes as you move down the leg. The fibula moves from lateral to posterior relative to the tibia. This matters for surgical approaches and for understanding how injuries propagate through compartment boundaries. I still reference cross-sectional atlases regularly even after years of practice. New imaging techniques and enhanced resolution protocols keep revealing details I hadn't noticed before. There's always another layer of the lower leg you haven't fully internalized yet. The anatomy doesn't stop being interesting just because you've seen it a hundred times already.