Why Your Calf Keeps Recurring Issues
I spent about eight years working with athletes who complained about the same calf problem season after season. They'd do stretches, get massage, come back worse. The issue was almost never the muscle belly itself. It was where the anatomy doesn't make sense on a diagram. Understanding Lower Leg Muscle Anatomy properly means you stop treating the leg as a single unit and start seeing the compartments, the aponeuroses, and the transition zones where injuries actually hide. Most people learn the names from a textbook. Very few of them can tell you why a gastrocnemius strain at the musculotendinous junction takes twelve weeks to heal while a soleus strain of the same grade only takes six.
Lower Leg Muscle Anatomy
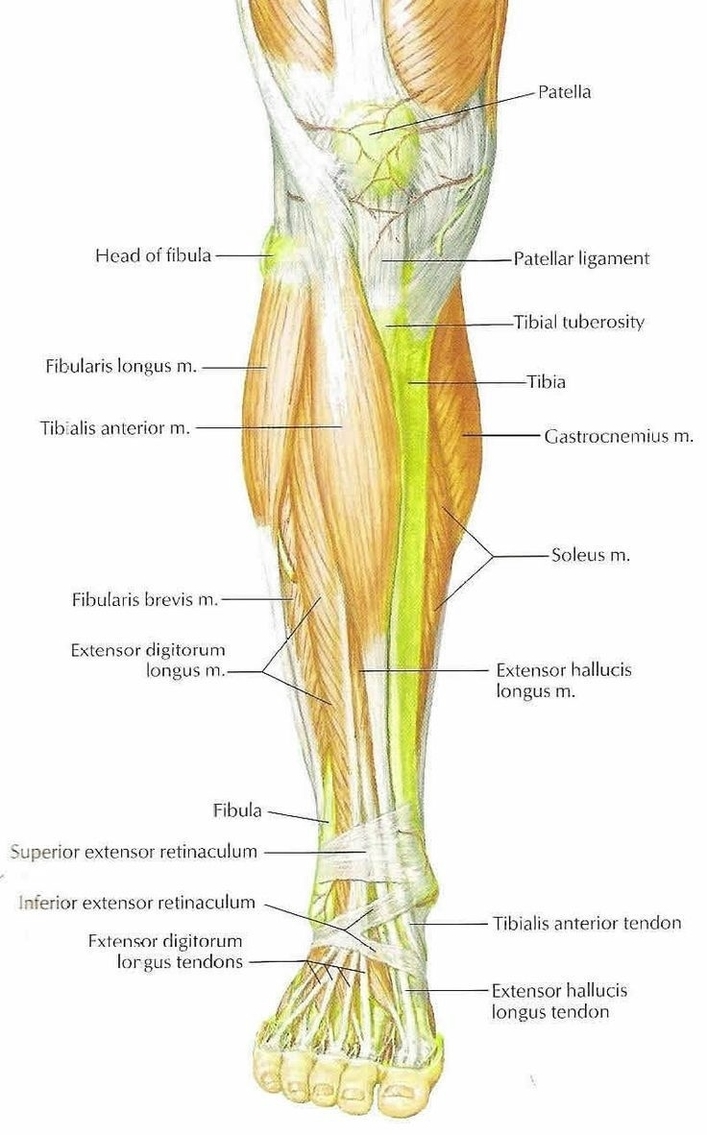
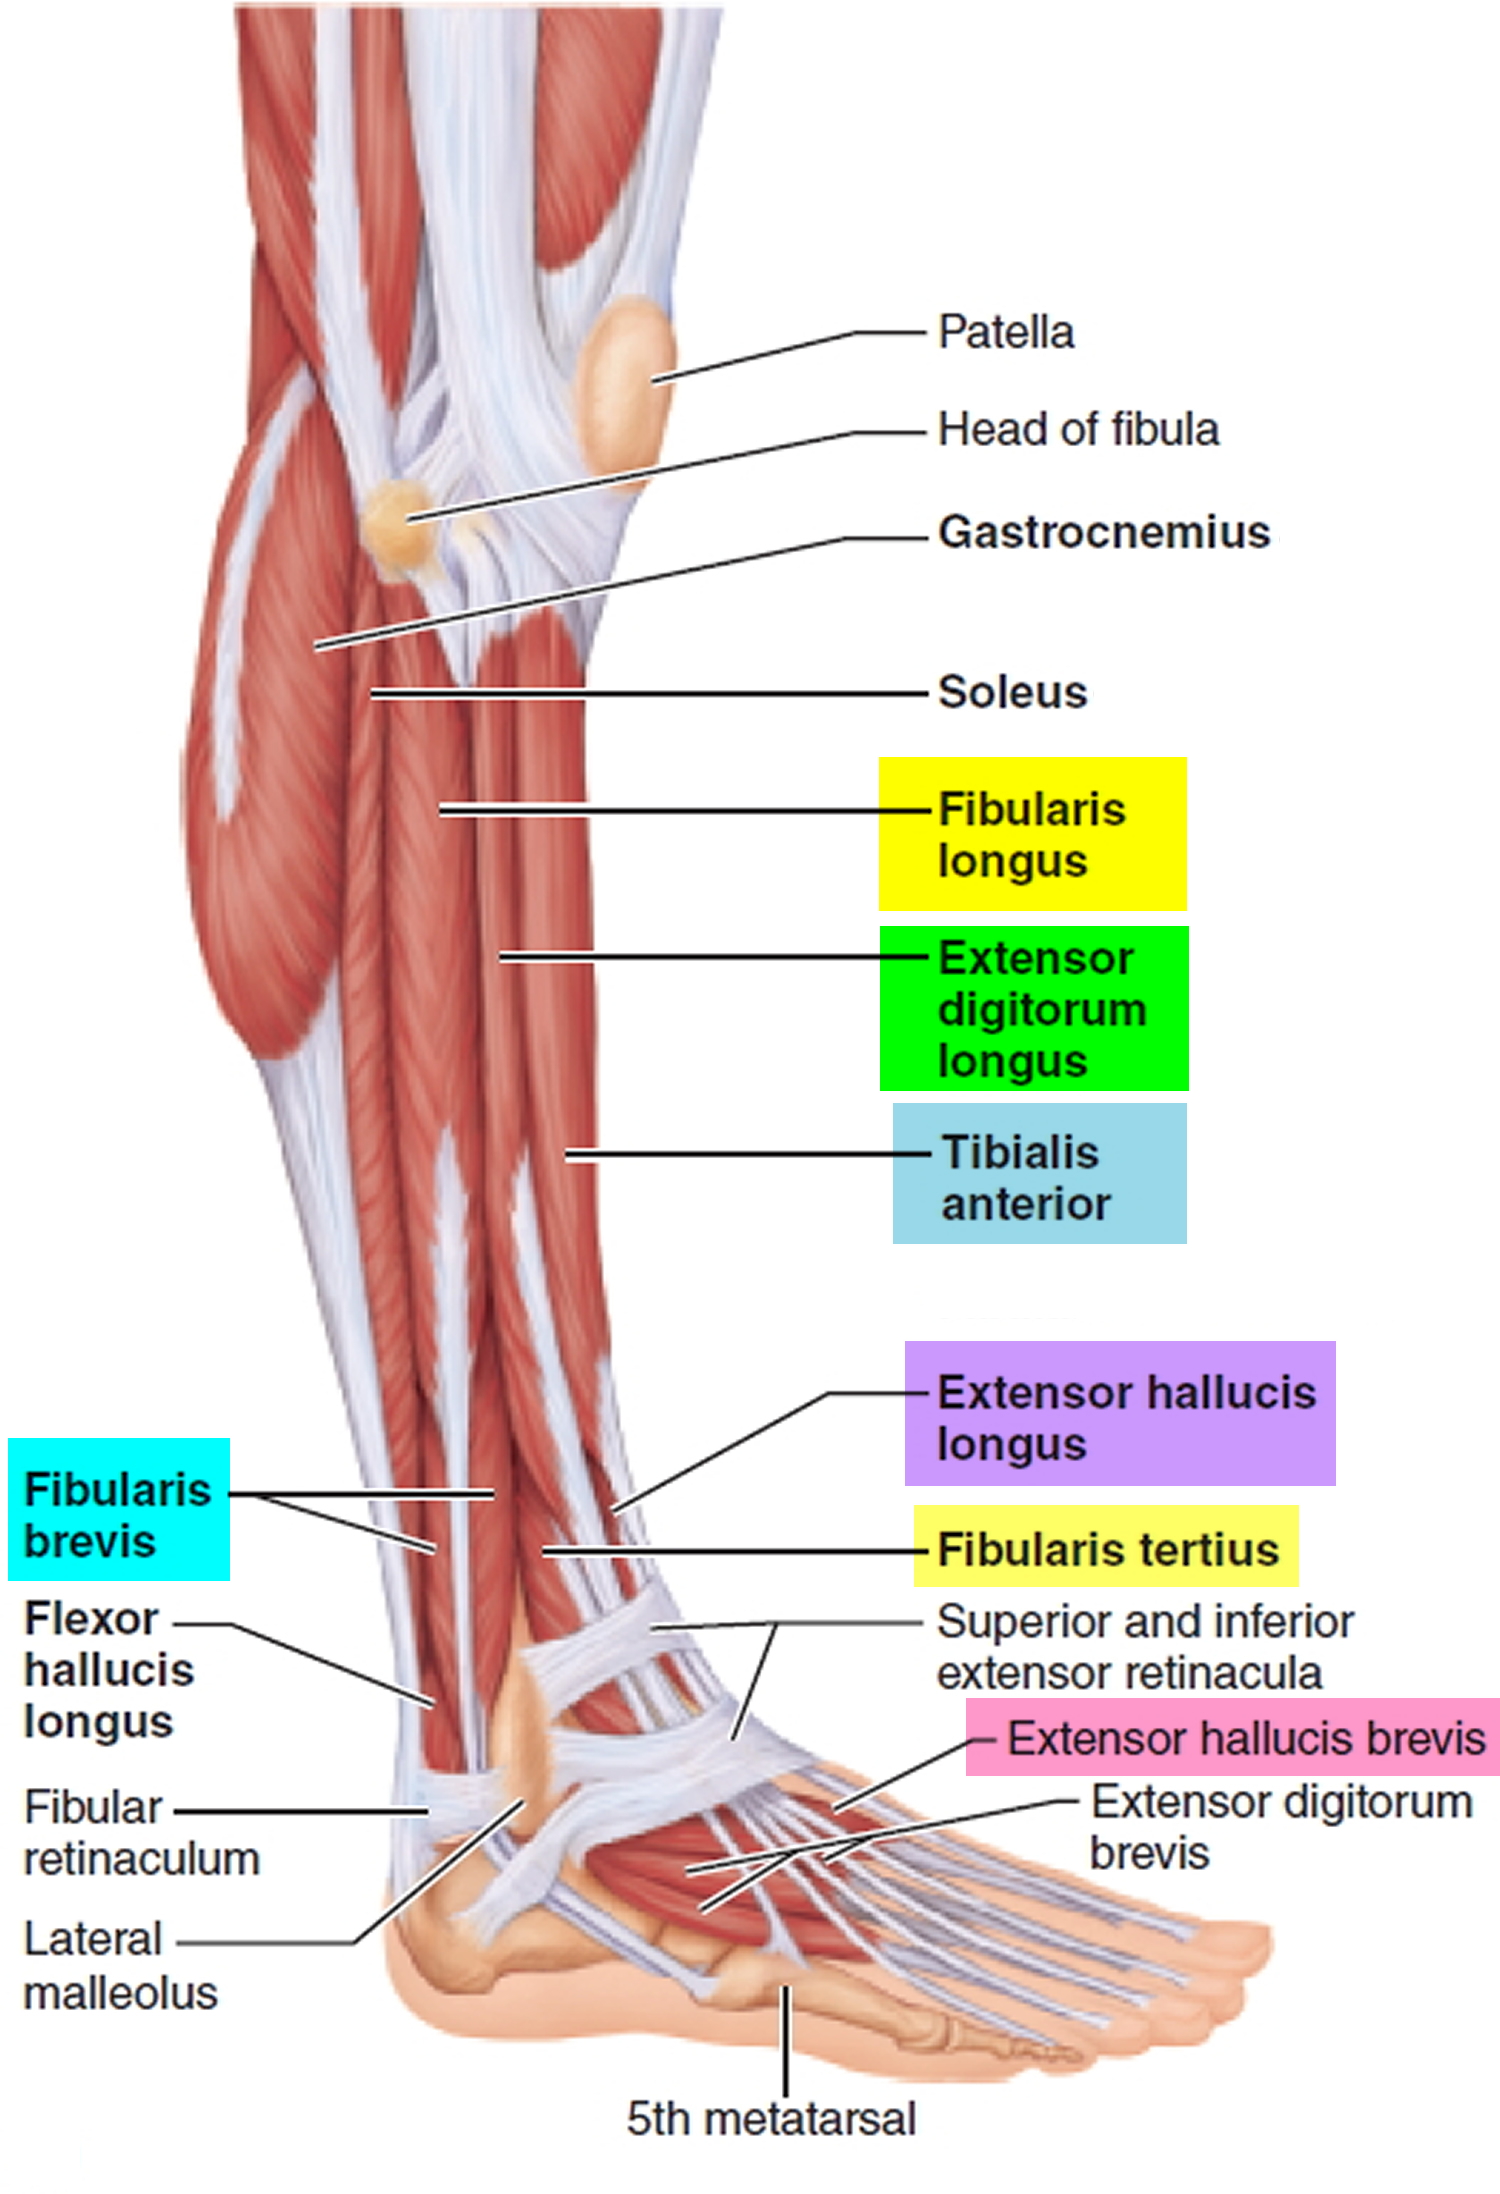
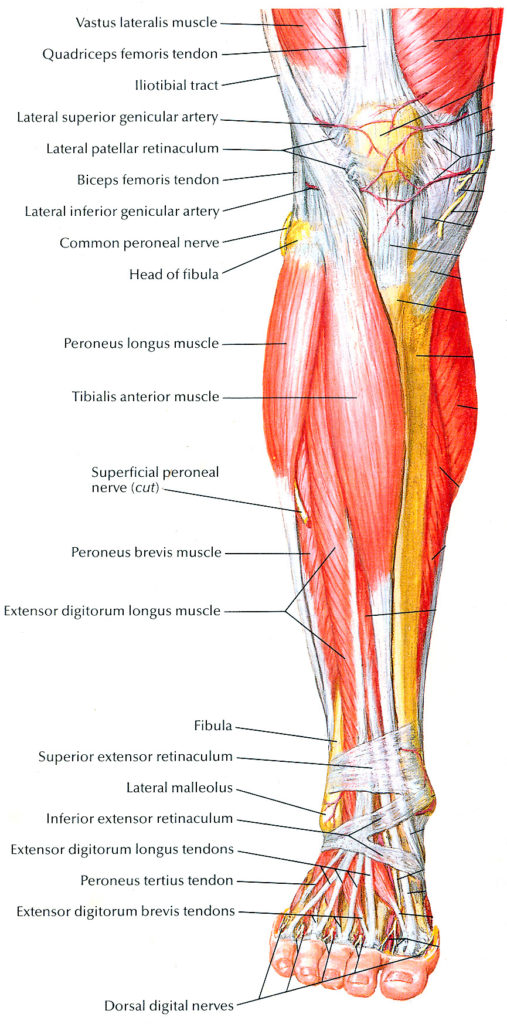
The lower leg is divided into three compartments: anterior, lateral, and posterior. Each has its own fascia, nerve supply, and clinical significance. The posterior compartment is further split into superficial and deep layers by the transverse intermuscular septum. This isn't academic detail. It determines everything about how injuries present and how they should be managed. The superficial posterior compartment contains the gastrocnemius, soleus, and plantaris. The gastrocnemius has two heads — medial and lateral — that originate from the femoral condyles. This matters because it means the gastrocnemius is BiArticular. It crosses both the knee and the ankle. When the knee is extended, the muscle is already lengthened. That changes the stress distribution during stretching or sprinting. The soleus originates from the posterior tibia and fibula. It's a pure ankle plantar flexor. It's also nearly all type I slow-twitch fibers, roughly 80 percent in most people. That's why soleus injuries feel different. They're more of a chronic, nagging thing rather than the acute tear sensation people describe with gastrocnemius injuries.
The plantaris is the outlier. Small, weak, useless for most functional purposes. But it causes problems anyway. Plantaris tendinitis or a ruptured plantaris can mimic a tennis leg injury — that sudden pop behind the medial calf. I've seen two cases where surgeons thought they were dealing with a gastrocnemius rupture and ended up removing the plantaris instead. It happens because the plantaris runs right between the gastrocnemius and soleus and its tendon can fray in a way that looks identical on MRI. The anterior compartment contains the tibialis anterior, extensor digitorum longus, extensor hallucis longus, and peroneus tertius. These are innervated by the deep peroneal nerve. This compartment is where you see compartment syndrome most often after trauma. The fascia here is tight and non-expandable. Swelling has nowhere to go. The lateral compartment houses the peroneus longus and peroneus brevis. They evert the foot and assist with plantar flexion. Peroneal tendinopathy is incredibly common in runners and people who walk on uneven terrain. The peroneus brevis passes behind the lateral malleolus in its own fibro-osseous tunnel. When that tunnel narrows — from a bone spur, a hypertrophied muscle, or scar tissue — the tendon gets compressed. This is often misdiagnosed as general ankle pain for months.
Get the Full Details

The Transition Zone Problem
Here's what textbooks rarely emphasize: the musculotendinous junction of the gastrocnemius is the single most common site for strains in the entire lower leg. It's located approximately two to three centimeters distal to the knee joint line on the medial side. This is the "tennis leg" zone. Most people don't know this because they're learning from diagrams that show clean lines between muscle and tendon. In reality, the transition is gradual and messy. I had a client — a competitive tennis player — who kept tearing his medial gastrocnemius. Same spot, same mechanism every time. He'd push off for a forehand, knee slightly bent, and feel a sharp pain. We spent months trying different rehab protocols. Nothing worked. The breakthrough came when we stopped treating it as a calf problem and started looking at the fascial connections. The deep posterior fascia connects the gastrocnemius to the soleus through the intermuscular septum. When the soleus was tight from excessive standing and walking, it pulled on that septum and altered the glide path of the gastrocnemius during push-off. The muscle was being strained not because it was weak, but because its sliding surface was compromised. The workaround was specific and somewhat counterintuitive. We did aggressive soleus release using a compression ball against a wall — not the gastrocnemius. Hold for sixty seconds, move the ankle through dorsiflexion and plantar flexion during each hold. We did this twice daily for three weeks. Then we added eccentric calf raises with the knee bent at 90 degrees to specifically load the soleus. The gastrocnemius strains stopped completely. Not because we strengthened the gastrocnemius, but because we freed up the system it slides against.
Nerve Supply and Why It Matters
The tibial nerve supplies the entire posterior compartment. It enters through the adductor hiatus and travels down behind the tibia. The deep peroneal nerve supplies the anterior compartment. The superficial peroneal nerve supplies the lateral compartment. These aren't just labels for a test. They determine how nerve compression presents. Tibial nerve entrapment at the level of the flexor retinaculum — tarsal tunnel syndrome — causes burning pain along the sole of the foot. But early on, patients often describe it as calf pain. I once spent six weeks trying to rehab someone's "calf strain" before a neurologist pointed out the tingling in the big toe. The problem was in the ankle, not the leg. The nerve was being compressed under the flexor retinaculum by a ganglion cyst. Simple surgical decompression resolved it in two weeks. Deep peroneal nerve compression can happen at the ankle where the nerve passes under the extensor retinaculum. This causes weakness in toe extension and numbness between the first and second toes. It's occasionally seen in people who wear tight boots or have significant anterior compartment swelling after exercise. The weakness in toe extension is the key indicator. If someone can't lift their big toe against resistance but has full ankle dorsif flexion strength, think nerve, not muscle.
Blood Supply and Healing Implications
The posterior compartment receives blood primarily from the posterior tibial artery and the peroneal artery. The musculotendinous junctions are watershed zones — areas where blood supply is naturally thinner. This is why strains at these junctions take longer to heal than mid-belly strains. The tissue has less vascularization to support repair. Grade 1 strains at the junction might seem minor but can take four to six weeks because the healing tissue is forming in a relatively avascular environment. The soleus has a better blood supply than the gastrocnemius because it's closer to the major vessels running alongside the tibia. This is another reason soleus injuries heal faster. It's also why I recommend Soleus-focused rehab for people with recurrent calf issues. Eccentric calf raises with a bent knee target the soleus directly and improve its tendon compliance without overstressing the more vulnerable gastrocnemius junction.

Practical Assessment You Can Do
If you're trying to understand your own Lower Leg Muscle Anatomy beyond memorizing names, the most useful thing you can do is palpate the boundaries. Stand barefoot. Flex your knee and contract your calf. You'll feel the two distinct bellies of the gastrocnemius — the medial head is larger and more prominent. The soleus is deeper and wider, visible as the broad area below and behind the gastrocnemius when you point your toes. Run your fingers along the lateral side of the lower leg. About midway between the knee and ankle, you'll feel the peroneal tendons behind the lateral malleolus. They should move smoothly under your fingers. If they catch or click, that's tenosynovitis and needs attention before it becomes a chronic issue. On the front of the leg, lift your big toe. The tendon that rises under your skin along the outer edge of the shin is the tibialis anterior. The one further toward the middle is the extensor digitorum longus. Weakness here causes foot drop and is a sign of deep peroneal nerve involvement, not muscle fatigue.
Common Mistakes People Make
Stretching the gastrocnemius with a straight knee when the problem originated in the soleus. This is the most frequent error I see. The two muscles have different fiber orientations and different attachments. A straight-knee calf stretch primarily targets the gastrocnemius. A bent-knee stretch isolates the soleus. If you're constantly doing the wrong stretch, you're not addressing the actual problem and may even be aggravating it by overloading the already tight structure. Ignoring the plantaris entirely. It's tiny, but it causes disproportionate trouble. I've had three clients with recurrent "calf tears" who turned out to have plantaris issues. The muscle can hypertrophy abnormally or develop fibrotic nodules that pull on the surrounding fascia. Palpation between the gastrocnemius and soleus along the medial border can reveal thickening or tenderness that points to the plantaris as the culprit rather than the larger muscles around it. Treating all calf pain the same way. Anterior leg pain from tibialis anterior issues is completely different from posterior calf pain. Lateral leg pain from peroneal involvement is yet another category. Knowing which compartment the problem sits in determines whether you need rest, specific strengthening, nerve gliding exercises, or imaging to rule out structural issues.
When to Stop Self-Managing
If you've done four to six weeks of appropriate rehab with no improvement, get imaging. Ultrasound is usually sufficient for muscle and tendon issues. MRI is better for evaluating the compartment structures and nerve pathways. Blood flow studies may be needed if vascular compromise is suspected. Acute injuries with a audible pop, immediate swelling, and loss of function need medical evaluation within 24 hours. These are often complete tears or ruptures that won't heal properly without intervention. A Grade 3 gastrocnemius rupture, for example, may require surgical repair if the gap is larger than two centimeters. Delaying evaluation beyond the first week makes surgical outcomes less predictable. Recurring injuries in the exact same location indicate a structural or biomechanical issue that won't resolve with rest alone. The fascial adhesion, the nerve entrapment, the compartment tightness — these are persistent problems that need targeted treatment, not just more time off from activity.